Thoracic / Lung
Studies from before MRI surveillance favored PCI (fewer brain mets, improved OS); MAVERICK asks whether that still holds now that MRI brain surveillance is routine.
SWOG S1827/MAVERICK
ForLS or ES SCLC, responding after platinum ± IO, no brain mets on MRI, PS 0-2
TL;DRRandomized phase III, LS or ES SCLC: PCI 25 Gy/10 fx + MRI vs MRI surveillance alone; no CFFS or OS results in source tweets.
The RT question is PCI omission, not RT omission: the surveillance arm still gets RT at brain mets (SRS, WBRT or HA-WBRT at discretion), so CFFS pits upfront 25 Gy/10 fx PCI against deferred salvage. HA-PCI was also discretionary, diluting any hippocampal-sparing read. No CFFS or OS result in source tweets.
CFFS compares upfront PCI 25 Gy/10 fx against salvage RT at detection, with SRS, WBRT or HA-WBRT left to discretion. Discretionary HA-PCI means the PCI arm mixes techniques, so a cognitive result will not isolate hippocampal sparing. No results in source tweets.
Immunotherapy was allowed (concurrent and/or adjuvant) and stratified, so the trial tests PCI in the chemo-IO era for both LS and ES. Entry required response to platinum without progression and enrollment within 16 weeks of the last cycle, which defines the surveillance pathway being tested. No results in source tweets.
9 details 4 trials watching
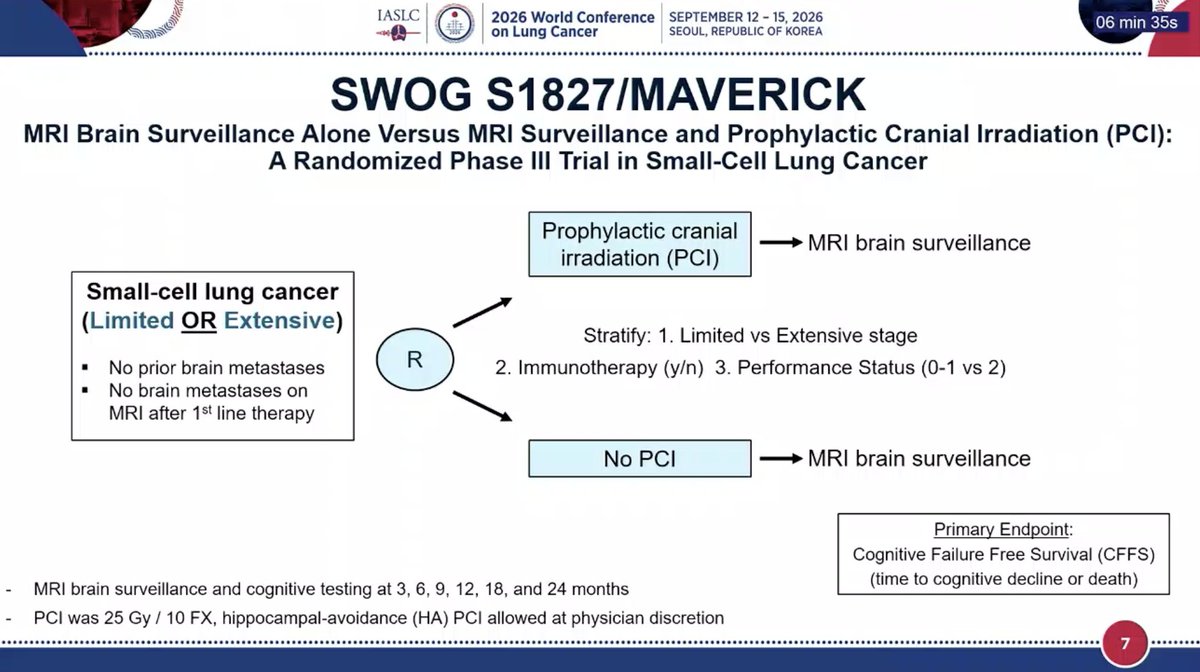
Randomized phase III, PCI + MRI brain surveillance vs MRI surveillance alone. Stratified by LS vs ES stage, immunotherapy (y/n) and PS 0-1 vs 2. N and follow-up not reported in source tweets.
LS or ES SCLC, ≥18y, PS 0-2. LS pts completed platinum chemo plus definitive thoracic RT or resection; ES pts completed platinum chemo; immunotherapy allowed. Required response to upfront therapy, no brain mets on MRI within 28 days, enrollment within 16 weeks of last chemo cycle.
PCI 25 Gy/10 fx, with HA-PCI allowed at physician discretion. RT recommended at detection of brain mets, with SRS, WBRT or HA-WBRT at physician discretion.
Primary: cognitive failure free survival (time to cognitive decline or death). Hypothesis: MRI surveillance alone gives superior CFFS without a decline in OS. MRI and cognitive testing at 3, 6, 9, 12, 18 and 24 mo.
No CFFS, OS or brain-met incidence results reported in source tweets.
Per the presenting tweet, pre-MRI-surveillance studies showed fewer brain mets and improved OS with PCI, the basis for PCI as standard. MAVERICK tests that against a modern MRI surveillance plus salvage RT pathway, the question also addressed by the Japanese ES-SCLC phase III (Takahashi) and EORTC PRIMALung.
Discretionary HA-PCI blends techniques in the PCI arm, and discretionary salvage modality (SRS vs WBRT vs HA-WBRT) makes the surveillance arm's cognitive cost practice-dependent. Source does not state how OS non-decline is formally tested.
The trial reframes PCI as a cognitive trade-off rather than a brain-met prevention question, with CFFS as the primary. Whatever the result, it will not separate standard PCI from HA-PCI or define the best salvage modality.
Source tweets carry design, eligibility and hypothesis slides only; no CFFS or OS result, so the PCI omission question cannot be classified yet.
- Does hippocampal-avoidance PCI change the cognitive trade-off vs surveillance?
- Is PCI omission equally safe in limited-stage and extensive-stage SCLC? n=534 · primary completion 2026-04 · phase 3 PCI vs MRI surveillance, LS-SCLC post-CRTrecruiting PRophylactic Cerebral Irradiation or Active MAgnetic Resonance Imaging Surveillance in Small-cell Lung Cancer Patients (PRIMALung Study) Phase NAn=600 · primary completion 2028-04 · phase 3 MRI alone vs PCI+MRI, LS and ES, OS NI
- SRS vs HA-WBRT for surveillance-detected brain metastases in SCLC n=152 · primary completion 2026-06 · phase 3 SRS vs HA-WBRT+memantine, cognition endpointn=340 · primary completion 2027-08 · phase 3 SRS/SRT vs HA-WBRT, ≤10 SCLC brain mets
📚 Sources · 🐦 1 tweet
Dr. Chad Rusthoven at #WCLC26 presents results from SWOG S1827, the phase III MAVERICK study exploring the benefit of PCI in pts with SCLC. Historic studies before the era of MRI surveillance showed a decrease in brain metastases with PCI and an improvement in OS but recent… pic.twitter.com/CZCbx0NSLN
— Stephen V Liu, MD (@StephenVLiu) September 12, 2026