Unclear
Decipher and PAM50 in NRG/RTOG 9601 and 0534
ForPost-prostatectomy prostate cancer, salvage RT candidates
TL;DRNo effect size reported in source tweets: Decipher and PAM50 biomarker analyses for guiding hormone therapy with salvage RT, presented by MD Anderson investigators.
6 details
Biomarker analyses (Decipher, PAM50) drawn from the postoperative trials NRG/RTOG 9601 and 0534. Analysis design, N and endpoints not stated in source.
Source gives no effect sizes, cohort sizes or endpoints for the biomarker analyses; the image content was not accessible.
- Which Decipher or PAM50 strata benefit from hormone therapy with salvage RT?
- Can low-risk genomic pts safely omit hormone therapy with salvage RT?
📚 Sources · 🐦 1 tweet
Genomic biomarkers to guide hormone therapy with salvage radiation: Decipher and PAM50 in NRG/RTOG 9601 and 0534. Krishnan Patel, MD, MHS & Shuang (George) Zhao, MD @UTMDAnderson join @l_ballas @CedarsSinai to present biomarker analyses from postoperative prostate cancer trials.… pic.twitter.com/nNru9J3S6n
— UroToday.com (@urotoday) November 2, 2026
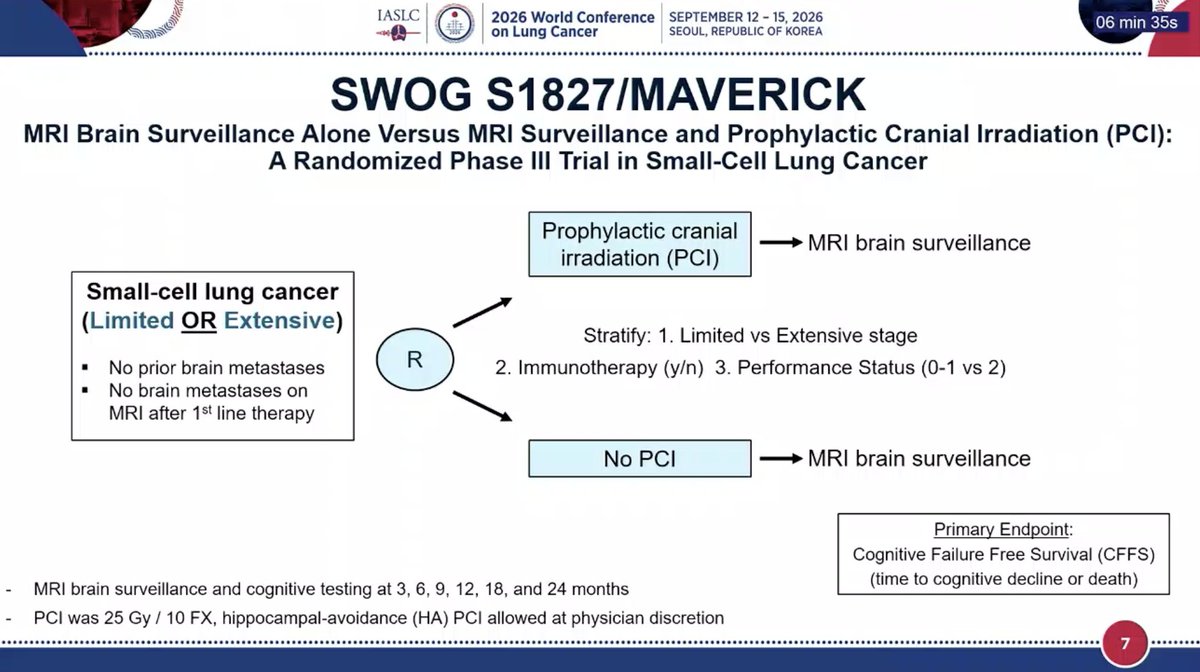
SWOG S1827/MAVERICK
ForLS or ES SCLC, responding after platinum ± IO, no brain mets on MRI, PS 0-2
TL;DRRandomized phase III, LS or ES SCLC: PCI 25 Gy/10 fx + MRI vs MRI surveillance alone; no CFFS or OS results in source tweets.
The RT question is PCI omission, not RT omission: the surveillance arm still gets RT at brain mets (SRS, WBRT or HA-WBRT at discretion), so CFFS pits upfront 25 Gy/10 fx PCI against deferred salvage. HA-PCI was also discretionary, diluting any hippocampal-sparing read. No CFFS or OS result in source tweets.
CFFS compares upfront PCI 25 Gy/10 fx against salvage RT at detection, with SRS, WBRT or HA-WBRT left to discretion. Discretionary HA-PCI means the PCI arm mixes techniques, so a cognitive result will not isolate hippocampal sparing. No results in source tweets.
Immunotherapy was allowed (concurrent and/or adjuvant) and stratified, so the trial tests PCI in the chemo-IO era for both LS and ES. Entry required response to platinum without progression and enrollment within 16 weeks of the last cycle, which defines the surveillance pathway being tested. No results in source tweets.
Also covered Sep 28
9 details 4 trials watching
Randomized phase III, PCI + MRI brain surveillance vs MRI surveillance alone. Stratified by LS vs ES stage, immunotherapy (y/n) and PS 0-1 vs 2. N and follow-up not reported in source tweets.
LS or ES SCLC, ≥18y, PS 0-2. LS pts completed platinum chemo plus definitive thoracic RT or resection; ES pts completed platinum chemo; immunotherapy allowed. Required response to upfront therapy, no brain mets on MRI within 28 days, enrollment within 16 weeks of last chemo cycle.
PCI 25 Gy/10 fx, with HA-PCI allowed at physician discretion. RT recommended at detection of brain mets, with SRS, WBRT or HA-WBRT at physician discretion.
Primary: cognitive failure free survival (time to cognitive decline or death). Hypothesis: MRI surveillance alone gives superior CFFS without a decline in OS. MRI and cognitive testing at 3, 6, 9, 12, 18 and 24 mo.
No CFFS, OS or brain-met incidence results reported in source tweets.
Per the presenting tweet, pre-MRI-surveillance studies showed fewer brain mets and improved OS with PCI, the basis for PCI as standard. MAVERICK tests that against a modern MRI surveillance plus salvage RT pathway, the question also addressed by the Japanese ES-SCLC phase III (Takahashi) and EORTC PRIMALung.
Discretionary HA-PCI blends techniques in the PCI arm, and discretionary salvage modality (SRS vs WBRT vs HA-WBRT) makes the surveillance arm's cognitive cost practice-dependent. Source does not state how OS non-decline is formally tested.
The trial reframes PCI as a cognitive trade-off rather than a brain-met prevention question, with CFFS as the primary. Whatever the result, it will not separate standard PCI from HA-PCI or define the best salvage modality.
Source tweets carry design, eligibility and hypothesis slides only; no CFFS or OS result, so the PCI omission question cannot be classified yet.
- Does hippocampal-avoidance PCI change the cognitive trade-off vs surveillance?
- Is PCI omission equally safe in limited-stage and extensive-stage SCLC? n=534 · primary completion 2026-04 · phase 3 PCI vs MRI surveillance, LS-SCLC post-CRTrecruiting PRophylactic Cerebral Irradiation or Active MAgnetic Resonance Imaging Surveillance in Small-cell Lung Cancer Patients (PRIMALung Study) Phase NAn=600 · primary completion 2028-04 · phase 3 MRI alone vs PCI+MRI, LS and ES, OS NI
- SRS vs HA-WBRT for surveillance-detected brain metastases in SCLC n=152 · primary completion 2026-06 · phase 3 SRS vs HA-WBRT+memantine, cognition endpointn=340 · primary completion 2027-08 · phase 3 SRS/SRT vs HA-WBRT, ≤10 SCLC brain mets
📚 Sources · 🐦 1 tweet
Dr. Chad Rusthoven at #WCLC26 presents results from SWOG S1827, the phase III MAVERICK study exploring the benefit of PCI in pts with SCLC. Historic studies before the era of MRI surveillance showed a decrease in brain metastases with PCI and an improvement in OS but recent… pic.twitter.com/CZCbx0NSLN
— Stephen V Liu, MD (@StephenVLiu) September 12, 2026
PROTEUS
ForHigh-risk prostate cancer, perioperative setting
TL;DR5-yr BCR-FS 44%, MFS 71%, CSS 92% at 60-mo median f/u in a real-world high-risk prostate cancer benchmark cohort.
7 details 1 trial watching
Design not stated in source; described as a real-world benchmark. Median follow-up 60 mo.
Reported: 5-yr BCR-FS, 5-yr MFS, 5-yr CSS. No primary endpoint or effect size stated.
Framed as a reference point for perioperative treatment strategies in high-risk disease, not a test of one. Useful only once the cohort definition and treatments received are known, since those determine which trial populations it can benchmark.
| Endpoint | 5-yr estimate |
|---|---|
| BCR-FS | 44% |
| MFS | 71% |
| CSS | 92% |
Descriptive benchmark with no comparator, N, eligibility, or treatment details in source; cannot classify impact on any perioperative decision.
- Which perioperative strategies improve on this BCR-FS benchmark? active COACTION Trial - COmbination Androgen bloCkade in inTermediate to hIgh-risk prOstate caNcer Phase 4n=144 · primary completion 2026-03 · RCT neoadjuvant leuprorelin+darolutamide pre-RP, pCR EP
- Cohort high-risk definition and treatments received
📚 Sources · 🐦 1 tweet
🔹 Median follow-up: 60 mo
— Can Aydogdu (@CanDAydogdu) August 28, 2026
🔹 5-yr BCR-FS: 44%
🔹 5-yr MFS: 71%
🔹 5-yr CSS: 92%
Providing a real-world benchmark to contextualize perioperative treatment strategies in this high-risk population.
📄 https://t.co/NyszMg9uCA#ProstateCancer #PROTEUS #Urology
USPCC 2026 Point-Counterpoint: PSMA PET Response Assessment in APMR
ForAPMR / mCRPC starting ARSI or bipolar androgen therapy, serial PSMA PET considered
TL;DRHigh vs low δ-percent SUVmax carried HR 5.03 (1.17-21.65) for OS; δ-absolute SUVmax HR 9.31 (1.81-47.87).
Reported via UroToday →
The prognostic separation is real but the direction of uptake change is the confound: ADT and ARSI can raise PSMA expression independent of burden, so a flare on restaging PET after starting an ARSI is not evidence to abandon a planned metastasis-directed course. Timing of the post-treatment scan relative to systemic therapy start is the parameter that gates interpretation.
In APMR pts imaged shortly after starting abiraterone, enzalutamide, or bipolar androgen therapy, rising PSMA uptake does not reliably separate progression from AR-driven expression change; it does not speak to baseline staging PET, where the evidence base is separate. The longer read
Metastasis-directed therapy decisions increasingly rest on restaging PSMA PET. If that scan follows ARSI initiation, increased lesion avidity may reflect AR-driven PSMA upregulation rather than new disease, so scan timing relative to systemic therapy start gates whether the images should redirect a planned SBRT course.
Post-ARSI uptake change stratifies outcomes (DPSM HR 5.03, DASM HR 9.31 for OS) but was measured in 16 pts, and rising uptake at 2-4 months does not establish treatment failure. Time to therapy change should still be driven by PSA and conventional imaging.
9 details 5 trials watching
A point-counterpoint conference presentation, arguing the negative position. The evidence marshalled is three published studies: a prospective single-arm imaging trial (n=16 evaluable), a bipolar androgen therapy series (n=6), and the RECIP 1.0 framework paper.
The anchor trial enrolled pts with APMR starting abiraterone or enzalutamide, imaged with 18F-DCFPyL PET/CT immediately before therapy and again at 2-4 months. The BAT series imaged at baseline and 3 months.
Prognostic separation was consistent across both quantitative stratifiers, with DPSM HR 5.03 (95% CI 1.17-21.65) and DASM HR 9.31 (95% CI 1.81-47.87) for overall survival. A mixed but predominantly increased uptake pattern marked the shorter time to therapy change.
| Stratifier | Median time to therapy change | Median OS | p (TTC / OS) |
|---|---|---|---|
| Low DPSM | 12.2 mo (11.3-NA) | 37.2 mo (28.9-NA) | reference |
| High DPSM | 6.5 mo (4.6-NA) | 17.8 mo (13.9-NA) | 0.0001 / 0.02 |
| Low DASM | 12.2 mo (11.3-NA) | NA (37.2-NA) | reference |
| High DASM | 6.9 mo (6.1-NA) | 17.8 mo (13.9-NA) | 0.003 / 0.002 |
RECIP 1.0 is the field's standardization attempt, categorizing PD/PR/SD/CR by combining PSMA PET with CT, but it was derived in the radioligand therapy setting and its transfer to AR-directed therapy is exactly what Rowe argues is unestablished.
Beyond the small samples, the measurement layer itself is unvalidated: repeatability work using Bland-Altman, ICC, and within-subject coefficient of variation found lesion identification and segmentation variability material even above 1.5 cm³. A biomarker whose test-retest behaviour is uncertain cannot support a serial-change decision rule.
The talk separates two claims that often get merged: that post-therapy PSMA PET change is prognostic, which the data support, and that it is a valid response assessment, which requires reproducibility and a therapy-independent relationship between uptake and burden. Prognostic value in a 16-patient series does not license per-patient treatment decisions.
Conference position talk, not a result. Its supporting datasets are n=16 and n=6 prospective series; no comparative design establishes or refutes PET response assessment.
- Kinetics of AR-axis therapy effects on PSMA expression recruiting Assessing Efficacy of Neoadjuvant ADT in Localized High-Risk Prostate Cancer Patients Utilizing 18F-Flotufolastat PSMA PET/CT Phase 2n=50 · primary completion 2030-02 · PSMA PET before and after neoadjuvant ADT, pre-RPrecruiting PSMA PET for Treatment Response evaLuation of systemIC Therapies in prostAte caNcer (PELICAN)n=1300 · primary completion 2034-04 · SUVmax/SUVmean on PSMA PET pre-abiraterone, n=1300
- Repeatability thresholds for SUV and lesion segmentation
- RECIP validation outside radioligand therapy not yet Prognostic Value of 177Lutetium-PSMA Single Photon Emission Tomography and Timing of Responsen=280 · primary completion 2026-09 · RECIP 1.0 by SPECT at cycle 2, not PETn=27 · primary completion 2027-07 · PSMA PET response endpoint after RT plus ADT/ARPIrecruiting Phase II Non-Randomized Study Evaluating POSLUMA-PSMA PET Response After Oligo- Metastatic/Progressive-directed Treatment With Radiotherapy (PROMPT-R) Phase 2n=50 · primary completion 2028-05 · PSMA PET response 6/12mo after ablative RT
📚 Sources · 📄 1 paper
Abstract
MROQC ADT Practice Patterns
ForIntact high-risk M0, N0-1 prostate cancer, definitive RT
TL;DRGuideline-concordant ≥18mo ADT intended in 67.0% of high-risk M0/N0-1 pts receiving definitive RT; ARPI recommended in 23.2% of STAMPEDE-eligible pts post-publication.
Facility-level variability in ≥18mo ADT recommendations persisted after adjusting for cN1, grade group and PSA (P<.0001), so treating site, not only tumor features, shapes duration. Among STAMPEDE M0-eligible pts, ARPI recommendations reached only 23.2% after publication, a gap a department can audit directly in its own high-risk RT cohort. The longer read
Grade group drove concordant ADT recommendations most (GG5 OR 9.45, GG4 OR 6.23), and site-level variability survived adjustment (P<.0001). For an RT department the benchmark is concrete: 67.0% intended ≥18mo ADT and 23.2% ARPI uptake in STAMPEDE M0-eligible pts after publication.
9 details
Prospective statewide quality-consortium data (MROQC), N=553 across 26 centers, June 2020 to November 2024. Multivariable analysis of predictors, a mixed-effects model with treatment site as random intercept, and ARPI adoption compared before vs after STAMPEDE M0 publication.
Intact high-risk M0, N0-1 prostate cancer treated with definitive RT: cT3/4 13.3%, cN1 19.9%, GG 4-5 75.0%, PSA ≥20 ng/mL 40.0%. 27.9% met STAMPEDE M0 criteria (≥2 of cT3/T4, GG 4-5, PSA ≥40 ng/mL, or cN1).
Primary: intended guideline-concordant ADT (GC-ADT, ≥18 months) per 2022 AUA/ASTRO. Also assessed: ARPI recommendation in STAMPEDE-eligible pts and facility-level variability.
91.3% recommended any ADT, 67.0% guideline-concordant. ARPI recommendations in STAMPEDE-eligible pts rose from 0% to 23.2% after publication; facility variability persisted on MVA (P<.0001).
| Factor | OR (95% CI) |
|---|---|
| cN1 | 2.94 (1.44-5.99) |
| GG4 | 6.23 (2.85-13.62) |
| GG5 | 9.45 (4.46-20.06) |
| PSA ≥40 ng/mL | 3.64 (1.22-10.87) |
Benchmarks practice against the 2022 AUA/ASTRO 18-36 month recommendation and STAMPEDE M0 ARPI intensification criteria. Single-state data, and the source offers no comparison with other practice settings.
The abstract gives no reasons for sub-18mo recommendations (comorbidity, pt preference, toxicity), so non-concordance is not necessarily poor care. The ARPI comparison is an uncontrolled before-after design, and no OR is reported for cT3/4.
The strongest predictors of a concordant recommendation were grade group (GG5 OR 9.45) and cN1, consistent with shorter courses being offered when high-risk status rests on other features. Residual site variability points to local norms beyond the modelled case mix, though unmeasured covariates could contribute.
Practice-patterns study of intended ADT recommendations; no efficacy or outcome endpoint, so nothing here confirms or challenges SOC.
- Delivered vs intended ADT duration in routine definitive RT practice
- Drivers of facility-level variation in ADT duration recommendations
- Barriers to ARPI intensification in STAMPEDE M0-eligible pts
📚 Sources · 📄 1 paper
Abstract
PROTEUS
TL;DRNo primary effect size in source; most distant mets were PSMA PET-detected (53.0% apalutamide group, 60.7% in the other group).
MFS here is largely a PET endpoint: most distant metastases were identified by PSMA PET (53.0% apalutamide group, 60.7% in the other group). Any MFS difference needs reading against conventional-imaging MFS endpoints with that ascertainment shift in mind.
The MFS read hinges on how events were detected: most distant metastases were PSMA PET-identified (53.0% apalutamide group, 60.7% in the other group). Whether adding apalutamide to ADT moves a conventional-imaging metastasis endpoint cannot be judged from source tweets; no effect size reported.
9 details 1 trial watching
Design not stated in source. Commentary frames the comparison as an ADT + apalutamide arm vs ADT alone; results published in NEJM alongside ASCO 2026.
Source names EFS and MFS. Primary endpoint and its effect size are not reported in source tweets.
Most distant metastases were identified by PSMA PET: 53.0% of those in the apalutamide group and 60.7% in the second group (label truncated in source).
The BCR counts (60 vs 50 per 100) come from a hypothetical thought experiment, not trial data. The arm attribution of the 60.7% figure is truncated in the source tweet.
A PET-dominated MFS event mix means the endpoint is not interchangeable with conventional-imaging MFS. Whether the result is a benefit or a negative trial, as the commentator frames the debate, cannot be settled from the source.
Source tweets give no primary endpoint result, design, phase or population; only the imaging mode of distant-met detection is stated.
- Primary endpoint effect size pending full presentation
- Does an MFS difference hold by conventional imaging alone? n=1503 · primary completion 2027-03 · apalutamide + RT in high-risk; conventional-imaging MFS
- Does PSMA PET-detected MFS track overall survival?
📚 Sources · 🐦 3 tweets
#ASCO26
— Daniel E Spratt (@DrSpratticus) May 31, 2026
The PROTEUS trial results are now online...buckle up as we wait to see the full presentation. This is going to be a trial that is likely highly controversial until the full results are published.
Some may call this a homerun, others may call this the largest negative…
Thought experiment:
— Sean McBride (@seanmmcbride) May 31, 2026
Let's take a very simple hypothetical trial involving 100 patients in the APA arm and 100 patients in the ADT alone arm. Pulling from PROTEUS EFS data, assume that, by 5 years, 60 patients in the ADT arm have had a BCR compared to 50 in the ADT+APA arm.… pic.twitter.com/WJaiDlJnQs
#ASCO26
— Daniel E Spratt (@DrSpratticus) May 31, 2026
Talk about real-time updates. NEJM paper now online and my predictions and inferences appear true.
Majority of MFS events were by PET not conventional imaging. "Most distant metastases were identified by PSMA PET (53.0% of those in the apalutamide group and 60.7% in the… https://t.co/Yz4myY0flq
RCC SBRT (5-year local control)
ForPrimary RCC treated with SBRT; stage and operability not stated in source
TL;DR100% local control at 5 years for RCC treated with SBRT, per a conference slide; no N, dose, or CI in source.
7 details
Not reported in source. The tweet gives a 5-year local control figure with no study type, N, institution, or registry identifier, so design cannot be inferred.
SBRT to primary RCC; dose, fractionation, number of fractions, and target definition are not reported in source. These are the parameters that gate transfer to practice, and none are available here.
100% local control at 5 years as stated in the source tweet. No confidence interval, no n-at-risk, and no statement of whether this is a Kaplan-Meier estimate or a crude proportion.
Beyond the missing design, the specific risk is effective follow-up: a medically inoperable RCC cohort loses pts to non-cancer death well before 5y, so a 100% figure can rest on very few pts at risk. Local control definition (RECIST-style size change vs absence of growth vs biopsy) is also unstated and swings the estimate.
Single tweet with one number, no N, design, dose, or LC definition. Cannot judge whether the 100% figure reflects efficacy or short effective follow-up.
- Dose and fractionation behind the reported 5-year local control
- Local control definition and n-at-risk at 5 years
- SBRT vs partial nephrectomy in operable primary RCC
📚 Sources · 🐦 1 tweet
These results are so impressive!! 💯 local control at 5 years for RCC treated with SBRT@DrRanaMcKay @AdityaBagrodia @DrTylerStewart @DrYukselUrun @OncoAlert https://t.co/fUB3airM5g
— Tyler Seibert MD PhD (@TylerSbrt) May 17, 2026
DIREKHT
ForResected HNSCC referred for post-operative RT
TL;DRDe-escalated post-op HNSCC RT: contralateral neck sparing and primary CTV to 56 Gy in selected pts; no outcome numbers in source tweet.
The two levers named are the ones that gate post-op HNSCC RT morbidity: contralateral neck omission and a 56 Gy primary CTV rather than standard higher-dose coverage. Which pts qualified is the whole question, and the source text does not give the selection criteria or any control or toxicity numbers.
Both levers are RT-side decisions: whether to cover the contralateral neck electively, and whether 56 Gy suffices for the primary CTV in selected post-op pts. The source names the approach but gives no selection rule and no control or toxicity numbers, so it flags a trial to read rather than a volume or dose change to adopt.
6 details
Two de-escalation levers reported in source: contralateral neck sparing in a specified subgroup, and reduction of the primary CTV dose to 56 Gy. Fractionation, technique, and the dose to involved or high-risk volumes are not stated in the source text.
Described as a trial, but phase, randomisation, N, sites, and follow-up are not stated in the source tweet.
No primary endpoint, effect size, or toxicity result reported in source. The tweet is commentary on the trial's approach, not its results.
Everything that would let a reader act on this is missing from the source: the selection rule for contralateral neck omission, the comparator, and any locoregional control or late-toxicity figures. A de-escalation result is only interpretable against its non-inferiority margin, which is not given.
Source is a single commentary tweet with no design, N, endpoint, or effect size. Nothing to classify beyond the de-escalation concept.
- Which pts qualify for contralateral neck sparing post-operatively
- Whether 56 Gy primary CTV holds locoregional control vs standard dose
📚 Sources · 🐦 1 tweet
There are tremendous opportunities to improve post-operative radiotherapy in HNSCC. The DIREKHT trial is an excellent example of such work, in which they spared the contralateral neck in a specified group of patients and/or reduced the primary CTV dose to 56 Gy.
— David Sher (@DavidSherMD) May 16, 2026
The details… https://t.co/7W84LYIofR