Curative
Radiotherapy for epithelial skin cancer (Locke)
ForCutaneous BCC/SCC, untreated or recurrent, definitive RT
TL;DRLocal control 89% overall (93% untreated vs 80% recurrent) across 531 BCC/SCC lesions; dose/fx <2 Gy predicted local failure (p=0.01).
The dose-per-fraction signal is confined to BCC 1.1-5 cm: 75% LC at ≤2 Gy/fx vs 95-100% at larger fx sizes (p=0.01), with no equivalent effect for SCC. Recurrent SCC is the weak group (68% LC, 32% nodal involvement), which bears on whether a recurrent SCC field should be treated more aggressively than a primary.
In a 1-5 cm BCC planned for definitive RT, this series argues against conventional ≤2 Gy fractions; it says nothing about fraction size for SCC, where no dose response was seen. The longer read
For BCC 1.1-5 cm, ≤2 Gy/fx gave 75% LC vs 95-100% with larger fractions (p=0.01), with no such effect in SCC. Modality dropped out on multivariate analysis (p=0.345) once electron margins widened, so margin and fraction size matter more than beam choice.
16 details
Single-institution retrospective review of consecutive pts treated 1966-1997. 468 pts, 531 lesions; median f/u 5.8 yr (range 2-24).
Biopsy-proven epithelial skin cancer: 389 BCC, 142 SCC; 364 previously untreated, 167 recurrent. Median age 73 (BCC) and 72 (SCC).
Superficial x-rays 60%, electrons 19%, electrons + superficial 20%, megavoltage photons <2%. Volume was tumor plus microscopic extension, with an additional 1 cm margin depending on size; lead eye shields when near the eye, and bolus use evolved over time.
Local control (relapse-free from RT start), cosmesis (telangiectasia, pigment change, fibrosis) and complications.
Overall LC 89%; untreated 93% vs recurrent 80%. On multivariate analysis, fraction size (p=0.01), lesion diameter and histology (p<0.01) predicted local failure; modality did not (p=0.345).
| Group | Local control |
|---|---|
| All lesions | 89% |
| Previously untreated | 93% (338 of 364) |
| Recurrent | 80% (133 of 167) |
| BCC overall | 92% (358 of 389) |
| SCC overall | 80% (113 of 142) |
| BCC recurrent | 86% (90 of 104) |
| SCC recurrent | 68% (43 of 63) |
| Dose/fx (Gy) | Local control |
|---|---|
| ≤2 | 38/51 (75) |
| 2.01-3 | 89/94 (95) |
| 3.01-4 | 10/10 (100) |
| >4 | 19/19 (100) |
Complications 5.8% overall (13% for lesions >5 cm), mainly soft-tissue necrosis: 9% of SCC vs 2% of BCC. Fair/poor cosmesis was 4% with superficial RT vs 12% electrons and 19% combination.
The same institution's 1986 series (Lovett et al.) found electrons worse on multivariate analysis. Here that association disappears, which the authors attribute to wider electron margins in later years. The <2 Gy/fx failure signal matches Silva et al. in pinna lesions.
Treatment spans three decades with evolving bolus and margin policy. The cosmesis data are missing for 15-25% of untreated lesions, and the SCC dose cells are small, so the absent SCC dose response may reflect low power.
The data support RT as definitive therapy for early BCC/SCC and put the main lever on fraction size and lesion size, not beam type. Recurrent SCC carries the poorest control and the most cosmetic cost, so failure at first treatment is expensive.
Retrospective single-institution series spanning three decades; modality chosen by lesion size, not randomized, so dose and modality associations are confounded. No surgical comparator.
- Optimal hypofractionation schedule for cutaneous SCC
- Elective nodal coverage for recurrent cutaneous SCC
- Do modern electron margins and bolus close the gap with superficial RT?
📚 Sources · 📄 1 paper
Hypofractionated electron beam RT for epithelial skin cancer, 434 cases
ForBiopsy-proven BCC or SCC, mostly head/face, elderly, primary or postop residual
TL;DR3-yr actuarial LRF 97.5% (54 Gy/18fx) vs 96.1% (44 Gy/10fx) with electrons for BCC/SCC; no significant difference in either histology.
The boundary is size: T3 tumours >5 cm recurred in 2/11, both after 44 Gy, so the centre now gives 54 Gy above 5 cm. SCC behaves differently from BCC. SCC recurrences came early (median 3.3 mo) and 3 of 5 had metastases. All BCC recurrences were local-only and treated by excision. Technique was a 1 cm margin with copper-foil compensation for skin sparing.
In an elderly pt with T1-T2 BCC or SCC on the face or head treated with electrons, this supports 44 Gy/10 fx as a convenience schedule equivalent in observed control to 54 Gy/18 fx; it does not extend to lesions >5 cm. The longer read
Size sets the limit: T3 >5 cm recurred in 2/11, both after 44 Gy, and the centre now uses 54 Gy above 5 cm. SCC failures came early (median 3.3 mo) and 3 of 5 had metastases. BCC failures were local-only and treated by excision. Technique was a 1 cm margin with copper-foil surface compensation.
15 details
Retrospective single-centre series, 434 tumours in 333 pts treated January 2001 to December 2006. Analysis per tumour; LRF and MFS as one minus cumulative incidence with death as competing risk.
Biopsy-proven BCC (n=332) or SCC (n=102), primary RT (n=386) or postop for residual disease (n=48). Median age 74.8y BCC, 78.3y SCC; 59.4% face, 22.4% elsewhere on head.
Electrons, 54 Gy/18 fx of 3 Gy (n=159) or 44 Gy/10 fx of 4.4 Gy (n=275), four fx per week. 4-12 MeV by tumour depth, tumour + 1 cm margin, copper foil to offset skin sparing.
No significant LRF difference between schedules in BCC (p=0.67) or SCC (p=0.46). T stage was the only factor associated with local recurrence (p=0.036); gender, age, histology, indication, site, dose and lesion number were not.
| Group | 54 Gy/18fx | 44 Gy/10fx | p |
|---|---|---|---|
| All tumours | 97.5% | 96.1% | not stated |
| BCC | 97.6% (95% CI 92.7-99.2%) | 96.9% (95% CI 93.1-98.8%) | 0.67 |
| SCC | 97.0% (95% CI 79.1-99.6%) | 93.6% (95% CI 83.4-97.6%) | 0.46 |
| Scorer · rating | 54 Gy | 44 Gy |
|---|---|---|
| Pt · good / fair / poor | 62% / 13% / 25% | 67% / 33% / 0% |
| Observer · good / fair / poor | 38% / 49% / 13% | 33% / 50% / 17% |
Toxicity not reported beyond cosmesis. In a 14-pt pilot, pt-scored good/fair cosmesis was 75% (54 Gy) and 100% (44 Gy), observer-scored 87% and 83%, no significant difference.
The authors cite RT local control of 87-97% for BCC and 56-91% for SCC in prior series, placing these rates at or above that range. They describe them as comparable to surgical series.
Frail pts were moved to 44 Gy before it became standard, which may bias toward fewer recurrences being seen (competing deaths) rather than toward better control. SCC CIs are wide (54 Gy lower bound 79.1%), so equivalence for SCC is not shown.
The authors argue follow-up was adequate because recurrences came early (median 10.4 mo BCC, 3.3 mo SCC). They conclude 44 Gy/10 fx is optimal for T1-T2 disease. The data support non-inferior-looking control at small size, not a formal non-inferiority claim.
Single-centre retrospective; schedule assigned by era and frailty, older 44 Gy cohort with shorter follow-up; univariate only, 15 events total. Cosmesis from 14 pts.
- Is 44 Gy/10 fx adequate for SCC, given wide CIs?
- Late cosmesis and fibrosis after 4.4 Gy fractions beyond 2 years
- Optimal dose for tumours >5 cm
📚 Sources · 📄 1 paper
Predictors of recurrence after RT for NMSC
ForBCC/SCC skin cancer treated with RT, primary/recurrent/postop, median age 78
TL;DRRecurrence 15.8% at median 18.4 mo across 448 RT-treated NMSCs; age, size ≥2 cm, immunosuppression and photon modality independently predicted recurrence.
Dose did not predict control (EQD2 OR 1.007, p=0.4735), while size ≥2 cm (OR 2.090) and immunosuppression (OR 2.939) did. Within the 40/10 and 50/20 schedules used here, escalation is not supported by this cohort; the lesion and host define risk. The photon OR is a marker of deeper, larger targets, not an argument against megavoltage.
In an immunosuppressed pt or a lesion ≥2 cm referred for skin RT, this supports counseling on a higher recurrence risk and closer follow-up past 2 years; it does not show that photons themselves are inferior for deep lesions. The longer read
Dose did not predict control (EQD2 OR 1.007, p=0.4735), while size ≥2 cm (OR 2.090) and immunosuppression (OR 2.939) did. Within the 40/10 and 50/20 schedules used here, escalation is not supported; the photon OR marks deeper, larger targets rather than inferior technique.
12 details 1 trial watching
Single-centre analysis of a prospectively maintained database, RT delivered 2007-2011. Recurrence was assessed clinically. Univariate then backwards logistic regression, per tumour, with no correction for multiple lesions per pt.
389 pts, 448 BCC/SCC lesions, median age 78 (41-99). 67.9% <2 cm; 9% in immunosuppressed pts. Primary 53.3%, recurrent 29.7%, postoperative 16.7%.
Orthovoltage 100-300 kV, electrons 6-18 MeV with bolus, or 1-2 field photons (IMRT selectively). Most common schedules 50 Gy/20 fx and 40 Gy/10 fx. GTV by clinical mark-up plus a 1-2 cm margin; CT planning for deep tumours.
LC 84.2% at median f/u 18.4 mo; median time to recurrence 11.4 mo. Independent predictors were age, size ≥2 cm, immunosuppression and modality; EQD2 and indication (primary vs recurrent vs postop) were not.
| Factor | OR | 95% CL | p |
|---|---|---|---|
| Age (per year) | 1.034 | 1.005, 1.063 | 0.0197 |
| Size ≥2 vs <2 cm | 2.090 | 1.197, 3.649 | 0.0095 |
| Immunosuppression | 2.939 | 1.321, 6.539 | 0.0082 |
| Electrons vs photons | 0.440 | 0.234, 0.829 | 0.0111 |
| Orthovoltage vs photons | 0.285 | 0.142, 0.572 | 0.0004 |
LC sits below the ranges the authors cite (BCC 87%-98%, SCC 56%-97%). The van Hezewijk series used higher-EQD2 schedules (44/10 vs 54/18) with 3y LC 96.1% and 96.9%, but the populations are not comparable.
Logistic regression treats a time-to-event outcome as binary, so pts with 0-mo follow-up count as controlled. The 3-category modality variable cannot separate technique from tumour depth. Recurrence was not split into in-field vs marginal.
The independent risk factors are patient and tumour features, not dose, which points to selection and target coverage rather than prescription as the lever. The modality OR reflects case mix per the authors and should not drive technique choice.
Single-centre retrospective analysis; logistic model ignores censoring, modality effect confounded by indication, and 18.4-mo median f/u undercounts late BCC recurrence.
- Does dose escalation improve control for NMSC ≥2 cm?
- Optimal RT approach for immunosuppressed pts with cutaneous SCC recruiting Alpha Radiation Emitters Device (DaRT) for the Treatment of Cutaneous SCC for Immunocompromised Patients Phase NAn=28 · primary completion 2026-12 · alpha DaRT brachy in immunocompromised cSCC, ORR 1° EP
- Late recurrence rates beyond 2 years after skin RT
📚 Sources · 📄 1 paper
Abstract
RT for nasal skin SCC, Princess Margaret experience
ForNasal skin SCC (excl. vestibule), mostly T1N0, elderly, primary or postop RT
TL;DRLocal relapse-free rate 90% at 2y and 85% at 5y, CSS 96%, no RTOG G4 late toxicity in 94 pts treated with mostly orthovoltage RT.
Failure pattern is the RT read: 6 of 10 local failures sat on the nasal bridge, and 3 of 4 bridge recurrences after CR had a marginal component, while 2 of 5 columella lesions failed. Curved surfaces and fusion planes argue for generous margins beyond the usual 1 cm.
In an elderly pt with cN0 nasal skin SCC selected for RT over excision, this supports definitive hypofractionated RT to the primary alone with nodal surveillance; it does not extend to nasal vestibule SCC. The longer read
Bridge and columella lesions drove local failure: 6 of 10 failures were on the bridge, 3 of 4 post-CR bridge recurrences had a marginal component, and 2 of 5 columella lesions failed. Margin and contour dosimetry, not dose, look like the lever, with no elective nodal coverage needed in cN0.
12 details
Retrospective chart review of 100 pts treated at Princess Margaret 1982-1993; 94 analyzed after 6 lost to follow-up. Median follow-up 2.9y (range 0.2-10.4) in the 45 survivors.
Histologically confirmed SCC of the nasal skin; nasal vestibule SCC excluded. T1 60, T2 11, T4 7, TX 16; only 1 pt N1 at presentation.
35 Gy/5 for lesions <2 cm, 45 Gy/10 for 2-5 cm, 50 Gy/20 for >5 cm or bone/cartilage invasion. Orthovoltage in 81%, energy chosen by lesion thickness (75-100 keV <2 mm, 125 keV 2-4 mm, 250 keV >4 mm); 1-cm field-edge margin; no elective nodal coverage.
Primary: local failure-free rate. Secondary: nodal failure-free rate, OS, cause-specific survival, late toxicity.
No RTOG G4 late toxicity and no cartilage or bone necrosis. Skin pallor, atrophy and telangiectasia common 1-5y post-RT, progressive but usually asymptomatic.
The Mazeron nose and vestibule series cited by the authors reported 11% local failure for SCC, in line with the 10% 2y local failure here. A cited vestibule series reported 5y local relapse-free 80%, consistent with the authors' point that vestibule disease does worse and was rightly excluded.
Treatment-era orthovoltage technique and no formal cosmetic assessment, so the optimal schedule cannot be derived. Dose was chosen by size and frailty, confounding any dose-response read.
Authors now prefer 50 Gy/20 or 60 Gy/30 for large infiltrative lesions, since schedules under 4 weeks usually leave a visible cosmetic defect after 1-2y. Many elderly pts still accept 1-2 week courses and the cosmetic trade-off.
| Endpoint | 2 years | 5 years |
|---|---|---|
| Local failure-free | 90% (SE 3%) | 85% (SE 5%) |
| Overall survival | 75% (SE 4%) | 51% (SE 6%) |
| Cause-specific survival | 96% (SE 2%) | 96% (SE 2%) |
Retrospective single-institution series without a surgical comparator; toxicity and cosmesis not formally scored; short survivor follow-up in an elderly cohort.
- Optimal dose-fractionation balancing cosmesis and local control
- Electrons or brachytherapy vs orthovoltage on curved nasal surfaces
- RT vs Mohs excision for nasal skin SCC
📚 Sources · 📄 1 paper
Risk factors determining prognosis of cutaneous SCC (Brantsch)
ForPrimary cutaneous SCC, resected to clear 3D-histology margins, no adjuvant RT
TL;DRNo metastases in tumours ≤2.0 mm thick; >6.0 mm metastasized in 14/90 (16%); desmoplasia drove local recurrence (HR 16.11) after margin-controlled resection.
Desmoplasia, which here included every case of perineural or perivascular invasion, carried local recurrence of 12/51 (24%) vs 8/564 (1%) despite tumour-free 3D-histology margins and no adjuvant RT. That is an RT-naive surgical baseline. It places the adjuvant RT question in desmoplastic/PNI or >6.0 mm tumours (LR 11/90, 12%), not in clear-margin thin SCC.
In resected cSCC with clear margins that is ≤2.0 mm thick and non-desmoplastic, this supports a very low expectation of metastasis or recurrence. It does not address whether adjuvant RT changes risk in desmoplastic or >6.0 mm tumours, because no pt received RT. The longer read
Desmoplasia, which included all PNI, carried LR of 12/51 (24%) vs 8/564 (1%) after clear margins with no adjuvant RT. This RT-naive baseline sets where adjuvant RT is worth weighing: desmoplastic/PNI or >6.0 mm tumours. The cohort cannot show that RT lowers that risk.
Clear 3D-histology margins with 2-10 mm safety margins held overall LR to 20 of 615 (3%), yet desmoplastic tumours still recurred locally in 24%. The first metastatic site was always a regional LN, which is why the authors raise SLNB and nodal ultrasound for high-risk pts.
11 details 2 trials watching
Prospective single-centre observational cohort following STROBE. Pts were resected between 1990 and 2001, follow-up closed Dec 2005, median f/u 43 mo. Cox models used forward selection, with a 200/415 learning-validation split for internal validation only.
615 assessable white pts with primary cutaneous SCC at any body site, median age 73, 5% immunosuppressed. Excluded: SCC in situ, keratoacanthoma, collision tumours, and recurrent SCC treated elsewhere.
No pt received adjuvant RT. Every resection reached tumour-free margins by 3D-histology, with re-excision as needed, so outcomes reflect surgery alone.
The source states the primary endpoints as time to metastasis and time to local recurrence, each measured from diagnosis of the primary. Seven candidate predictors were chosen a priori.
26 (4%) metastases and 20 (3%) local recurrences. No tumour ≤2.0 mm metastasized. The thinnest tumour that metastasized was 2.8 mm thick.
| Thickness | Metastasis | Local recurrence |
|---|---|---|
| ≤2.0 mm (n=207) | 0 | 1 |
| 2.1-6.0 mm (n=318) | 12 (4%) | 8 (3%) |
| >6.0 mm (n=90) | 14 (16%) | 11 (12%) |
| Endpoint | Factor | HR (95% CI) | p |
|---|---|---|---|
| Metastasis | Tumour thickness | 4.79 (2.22-10.36) | <0.0001 |
| Metastasis | Immunosuppression | 4.32 (1.62-11.52) | 0.0035 |
| Metastasis | Ear location | 3.61 (1.51-8.67) | 0.0040 |
| Metastasis | Horizontal size | 2.22 (1.18-4.15) | 0.0128 |
| Local recurrence | Tumour thickness | 6.03 (2.71-13.43) | <0.0001 |
| Local recurrence | Desmoplasia | 16.11 (6.57-39.49) | <0.0001 |
Clayman and colleagues reported LR in 12% (15 of 130) of primary SCC. Margin-controlled resection here gave 3% (20 of 615). The authors cite an Australian series of 266 pts with nodal disease that also supports tumour thickness over horizontal size.
Follow-up after the early period relied partly on mailed questionnaires to treating physicians. New field-cancerization SCC can mimic local recurrence. University referral may have enriched for poorly differentiated tumours.
Thickness, immunosuppression and desmoplasia outperformed Broders' grade and horizontal size as prognostic factors. The authors propose thickness-based T1-T3 cutoffs (≤2.0, 2.1-6.0, >6.0 mm) with "d" and "i" modifiers. The study does not test whether any treatment changes the high-risk course.
Single-centre prognostic cohort, model selected by forward selection with events per predictor below 5. Validated only internally; no external cohort.
- Does adjuvant RT reduce LR in desmoplastic/PNI or >6.0 mm cSCC? recruiting Study of a Strategy Integrating Adjuvant Radiation Therapy Versus Strategy Based on Monitoring in the Treatment of Carcinomas Spinocellular With High Risk of Recurrence Phase 3n=266 · primary completion 2031-06 · phase 3 adjuvant RT vs surveillance, high-risk cSCC, DFS
- Role of SLNB in high-risk cSCC recruiting Sentinel Lymph Node Biopsy for Cutaneous Squamous Cell Carcinoma of the Head and Neck Phase NAn=94 · primary completion 2026-09 · SLNB occult nodal rate, cN0 T2-T4 H&N cSCC
- External validation of thickness cutoffs in larger cohorts
📚 Sources · 📄 1 paper
Kilovoltage RT for carcinomas overlying nasal cartilage (671 lesions)
ForBCC and SCC of skin overlying nasal cartilage
TL;DR5-yr cure rate 88.09% and 10-yr 86.51% in 671 BCC and SCC over nasal cartilage; cosmesis good or acceptable in 96.84%.
Failure was mostly marginal (25 of 38 recurrences) with 0.5-1 cm field margins, which argues for generous margins over nasal skin; morpheaform lesions got 1.5 cm. With 5 Gy twice weekly (median 55 Gy), the authors report no cartilage sequelae. That supports kV RT as the nonsurgical option where excision would need complex reconstruction.
In a pt with BCC or SCC of skin over the nasal cartilage whose excision would need complex reconstruction, this supports superficial kV RT as a durable nonsurgical option; with no surgical arm, it does not settle RT vs excision for a surgically straightforward lesion. The longer read
Failure was mostly marginal (25 of 38 recurrences) with 0.5-1 cm margins, which argues for wider fields over nasal skin. With 5 Gy twice weekly (median 55 Gy), the authors report no cartilage sequelae, supporting kV RT where excision would need complex reconstruction.
11 details
Retrospective single-institution series of 671 lesions treated 1972-2007. Mean follow-up 38.016 mo (range 1-351). Actuarial cure rate by life-table method; chi-squared for dose and size associations.
Basal and squamous cell carcinomas of the skin overlying the nasal cartilages. Histology split of the full cohort not given in the source excerpt. Relapses included 10 lesions already recurrent after prior non-radiological treatment.
CRT in 668 lesions: 55-60 kV, HVD 2-12 mm, 5 Gy/fx twice weekly, total 30-75 Gy (median 55 Gy). Margin 0.5-1 cm, 1.5 cm for morpheaform BCC. Septal cartilage shielded with 1 mm Pb nostril inserts at the alae.
CR 98.80% at 1 mo; 5-yr cure 88.09%, 10-yr 86.51%. Recurrence 38 lesions (13 central, 25 marginal), onset 3-96 mo. No relationship between relapse and dose or size.
| Endpoint | Lesions | % |
|---|---|---|
| CR at 1 mo | 663 | 98.80% |
| PR (all BCC) | 3 | 0.44% |
| Recurrence (13 central, 25 marginal) | 38 | 5.66% |
| 5-yr cure rate | n/a | 88.09% |
| 10-yr cure rate | n/a | 86.51% |
| Rating | Lesions | % |
|---|---|---|
| Good | 496 | 74.47% |
| Acceptable | 149 | 22.37% |
| Not acceptable | 16 | 2.40% |
Cosmesis good or acceptable in 96.84%; 16 lesions not acceptable. Authors report no complications or sequelae, and flag the 7 newly not-acceptable cases for continued follow-up.
No contemporaneous comparator. The authors cite randomised facial BCC data comparing RT with surgery: cosmesis was similar on nasal skin but control favoured surgery, in tumors under 4 cm treated with mixed RT techniques. Mohs surgery, the usual comparator for nasal BCC today, is not addressed.
Toxicity is clinician-rated cosmesis without a named scale, and a mean follow-up near 3 years is short for late cartilage effects. The null dose-relapse finding is likely confounded by dose being chosen by lesion size.
The data support kV RT as an effective, cartilage-sparing option for nasal skin carcinoma, where tight adherence of skin to cartilage complicates excision. They do not establish superiority over surgery, and the marginal-failure pattern raises the question of whether margins were adequate.
Single-institution retrospective series, 1972-2007, no surgical comparator; the authors' claim of superiority over other modalities rests on cross-literature comparison this design cannot support.
- Local control vs Mohs surgery for nasal skin carcinoma
- Adequate field margin given mostly marginal recurrences
- Late cartilage toxicity of 5 Gy fractions beyond 10 years
📚 Sources · 📄 1 paper
Facial cutaneous carcinoma HDR contact brachytherapy with customized molds
ForFacial BCC/SCC ≤3 mm thick, ≤4 cm, mostly elderly, non-surgical
TL;DR5-yr actuarial LC 89% (100% flat surfaces, 83% nose) with Ir-192 HDR contact mold BT, 48 Gy/12 fx, for facial BCC/SCC ≤3 mm thick.
Failure tracked the applicator, not the dose: all five relapses had only three catheters, and four sat on the nasal tip (LC 73%) versus 95% on pyramid/wing and 100% on flat skin. The 3 mm prescription depth only fits lesions ≤3 mm, so nasal-tip lesions or thicker tumors argue for electrons, interstitial BT or surgery.
In an elderly pt with a thin (≤3 mm) facial BCC/SCC on the temple, forehead, cheek or nasal dorsum/ala, this supports HDR contact mold BT as a surgical alternative; it does not extend to nasal-tip lesions or tumors thicker than 3 mm. The longer read
Failure tracked the applicator, not the dose: all five relapses had only three catheters, and four sat on the nasal tip (LC 73%) versus 95% on pyramid/wing and 100% on flat skin. The 3 mm prescription depth only fits lesions ≤3 mm, so nasal-tip lesions or thicker tumors argue for electrons, interstitial BT or surgery.
12 details
Retrospective single-institution series, 51 lesions in 48 pts referred 1999-2005. Median follow-up 45 mo (range 4-102); LC by Kaplan-Meier.
Facial BCC (82.4%) and SCC (17.6%), mean diameter 1.5 cm (0.5-4 cm), thickness ≤3 mm in all; thicker lesions went to electrons. Median age 78; 95% radical, 5% adjuvant after lateral-margin-positive excision.
Ir-192 HDR contact BT via custom wax nasal molds (CT-planned) or bolus applicators on flat skin, 1 cm margin, prescribed at 3 mm depth. Standard 48 Gy in 12 fx of 4 Gy, 3 fx/wk, over 4 wk; 3 Gy x 17-18 and 7 Gy x 5 schedules also used.
5 relapses (9.8%) at 6-32 mo, all on the nose and all with three-tube applicators. Nasal tip LC 73% vs 95% on pyramid/wing; all salvaged surgically.
| Schedule | Share of cases | EQD α/β10 | EQD α/β2.5 |
|---|---|---|---|
| 44-48 Gy, 4 Gy x 11-12 fx | 57% | 57.75-63 Gy | 61.5-67 Gy |
| 51-57 Gy, 3 Gy x 17-18 fx | 37% | 62-69.3 Gy | 61.2-64.8 Gy |
| 35 Gy, 7 Gy x 5 fx (very old pts) | 6% | 55.5 Gy | 72 Gy |
Acute G4 dermatitis in 11 pts (21%), healed within 3 wk; no late complications including chondritis. Cosmesis good or very good in all cases.
Source cites Guix et al. contact HDR-BT with 5-yr LC 98% at 60-65 Gy/1.8 Gy fx, and Rio et al. LDR interstitial BT with 92.5% radical LC. This series sits below those on the nose, driven by the tip.
Only 9 SCC, so no histology-specific read. Cosmesis was physician-graded and the G4 dermatitis rate differs between Results (21%) and Discussion (12%).
Authors attribute nasal-tip failure to undersized three-tube molds and poor catheter bending at the tip's lower surface, and now add catheters. A deeper prescription point was not excluded as a cause.
Retrospective single-arm series, 51 lesions, one institution; no comparator vs Mohs, electrons or orthovoltage. Nasal-tip failures tied to an early three-tube applicator.
- Do multi-catheter nasal molds restore control on the nasal tip?
- Contact HDR-BT vs Mohs or electrons for cosmesis and control
- Would a deeper prescription point reduce marginal failures?
📚 Sources · 📄 1 paper
Hypofractionated HDR plesiotherapy in nonmelanoma skin cancer
ForClinically N0 BCC/SCC skin, primary or recurrent, definitive or adjuvant
TL;DR3y/5y DFS 95.12%/93.36% after 3 Gy/fx HDR surface brachy for 134 BCC/SCC lesions; CR 98%, recurrent lesions did worse.
Disease status, not applicator, split control: recurrent lesions reached 3y/5y DFS 85.9%/85.9% vs 97.9%/95.6% for primary (p=0.003). Acute G3 was 40.3% at 3 Gy/fx three times weekly, higher with definitive intent and molds, so fraction size and applicator choice gate tolerability more than control for larger or curved lesions.
In older pts with a small flat primary BCC or SCC, this supports HDR surface brachy at 3 Gy/fx as a definitive option with high control; it is weaker support for recurrent lesions, where 5y DFS was 85.9%. The longer read
Disease status, not applicator, split control: recurrent lesions reached 5y DFS 85.9% vs 95.6% for primary (p=0.003). Acute G3 was 40.3% at 3 Gy/fx three times weekly, higher with definitive intent and molds, so fraction size and applicator choice gate tolerability for larger or curved lesions.
13 details
Retrospective single-institution series, 114 pts and 134 lesions treated Nov 2006 to Dec 2011. Analysis per lesion; median follow-up 33 mo.
92 BCC and 42 SCC, all clinically N0. 77.3% definitive, 22.7% adjuvant after excision with positive or close margins.
Ir-192 HDR plesiotherapy, 3 Gy/fx, 3 fx/wk; mean 48.79 Gy (45-54) for BCC and 50.55 Gy (45-57) for SCC, prescribed 3-5 mm below the surface with a 0.5-1 cm margin. Leipzig 2 or 3 cm applicators for flat lesions ≤2 cm (75.4%); customized molds for raised or larger lesions.
Overall 3y/5y DFS 95.12%/93.36%, CR 98%. Recurrent lesions did worse than primary (85.9% vs 95.6% at 5y, p=0.003); applicator and definitive vs adjuvant did not separate DFS.
| Group | 3y DFS | 5y DFS |
|---|---|---|
| Overall | 95.12% | 93.36% |
| Leipzig applicator | 94.9% | 94.9% |
| Customized mold | 93.1% | 88% |
| Primary lesion | 97.9% | 95.6% |
| Recurrent lesion | 85.9% | 85.9% |
| BCC | 94.1% | 91.3% |
| SCC | 97.5% | 97.5% |
Acute RTOG G3 40.3%, G4 2.2%; toxicity higher with definitive intent (OR 2.928, p=0.013) and borderline with molds (p=0.067). Late G0-1 95.2%; cosmesis excellent/good 82%.
Authors place results alongside the Kohler Leipzig series (91% complete remission) and Guix's mold series (5y DFS 98%). They cite one randomized surgery vs RT trial as the only head-to-head data, with no numbers given in source.
Molds treated larger lesions, so mold vs Leipzig DFS and toxicity differences cannot be separated from size. Reported recurrence counts do not add up, and the acute toxicity figure differs between abstract and results.
Supports surface HDR as a definitive alternative to excision for small primary NMSC. It does not settle optimal fraction size, and the high acute G3 rate argues for weighing applicator and dose per fraction for larger lesions.
Retrospective single-institution series, no comparator arm; applicator comparison confounded by lesion size and location; DFS per lesion with 33-mo median f/u.
- Optimal fraction size for HDR surface brachy in NMSC
- Late recurrence and cosmesis beyond 5 years
- HDR plesiotherapy vs Mohs or excision head-to-head
📚 Sources · 📄 1 paper
Decipher and PAM50 in NRG/RTOG 9601 and 0534
TL;DRASTRO 2026 secondary analyses: Decipher prognostic in 9601 but not formally predictive; PAM50 luminal-B predicted STADT benefit with salvage RT in 0534.
Reported via UroToday →
NRG/RTOG 9601NRG/RTOG 0534NRG-GU006NRG GU-009
The actionable split is early salvage with low Decipher: no significant 15-yr PCSM benefit from bicalutamide, while late salvage benefited regardless of score. PAM50 luminal-B status, reported on the Decipher grid, adds a predictive read for STADT. The PLNRT-by-subtype MFS trend is exploratory and should not yet move pelvic nodal coverage decisions.
In a post-RP pt with early salvage PSA and Decipher ≤0.6, this questions the PCSM value of adding hormone therapy to salvage RT; it does not extend to late salvage pts, who benefited regardless of score. The longer read
For salvage prostate bed RT, low-Decipher early salvage pts showed no significant PCSM gain from adding bicalutamide, while late salvage benefited regardless. A PAM50 luminal-B trend toward PLNRT benefit on MFS appeared in 0534 but is exploratory and does not support changing nodal fields.
PAM50 luminal-B predicted benefit from STADT in 0534 (significant interaction), matching NRG-GU006 with apalutamide, which suggests the effect does not depend on the agent. Decipher stayed prognostic but did not meet the predictive criterion, so it refines absolute risk rather than identifying who responds to ADT.
11 details
Two ASTRO 2026 secondary biomarker analyses of randomized salvage trials, discussed in a UroToday interview. RTOG 9601: salvage RT ± bicalutamide 24 mo. RTOG 0534: PBRT vs PBRT + STADT vs PBRT + STADT + PLNRT, PAM50 on a subset.
Post-prostatectomy salvage pts. 9601 enrolled PSA 0.2 to 4.0, early and late salvage. The 0534 PAM50 subset showed no significant baseline differences across arms.
Decipher was prognostic for OS, PCSM and DM, including early salvage, but not predictive by the statistical criterion. In 0534, luminal-B pts gained a large FFP benefit from STADT vs much less in non-luminal-B, with a significant interaction p.
| Salvage setting | Decipher | PCSM benefit at 15 yr |
|---|---|---|
| Early salvage | >0.6 | >5% |
| Late salvage | Any | >5% |
| Early salvage | Low (≤0.6) | No significant benefit |
The PAM50 finding matches NRG-GU006, where luminal-B tumors benefited from apalutamide, so the signal holds across bicalutamide, leuprolide-based STADT and an ARPI. NRG GU-009/010 used a Decipher cut of 0.85 in the intact setting, vs 0.6 here post-op.
No HRs, interaction p-values or absolute rates are given in the source interview. The PSA threshold separating early from late salvage is not stated. Decipher and PAM50 can be discordant, and the source offers no data on how to resolve that.
Presenters frame both tests as one input to shared decision-making with pts, not a gate. Decipher reports PAM50 subtype on the same grid, so a single order yields both.
- Does PAM50 luminal-B status predict benefit from pelvic nodal RT?
- How to act on discordant Decipher and PAM50 results
- Optimal Decipher cut point for de-intensifying ADT in early salvage
📚 Sources · 📄 1 paper
Abstract
AZUR-1 NCT05723562
FordMMR/MSI-H locally advanced rectal cancer, treatment-naive
TL;DRcCR12 68% (investigator) and cCR12+pCR 76% with dostarlimab alone in dMMR/MSI-H LARC, no recurrences to date at 26.3mo median f/u.
The RT-omission read hinges on the assessor: investigator cCR12 is 68%, central review 47% (54/116) with 38 pts still pending. Either figure exceeds the 21-41% post-TNT cCR range the source cites, which supports MMR testing before any pelvic RT is planned in LARC.
In dMMR/MSI-H LARC, this supports checkpoint-first, organ-preservation discussion before committing to chemoRT or TNT; it does not extend to pMMR/MSS rectal cancer. The longer read
Central review cCR12 is 47% (54/116) against investigator 68%, with 38 pts pending; both exceed the 21-41% post-TNT cCR range cited. In dMMR/MSI-H LARC, pelvic RT is shifting toward a salvage role, so MMR status should be known before simulation.
Nine cycles of dostarlimab 500 mg q3w delivered 68% cCR12 (INV) with 88% completing therapy and G≥3 immune-mediated AEs in 4 pts. This positions PD-1 monotherapy as the first move in dMMR/MSI-H LARC, ahead of oxaliplatin-based TNT.
Only 15 pts underwent resection after dostarlimab alone and 12 (80%) were pCR, so most surgical specimens showed no residual tumour. The surgical question becomes timing of salvage and surveillance intervals, not upfront TME, in dMMR/MSI-H LARC.
10 details 2 trials watching
Global single-arm phase II, registrational. Interim analysis, N=154 enrolled, median f/u 26.3 mo (range 2-36).
dMMR/MSI-H locally advanced rectal cancer. 144 pts had ≥12 mo f/u for investigator-assessed cCR12.
Dostarlimab 500 mg IV q3w for 9 cycles as monotherapy; chemotherapy, radiation and surgery reserved for non-responders.
Key endpoints: sustained cCR for 12 months (cCR12) after end of treatment by investigator and independent central review, and composite cCR12 (INV) + pCR.
cCR12 68% (INV) vs 47% (54/116) (ICR); composite cCR12+pCR 76%. Of 15 resected pts, 12 (80%) had pCR; no recurrences to date after cCR or pCR.
| Assessor | Evaluable | cCR12 |
|---|---|---|
| Investigator | 144 | 68% |
| Independent central review | 116 | 54/116 (47%) |
88% completed all 9 cycles. G≥3 immune-mediated AEs in 4 pts.
Post-TNT cCR is cited at 21-41% in LARC broadly; AZUR-1 exceeds that in a biomarker-selected group. It scales up the earlier small dostarlimab study that first showed durable cCR in dMMR LARC.
Investigator and central review diverge on cCR12, and ICR evaluability lagged because cCR was confirmed later. cCR12 is a surrogate for durable organ preservation; local regrowth risk beyond 3 years is unmeasured.
Durable cCR with no recurrences so far makes RT omission a realistic default question in dMMR LARC. Open: how long surveillance must run, and what salvage looks like for late regrowth.
Single-arm interim analysis without a randomised comparator; investigator vs central review cCR12 diverge, and durability beyond 26.3mo median f/u is unproven.
- Will ICR cCR12 converge with investigator rate as pending pts mature?
- Late local regrowth risk beyond 3 years without RT or surgery not yet Non-Operative Management and Following Immunotherapy for Colorectal Cancer and Other GI Cancersn=50 · primary completion 2029-06 · dMMR/MSI-H W&W registry after neoadjuvant IO
- Role of RT for dMMR pts without cCR after dostarlimab recruiting Study of Induction PD-1 Blockade in Subjects With Locally Advanced Mismatch Repair Deficient Solid Tumors Phase 2n=212 · primary completion 2026-11 · dostarlimab then capecitabine-IMRT in dMMR LARC
📚 Sources · 📄 2 papers
Abstract
Abstract
SANO
ForLocally advanced oesophageal cancer, cCR after nCRT
TL;DR5y OS 50% vs 54%, HR 1.17 (0.77-1.77) active surveillance vs surgery after cCR to nCRT; distant mets 46% vs 29%, P<.01.
The RT read is that nCRT alone was the definitive treatment for 43% of the surveillance arm, but distant mets rose to 46% vs 29% without immediate surgery. That makes cCR after nCRT a reasonable organ-preservation endpoint for selected pts. Whether early oesophagectomy suppresses distant spread, or the gap comes from how surveillance detects disease, is the open question.
In locally advanced oesophageal cancer with cCR on biopsies, EUS and PET-CT after nCRT, this supports active surveillance with surgery as needed as a discussable option; it does not address pts without cCR or nCRT regimens other than those used in SANO. The longer read
nCRT alone was definitive treatment for a large part of the surveillance arm, which makes cCR on biopsies, EUS and PET-CT the decision gate. The nCRT regimen is not stated in source, so dose transfer cannot be judged, and the distant-mets excess (46% vs 29%) matters when counselling responders.
Surgery as needed spared 85/198 (43%) a non-beneficial oesophagectomy with no significant 5y OS difference (HR 1.17). The distant-mets excess under surveillance (P<.01) raises the question of whether delaying resection gives up systemic control, and that 43% includes pts who progressed within 6 mo.
9 details 1 trial watching
Multicentre stepped-wedge cluster-randomised non-inferiority trial, 2017-2021, Netherlands Trial Register NTR-6803. This report covers 5y outcomes at median f/u 76 mo (IQR 67-86).
Locally advanced oesophageal cancer with a complete clinical response after nCRT, defined as no tumour on endoscopic biopsies, endoscopic ultrasound, or PET-CT. N=309: 198 active surveillance, 111 standard surgery.
nCRT was the common backbone. The regimen, dose and fractionation are not stated in source, so whether the result transfers to a given chemoRT protocol cannot be judged from this abstract.
The earlier report showed non-inferiority on two-year OS with improved QoL under surveillance. This analysis compares 5y OS and DFS by Cox regression and estimates distant metastasis incidence with competing-risk analysis.
OS and DFS were not significantly different, but distant mets were higher under surveillance (P<.01). 85/198 (43%) were spared non-beneficial oesophagectomy.
| Endpoint | Active surveillance (n=198) | Standard surgery (n=111) | Effect |
|---|---|---|---|
| 5y OS | 50% (95%CI 34-57) | 54% (95%CI 46-64) | HR 1.17 (95%CI 0.77-1.77) |
| DFS | not reported per arm | not reported per arm | HR 1.39 (95% CI 0.94-2.06) |
| 5y cumulative incidence distant mets | 46% (95%CI 39-53) | 29% (95%CI 21-37) | P<.01 |
This extends SANO's own 2y non-inferiority result and follows the preSANO cCR-assessment framework. It parallels the watch-and-wait paradigm in rectal cancer (OPRA). The randomised definitive-CRT question is being tested separately in NEEDS.
The 43% spared figure counts pts with distant mets within 6 mo of nCRT, which inflates the organ-preservation benefit. At 5y, no NI margin is reported, and an OS HR upper bound of 1.77 cannot exclude clinically relevant harm.
Survival parity holds at 5y, but the distant-mets excess is the signal to explain. It could reflect micrometastatic seeding during delayed resection, or disease surfacing on surveillance imaging that resection would have found later. The abstract cannot separate the two.
Long-term f/u of a cluster-randomised NI trial supporting emerging organ preservation; wide OS CI and a significant distant-mets excess stop short of practice-changing.
- Why are distant metastases higher under active surveillance?
- Does systemic therapy during surveillance offset the distant-mets excess? recruiting An Organ Preservation Strategies After Chemoradiotherapy Combined With Immunotherapy for Esophageal Cancer (PALACE3). Phase 3n=356 · primary completion 2028-03 · ph3 nCRT+IO organ preservation vs nCRT+surgery, 3y OS
- Which nCRT regimen maximizes durable cCR?
📚 Sources · 📄 2 papers
Abstract
Abstract
DASL-HiCaP NCT04136353
ForVery high-risk localised PCa, or PSA persistent/recurrent within 1 yr of RP
HR 0.42
95% CI 0.27-0.66, p=0.0001; 4-yr 95% vs 88%
TL;DR4-yr MFS-CI 95% vs 88%, HR 0.42 (0.27-0.66), adding darolutamide to 96-wk ADT plus prostate/bed and pelvic nodal RT in very high-risk disease.
Every pt received pelvic nodal RT with 96 wk of LHRH analog, so darolutamide's MFS-CI HR 0.42 is measured on top of elective nodal coverage, not instead of it. 29% were node-positive on CT and the benefit held across primary vs salvage RT and N+ vs N0 (subgroup HRs not in source). The decision it moves is ARSI intensification alongside whole-pelvis RT, not RT field or dose.
In very high-risk localised prostate cancer planned for 96 wk of ADT with prostate and pelvic nodal RT, this supports darolutamide intensification for MFS-CI; it does not yet establish an OS gain and gives thin data for post-RP salvage pts (15% of the cohort). The longer read
The RT backbone was fixed: prostate or prostate bed plus pelvic nodes in both arms, so the HR 0.42 adds to elective nodal RT rather than replacing it. Benefit was reported consistent for salvage RT and for CT node-positive pts (29%), but only 15% had prior RP and subgroup HRs are not in source.
Darolutamide 600 mg BID for 96 wk on top of 96 wk ADT cut MFS-CI events 27 vs 63 with G≥3 AEs 43% vs 36%, and fractures and cardiac G≥2 events no higher than placebo. OS (HR 0.88) and PCSS remain immature, so the ARSI choice in this setting hinges on surrogacy holding.
10 details 1 trial watching
International, placebo-controlled, randomised 1:1 phase III, N=1,106 accrued 30APR20 to 09AUG23. Single prespecified interim after 87 MFS-CI events, disclosed only if 2-sided p<0.012. Median follow-up 3.8 yr (IQR 3.3-4.5).
Very high-risk localised prostate cancer, or biochemically persistent/recurrent disease within 1 yr after RP. Median age 71, Gleason 9-10 in 73%, pelvic nodal involvement on CT in 29%, prior RP in 15%.
Darolutamide 600 mg BID vs placebo for 96 wk, both arms on an LHRH analog for 96 wk.
Definitive or salvage RT to prostate or prostate bed plus pelvic nodes in both arms. Dose and fractionation not reported in source.
Primary: MFS on conventional imaging (CT and/or Tc bone scan), chosen per ICECaP surrogacy for OS. Secondary: PSA-PFS, PCSS, OS.
Primary met at interim (table above). OncLive reports MFS benefit consistent across primary vs salvage RT and N+ vs N0, and castration resistance and subsequent hormonal therapy endpoints favouring darolutamide; no numbers given for those.
| Endpoint | Darolutamide N=553 | Placebo N=553 | HR (95% CI) |
|---|---|---|---|
| MFS-CI | 27 (95%) | 63 (88%) | 0.42 (0.27-0.66), p=0.0001 |
| PSA-PFS | 46 (91%) | 95 (83%) | 0.47 (0.33-0.67) |
| PCSS | 4 (99%) | 7 (99%) | 0.58 (0.17-1.97) |
| OS | 21 (97%) | 24 (95%) | 0.88 (0.49-1.59) |
| AE | Darolutamide | Placebo |
|---|---|---|
| Fatigue/asthenia G≥2 | 14% | 10% |
| Hypertension G≥2 | 7% | 9% |
| Fractures G≥2 | 2% | 3% |
| Cardiac G≥2 | 3% | 3% |
| Any AE G≥3 | 43% | 36% |
Any G≥3 AE 43% vs 36%. G≥2 fatigue/asthenia 14% vs 10%; hypertension, fractures and cardiac events not higher with darolutamide.
Tests the same ARSI-added-to-ADT-plus-RT question as ENZARAD (enzalutamide) and ATLAS (apalutamide), and sits against the STAMPEDE abiraterone data that currently anchor intensification in high-risk nonmetastatic disease. DASL-HiCaP differs by mandating pelvic nodal RT and including early post-RP salvage pts.
Staging and progression on conventional imaging in a PSMA-era practice; salvage pts are only 15%. Backbone was 96 wk ADT plus pelvic RT in everyone, so benefit with shorter ADT or prostate-only fields is untested.
The MFS-CI gain is large but OS events are few (21 vs 24) and PCSS is 99% in both arms at 4 yr. Whether this becomes a darolutamide option alongside abiraterone in this setting depends on surrogacy holding at final analysis.
CONSORT flow
Prespecified interim analysis, not the final primary analysis; MFS-CI surrogate with PCSS and OS immature (OS HR 0.88, CI crosses 1). Randomised, placebo-controlled design is otherwise clean.
- Does MFS-CI benefit translate to OS at final analysis?
- Benefit in PSMA PET-staged very high-risk disease recruiting Treatment of High-Risk Prostate Cancer Guided by Novel Diagnostic Radio- and Molecular Tracers Phase 2/3n=493 · primary completion 2030-07 · ph3 RT ± darolutamide, tracer-staged high-risk
- Darolutamide vs abiraterone intensification with pelvic RT
📚 Sources · 📄 3 papers
Abstract
Abstract
Abstract
Decipher and PAM50 in NRG/RTOG 9601 and 0534
ForPost-prostatectomy prostate cancer, salvage RT candidates
TL;DRNo effect size reported in source tweets: Decipher and PAM50 biomarker analyses for guiding hormone therapy with salvage RT, presented by MD Anderson investigators.
6 details
Biomarker analyses (Decipher, PAM50) drawn from the postoperative trials NRG/RTOG 9601 and 0534. Analysis design, N and endpoints not stated in source.
Source gives no effect sizes, cohort sizes or endpoints for the biomarker analyses; the image content was not accessible.
- Which Decipher or PAM50 strata benefit from hormone therapy with salvage RT?
- Can low-risk genomic pts safely omit hormone therapy with salvage RT?
📚 Sources · 🐦 1 tweet
Genomic biomarkers to guide hormone therapy with salvage radiation: Decipher and PAM50 in NRG/RTOG 9601 and 0534. Krishnan Patel, MD, MHS & Shuang (George) Zhao, MD @UTMDAnderson join @l_ballas @CedarsSinai to present biomarker analyses from postoperative prostate cancer trials.… pic.twitter.com/nNru9J3S6n
— UroToday.com (@urotoday) November 2, 2026
UNION NCT04928807
ForcT3-4 or N+ rectal adenocarcinoma ≤10 cm from anal verge
TL;DR3-yr EFS 91.3% vs 77.4%, HR 0.33 (0.15-0.71), P=0.0029: SCRT → camrelizumab + CAPOX vs long-course CRT → CAPOX in LARC.
The control is long-course CRT, so the EFS gain (HR 0.33) comes with a switch to 25 Gy/5f. That makes SCRT the RT backbone for an IO-containing TNT, not a compromise. Because RT schedule and camrelizumab were changed together, the trial cannot say whether SCRT itself is what lets IO work in largely pMMR disease.
In cT3-4 or node-positive low/mid rectal adenocarcinoma, this supports SCRT followed by PD-1 inhibitor plus CAPOX as an evidence-backed TNT option. It does not settle IO use when no PD-1 agent equivalent to camrelizumab is available, or questions of organ preservation. The longer read
The experimental arm swapped 50.4 Gy/28f chemoRT for 25 Gy/5f and still improved 3-yr EFS (91.3% vs 77.4%). That puts SCRT forward as the RT platform for IO consolidation. Whether SCRT is synergistic or just interchangeable cannot be separated from the camrelizumab effect.
Adding camrelizumab across neoadjuvant and adjuvant CAPOX (up to 17 cycles) gave EFS HR 0.33 with G≥3 TRAE 51.3% vs 48.2%. It is a signal for PD-1 blockade beyond dMMR in LARC, though the MMR breakdown and OS are not in source, and camrelizumab availability outside China limits how far it transfers.
8 details 2 trials watching
Phase 3, randomized 1:1, N=231 (113 vs 118), accrued July 2021 to March 2023. Median follow-up 36.8 vs 35.6 mo at the October 1, 2025 cutoff.
cT3-4 or N+ rectal adenocarcinoma, tumor ≤10 cm from the anal verge. MMR/MSI composition of the enrolled cohort is not reported in source.
Experimental: SCRT 25 Gy/5f. Control: 50.4 Gy/28f with concurrent capecitabine 825 mg/m2 BID. Target volumes are not reported in source.
Both arms: 2 neoadjuvant + 6 adjuvant cycles of CAPOX. Experimental adds camrelizumab 200 mg d1 given alongside CAPOX for up to 17 cycles.
Primary: BIRC-assessed pCR rate (result not in source). Key secondary endpoints with prespecified α: investigator-assessed EFS and OS.
G≥3 TRAE over the whole treatment period 51.3% (59/115) vs 48.2% (54/112). The RT-attributable split is not reported.
RAPIDO set SCRT followed by consolidation chemo as a TNT option, and PRODIGE 23 did the same for an LCCRT-based approach. UNION is the first phase 3 to layer a PD-1 inhibitor onto SCRT in LARC, building on earlier SCRT + IO phase 2 signals such as TORCH.
The safety population (115 vs 112) does not match randomization (113 vs 118), so some pts received the other arm's treatment. Neoadjuvant CAPOX was only 2 cycles in the control arm, lighter than full TNT backbones. OS and surgical or organ-preservation outcomes are absent.
The EFS effect is large and was tested under alpha control, but it comes from a two-variable comparison. It supports the whole package and does not establish what SCRT or camrelizumab contributes individually.
| Endpoint | SCRT + camrelizumab + CAPOX | LCCRT + CAPOX | Effect |
|---|---|---|---|
| 3-yr EFS (investigator) | 91.3% (83.9-95.4) | 77.4% (67.9-84.4) | HR 0.33 (0.15-0.71), P=0.0029 |
| G≥3 TRAE | 51.3% (59/115) | 48.2% (54/112) | n/a |
| Median f/u | 36.8 mo (34.8-37.8) | 35.6 mo (34.3-36.9) | n/a |
CONSORT flow
Randomized phase 3, but the primary pCR result is not in source and EFS is secondary. SCRT and camrelizumab change together, so the benefit cannot be attributed to either.
- Does SCRT, versus long-course CRT, drive the immunotherapy benefit?
- Unreported pCR primary result and OS
- Benefit in confirmed pMMR/MSS pts specifically recruiting Neoadjuvant CAPOX With or Without Pucotenlimab Plus Selective Radiotherapy for Locally Advanced Rectal Cancer Phase 3n=556 · primary completion 2032-04 · phase 3 CAPOX ± pucotenlimab, pMMR/MSS LARCn=612 · primary completion 2032-12 · phase 3 SCRT+PD-1 iTNT vs LCRT TNT, MSS/pMMR only
📚 Sources · 📄 1 paper
Abstract
TOP-1 (BOOG 2016-01)
ForWomen ≥70, low-risk ER+ HER2- T1 BC after BCS, no endocrine therapy
TL;DR5-yr local recurrence 14.8% (95% CI 12.3-17.5) after BCS alone without RT or ET in women ≥70 with low-risk ER+ HER2- BC.
The trial removed endocrine therapy as well as RT, which earlier omission trials never did, and LR reached 14.8%, above the 10% ceiling it was powered to exclude. Salvage was mostly feasible (86 repeat BCS), but 70 pts received RT at recurrence anyway. So in ET-untreated older women, omitting RT often postpones it rather than avoiding it.
In a woman ≥70 with ≤2cm low-grade ER+ HER2- BC after BCS who will not take ET, this questions RT omission as low-risk; it does not test RT omission in women who do take ET. The longer read
In women ≥70 with low-risk ER+ disease, omitting RT without ET gave 14.8% 5-yr LR, and 70 of 123 recurrences received RT at salvage. Without ET, RT omission often means postponed RT, which reframes the omission conversation for pts declining or not offered ET.
Dutch guidelines do not advise ET for T1 low-grade ER+ BC, and this cohort shows what happens when RT is also dropped: 14.8% 5-yr LR. For pts in whom RT is omitted, the decision to withhold ET as well now carries a measured local cost.
10 details 2 trials watching
Prospective, multicenter, observational, single-arm cohort; N=792 of 800 planned (80% power to exclude a 10% 5-yr LR). Median f/u 5.1y; cumulative incidence with death as competing event.
Women ≥70y, ER ≥50%, HER2-negative, ≤1cm grade 1/2 or ≤2cm grade 1, free margins, after BCS with no RT and no ET. Median age 73.6y.
Primary: 5-yr LR, a histologically confirmed invasive ipsilateral event. Secondary: contralateral BC, OS, BC-specific survival.
5-yr LR 14.8% (95% CI 12.3-17.5), exceeding the prespecified 10% threshold. 2 of 81 deaths BC-related.
| Endpoint | Result |
|---|---|
| Local recurrence (invasive ipsilateral) | 123 pts · 5-yr 14.8% (95% CI 12.3-17.5) |
| Contralateral BC | 32 (4.0%) |
| Deaths, any cause | 81 (10.2%) |
| Deaths, BC-related | 2 (2.5% of deaths) |
PRIME II and CALGB 9343 supported RT omission in older women who received ET; TOP-1 tests the population that skips both. The trial's own benchmark is a national registry LR of 1.3% with RT, not a randomized arm.
Only invasive ipsilateral events counted, so DCIS recurrence is excluded from the primary. Registry comparator differs in era and selection, and ER+ low-grade recurrences accrue well beyond 5y.
Dropping both adjuvant therapies failed the study's own safety bar, while salvage remained mostly breast-conserving. The authors keep RT omission as a shared-decision option, but the result does not show which omitted therapy drove the excess.
Single-arm observational cohort against a historical registry benchmark; no concurrent RT or ET arm, and 5.1y f/u is short for low-grade ER+ recurrence kinetics.
- LR with ET alone after RT omission in this exact population n=1167 · primary completion 2027-09 · RT vs observation after BCS + planned ET, luminal An=202 · primary completion 2028-05 · ET alone, no RT; postmenopausal HR+ HER2-, RS ≤18
- Breast cancer-specific survival impact beyond 5 years
- Genomic or biomarker selection for safe omission of both RT and ET
📚 Sources · 📄 2 papers
Abstract
Abstract
KEYNOTE-975 NCT04210115
ForUntreated unresectable locally advanced ESCC/EAC/GEJ, dCRT candidates
HR 0.97
95% CI 0.77-1.23, P=0.3994; not met (boundary 0.0193)
TL;DREFS HR 0.97 (95% CI 0.77-1.23), median 15.2 vs 14.7 mo in PD-L1 CPS ≥10: no EFS gain adding concurrent pembro to dCRT in unresectable esophageal/GEJ cancer.
The trial failed in the enriched PD-L1 CPS ≥10 group, where IO was most likely to help, and the curves sat on top of each other (EFS HR 0.97, OS HR 1.00) at 47.1 mo median f/u. Grade 5 AEs ran 13% vs 10%, so concurrent pembro with 50-60 Gy dCRT adds toxicity without benefit. This leaves dCRT alone as the backbone.
In untreated unresectable esophageal or GEJ cancer going to dCRT, including PD-L1 CPS ≥10, this does not support concurrent pembrolizumab; it does not address consolidation-only IO after dCRT or the resectable trimodality setting. The longer read
Concurrent pembro with 50-60 Gy dCRT did not move EFS (HR 0.97) or OS (HR 1.00) in CPS ≥10 pts, and grade 5 AEs rose to 13% vs 10%. No local control or dose-stratified data in source, so the RT backbone stays dCRT alone with no IO-driven change to dose or volume.
PD-L1 CPS ≥10 enrichment did not rescue concurrent pembro (EFS HR 0.97, OS HR 1.00), and AE discontinuation rose to 34% vs 27%. Biomarker selection does not justify adding PD-1 blockade to dCRT; consolidation-only timing remains untested by this trial.
9 details
International phase 3, randomized 1:1, double-blind, placebo-controlled, multicenter; N=703. Results are from the second interim analysis (IA2), after which the study was stopped. Median follow-up 47.1 mo.
Previously untreated locally advanced unresectable ESCC, EAC or GEJ cancer (cTX N+ M0 or cT2-T4a NX M0), or cervical/upper thoracic EC with supraclavicular nodal M1 only. ECOG 0-1, ineligible for curative surgery but suitable for dCRT.
Pembro 200 mg or placebo Q3W for 8 cycles, then 400 mg or placebo Q6W for 5 cycles, concurrent with dCRT. Chemo backbone FP or FOLFOX by site choice.
50 Gy or 60 Gy with FP, or 50 Gy with FOLFOX, by site choice. Fractionation, technique and target volume not reported in source.
Dual primary: investigator-assessed EFS and OS, tested hierarchically in PD-L1 CPS ≥10, CPS ≥1, then all pts.
EFS not improved in CPS ≥10 (arm-level numbers in table), so every downstream comparison went untested and the study was stopped.
| Endpoint (CPS ≥10) | Pembro + dCRT | Pbo + dCRT | HR (95% CI), P |
|---|---|---|---|
| Median EFS (investigator) | 15.2 mo | 14.7 mo | 0.97 (0.77-1.23), P=0.3994; boundary 0.0193 |
| Median OS | 32.2 mo | 35.0 mo | 1.00 (0.77-1.30), nominal P=0.5003 |
| AE | Pembro + dCRT | Pbo + dCRT |
|---|---|---|
| Grade ≥3 | 100% | 100% |
| Grade 5 | 44 (13%) | 37 (10%) |
| Discontinuation for any AE | 117 (34%) | 97 (27%) |
Grade ≥3 AEs in 100% of both arms. Grade 5 AEs 44 (13%) vs 37 (10%), AE discontinuation 117 (34%) vs 97 (27%). Authors report no new safety signals.
Joins KUNLUN (durvalumab + dCRT) as a negative concurrent IO-dCRT trial in esophageal cancer. Adjuvant nivolumab per CheckMate 577 belongs to the resected trimodality setting and is untouched by this result.
RT dose and chemo backbone by site choice with no outcome breakdown, pooled histologies, and no local control or failure-pattern data in source to show whether IO changed in-field control.
A flat EFS and OS in the PD-L1-enriched group argues against a hidden benefit in the untested CPS ≥1 or all-comer groups. Whether timing (consolidation vs concurrent) or histology matters stays open.
CONSORT flow
Double-blind phase 3 stopped at IA2 after the gatekeeper EFS endpoint failed in the enriched CPS ≥10 group; reaffirms dCRT alone as standard. Downstream populations formally untested.
- Would consolidation-only IO after dCRT differ from concurrent dosing?
- Histology-specific EFS in ESCC vs EAC/GEJ
- Did pembro alter local control or failure patterns?
📚 Sources · 📄 1 paper
Abstract
APCCC 2026: High-risk Localised, Locally Advanced, and Biochemically Recurrent PC
TL;DRConsensus (≥75%) reached on 44 of 134 questions (32.8%); fractionation for high-risk localised PC reached no consensus despite 88% favoring some hypofractionation.
HEATENZARADSTAMPEDEHYPO-RT-PCSHARPATLASPEACE-7THUNDER
Fractionation drew 88% for some form of hypofractionation but no consensus on which form, and 44 panellists abstained or declared themselves unqualified. Moderate hypofractionation (2.5–3.4 Gy/fx) is framed as the established option. SBRT for high-risk disease rests on non-randomised SHARP pooling, with 5-yr G2 GU toxicity of 23%, so it stays a trial question.
In very high-risk cN0 PC planned for RT + long-term ADT, panel opinion (65–71%) favors adding 2 yr abiraterone over enzalutamide. This does not settle the choice between ultrahypofractionation and moderate hypofractionation for high-risk disease. The longer read
Fractionation reached no consensus: 88% favored some hypofractionation, and 44 panellists abstained. Moderate hypofractionation (2.5–3.4 Gy/fx) is the established option, while SBRT for high-risk disease rests on non-randomised SHARP pooling. DIL focal boost up to 95 Gy over 77 Gy/35 fx is presented as validated dose escalation.
In very high-risk cN0 disease, 65–71% backed 2 yr abiraterone with RT + long-term ADT, and very few backed enzalutamide, tracking ENZARAD's null MFS (HR 0.88). A combined 83% would stop ADT after 2 yr with abiraterone. ATLAS, PEACE-7, THUNDER and DASL-HiCaP will test other ARPIs.
32–38% favored surgery as part of a multimodal approach for high-risk cN0 disease. The panel reached consensus against perioperative ADT + ARPI before RP, but voted before PROTEUS (pCR/MRD 8.9% vs 1.0%) was presented, so that position may shift.
9 details 3 trials watching
Modified Delphi process: 144 international experts drafted 313 multiple-choice questions, 134 on high-risk localised / locally advanced PC, PSA persistence and recurrence. 133 panellists voted by web survey before the conference.
Consensus defined a priori as 75% agreement, strong consensus 90%. Consensus reached on 44 of 134 questions (32.8%), seven of them strong.
No consensus on fractionation (Q19) despite a combined 88% favoring some hypofractionation. Moderate hypofractionation (2.5–3.4 Gy per fraction) is named as an option. MRI-defined DIL focal boost up to 95 Gy over 77 Gy in 35 fractions is described as validated in a randomised trial.
Very high-risk disease: RT + long-term ADT (2–3 yr) with the option of abiraterone for 2 yr. A combined 83% voted ADT can be stopped after 2 yr with abiraterone in most or selected pts (Q7).
The intensification votes follow STAMPEDE over ENZARAD, whose null MFS (HR 0.88, 95% CI 0.67–1.15) came in a lower-risk population. ATLAS, PEACE-7, THUNDER and DASL-HiCaP are testing other ARPIs in this setting.
44 panellists abstained or declared themselves unqualified on fractionation, which shrinks the informed denominator. The Q6 vote against perioperative ADT + ARPI before RP predates PROTEUS, which was presented and published after the conference.
The panel accepts RT and multimodal surgery as defensible for high-risk cN0 disease without settling the comparison. Its abiraterone-not-enzalutamide vote is drug-specific, not a class effect, and the ongoing ARPI trials will decide whether that distinction holds.
| Question | Setting | Panel vote |
|---|---|---|
| Q1–Q2 | High-risk cN0 M0 (conventional or next-gen imaging) | RT + long-term ADT ± ARPI 62–68%; surgery as multimodal 32–38% |
| Q3–Q4 | Very high-risk cN0 M0 | RT + long-term ADT + abiraterone 2 yr 65–71%; very few for enzalutamide |
| Q5 | Neoadjuvant systemic therapy before RT | Selected or most pts, combined 83%+ (87% combined) |
| Q6 | Perioperative ADT + ARPI before RP | Consensus against |
| Q7 | Stop ADT after 2 yr with abiraterone | Most or selected pts, combined 83% |
| Q19 | Fractionation, high-risk localised / locally advanced | No consensus; combined 88% some hypofractionation; 44 abstained / unqualified |
- Can other ARPIs replace abiraterone in very high-risk localised PC? recruiting Relugolix and Enzalutamide in Combination With Radiation Therapy for the Treatment of Very High Risk Prostate Cancer, OPTIMAL Trial Phase 2n=50 · primary completion 2030-11 · ph2 enzalutamide + relugolix + RT, NCCN very-high-risk
- Role of SBRT in high-risk localised PC n=146 · primary completion 2024-02 · randomised ph2 SBRT ± ADT, NCCN IR/HR, PET N0M0n=90 · primary completion 2028-08 · ph2 SBRT ± brachy boost + 6mo ADT in NCCN high-risk
- Does PROTEUS change the stance on perioperative ARPI before RP?
📚 Sources · 📄 1 paper
EORTC 1420 Best-of NCT02984410
ForT1-T2 N0-1 OPSCC/SGSCC or T1 N0 HPSCC, fit for TOS or RT
+3.9 points
90%CI -2.7 to +10.5; p=0.326, not met
TL;DR12-mo MDADI adjusted difference +3.9 points (90%CI -2.7 to +10.5; p=0.326), TOS vs DO-IMRT; no swallowing difference, more mucosal toxicity with DO-IMRT.
The RT cost is mucosal, not swallowing: DO-IMRT carried mucositis 39% vs 10%, dry mouth 49% vs 14% and dysgeusia 46% vs 17%, against TOS hemorrhage 5% and fistula 2%, with G≥3 TRAEs 21% each. DO-IMRT dose, fractionation and target volume are not reported in source, so dysphagia-sparing constraints cannot be benchmarked.
In T1/T2 N0-1 oropharyngeal or supraglottic, or T1 N0 hypopharyngeal carcinoma fit for either modality, this supports choosing TOS or DO-IMRT on toxicity profile and preference rather than expected 12-month swallowing; it does not address T3-T4 or N2+ disease. The longer read
DO-IMRT's cost is mucosal: mucositis 39% vs 10%, dry mouth 49% vs 14%, dysgeusia 46% vs 17%, with G≥3 TRAEs 21% each. Dose and constraints are not reported in source, and 7/44 declined RT, so the arm's swallowing estimate rests on 64% evaluable.
All TOS pts were operated, with hemorrhage 5% and fistula 2%. Numerically higher 6-mo CR (98% vs 82%) and 2y EFS (84% vs 72%, HR=1.64, 95%CI 0.77-3.50) are not significant, so oncologic superiority of TOS is not established.
10 details 1 trial watching
Phase III, randomised 1:1, 25 centres in 9 countries, accrual 2018-2024. Powered (80%, alpha 10% two-sided) for a 10-point MDADI difference; 54 evaluable needed, 84 planned for 35% attrition, 86 randomised.
T1/T2 N0-1 OPSCC/SGSCC or T1 N0 HPSCC suitable for either TOS or DO-IMRT. Median age 64, 86% OPSCC, 49% HPV-positive; arms balanced.
Dysphagia-optimized IMRT (DO-IMRT). Dose, fractionation and target volumes not reported in source. 7/44 (16%) allocated to DO-IMRT declined treatment.
Primary: MDADI total score at 12 months (ANCOVA). Secondary: MDADI at 4.5, 6 and 9 months, PSS-HN, oncological outcomes, toxicity.
12-mo MDADI adjusted difference +3.9 points (90%CI -2.7 to +10.5; p=0.326), consistent across sensitivity analyses. Arm-level secondary outcomes are in the table.
| Endpoint | TOS | DO-IMRT | Effect |
|---|---|---|---|
| Unrestricted diet (PSS-HN) at 12 mo | 87% | 83% | n/a |
| Feeding tube at 12 mo | None | None | n/a |
| Complete response at 6 mo | 98% | 82% | n/a |
| 2y EFS | 84% | 72% | HR=1.64 (95%CI 0.77-3.50), p=0.200 |
| OS | 97% | 100% | n/a |
| G≥3 treatment-related AEs | 21% | 21% | n/a |
| AE | TOS | DO-IMRT |
|---|---|---|
| Mucositis | 10% | 39% |
| Dry mouth | 14% | 49% |
| Dysgeusia | 17% | 46% |
| Hemorrhage | 5% | n/a |
| Fistula | 2% | n/a |
G≥3 treatment-related AEs 21% in each arm. TOS: hemorrhage 5%, fistula 2%. DO-IMRT vs TOS: mucositis 39% vs 10%, dry mouth 49% vs 14%, dysgeusia 46% vs 17%.
ORATOR randomised TORS against RT in OPSCC and also found comparable function with different toxicity profiles. Best-of extends the comparison to supraglottic and hypopharyngeal primaries and to a phase III frame, but still with a small N.
The EFS HR CI (0.77-3.50) is wide and follow-up reaches only 2 years. A 49% HPV-positive mix limits transfer to HPV-positive de-escalation. RT technique is unreported, so the DO-IMRT arm cannot be audited.
With swallowing function apparently similar, toxicity profile and patient preference become the deciding factors. The numerically lower CR and EFS in the DO-IMRT arm (98% vs 82%; 84% vs 72%) are not significant and may partly reflect pts who declined RT, so they need longer follow-up before they carry weight.
CONSORT flow
Phase III, but differential 12-mo MDADI evaluability (86% vs 64%) and 16% refusal of DO-IMRT; CI does not exclude the 10-point margin, so equivalence is not shown.
- Does the EFS gap persist with longer follow-up?
- Swallowing function beyond 12 months n=150 · primary completion 2031-06 · MDADI at 2y, transoral resection vs IMRT, T1-T2 OPSCC
- Does HPV status modify the TOS vs RT comparison?
📚 Sources · 📄 1 paper
Abstract
HDR brachytherapy with custom-made surface molds for facial skin carcinomas
ForFacial BCC/SCC, primary or post-surgical recurrence, node-negative
TL;DR5y actuarial LC 98% overall (99% primary, 87% recurrent) in 136 facial BCC/SCC treated with HDR Ir-192 surface molds, no severe late complications.
The RT read is geometry plus fractionation: a custom PMMA mold held dose at 5 mm depth within 5% of prescription over curved facial surfaces, with 180 cGy fractions to 6000-6500 cGy and no severe late effects. Whether that conformality keeps its late-toxicity profile with fewer, larger fractions was not tested here.
In node-negative BCC/SCC on curved facial skin (nose, eyelid, ear) where an electron or orthovoltage field fits poorly, this supports HDR surface-mold brachytherapy as a conformal RT option; it does not inform hypofractionated mold schedules or deeply invasive lesions. The longer read
A custom PMMA mold held dose at 5 mm depth within 5% of prescription over curved facial anatomy with a sharp edge gradient, giving 99% 5y LC in primaries and no severe late effects at 180 cGy per fraction. It supports molds for non-flat sites; transfer to short-course schedules is untested.
14 details
Prospective single-institution series, 136 consecutive pts treated 1992-1997 in Barcelona. Minimum follow-up 12 mo; median follow-up not reported.
Pathologically confirmed facial BCC (102) or SCC (34), 73 primary and 63 recurrent after prior local therapy. Gross tumor left in place in most; margins positive in 128. No nodal or distant disease on CT head/neck and chest X-ray.
HDR Ir-192 via 117 custom PMMA molds (3-7 parallel catheters, 5 mm bolus layer) or 19 Brock applicators. 6000-6500 cGy in 33-36 fx of 180 cGy at 5 mm depth; lesions ≥4 cm boosted 1800 cGy/10 fx after a 3-wk rest to 7500-8000 cGy. Eye shielded with a 5 mm lead sheet in the mold.
All pts complete responders; 3 local recurrences (1/73 primary, 2/63 recurrent). 5y actuarial LC 98% overall, 99% primary, 87% recurrent; no regional or distant failure.
| Group | N | Local recurrences | 5y actuarial LC |
|---|---|---|---|
| All pts | 136 | 3 | 98% |
| Primary tumors | 73 | 1 | 99% |
| Recurrent tumors | 63 | 2 | 87% |
| Previously untreated >4 cm | 16 | 1 | 91% |
| Timepoint | Good/excellent cosmesis |
|---|---|
| 2 wk | 38% |
| 3 mo | 92% |
| 6 mo | 98% |
Erythema G1 in 117 and G2 in 19; 14 (10%) had G1 ulceration at 6 wk, all healed by 4 mo. Good/excellent cosmesis 98% at 6 mo; no severe late complications.
Primary-tumor LC of 99% sits alongside the 95% superficial X-ray result in the Lovett EBRT series and above Lovett's 77% with electrons. Daly's Ir-192 interstitial implants reached 96% LC but with 18% severe late effects, the toxicity gap the mold approach is designed to close.
Dose per fraction (180 cGy) far from modern short-course skin brachy, so the late-effect profile may not transfer. Recurrent-tumor LC timepoint reported inconsistently (5y vs 4y), and cosmesis was graded by the treating team.
The contribution is technical: a reproducible, afterloaded surface applicator that conforms to non-flat facial anatomy with a sharp edge gradient. It shows high control with conventional fractionation but does not settle how it compares head-to-head with superficial X-ray, electrons, or Mohs.
Single-arm single-institution series without a comparator; follow-up minimum only 12 mo with median unreported; comparisons rest on historic EBRT and implant series.
- Does late cosmesis hold with hypofractionated HDR mold schedules?
- Head-to-head vs superficial X-ray or electrons on curved facial sites
- Durability of control beyond 5 years in recurrent lesions
📚 Sources · 📄 1 paper
Fractionated HDR brachytherapy moulds for carcinoma of the pinna
ForSuperficial BCC/SCC of the pinna, no cartilage invasion
TL;DR13 pts with superficial pinna carcinoma treated with HDR moulds, 45 Gy/8 fx: complete resolution in all, no recurrences at minimum 18 mo f/u.
The transferable parameter is ultrasound-guided mould height: measuring tumour depth (0.84 mm in one case) lets the 80% isodose cover disease while leaving cartilage outside, which electrons cannot do for lesions thinner than 12 mm. Full-thickness cases needed a sandwich mould at reduced dose (42.5 Gy), so cartilage sparing is the selection criterion.
In superficial BCC or SCC confined to pinna skin without cartilage invasion on ultrasound, this supports an HDR surface mould as a cartilage-sparing RT option; it does not address lesions requiring full-thickness pinna irradiation. The longer read
The transferable parameter is ultrasound-guided mould height: measuring tumour depth (0.84 mm in one case) lets the 80% isodose cover disease while leaving cartilage outside, which electrons cannot do for lesions thinner than 12 mm. Full-thickness cases needed a sandwich mould at reduced dose (42.5 Gy).
13 details
Retrospective single-institution series of 13 pts treated at the Christie Hospital up to July 1996. Technique description with three illustrative cases.
9 BCC, 3 SCC, 1 intraepidermal carcinoma. Lesion confined to pinna skin; dermal ultrasound confirmed cartilage not invaded in all but one.
HDR microselectron with single stepping iridium source via custom vacuum-formed mould. 45 Gy in 8 fx over 5 days prescribed to the surface, mould height set so tumour depth lies within the 80% isodose. Sandwich mould case reduced to 42.5 Gy.
Complete tumour resolution in all pts, barely perceptible scar. No recurrences and no late complications over minimum 18 mo f/u.
Moderate cutaneous erythema limited to the high-dose area, settled by the 6 wk visit. No discernible reaction on the contralateral pinna skin.
Authors position moulds against electrons (poor fall-off for thin lesions, cartilage necrosis risk), 30 kVp X-rays (dose inhomogeneity on curved surfaces, limited availability) and surgery (amputation or excision with graft). No head-to-head data.
Outcomes reported as a blanket statement without per-pt f/u, actuarial LC, or a validated cosmesis scale. Late cartilage toxicity can emerge beyond 18 mo, and the LQ-based BED rationale assumes complete repair between fractions.
The contribution is technique, not efficacy: ultrasound depth measurement plus tunable source height makes the plan conformal to sub-millimetre tumour thickness. Whether a higher late-tissue BED is tolerated because of the small volume is asserted, not shown.
Single-institution case series of 13 selected pts, no comparator, 18 mo minimum f/u too short for late cartilage effects; outcomes descriptive only.
- Late cartilage toxicity beyond 18 months
- Local control vs surgery or electrons in matched pts
📚 Sources · 📄 1 paper
Skin surface brachytherapy practice-pattern survey
ForBCC and cSCC treated with skin surface brachytherapy
TL;DR16 ABS respondents: gross-disease margin 3-15mm (median 5mm), doses 30 Gy/5fx to 64 Gy/32fx (EQD2 40-65 Gy), no consensus on dosimetric constraints.
The transferable read is pretibial dosing: 10 respondents (63%) dropped to 2-3 Gy per fraction there, and eight reported severe toxicity on the lower extremity. With max skin dose ranging 125-150% and fractionation cut points spanning 2-5 cm, a reader building a skin HDR program has a variance map, not a constraint set.
For a BCC or cSCC on the pretibial skin, this survey supports treating site as a reason for gentler fractionation; it does not inform lesions deeper than 3 mm or with perineural invasion, which respondents steered away from brachytherapy. The longer read
The transferable read is pretibial dosing: 10 respondents (63%) dropped to 2-3 Gy per fraction there, and eight reported severe lower-extremity toxicity. Max skin dose 125-150% and fractionation cut points of 2-5 cm mean a skin HDR program must set and audit its own constraints.
12 details
30-question electronic survey sent to ~400 American Brachytherapy Society clinician members. 16 fully completed surveys analyzed; one incomplete survey excluded. Nearly all US respondents, one from Spain.
Radiation oncologists using skin surface brachytherapy for cSCC and BCC. Practice settings spanned academic, hospital-based and private; aggregate experience ranged 8 to 1800 cases.
Hypofractionation preferred; clinical-scenario doses ranged 30 Gy in 5 fractions to 64 Gy in 32 fractions (EQD2 40 Gy-65 Gy). Median max prescription depth 5 mm; shielded applicators most common, custom molds for large or curved areas. Respondents avoided daily schedules when hypofractionating.
Margin on gross disease 3-15mm, median 5mm. Max skin dose 125-150% (median 135%) of prescription; CTV coverage 90-100% (median 95%). No consensus on dosimetric constraints.
| Parameter | All respondents | >100 cases in career |
|---|---|---|
| Max dose at skin surface | 13 (81%) | 7 (78%) |
| Min dose to CTV | 8 (50%) | 3 (33%) |
| Depth of 90% isodose line | 6 (38%) | 3 (33%) |
| Min dose to skin surface | 5 (31%) | 4 (44%) |
| V150 | 4 (25%) | 2 (22%) |
| D95 | 2 (13%) | 1 (11%) |
Eight respondents described severe acute and late toxicity on the lower extremity, especially pretibial skin. Three referred non-healing in-field ulcers for hyperbaric oxygen.
The cited prior literature (Guix custom-mold HDR, Paravati electronic brachytherapy, van Hezewijk hypofractionated electrons) reports single-series outcomes. This survey adds no outcomes; it documents how widely dose, margin and constraints vary across practices using the technique.
Several key tables carry ambiguous row-value pairing in the source, and the scenario table (Table 4) was not captured. Toxicity is anecdotal recall with no denominators.
The useful output is the spread itself: margins, skin-dose ceilings and the lesion-size threshold for gentler fractionation all vary several-fold. Prospective trials and expert consensus are what the authors call for, and this survey cannot substitute for either.
Practice survey of 16 self-selected respondents; no efficacy or toxicity endpoints measured, so the authors' 'convenient and safe' conclusion is not testable from this design.
- Which dosimetric constraints predict late skin toxicity?
- Optimal fractionation for pretibial and lower-extremity lesions
- Brachytherapy vs electrons or orthovoltage for cosmesis
📚 Sources · 📄 1 paper
CT-based flap brachytherapy for facial non-melanoma skin cancers
ForT1 facial BCC/SCC (area H/M), elderly, surgery-unfit or refusing
TL;DR1-yr KM local control 92% after HDR flap brachy 40 Gy/8 fx twice weekly for T1 facial BCC/SCC; no chronic G≥3 toxicity.
The dosimetry is the transferable part: median V100 85% and D90 92% with catheters 5 mm off the skin, against tumors up to 7 mm thick, so deep-margin coverage is the weak point. Three of 4 recurrences were nose, eyelid and lip, the irregular sites the flap is meant to solve.
In an elderly pt with T1 BCC or SCC of the nose, eyelid or temple who declines or cannot tolerate Mohs, this supports CT-planned flap HDR 40 Gy/8 fx as a reasonable option; it does not address pts fit for surgery or lesions thicker than 7 mm. The longer read
The dosimetry is the transferable part: median V100 85% and D90 92% with catheters 5 mm off the skin, against tumors up to 7 mm thick, so deep-margin coverage is the weak point. Three of 4 recurrences were nose, eyelid and lip, the irregular sites the flap is meant to solve.
12 details
Single-institution retrospective review, January 2007 to December 2018. 50 pts, 53 lesions, minimum 6 mo follow-up, median follow-up 15 mo (range 6-27). LC by Kaplan-Meier.
Histologically confirmed BCC or SCC, AJCC 8th T1, all NCCN high-risk by area H or area M location. Median age 80; selected by a multidisciplinary dermatology clinic, mostly for inability to tolerate or refusal of surgery.
40 Gy in 8 fractions twice weekly (BED 60 Gy, α/β 10) via Ir-192 HDR catheter flap, CT-planned in BrachyVision. CTV = visible tumor + 5 mm, PTV = CTV with no margin; 5 mm spacers protected the nasal mucosa, globe and gingiva.
1-yr LC 92%, 4 local recurrences, 3 in nose/eyelid/lip. 49 lesions (92%) had good/excellent cosmesis with complete remission.
| Toxicity | n (%) |
|---|---|
| Acute G1 (erythema) | 32 (60%) |
| Acute G2 | 19 (35%) |
| Acute G3 (moist desquamation) | 3 (5%) |
| Chronic G1 at 6 mo | 5 (10%) |
| Chronic G1 hypopigmentation at 12 mo | 2 (4%) |
| Chronic G2 telangiectasia at 12 mo | 2 (4%) |
Acute G1 60%, G2 35%, G3 5%, all after fraction 5. Chronic G2 telangiectasia in 2 pts (4%) at 12 mo, no chronic G≥3, no toxicity-related hospitalization.
Local control falls inside the 87%-100% range of prior retrospective HDR surface-mold series. The only randomized surgery-vs-RT trial in facial BCC cited by the authors found 4-yr failure 7.5% vs 0.7% favoring surgery, though RT there was mostly interstitial brachy, not surface HDR.
Median V100 85% falls short of the ≥95% PTV coverage goal, and depth was assessed mostly by palpation. Abstract and body disagree on acute toxicity grade, and the Discussion understates chronic G2 events.
The flap's value is conformity on irregular surfaces where surface molds and electrons struggle, yet recurrences clustered in exactly those sites. BCC and SCC got identical dose and margins, consistent with NCCN, the 2020 ASTRO guideline and the 2019 ABS consensus, so histology-specific dosing is still untested.
Single-arm retrospective series, surgery-unfit/refusing pts, 15-mo median f/u; no comparator vs Mohs or EBRT. Consistent with prior HDR surface-mold series.
- Durability of local control and late cosmesis beyond 2 years
- Histology-specific dose or margin for BCC vs SCC
- Surface HDR brachytherapy vs Mohs or EBRT head to head
📚 Sources · 📄 1 paper
Bladder preservation after neoadjuvant/perioperative therapy in MIBC (reTURBT cohort)
ForMIBC cT2-4N0M0 urothelial, post-neoadjuvant IO/ADC, declining RC
TL;DRypT0Nx at reTURBT after neoadjuvant therapy: 24-mo EFS 87.6%, OS 96.7% in MIBC pts declining RC (n=54); non-pCR pts fared far worse.
Chemo-RT here was only salvage for residual tumor or recurrence, so this tests a bladder-sparing route that skips upfront RT. The split is stark: non-pCR at reTURBT gave 24-mo OS 50.4% vs 82.5% after RC, so residual disease at reTURBT is the point where definitive local therapy (RC or chemoRT) should be on the table.
In an MIBC pt with ypT0 at reTURBT plus negative MRI and cytology after IO-based neoadjuvant therapy who declines RC, this supports surveillance as a discussable option; it does not extend to pts with any residual disease at reTURBT. The longer read
Chemo-RT was used only as salvage for residual tumor or recurrence, so this tests bladder sparing without upfront RT. Non-pCR at reTURBT gave 24-mo OS 50.4% vs 82.5% after RC, marking residual disease as the point where definitive local therapy, including chemoRT, belongs.
Response at reTURBT after pembrolizumab-, SG- or nivolumab-based neoadjuvant therapy separated outcomes sharply: 24-mo EFS 87.6% with ypT0 vs 19.3% with residual disease. Depth of response to the systemic regimen, not the regimen label, drove eligibility for surveillance.
ypT0 at reTURBT pts who declined RC had 24-mo OS 96.7%, but EFS HR 1.96 (0.53-7.27) vs RC pCR is too imprecise to call equivalence. Residual disease at reTURBT tracked with far worse outcomes than RC, keeping cystectomy the default for incomplete responders.
| Group | 24-mo EFS | 24-mo OS |
|---|---|---|
| reTURBT pCR | 87.6% | 96.7% |
| reTURBT vs RC, pCR (HR) | 1.96 (0.53-7.27) | 0.90 (0.10-8.40) |
| reTURBT non-pCR | 19.3% | 50.4% |
| RC non-pCR | 67.8% | 82.5% |
+2 more figures

13 details 3 trials watching
Pooled cohort from four neoadjuvant/perioperative trials (PURE-01, SURE-01, SURE-02, NURE-Combo), N=279 enrolled 02/2017-07/2025. Bladder preservation was pt choice, not a randomized allocation.
MIBC cT2-4N0M0, pure/predominant (≥50%) urothelial carcinoma. The reTURBT group (n=54) declined RC and required negative imaging, biopsy and cytology.
Pembrolizumab, sacituzumab govitecan, SG + pembrolizumab, or nivolumab + nab-paclitaxel, restaged with CT + multiparametric bladder MRI. Adjuvant/maintenance per protocol; deferred RC or chemo-RT only for residual tumor or recurrence.
Whole reTURBT group: 36-mo EFS 66.7%, 36-mo OS 82.7%; 19% recurred, 13% distantly. Outcomes split sharply by response at reTURBT (Fig 2).
The comparator is the trials' own RC cohort, not a randomized arm. Trimodality therapy, the established bladder-sparing alternative, was not a planned arm here; chemo-RT appears only as salvage.
Four different regimens pooled into one small cohort. The tweet's comparison claim is truncated, and the 30/54 (56%) vs 43/213 (20%) schema figure carries no endpoint label in the source.
The pCR stratum looks good, but HRs vs RC of 1.96 (0.53-7.27) for EFS and 0.90 (0.10-8.40) for OS are too imprecise to call equivalence. Non-pCR at reTURBT is the clear failure mode and argues for definitive local therapy rather than continued surveillance.
Pts self-selected by declining RC; RC comparison non-randomized, pCR-stratum HR CIs span 1, reTURBT n=54 pooled across four heterogeneous phase 2 regimens.
- Durability of ypT0 at reTURBT beyond 36 months without cystectomy active Stage II-IIIa Urothelial Cancer Randomizing Pre-operative Nivolumab With or Without Relatlimab Phase 2n=90 · primary completion 2026-12 · bladder preservation in responders to nivo±relatlimabactive A Study of Risk Enabled Therapy After Neoadjuvant Immunochemotherapy for Bladder Cancer Phase 2n=81 · primary completion 2027-05 · cCR after AMVAC+nivo then active surveillance
- Would planned chemoRT rescue non-pCR pts at reTURBT? n=20 · primary completion 2027-09 · systemic tx response + genomics assign chemoRT vs RC
- Can ctDNA or MRI better select pts for surveillance?
📚 Sources · 🐦 1 tweet
Bladder preservation after neoadjuvant/perioperative therapy in 🇮🇹 MIBC pts who declined RC and underwent reTURBT (n=54)
— Rashid K. Sayyid (@RKSayyid) October 25, 2026
📌Negative imaging, biopsy & cytology
🔹19% recurred; 13% developed distant recurrence
🔹 ypT0Nx at reTURBT → 24-mo EFS 88%; MFS & OS >95%, comparable with… pic.twitter.com/2I402Cwxa9
STAMPEDE, ENZARAD, PROTEUS and DASL in context
TL;DRESMO26 round-up of four intensification trials. STAMPEDE Decipher update suggests differential abiraterone benefit in cN0 disease (interaction P=.01).
STAMPEDEENZARADPROTEUSDASL
The RT-relevant read is that STAMPEDE's abiraterone benefit was reported as predominantly in pts receiving RT, and the ESMO26 Decipher data suggest the abiraterone benefit differs in cN0 disease (interaction P=.01). Subgroup HRs are not reported in source text, so this flags, rather than settles, genomic selection of who gets abiraterone added to RT.
STAMPEDE's abiraterone benefit was reported as predominantly with RT, so the intensification question sits on the RT backbone. The ESMO26 Decipher interaction in cN0 (P=.01) hints at genomic selection for adding abiraterone to RT; subgroup magnitudes are not in the source.
The Decipher update suggests abiraterone benefit is not uniform in cN0 disease (interaction P=.01), raising biomarker-gated intensification. No subgroup HRs are reported in source, and the ENZARAD, PROTEUS and DASL updates are not described in the truncated tweet.
Also covered Jul 15
7 details
- 🔍 Trade-press-style round-up tweet placing STAMPEDE, ENZARAD, PROTEUS and DASL against #ESMO26 updates
- 🔍 Disease state and RT dose/fractionation not stated in source
- 📊 STAMPEDE: abiraterone-based intensification improved MFS and OS, predominantly with RT, per source
- 📊 New #ESMO26 Decipher data: differential abiraterone benefit in cN0 disease, interaction P=.01
- ⚠️ No effect size reported in source tweet for MFS, OS, or the Decipher subgroups
- ⚠️ Decipher interaction is a biomarker subgroup analysis; hypothesis-generating until validated
- ⚠️ Tweet is truncated; ENZARAD, PROTEUS and DASL updates are not described in the source text
- Does Decipher score select cN0 pts for abiraterone with RT?
- Where do ENZARAD, PROTEUS and DASL fit relative to STAMPEDE?
📚 Sources · 🐦 1 tweet
Putting STAMPEDE, ENZARAD, PROTEUS & DASL into context with the latest #ESMO26 updates:
— Himanshu Nagar (@HimanshuNagarMD) October 24, 2026
STAMPEDE: Abiraterone-based intensification improved MFS AND OS, predominantly with RT. New #ESMO26 Decipher data suggests differential abi benefit in cN0 disease (interaction P=.01); using…
DASL-HiCaP NCT04135353
ForVery high-risk or N1 prostate, radical or early salvage RT + 2y ADT
HR 0.42
95% CI 0.27-0.66, p=0.0001; 4-yr MFS-CI 95% vs 88%
TL;DR4-yr MFS-CI 95% vs 88%, HR 0.42, adding darolutamide to prostate/bed + pelvic LN RT and 96 wk ADT in very high-risk prostate cancer.
Every metastasis-free survival (MFS) difference comes from metastases (9 vs 46). Deaths without prior metastases were 18 vs 17. Both arms got prostate/bed plus pelvic nodal RT with 96 wk ADT, so this is darolutamide on top of an already intensified RT backbone, in both radical and salvage settings. RT dose was not reported.
For a very high-risk patient (GG5, GG4 with adverse T stage or PSA, or cN1/pN1) planned for pelvic nodal RT with 2y ADT, this supports discussing darolutamide intensification. It does not extend to shorter ADT courses or to RT without nodal coverage. The longer read
Darolutamide cut metastases (9 vs 46) even though both arms got pelvic nodal RT and 96 wk ADT, so nodal coverage did not remove the distant-failure risk the drug addresses. The result covers both radical and early salvage RT. Dose/fractionation is not in the source, so it can't be checked against your own regimen.
The secondary endpoints all point the same way: time to CRPC HR 0.22 (0.09-0.52) and subsequent hormonal therapy HR 0.36 (0.21-0.60). This makes darolutamide the ARPI with placebo-controlled data alongside 2y ADT and RT. OS HR 0.88 (0.49-1.59) is still immature.
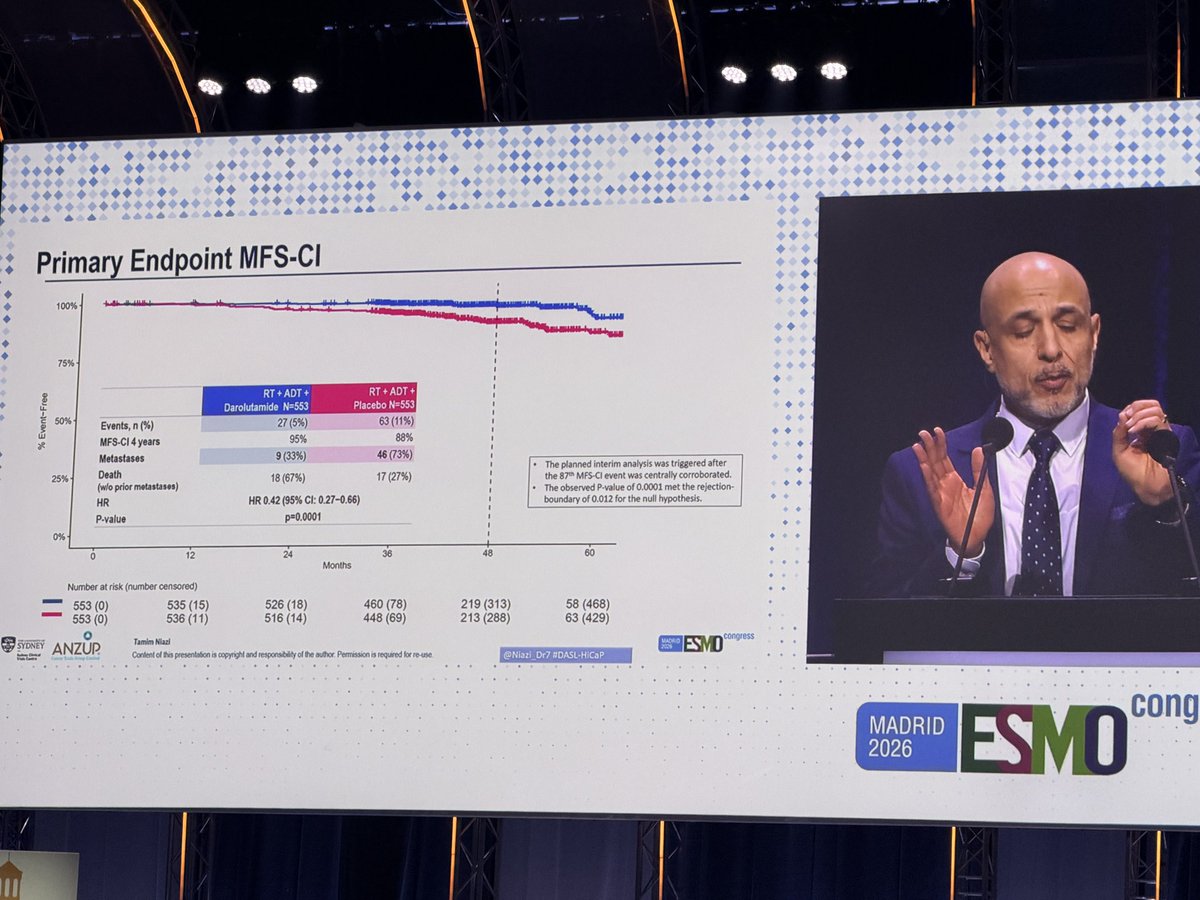
| MFS-CI | RT + ADT + Darolutamide N=553 | RT + ADT + Placebo N=553 |
|---|---|---|
| Events, n (%) | 27 (5%) | 63 (11%) |
| 4-yr MFS-CI | 95% | 88% |
| Metastases | 9 (33%) | 46 (73%) |
| Death (w/o prior metastases) | 18 (67%) | 17 (27%) |
| HR (95% CI), p | 0.42 (0.27-0.66), p=0.0001 | ref |
+2 more figures
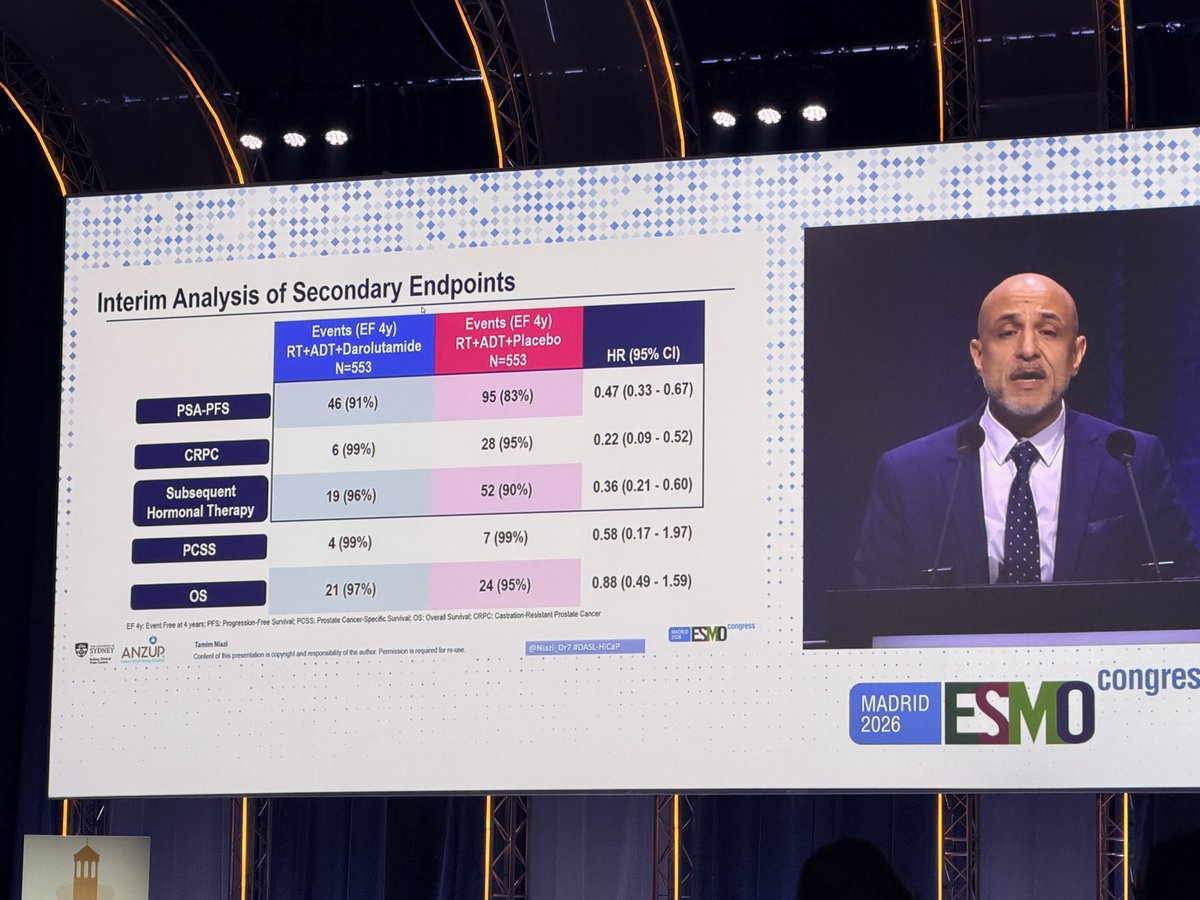
| Secondary endpoint (interim) | HR (95% CI) |
|---|---|
| PSA-PFS | 0.47 (0.33-0.67) |
| CRPC | 0.22 (0.09-0.52) |
| Subsequent hormonal therapy | 0.36 (0.21-0.60) |
| PCSS | 0.58 (0.17-1.97) |
| OS | 0.88 (0.49-1.59) |
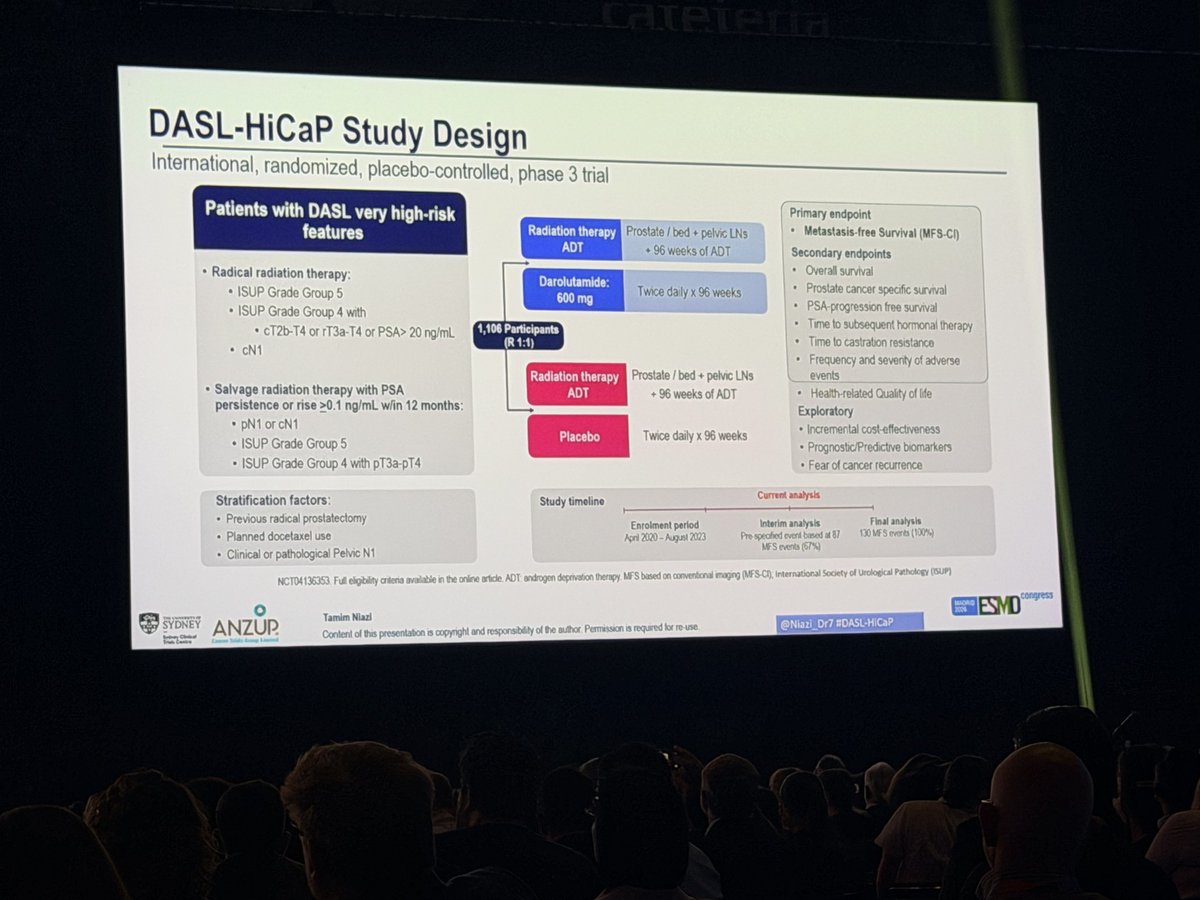
9 details
International, randomized, placebo-controlled phase 3, 1:1, N=1,106. Enrolment April 2020 to August 2023. Interim analysis triggered at the 87th MFS-CI event (67%); final analysis planned at 130 events.
DASL very high-risk pts getting radical RT (ISUP GG5, GG4 with cT2b-T4 / rT3a-T4 / PSA >20 ng/mL, or cN1) or salvage RT for PSA persistence or rise ≥0.1 ng/mL within 12 mo with pN1/cN1, GG5, or GG4 pT3a-pT4. Stratified by prior RP, planned docetaxel, pelvic N1.
Darolutamide 600 mg BID x 96 wk vs placebo. Both arms got 96 wk ADT. Docetaxel use was allowed as a stratification factor.
Both arms: prostate/bed + pelvic LNs. Dose, fractionation and imaging used for staging are not reported in the source.
Primary: MFS by conventional imaging (MFS-CI). Secondary: OS, PCSS, PSA-PFS, time to subsequent hormonal therapy, time to castration resistance, AEs, HRQoL.
Primary met at interim, HR 0.42 (0.27-0.66), p=0.0001, against a rejection boundary of 0.012. Authors report the benefit was consistent across all subgroups (no subgroup HRs in source).
Authors describe the treatment burden as similar to placebo. No AE rates or grade breakdown in source.
This sits alongside ENZARAD and the STAMPEDE M0 abiraterone work, which ask the same ARPI-plus-RT intensification question. DASL-HiCaP is the placebo-controlled test, it mandates pelvic nodal RT in both arms, and it includes an early-salvage cohort.
Event-driven interim with only 27 vs 63 events, so the estimate may shrink by the final analysis. MFS is read on conventional imaging, which may not match PSMA-staged practice. Primary vs salvage results are not shown separately.
The drug's effect is on metastases, not competing mortality, which supports a real anticancer benefit. Whether it becomes an OS benefit at PCSS HR 0.58 and OS HR 0.88 is still unknown.
CONSORT flow
Clean placebo-controlled phase 3, but this is the interim analysis (87/130 events). MFS is a surrogate and OS is immature. The prespecified final analysis is the gate.
- Does the MFS benefit translate to OS at final analysis?
- Is benefit similar in salvage vs radical RT cohorts?
- Does the effect hold in PSMA-PET staged pts?
📚 Sources · 🐦 1 tweet
DASL-HiCaP at #ESMO26, presented by @Niazi_Dr7: darolutamide + RT + 2 yrs ADT vs placebo in very high-risk prostate cancer (n=1,106)
— Alan Tan (@alantanmd) October 24, 2026
▪️ MFS HR 0.42, 4-yr MFS 95% vs 88%
▪️ PSA-PFS HR 0.47
▪️ Time to CRPC HR 0.22
▪️ OS immature (HR 0.88)#ProstateCancer pic.twitter.com/pfDHyuM2qW
PROTEUS Substudy
ForHR LPC/LAPC, conventionally staged M0, planned RP + PLND
HR 0.38
95% CI 0.26-0.55, p<0.0001
TL;DREFS HR 0.38 (95% CI 0.26-0.55) with perioperative apalutamide + ADT around RP + PLND in HR LPC/LAPC; MFS HR 0.49, nominal p only.
The testosterone curve is the hidden read: T recovery to ≥200 ng/dL took a median 20.7 mo (~9 mo from EOT), so much of the EFS window is BCF assessed under residual castration. TTST medians of 46.0 vs 12.3 mo carry ~20 mo of lead-time, which leaves the durable-benefit question with MFS and its nominal p=0.0193.
In conventionally staged HR LPC/LAPC headed for RP + PLND, this supports perioperative APA + ADT as an EFS-delaying option under discussion; it does not extend to PSMA PET-staged pts or to men treated with definitive RT. The longer read
Testosterone recovery took a median 20.7 mo (~9 mo from EOT), so the EFS gain is partly measured during residual castration. MFS HR 0.49 with nominal p=0.0193 is the endpoint that will decide whether perioperative APA + ADT changes disease course or only delays PSA events.
The surgical backbone was unchanged (RP + PLND in both arms), and the control arm's adjuvant management was left to physician discretion. Without baseline PSMA PET, some conventionally staged M0 candidates may have had occult disease, which matters when selecting HR LPC/LAPC pts for RP.

| Arm | Median | Rate (95% CI) |
|---|---|---|
| APA + ADT | Not reached | 63.0% (52.2-71.9) |
| RP + PLND alone | 19.1 months | 41.4% (35.6-47.1) |
| HR 0.38 (95% CI 0.26-0.55) | p<0.0001 | n/a |
+3 more figures

| Metastasis detection method, n (%) | APA + ADT | RP + PLND |
|---|---|---|
| PSMA PET | 9 (8.8) | 50 (16.3) |
| Conventional imaging | 1 (1.0) | 6 (2.0) |
| MFS HR 0.49 (95% CI 0.26-0.90) | nominal p=0.0193 | n/a |

| Arm | Median time to first subsequent therapy |
|---|---|
| APA + ADT | 46.0 months |
| RP + PLND alone | 12.3 months |
| HR 0.29 (95% CI 0.20-0.43), nominal p<0.0001 | n/a |
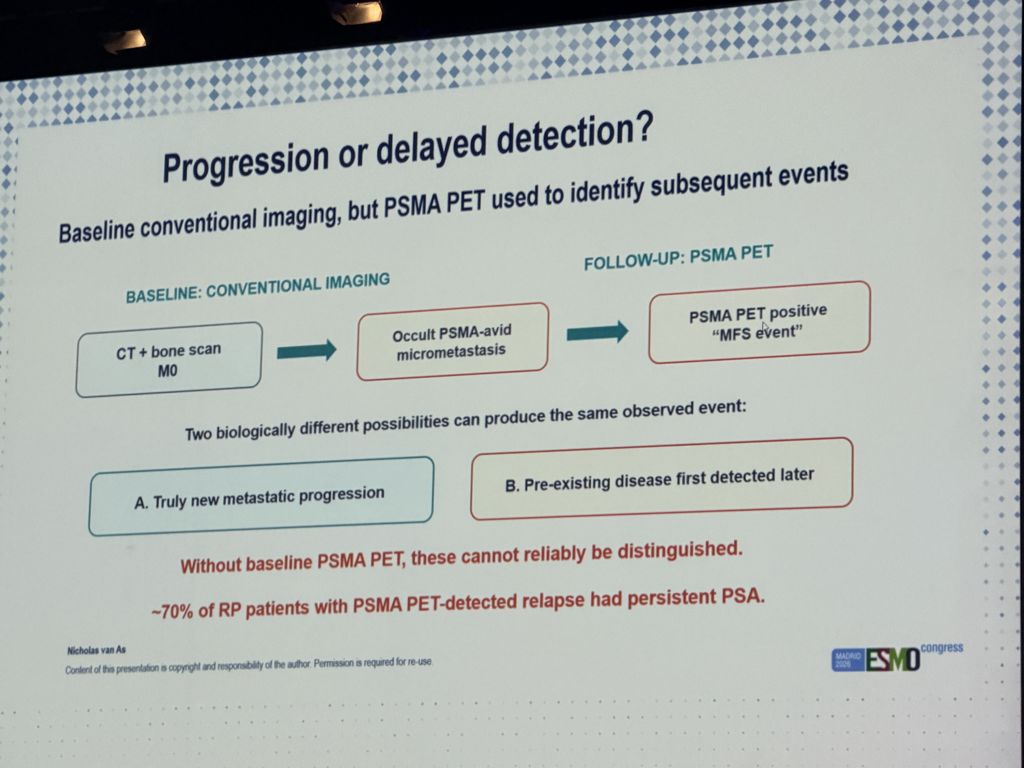
11 details 1 trial watching
Randomized 1:3, open-label, N=408, accrual July 2022 to October 2023. Stratified by cN0 vs cN1, Gleason 7 vs 8-10, and region. Phase not stated in source.
HR LPC/LAPC, conventionally staged M0 (CT + bone scan). No baseline PSMA PET.
APA 240 mg QD + ADT for 6 cycles neoadjuvant, RP + PLND, then 6 cycles adjuvant. Control: RP + PLND with local or systemic adjuvant tx at physician discretion.
Primary: EFS, time to first BCF (PSA progression), LRR, DM or death. Secondary/exploratory: MFS, time to first subsequent therapy.
EFS HR 0.38 (0.26-0.55), p<0.0001; MFS HR 0.49 (0.26-0.90), nominal p=0.0193; TTST HR 0.29 (0.20-0.43), nominal. Per-arm values in the figure captions.
proPSMA showed PSMA PET staging accuracy of 92% vs 65% for CT + bone scan, and EAU/ESMO advise PSMA PET/CT for high-risk disease where available. PROTEUS staged without it, so its M0 population differs from a modern PSMA-staged cohort.
1:3 allocation leaves 102 pts in the experimental arm. The control adjuvant strategy was at physician discretion, so the comparator is heterogeneous. Safety magnitudes were truncated in the source.
Lead-time from treatment exposure and slow testosterone recovery inflate the early-window endpoints. Whether metastatic progression is truly delayed, rather than PSMA-avid disease being detected later, is not settled without baseline PSMA PET.
CONSORT flow
Randomized, EFS met, but EFS leans on PSA failure during slow testosterone recovery; MFS nominal and PSMA-detection driven; TTST lead-time biased; no baseline PSMA PET.
- Does the EFS benefit hold in PSMA PET-staged M0 pts?
- Will MFS reach non-nominal significance with longer follow-up? n=2517 · primary completion 2026-12 · phase 3 parent RCT, MFS 1° EP vs placebo + ADT
- Does any benefit persist after testosterone recovery?
📚 Sources · 🐦 2 tweets
PROTEUS Substudy: Periop Apa + ADT with RP+PLND vs RP+PLND in HR PCa @urotoday #ESMO26
— Zach Klaassen (@zklaassen_md) October 24, 2026
Periop APA + ADT (+ RP+PLND; n= 102) vs RP+PLND alone (n=306)
🚨EFS: HR 0.38, 95% CI 0.26–0.55
🚨MFS: HR 0.49, 95% CI 0.26–0.90
🚨TT 1st Sub Rx: HR 0.29, 95% CI 0.20–0.43
🚨All Gr Hot Flush:… pic.twitter.com/v7zhSfLzrR
#ESMO26 PROTEUS discussion by Nicholas van As
— Alan Tan (@alantanmd) October 24, 2026
• No baseline PSMA PET; enrolled conventionally staged M0
• MFS events: true progression or delayed detection? Most were PSMA PET-detected (8.8% vs 16.3%)
• TTST HR 0.29, but ~20-mo lead-time bias#ProstateCancer pic.twitter.com/FfugtpcYwU
Postoperative endometrial cancer with electronic brachytherapy (Axxent)
ForPostop endometrial cancer, FIGO IA to IVA, adjuvant VBT ± pelvic EBRT
TL;DRAxxent eBT vs replanned Ir-192 HDR: bladder D2cc 63.8% vs 70.1%, rectum 61.2% vs 68.4% of prescription; one G2 acute toxicity in 94 pts.
The prescription copied Ir-192 doses onto a 26 keV source with no RBE adjustment, so the OAR %PD reductions are physical-dose figures and the higher V150/V200 sits at the mucosa. Low acute mucositis at 25 Gy/5 fx and 15 Gy/3 fx is reassuring, but vaginal stenosis and late effects are untested here.
In postop endometrial pts needing vaginal cuff brachytherapy at a centre with no HDR afterloader, this supports eBT as feasible on acute toxicity; it does not inform late vaginal toxicity or cuff control vs Ir-192 HDR. The longer read
Ir-192 prescriptions were applied to a 26 keV source without RBE correction (cited RBE 1.29 to 1.85 at 5 mm), so the bladder and rectal %PD reductions are physical dose and the mucosa carries higher V150/V200. Acute toxicity at 25 Gy/5 fx and 15 Gy/3 fx was low; late vaginal effects remain untested.
11 details
Single-centre series of 94 pts treated with Axxent eBT, Sept 2015 to Oct 2017. Each eBT plan was replanned a posteriori for Ir-192 and Co-60 (282 plans); toxicity scored by RTOG. Mean follow-up 14 mo (4 to 25).
Postoperative endometrial cancer, mean age 65.9 (33 to 84), FIGO IA through IVA. 33 pts (35%) received chemo before RT.
eBT alone 25 Gy/5 fx (n=37, stage IA plus seven IB1) or pelvic EBRT 23 × 2 Gy then eBT 15 Gy/3 fx (n=57), twice weekly. Dose prescribed at 5 mm from a 2.5 to 3.5 cm cylinder; 50 kVp source, TG-43 planning, no RBE correction.
Only one G2 acute event. At 1 month, vaginal G1 5.3%, rectal G1 1.1%, urinary G1 2.1%, no G2.
PORTEC-2 established vaginal brachytherapy as adjuvant RT for high-intermediate risk disease using conventional HDR; this series does not test eBT against that clinical benchmark. A cited multicentre eBT series reported bladder V50% 11.5 ± 9.7% and rectum 17.4 ± 10.9%, in the same range as here.
Higher V150/V200 places hotter dose at the vaginal mucosa, where late stenosis would show and 14 mo cannot capture it. TG-43 without heterogeneity correction may misstate low-energy dose in tissue.
The OAR advantage comes from rapid dose fall-off at low energy, the same property that concentrates dose near the applicator surface. Whether uncorrected RBE translates into more late mucosal toxicity, or whether RBE-based de-escalation would cost control, remains open.
| OAR parameter | Axxent eBT | Ir-192 HDR |
|---|---|---|
| Bladder D2cc (%PD) | 63.8% | 70.1% |
| Bladder V50% | 7.2% | 12.7% |
| Bladder V35% | 15.2% | 28.2% |
| Rectum D2cc (%PD) | 61.2% | 68.4% |
| Rectum V50% | 7.9% | 14.3% |
| Rectum V35% | 16.7% | 32% |
Single-centre uncontrolled series, 14 mo mean f/u; HDR comparison is replanning, not a treated arm; no late toxicity or local control data at meaningful follow-up.
- Late vaginal mucosal toxicity with uncorrected RBE
- Vaginal cuff control vs Ir-192 HDR at longer follow-up
- Should eBT prescriptions be RBE-adjusted?
📚 Sources · 📄 1 paper
Abstract
PORTEC-3 NCT00411138
ForHigh-risk endometrial cancer, FIGO 2009 stage I-III, post-hysterectomy
HR 0.76
95% CI 0.54–1.06, p=0.11, OS not met; co-primary FFS HR 0.71, p=0.022
TL;DR5y FFS 75.5% vs 68.6% (HR 0.71, p=0.022) with CRT over pelvic RT alone; co-primary 5y OS 81.8% vs 76.7% not met (HR 0.76, p=0.11).
Pelvic control was 91% with RT alone, so chemotherapy is not buying locoregional control here; 48.6 Gy pelvic EBRT (plus brachy boost in 47%, balanced by arm) stays the backbone in both arms. The RT question left open is whether pelvic RT can be dropped once chemo is given, which GOG-258 tests and its abstract suggests costs vaginal and nodal control.
In stage III high-risk endometrial cancer, this supports discussing concurrent cisplatin plus adjuvant carboplatin/paclitaxel with pelvic RT for failure-free survival; in stage I-II disease the FFS estimate (HR 0.85, p=0.47) does not clearly justify the added toxicity. The longer read
Pelvic control was 91% with RT alone, so chemo adds nothing locoregionally and 48.6 Gy pelvic EBRT plus indicated brachy boost stays the backbone. The RT decision this trial leaves open is omission of pelvic RT once chemo is given, where GOG-249 and the GOG-258 abstract both show more pelvic and nodal failure without it.
The regimen is demanding: all 4 carboplatin and paclitaxel cycles were completed by 79% and 71%, G3+ AEs ran 60% vs 12%, and G2+ neuropathy persisted at 3y in 8%. The FFS gain concentrates in stage III, and the authors flag a larger benefit in women over 70 and at least as much benefit in serous or clear cell histology.
10 details 4 trials watching
Open-label, international, randomised phase 3 at 103 centres across six GCIG groups; 1:1 by biased-coin minimisation, stratified by centre, lymphadenectomy, stage and histology. 686 enrolled, 660 in the ITT analysis; median follow-up 60.2 mo.
High-risk endometrial cancer, FIGO 2009: stage IA EEC grade 3 with LVSI, IB EEC grade 3, EEC stage II or III, or serous / clear cell stage IA (with invasion) to III. WHO PS 0-2, no upper age limit; median age 62, stage III in 46% vs 43%.
Experimental arm added cisplatin 50 mg/m² x2 concurrent, then 4 cycles carboplatin AUC5 + paclitaxel 175 mg/m². Both cisplatin cycles completed by 92%; all 4 carboplatin and paclitaxel cycles by 79% and 71%.
Pelvic EBRT 48.6 Gy in 1.8 Gy fractions in both arms; 45.0-50.4 Gy delivered in 100% vs 98%. Vaginal brachy boost for cervical invasion, given in 46% vs 48%.
Co-primary: overall survival and failure-free survival, ITT, Cox-adjusted for stratification factors.
G3+ AEs during treatment 60% vs 12% (p<0.0001). G2+ neuropathy persisted at 3y in 8% vs 1%.
Direction matches the pooled NSGO-EC-9501/EORTC-55991 + ManGO Iliade analysis (PFS 78% vs 69%, OS trend 82% vs 75%), here in a larger trial with concurrent plus adjuvant chemo. GOG-249 found chemo + VBT no better than pelvic EBRT in stage I-II with more pelvic and para-aortic recurrence; the GOG-258 abstract reported no OS/RFS gain for CRT over chemo alone but more vaginal and nodal failures without RT.
Final analysis was time-based, with OS events at 69% of the number required, so a 5% OS difference was below what the trial could detect. RT plan QA outside ANZGOG was still pending, and the stage and age subgroup reads are exploratory.
CRT buys FFS, not OS, at 5y, at the price of a fivefold G3+ toxicity rate and persistent neuropathy. The authors read the stage I-II FFS gain as not outweighing toxicity, so the combined regimen fits individual counselling, mainly in stage III.
| Endpoint | CRT | RT alone | Effect |
|---|---|---|---|
| 5y OS | 81.8% (77.5–86.2) | 76.7% (72.1–81.6) | HR 0.76 (0.54–1.06), p=0.11 |
| 5y FFS | 75.5% (70.3–79.9) | 68.6% (63.1–73.4) | HR 0.71 (0.53–0.95), p=0.022 |
| Stage III 5y OS | 78.7% | 69.8% | HR 0.71 (0.45–1.11), adjusted p=0.074 |
| Stage III 5y FFS | 69.3% | 58.0% | HR 0.66 (0.45–0.97), adjusted p=0.014 |
| Stage I–II 5y FFS | 80.8% | 76.6% | HR 0.85 (0.54–1.33), p=0.47 |
| G3+ AEs during treatment | 198 (60%) | 41 (12%) | p<0.0001 |
| G2+ neuropathy at 3y | 20 (8%) | 1 (1%) | p<0.0001 |
CONSORT flow
Randomised phase 3 met co-primary FFS but missed OS with only 69% of required OS events; direction matches pooled NSGO-EC-9501/ManGO data. Toxicity cost tempers adoption.
- Does the OS difference emerge with longer follow-up?
- Is pelvic RT still needed in stage III when chemotherapy is given? not yet Chemotherapy vs Chemoradiotherapy for Post-operative Endometrial Cancer Patients With P53-mutation Phase 2/3n=294 · primary completion 2028-08 · randomizes chemo alone vs CRT, p53abn stage I-IVA
- Can stage I-II pts be spared chemotherapy toxicity safely? n=590 · primary completion 2026-12 · molecular profile assigns CRT vs RT, stage I-IIn=316 · primary completion 2030-01 · RT + durvalumab vs RT ± chemo in MMRd ECn=600 · primary completion 2030-12 · RT + progestin vs RT + chemo, high-risk NSMP
📚 Sources · 📄 1 paper
HDR vaginal brachytherapy cylinder dosimetry
ForPost-hysterectomy endometrial cancer, adjuvant HDR vaginal cuff brachytherapy
TL;DRSurface SD 6% vs 18% with surface vs 0.5-cm depth prescription (2-cm cylinder). Omitting dome optimization points gave hot spots >150% and cold spots <60%.
The actionable physics: the dome needs optimization points. Without them the apex runs cold (50-65%) or hot (140-170%) depending on tip space, and the 0.5-cm depth prescription hides surface SD up to 18%. If you switch to a surface prescription, M = 1.00 + 0.64/L + 1.23/S gives the surface dose that keeps the 0.5-cm dose unchanged.
For post-hysterectomy endometrial pts on single-channel cylinder VBT, this supports checking that apex and dome points are in the optimization and reporting both surface and 0.5-cm doses. It gives no outcome evidence for changing an established 0.5-cm depth prescription. The longer read
The actionable physics: the dome needs optimization points. Without them the apex runs cold (50-65%) or hot (140-170%) depending on tip space, and the 0.5-cm depth prescription hides surface SD up to 18%. M = 1.00 + 0.64/L + 1.23/S converts a depth dose to its surface equivalent if you switch conventions.
12 details
A treatment-planning study with no patients. Plato BPS 14.2.4 plans were built on Nucletron radiographic cylinders (tip space ~0.5 cm) and CT/MR-compatible cylinders (tip space 0.6-0.8 cm). Dose uniformity at each depth was measured as the mean dose (MD) and SD across dose points spaced evenly around the dome and along the cylinder.
Cylinders were 2.0, 2.5, 3.0, 3.5 and 4.0 cm in diameter, with active lengths of 3 to 8 cm (upper third to the whole vagina). Prescription was to the surface (P0) or to 0.5-cm depth (P5), with or without optimization points on the curved end (NEP). The worked illustration used 7 Gy × 3 fractions.
Primary measures: MD and SD at the surface and at 0.5-cm depth. Dose fall-off was the ratio of MD at 0.75 cm to MD at 0.5 cm.
Surface prescription gave surface SD 6% vs 18% with P5 (2-cm cylinder, 0.8-cm tip), with almost the same fall-off beyond 0.5 cm. NEP plans produced hot spots >150% and cold spots <60%. A shorter tip space raised dosimetric uncertainty >30%.
The paper frames its result against the ABS 2000 guidance (dome optimization points, report doses at both surface and 0.5 cm) and an ABS survey in which >90% prescribe to 0.5 cm. It also cites Sorbe's randomized 2.5 vs 5.0 Gy × 6 trial, in which higher dose increased atrophy, bleeding and shortening.
The M regression was fit on only two lengths × two diameters, using one vendor's applicators and TPS. The claim that a lower surface dose reduces atrophy and shortening is extrapolated from other trials, not measured.
A 0.5-cm depth prescription delivers its intended depth dose only when dome points are included, and the surface dose it gives varies with cylinder size and tip space. Prescribing to the surface with a geometry-scaled dose fixes the surface number. Whether that changes toxicity remains open.
Planning-system dosimetry with no patients or outcomes. 'Surface prescription is optimal' rests on mucosal dose uniformity, a surrogate never tied to toxicity or vaginal control here.
- Does surface prescription reduce vaginal atrophy or shortening clinically?
- Does the M factor hold on modern 3D image-guided planning?
📚 Sources · 📄 1 paper
Composite pathologic risk stratification, resected HPV+ oropharyngeal cancer
ForSurgically resected HPV+ OPSCC, LN yield ≥15, AJCC 7th T1-4 N0-3 M0
TL;DRTraditional pathologic risk tiers discriminate poorly in resected HPV+ OPSCC (C-index 0.58); a points-based composite reaches 0.67 and moves high-risk share from 45.1% to 6.6%.
The composite down-weights margins and ENE against T4 and ≥5 nodes, so most traditional high-risk pts become low risk (high-risk share 45.1% to 6.6%). That is the adjuvant CRT escalation trigger. NCDB has OS but no locoregional failure, so it cannot say whether reclassified microscopic-ENE or margin-positive pts keep in-field control with less RT or no chemo.
In resected HPV+ OPSCC with microscopic ENE or a microscopically positive margin but T1-2 disease and fewer than 5 nodes, this questions reading the case as automatically high risk for CRT escalation; it does not extend to T4 or ≥5-node disease, or to HPV-unassociated HNSCC. The longer read
The CRT-escalation triggers, ENE and positive margins, carry little OS weight in HPV+ disease here, while T4 and ≥5 nodes dominate. Without locoregional endpoints and with adjuvant RT/CRT adjusted out, it frames but cannot license reduced adjuvant RT or chemo omission.
Pathologic staging after transoral surgery and neck dissection (LN yield ≥15) is the input: nodal count and T stage drive prognosis, while margin status and LN size, level or laterality do not track mortality. That changes which specimen findings carry weight when counseling on adjuvant needs.
14 details
Retrospective NCDB cohort, dx 2010-2013, analyzed 2018-2019. Univariate + multivariate Cox for OS; points assigned to features in proportion to effect size, then the composite was selected on C-index, AIC and clinical judgement.
Upfront surgery + adequate neck dissection (LN yield ≥15), non-metastatic T1-4 N0-3 M0 (AJCC 7th). HPV+ OPSCC n=2302 vs HPV-unassociated HNSCC n=13 022; OPSCC without HPV testing and surgery + chemo alone excluded.
5-y OS (KM, log-rank) and discrimination by C-index. Multivariate models adjusted for age, sex, race, comorbidity, insurance, adjuvant RT and/or CRT, and hospital type.
In HPV+ OPSCC only T stage, LVI, number of LN mets and ENE tracked with mortality; margins, LN size, level IV-V and bilateral nodes did not. Composite C-index 0.67 (3 tiers) vs 0.58 traditional.
| Traditional tier | HPV+ OPSCC | HPV-unassociated HNSCC |
|---|---|---|
| Low | 93.2% | 76.2% |
| Intermediate | 88.9% | 54.5% |
| High | 83.7% | 40.9% |
| C-index | 0.58 | 0.68 |
| Risk group | Traditional | Composite |
|---|---|---|
| Low risk | 24.5% (564/2302) | 75.3% (1733/2302) |
| High risk | 45.1% (1038/2302) | 6.6% (151/2302) |
The traditional tiers being tested come from NCCN, ASCO, ECOG 3311 and PATHOS definitions, the de-escalation trials that use pathology to allocate adjuvant RT vs CRT. ICON-S refined clinical staging for HPV+ disease but was built on definitive CRT with only 2% surgical pts, so it could not weigh pathologic features.
Points include margins despite no multivariate association, a judgement call that inflates their weight. The source states the traditional high-risk share inconsistently (46.1% and 45.1%), and HPV testing method is not described.
Traditional HNSCC pathologic tiers are weakly prognostic in HPV+ OPSCC, and nodal burden plus T4 matter more than ENE or margins. Whether the reclassified majority can safely receive less adjuvant therapy is untested here and belongs to the next deintensification trials.
Registry retrospective, OS-only, model scored in its own derivation cohort without external validation; cannot show reclassified pts tolerate less adjuvant RT/CRT.
- Does composite low-risk status predict safe omission of adjuvant RT?
- External validation with locoregional recurrence endpoints
- Does microscopic ENE alone justify adding concurrent chemo?
📚 Sources · 📄 1 paper
Nodal metastasis mapping in seminoma (RT fields)
ForCS IIA/B or recurrent CS I seminoma post-orchiectomy, nodes ≤5cm
TL;DRAcross 145 imaging-positive nodes in 90 pts, 99% sat within a 2.5cm lateral/posterior and 2.1cm anterior arterial expansion, smaller than Classen fields.
The superior border is the volume lever: no left-sided node sat above L1 or in the renal hilum, supporting a border 1.5cm above the left renal artery rather than T10/T11. Prior inguinal or pelvic surgery is the exception, needing an inferior border 1cm below the femoral head.
In CS IIA/B seminoma with a left-sided primary and no prior inguinal or scrotal surgery, this supports a vascular-referenced CTV without right paracaval or high superior extension; it does not extend to pts with prior pelvic surgery, where inguinal coverage was needed. The longer read
The superior border is the volume lever: no left-sided node sat above L1 or in the renal hilum, supporting a border 1.5cm above the left renal artery rather than T10/T11. Prior inguinal or pelvic surgery is the exception, needing an inferior border 1cm below the femoral head.
9 details
Retrospective multicenter imaging review, 4 academic centers, staging scans read by a single abdominal radiologist. Each node transferred to a CT template by its relation to the aorta and renal arteries, with craniocaudal scaling for height.
90 pts, CS IIA/B or recurrent CS I seminoma after orchiectomy, nodes ≤5cm. 40 (44%) relapsed on CS I surveillance at a median 8.5 mo (range 3.2-50.4); 50 (56%) node-positive within 3 mo of diagnosis. 48 (53%) left-sided, 41 (46%) right-sided primaries.
Proposed CTV: 2.5cm lateral/posterior and 2.1cm anterior expansion of arterial vasculature, superior border 1cm above the right or 1.5cm above the left renal artery. Classen acetabular inferior border retained; NCCN 2cm GTV boost and setup margins added on top.
145 nodes, average 1.6 per pt, median size 18 mm. 99% of nodes fell inside the proposed expansion; nodal region was unrelated to CS at presentation (P = 0.16) or primary laterality (P = 0.15).
| Region | % of all nodes | % of pts with ≥1 node |
|---|---|---|
| Para-aortic | 84% | 88% |
| Common iliac | 9% | 12% |
| Pelvic | 7% | 9% |
Classen extended fields (prospective phase II, 2003) are the NCCN- and European consensus-endorsed standard; this map supports Classen's acetabular inferior border but argues the T10/T11 superior border overtreats. MRC TE10 linked smaller fields to less acute GI toxicity and leukopenia. Martin et al. used a 1.4cm aorta/IVC expansion from non-enlarged nodal anatomy.
Single-timepoint CT in many pts, so original nodal position before reaching size criteria was estimated, not observed. Two atypical nodes (1.4%) were excluded from the expansion analysis. Relapses that would emerge outside the reduced field after treatment are unmeasured.
The case for smaller fields rests on second-malignancy risk in a young cohort, with extended fields linked to up to 50% more SMNs than PA strip fields in cited data. The trade the authors accept is a small out-of-field relapse risk, judged salvageable, against lower SMN risk.
Retrospective imaging-defined node map; proposed CTV never tested for relapse or toxicity. Authors themselves limit it to research use pending validation.
- Out-of-field relapse rate when treating the vascular-based CTV prospectively
- Does nanoparticle MRI identify nodes before size criteria change target volumes?
📚 Sources · 📄 1 paper
Classen reduced-portal RT for stage IIA/B seminoma
ForPure seminoma, Royal Marsden stage IIA/IIB, AFP-negative, post-orchiectomy
TL;DR6-yr RFS 95.3% (IIA) and 88.9% (IIB) with para-aortic/ipsilateral high iliac RT, 30/36 Gy; 100% in-field control, no late toxicity.
Field size is the transferable parameter: dropping the contralateral pelvis and inguinal chain to a T11-to-acetabulum hockey-stick gave no pelvic or inguinal failures and 100% in-field control. 3 of 4 relapses involved the mediastinum, outside any infradiaphragmatic field, so the residual risk is systemic, not a portal or dose problem.
In AFP-negative stage IIA seminoma, this supports para-aortic plus ipsilateral high iliac RT to 30 Gy without pelvic or mediastinal extension; it does not settle stage IIB, where 21 pts and a 74.4% lower CI bound leave room for chemo-based approaches. The longer read
The reduced hockey-stick (para-aortic plus ipsilateral high iliac, T11 to acetabulum) gave no pelvic or inguinal failures and 100% in-field control at 30 Gy (IIA) and 36 Gy (IIB). Contralateral pelvic and mediastinal coverage add toxicity without addressing the observed failure sites.
All four relapses were mediastinal or pulmonary and every one was salvaged with platinum chemo, giving DSS 100%. In the source's framing, chemo-first options (modified EP 9% relapse, carboplatin 15% failure) add toxicity without better control, though the IIB cohort of 21 pts leaves that comparison open.
11 details 1 trial watching
Prospective multicentre observational study, 30 German centres, enrolment April 1991 to March 1994. 94 enrolled, 87 assessable, median follow-up 70 mo. Analysed ITT, including 22 pts with major protocol violations.
Histologically confirmed pure testicular seminoma, Royal Marsden stage IIA (<2 cm) or IIB (2-5 cm) after high inguinal orchiectomy. Elevated AFP excluded; βHCG up to 200 IU/L allowed after year 1. 66 IIA, 21 IIB; median age 32.5 and 32.
AP/PA hockey-stick to para-aortic/paracaval and ipsilateral high iliac nodes, gross disease plus 2 cm margin, T11 to acetabular rim. 2.0 Gy/fx: 30 Gy for IIA, 36 Gy for IIB, no boost; 5 pts treated bilateral iliac.
Primary: relapse-free survival at 5 years. Secondary: disease-specific survival (expected at least 95% at 5 yr) and acute/late GI and skin toxicity.
Acute toxicity dominated by grade 1 nausea (53% IIA, 52% IIB); no grade 4. No late GI toxicity, no peptic ulceration, no second malignancy to date; one pt with G1 skin hyperpigmentation.
Prior stage II series used larger portals covering the entire ipsilateral iliac/inguinal chain and contralateral pelvis; this cohort shows the reduced field loses no pelvic control. The source places modified EP (9% relapse, 33% G3/4 leukopenia) and carboplatin alone (15% failure) as no better on control with more toxicity.
Study was not designed to test reduced vs extended portals, so the toxicity advantage is inferred against historic series. Seven pts lost to follow-up were excluded rather than censored, and the IIB cohort is too small for its own protocol-violation analysis.
Failures were all extra-field (mediastinal or lung) except one lateral para-aortic field-edge relapse, and all were salvaged, so DSS was 100%. The authors suggest room for dose reduction below 30 Gy in IIA, though no dose-response relationship was established.
| Measure | Stage IIA | Stage IIB |
|---|---|---|
| Assessable pts | 66 | 21 |
| Dose | 30 Gy | 36 Gy |
| 6-yr RFS (95% CI) | 95.3% (88.9-100%) | 88.9% (74.4-100%) |
| Relapse sites | 1 mediastinal, 1 field-edge | 1 mediastinal, 1 mediastinal/pulmonary |
| G3 nausea | 8% | 10% |
| G3 diarrhea | 6% | 10% |
Single-arm observational cohort with no randomised comparator vs chemo; IIB subset small (n=21). Single-arm gate caps the verdict despite 70-mo follow-up.
- Dose de-escalation below 30 Gy in stage IIA
- RT vs chemotherapy in stage IIB seminoma n=90 · primary completion 2032-05 · post-1 EP randomised RT boost vs carbo, stratified IIA/IIB
- Second-malignancy risk beyond 6-yr follow-up
📚 Sources · 📄 1 paper
Abstract
F-SHARP
ForIntraprostatic radiorecurrence after definitive RT for localized prostate cancer
TL;DRNo acute G3+ toxicity and 3-yr bPFS 62.7% after dose-escalated focal salvage HDR (up to 30 Gy/1-2 fx) for intraprostatic radiorecurrence, N=62.
The single-fraction arm (24 pts) matched two fractions on every endpoint (all P > .05), making a one-visit focal salvage HDR schedule a real option. The GC tail is the second read: all 4 pts with score >0.85 recurred locally and distantly, so focal-only salvage looks like the wrong tool for them.
In intraprostatic radiorecurrence after definitive RT, this supports focal salvage HDR (up to 30 Gy in 1-2 fractions) as a low-toxicity local option; it does not settle management for the GC score >0.85 pt, where focal salvage alone failed in all 4. The longer read
Single-fraction focal salvage HDR (24 pts) performed no differently from two fractions (all P > .05), with no acute G3 toxicity at up to 30 Gy. The GC tail flags who focal salvage fails: all 4 pts with score >0.85 recurred locally and distantly, arguing against focal-only treatment in that group.
12 details
Multi-institutional phase I/II, single-arm, N = 62. Median follow-up 39.4 mo.
Intraprostatic radiorecurrence (IPR) after any form of RT for localized prostate cancer. GC results available in 31 pts.
Dose-escalated focal salvage HDR, up to 30 Gy in 1-2 fractions. 24 pts received one fraction and 38 received two.
Primary: acute RT-related G3+ GU and GI toxicity (CTCAE v4.03). Secondary: all-grade toxicity, QoL (EPIC-26, IPSS), bPFS, rPFS, LRFS, MFS and survival.
No acute G3 toxicity. Late G3 toxicity in 2 pts (3.2%); QoL changes did not meet MCID criteria.
Prospective salvage brachytherapy data after EBRT are sparse, with RTOG 0526 testing whole-gland salvage LDR in this setting. F-SHARP adds a focal, dose-escalated HDR approach and a genomic risk layer that prior salvage series lacked.
The GC analysis is restricted to 31 of 62 pts and the >0.85 cutpoint rests on n = 4, so it is a descriptive tail, not a validated threshold. The 1 vs 2 fraction comparison was not randomized and is underpowered for equivalence.
Toxicity is the settled part: focal dose escalation to 30 Gy in the re-irradiated gland produced no acute G3 events. Durability is the open part, since bPFS at 3 yr is 62.7% and the efficacy endpoints carry no comparator.
| Endpoint | 3-yr rate |
|---|---|
| bPFS | 62.7% |
| rPFS | 67.5% |
| LRFS | 73.0% |
| MFS | 85.9% |
Single-arm phase I/II, N=62, toxicity primary objective; efficacy endpoints secondary and uncontrolled. GC signal from half the cohort.
- Focal vs whole-gland salvage brachytherapy for intraprostatic radiorecurrence
- Does GC-guided intensification improve outcomes in high-score pts?
- Is single-fraction focal salvage HDR equivalent to two fractions?
📚 Sources · 📄 1 paper
Abstract
Prostate SBRT intra-fraction motion and margins
ForProstate SBRT 36.25 Gy/5 fx, fiducial CBCT IGRT, no intra-fraction tracking
TL;DRCurrent 6 mm/3 mm posterior PTV margins covered IFPM in 92% of fractions. BIR-guideline margins ran from 3.3 mm laterally and posteriorly to 7.0 mm inferiorly.
The 7.0 mm inferior margin is driven mainly by apex delineation error on MRI-only contours, and dropping one outlier contour gives 5.8 mm. Lateral margins of 3.3 and 3.5 mm suggest room to trim. The posterior miss (6 of 97 fractions past 3 mm) sits at the rectal edge, which argues for bladder/rectal consistency or tracking rather than a wider posterior PTV.
In fiducial-guided 36.25 Gy/5 fx prostate SBRT delivered without intra-fraction tracking, this supports existing 6 mm/3 mm posterior margins as covering most fractions; it does not inform tracked, MR-guided, or CT-only-delineated workflows. The longer read
The inferior 7.0 mm BIR margin mostly reflects apex delineation error on MRI-only contours (5.8 mm without one outlier). Lateral margins of 3.3 and 3.5 mm suggest room to trim. Posterior misses (6 of 97 past 3 mm) point to bladder/rectal consistency or tracking, not a wider rectal-side PTV.
13 details 2 trials watching
Retrospective single-centre audit of 97 pre/post-treatment CBCT pairs from 20 pts. Margins were calculated from IFPM alone and with the updated BIR geometric uncertainty guidelines.
36.25 Gy in 5 fractions SBRT without intra-fraction tracking, with fiducial-based daily online CBCT IGRT. Current margins were 6 mm isotropic, 3 mm posterior. Mean pre- to post-imaging interval was 9 min.
magnitude and direction of IFPM and coverage by current margins. Secondary: margins derived from IFPM alone and from the BIR guidelines.
Averaged 3D RMS IFPM was 2.5 mm (4.2 mm), mostly posterior (70%) and inferior (63%). Current margins covered 92% of fractions, and 8 of 97 exceeded them, six posteriorly.
| Direction | Current margin | BIR-derived margin |
|---|---|---|
| Right | 6 mm | 3.5 mm |
| Left | 6 mm | 3.3 mm |
| Superior | 6 mm | 3.7 mm |
| Inferior | 6 mm | 7.0 mm |
| Anterior | 6 mm | 4.4 mm |
| Posterior | 3 mm | 3.3 mm |
The authors report RL motion above comparable CBCT series, with AP and SI comparable. A larger cited margin study (n=205) found smaller systematic errors and similar random errors.
Delineation error, the dominant component, came from an MRI-only study and is probably smaller than real CT or fused MR/CT error. Deformation was set to 0, match error was assumed rather than measured, and AP and SI were not split by direction.
The guideline-derived numbers suggest lateral margins could shrink while the inferior margin grows, but the inferior increase rests heavily on one outlier contour. The authors advise checking outcomes in current trials before changing practice, given favourable control and toxicity with existing margins.
Single-centre retrospective geometric audit, n=20, no clinical outcome endpoint; proposed margin changes are untested against toxicity or biochemical control.
- Does a larger inferior margin change toxicity or biochemical control? recruiting Adaptive Radiation Therapy (ART) Stereotactic Ablative Body Radiotherapy (SABR) for Primary Localized Prostate Cancer Phase NAn=164 · primary completion 2027-04 · near margin-less ART vs standard SABR, QoL compared
- Would intra-fraction tracking eliminate posterior out-of-margin fractions? n=91 · primary completion 2035-09 · CT-guided prostate SBRT with intrafraction motion monitoring
- Margins with CT or fused MR/CT delineation error measured
📚 Sources · 📄 1 paper
Abstract
RTOG 9601 NCT00002874
ForpN0 pT2 R1/pT3 post-RP, detectable PSA 0.2-4.0 ng/ml, salvage RT
HR 0.77
95% CI 0.59-0.99, P=0.04; 12-yr OS 76.3% vs 71.3%
TL;DR12-yr OS 76.3% vs 71.3%, HR 0.77 (0.59-0.99), adding 24mo bicalutamide 150mg to salvage RT in pN0 post-RP pts with PSA 0.2-4.0.
The benefit follows pre-SRT PSA: 12-yr OS HR 0.45 (0.25-0.81) above 1.5 ng/ml and 0.61 at 0.7-1.5, but HR 1.13 (0.77-1.65) below 0.7, where the median entry PSA of 0.6 sat. RT was prostate bed only, 64.8 Gy/36 fx, so this informs hormone addition separately from the pelvic nodal coverage decision.
In a pN0 man after RP heading to salvage RT with PSA above 0.7 ng/ml, this supports adding hormone therapy to bed RT; it does not extend to PSA below 0.7 ng/ml, where the post hoc OS HR was 1.13. The longer read
Entry PSA gates the hormone add-on to prostate-bed salvage RT: OS HR 0.45 above 1.5 ng/ml, 0.61 at 0.7-1.5, 1.13 below 0.7. RT was 64.8 Gy/36 fx with nodes omitted in pN0 pts, so the trial leaves the elective pelvic nodal question open.
The drug tested, bicalutamide 150 mg for 24 months, is no longer standard, and gynecomastia reached 69.7% without prophylaxis. Whether GnRH-agonist ADT or a shorter course reproduces the OS HR 0.77 was not tested; the benefit concentrates at entry PSA ≥0.7 ng/ml.
11 details 1 trial watching
Randomized, double-blind, placebo-controlled NRG/RTOG trial; 840 randomized 1998-2003, 760 eligible analyzed (384 vs 376). Median follow-up 13 years among survivors.
Post-RP with lymphadenectomy, pT2 with positive margin or pT3, pN0, detectable PSA 0.2-4.0 ng/ml at least 8 weeks after surgery. No prior RT or chemo; prior hormones limited to short preoperative courses (6.4%). Staging by CT and bone scan.
Bicalutamide 150 mg daily for 24 months vs placebo, starting with RT. Adherence ≥18 months was 69.8% vs 74.7%.
64.8 Gy in 36 fractions of 1.8 Gy to the prostatic bed and membranous urethra, 6-10 MV photons, 2D or 3D planning. Pelvic nodes omitted because all dissections were negative. QA: 64.8% per protocol, 4.4% unacceptable variation.
Primary: overall survival. Secondary: disease-specific death, distant metastases, local progression, non-disease-specific death, second biochemical recurrence, AEs.
Primary met; every disease-control endpoint favored bicalutamide (table). The OS gain is concentrated at entry PSA ≥0.7 ng/ml in post hoc subgroups.
| Endpoint | RT + bicalutamide | RT + placebo | HR (95% CI), P |
|---|---|---|---|
| OS (1° EP) | 76.3% | 71.3% | 0.77 (0.59-0.99), P=0.04 |
| Death from PCa | 5.8% | 13.4% | 0.49 (0.32-0.74), P<0.001 |
| Metastatic PCa | 14.5% | 23.0% | 0.63 (0.46-0.87), P=0.005 |
| 2nd biochemical recurrence | 44.0% | 67.9% | 0.48 (0.40-0.58), P<0.001 |
| PSA at entry | n (%) | Bicalutamide | Placebo | HR (95% CI), P |
|---|---|---|---|---|
| <0.7 ng/ml | 405 (53.3) | 76.8% | 80.7% | 1.13 (0.77-1.65), 0.53 |
| 0.7-1.5 ng/ml | 237 (31.2) | 77.0% | 67.5% | 0.61 (0.39-0.95), 0.03 |
| >1.5 ng/ml | 118 (15.5) | 73.5% | 48.9% | 0.45 (0.25-0.81), 0.007 |
Gynecomastia 69.7% vs 10.9%. Late GU G3 7.0% vs 6.0%; no excess early bladder, bowel or hematologic toxicity, and no excess non-disease-specific death.
SPPORT and RADICALS-HD tested GnRH-based ADT with salvage RT, but neither used a placebo-controlled OS design. The Early Prostate Cancer Program trials of the same drug and dose reported a matching gynecomastia signal (68% vs 8%).
Post-randomization exclusion of 79 ineligible pts departs from strict ITT. Cardiac events were captured only as reported AEs, which risks ascertainment bias. Pre-PSMA staging leaves occult extra-field disease in the cohort.
OS benefit is real but risk-adapted: below PSA 0.7 the subgroup trended the other way. The open questions are whether a modern GnRH agonist reproduces the effect and which duration is enough.
CONSORT flow
Double-blind placebo-controlled RCT, OS primary met at 13y median f/u. Benefit concentrated at PSA ≥0.7 (post hoc); bicalutamide 150mg since superseded by GnRH agonists.
- Does GnRH-agonist ADT reproduce the bicalutamide OS benefit?
- Optimal hormone duration with salvage RT at low PSA active Comparison of HT Concomitant With RT vs RT Alone in Patients With a Detectable PSA After Prostatectomy Phase 2n=120 · primary completion 2022-03 · short degarelix + SRT vs SRT alone, pN0, PSA ≥0.2
- Does PSMA PET staging change who benefits from added hormones?
📚 Sources · 📄 1 paper
NRG/RTOG 0415 late toxicity tolerance doses
ForLow-risk prostate cancer, HRT arm of NRG/RTOG 0415
TL;DRRectal D5% (EQD2) ≤62 Gy predicted halving late ≥G2 GI toxicity from 20% to 10% after 70 Gy at 2.5 Gy/fx in low-risk prostate cancer.
The constraint that matters is a small-volume hotspot, not the high-dose V74Gy rule, which 16% of plans missed anyway. Pts with acute GI toxicity have a lower modeled tolerance (D5% ≤55 Gy for a 10% late GI rate), so planning targets may need to differ by acute course. Bladder dose explained nothing for GU, pointing elsewhere for mitigation.
In low-risk prostate cancer planned for moderate HRT at 2.5 Gy/fx, this supports adding a rectal D5% (EQD2) ceiling near 62 Gy as a GI-toxicity planning goal; it does not inform GU toxicity, where no bladder dose-response emerged. The longer read
The constraint that matters is a small-volume rectal hotspot (D5%), not the V74Gy rule that 16% of plans missed anyway. Pts with acute GI toxicity carry lower modeled tolerance (D5% ≤55 Gy for a 10% late GI rate), and bladder dose explained nothing for GU, pointing mitigation toward substructures.
11 details 1 trial watching
Secondary dose-volume analysis of the HRT arm of the multicenter NRG/RTOG 0415 trial, N=521. Cohort split 70%/30% into training and validation with preserved toxicity rates; univariate and multivariate logistic regression on bootstrapping.
Low-risk prostate cancer treated on the HRT arm. Median follow-up 5.9 yr.
70 Gy at 2.5 Gy/fraction, 3DCRT/IMRT N=108/413. Doses converted to EQD2 with rectum α/β 3 Gy and bladder 6 Gy; trial rectal constraint EQD2 74 Gy ≤15%.
Late ≥G2 GI and GU toxicity, plus proctitis and pollakiuria (the symptoms with rates ≥10%). Generalizability required validation AUC within training AUC ± SD, p≤0.05, and pHL >0.05.
Rectal D5% was the dominant GI predictor; with or without acute GI toxicity it generalized (AUCvalidation 0.64, 0.65). Modeled late GI falls from 20% to 10% at D5% ≤62 Gy. No GU dose-response was found, including at α/β 0.8 Gy.
| Late GI rate | D5% (Model IV) | D5% if acute GI tox (Model II) |
|---|---|---|
| 20% (observed) | 65 Gy | ≤59 Gy |
| 15% | ≤64 Gy | ≤58 Gy |
| 10% | ≤62 Gy | ≤55 Gy |
PROFIT, CHHiP, HYPRO and RTOG 0415 established moderate HRT with similar biochemical control to CFRT but a tendency to more late toxicity. The late GI rate here was 19% vs 2% in a cited high-dose CFRT IMRT series planned with a strict high-dose rectal constraint.
Validation is an internal random split of the same cohort, not an external dataset. The IMRT-heavy mix (79% vs 21%) left a technique interaction untestable, and constraint adherence was incomplete, so part of the signal may reflect plan quality rather than tolerance.
Results point to small rectal hotspots as the modifiable driver of excess late GI toxicity after moderate HRT, with authors also advocating rectal spacers. GU toxicity likely needs a substructure (not whole-bladder) approach.
Post-hoc NTCP modeling within one arm of a phase III; modest AUC 0.64-0.65, internal split validation only, no prospective test of the proposed D5% constraint.
- Does a prospective D5% ≤62 Gy rectal objective lower late GI toxicity?
- Which urinary substructure drives late GU toxicity after HRT?
- Does rectal spacer use make the D5% threshold redundant? n=500 · primary completion 2027-12 · SpaceOAR Vue effect on late GI toxicity, prostate SBRT
📚 Sources · 📄 1 paper
Moderate hypofractionation 70 Gy/28 fx, 10-year outcomes
ForLocalized prostate cancer, all NCCN risk groups, definitive RT ± ADT
TL;DR10-yr bRFS 71%, cRFS 86%, PCSM 6.8% after 70 Gy/28 fx IMRT for localized prostate cancer; late G≥3 GU 2%, GI 1%.
Failure after 70 Gy/28 fx was almost entirely distant: 117 of 125 clinical failures were metastatic, 8 local-only. The HR 10-yr bRFS of 42% came with only 5/244 HR pts receiving elective nodal RT, which the authors attribute to short ADT and rare nodal coverage rather than inadequate prostate dose.
In localized low and intermediate-risk prostate cancer, this supports 70 Gy/28 fx IMRT with daily IGRT as a durable schedule past 10 yr; it does not settle HR disease treated with short ADT and no pelvic nodal RT. The longer read
Failure after 70 Gy/28 fx was almost entirely distant (117 of 125 clinical failures; 8 local-only), so prostate dose is not the HR weak point. Low late toxicity was achieved with rectal/bladder V70 held to 5%, far tighter than NRG-GU005 allows, which gates whether the 2%/1% rates transfer.
12 details 3 trials watching
Single-institution consecutive series from a prospectively maintained registry, 854 pts treated 1998-2012. Median follow-up 11.3 yr (max 19). Not randomized; no comparator arm.
Biopsy-proven, clinically localized prostate adenocarcinoma across all NCCN risk groups: 266 LR, 238 FIR, 106 UIR, 244 HR. Median age 68, median PSA 8.6 ng/mL. ADT in 61%, mostly 1-6 mo.
70 Gy/28 fx at 2.5 Gy/fx, IMRT with daily IGRT (BAT ultrasound 94.8%). CTV prostate alone for LR, plus proximal SV for IR/HR; PTV margin 4-10 mm. Elective pelvic nodes in only 5 of 244 HR pts.
Whole-cohort 10-yr bRFS 71%, cRFS 86%, OS 69%, PCSM 6.8%. Of 125 clinical failures, 117 were distant and 8 local-only.
| Endpoint | LR | FIR | UIR | HR | p |
|---|---|---|---|---|---|
| bRFS | 88% | 78% | 71% | 42% | <.0001 |
| cRFS | 95% | 91% | 85% | 72% | <.0001 |
| PCSM | 2% | 5% | 5% | 15% | n/a |
10-yr late G≥3 GU 2% (mostly urethral stricture) and G≥3 GI 1% (mostly rectal bleeding). One grade 5 event each in GU and GI. 119 pts (14%) developed a new cancer, lung most common.
Authors place this alongside RTOG 0415, CHHiP, PROFIT, HYPRO and the MDACC series, none with 10-yr outcomes at publication. RTOG 0415 used the same 70 Gy/28 fx with G3 toxicity 3% to 4% at 5 yr, under looser dose-volume constraints and without mandatory IMRT.
Toxicity was physician-reported from retrospective chart review, likely underreporting events. Institutional constraints (rectal/bladder V70 5%, up to 10%) are far tighter than NRG-GU005 allows, so the toxicity rates may not hold under trial or community constraints.
The schedule controls the prostate well over 10+ yr; the risk-group gradient is driven by distant failure. What is left open is whether HR outcomes improve with longer ADT and nodal coverage at this fractionation.
Single-institution nonrandomized cohort without a comparator arm; long follow-up adds durability to randomized hypofractionation data but cannot establish equivalence on its own.
- HR outcomes with 70 Gy/28 fx plus ≥2 yr ADT and pelvic nodal RT recruiting Efficacy and Safety of Simultaneous Integrated Boost Radiotherapy in HR/VHR Prostate Cancer With EPLNI Phase 2n=30 · primary completion 2026-09 · hypofx SIB-VMAT + EPLNI in HR/VHR, bPFS endpointrecruiting Hypofractionated Radiotherapy With a Focal Microboost for High-Risk and Locally Advanced Prostate Cancer Phase 2n=46 · primary completion 2029-01 · hypofx + microboost, HR/VHR/N+ intact prostate
- Toxicity reproducibility under looser multi-institutional dose constraints n=400 · primary completion 2029-02 · 70 Gy/28 fx vs 60 Gy/20 fx, intact T1-3N0M0
- Whether tighter modern IGRT margins preserve low local failure
📚 Sources · 📄 1 paper
HYPO-RT-PC
ForIntermediate/high-risk N0M0 prostate, PSA ≤20, no ADT, age ≤75
5yr FFS 84% vs 84%
adjusted HR 1.002 (95% CI 0.758-1.325), non-inferior vs HR limit 1.338
TL;DR5yr FFS 84% vs 84%, adjusted HR 1.002 (95% CI 0.758-1.325): 42.7 Gy/7 fx non-inferior to 78 Gy/39 fx in intermediate-to-high-risk prostate, no ADT.
The schedule tested is 42.7 Gy/7 fx every other weekday to a prostate-only CTV (no seminal vesicles) with a 7 mm fiducial margin, 80% 3DCRT, no ADT. That supports UHF for prostate-only volumes without ADT, not SV-inclusive or ADT-paired high-risk plans. Counsel on the 1yr G2+ GU bump (6% vs 2%).
In a man up to 75 with intermediate-risk, N0M0 prostate cancer, PSA ≤20 and no ADT planned, this supports 7-fraction UHF as disease-control equivalent to 39 fractions; it does not extend to pts needing ADT, PSA >20, or seminal vesicle coverage. The longer read
The schedule tested is 42.7 Gy/7 fx every other weekday to a prostate-only CTV (no seminal vesicles) with a 7 mm fiducial margin, 80% 3DCRT, no ADT. That supports UHF for prostate-only volumes without ADT, not SV-inclusive or ADT-paired high-risk plans. Counsel on the 1yr G2+ GU bump (6% vs 2%).
10 details 5 trials watching
Open-label randomised phase 3 non-inferiority trial, 1:1, 12 centres in Sweden and Denmark, N=1200 randomised 2005-2015. Median follow-up 5.0 yr (IQR 3.1-7.0).
Men up to 75 with intermediate-to-high-risk, T1c-T3a N0M0 prostate cancer, PSA ≤20, WHO PS 0-2. No ADT allowed. 89% intermediate risk, 11% high risk.
42.7 Gy/7 fx (3 d/wk, 2.5 wk) vs 78.0 Gy/39 fx (5 d/wk, 8 wk), prescribed as mean PTV dose and designed equi-effective for late effects at α/β = 3 Gy. CTV prostate only, no seminal vesicles; 7 mm isotropic margin with fiducials; 80% 3DCRT.
Primary: failure-free survival (Phoenix nadir+2 biochemical or clinical failure), per-protocol, NI margin 4% at 5yr (critical HR 1.338). Secondary: OS, PCSS, RTOG toxicity, erectile function.
Efficacy and toxicity by arm are tabulated above; the primary met NI with a point estimate of essentially no difference.
| Endpoint | UHF 42.7 Gy/7 fx | CF 78.0 Gy/39 fx | Comparison |
|---|---|---|---|
| 5yr FFS | 84% (80-87) | 84% (80-87) | adj HR 1.002 (0.758-1.325) |
| 5yr OS | 94% (92-96) | 96% (95-98) | HR 1.11 (0.73-1.69) |
| Acute G2+ GU, end RT | 28% (158/569) | 23% (132/578) | p=0.057 |
| G2+ GU at 1yr | 6% (32/528) | 2% (13/529) | p=0.0037 |
| G2+ GU at 5yr | 5% (11/243) | 5% (12/249) | p=1.00 |
| G2+ bowel at 5yr | 1% (3/244) | 4% (9/249) | p=0.14 |
| Endpoint | UHF | CF | Log-rank p |
|---|---|---|---|
| GU at 2yr | 13% (11-16) | 9% (7-12) | 0.63 |
| GU at 5yr | 18% (15-22) | 17% (14-20) | 0.63 |
| Bowel at 2yr | 6% (5-9) | 5% (4-8) | 1.00 |
| Bowel at 5yr | 10% (7-13) | 10% (7-13) | 1.00 |
UHF carries a higher acute and 1yr GU burden (G2+ at 1yr 6% vs 2%, p=0.0037) that converges by 5yr (5% vs 5%). Late bowel toxicity no different; patient-reported acute urinary and bowel symptoms higher with UHF.
CHHiP, RTOG 0415, PROFIT and HYPRO established moderate hypofractionation against conventional fractionation. HYPO-RT-PC is the first randomised test of ultra-hypofractionation, the evidence the 2018 ASTRO/ASCO/AUA guideline said it was waiting for.
The upper CI bound (1.325) clears the 1.338 limit narrowly. 80% 3DCRT and a 7 mm margin predate modern SBRT delivery, and 7 fx every other weekday is not the 5 fx schedule most programs use. Five-year median follow-up is short for late intermediate-risk failures.
The trial settles disease-control equivalence of UHF for prostate-only, ADT-free treatment. It leaves open UHF with ADT, with SV or nodal coverage, and against moderate hypofractionation.
CONSORT flow
Randomised phase 3, NI primary met at 5yr median f/u; open-label, per-protocol primary, redesigned from superiority mid-trial. Backs guideline-conditional UHF rather than redefining SOC alone.
- UHF with concurrent ADT or seminal vesicle coverage in high-risk disease n=120 · primary completion 2027-12 · randomized SBRT vs 76 Gy/38 fx IMRT, high-risk N0n=700 · primary completion 2033-10 · phase 3 2x2: SBRT dose escalation ± darolutamide, high-risk
- UHF versus moderate hypofractionation head-to-head active Radiation Hypofractionation Via Extended Versus Accelerated Therapy (HEAT) For Prostate Cancer Phase NAn=161 · primary completion 2027-02 · 36.25 Gy/5 fx vs 70.2 Gy/26 fx, 4-yr BF non-inferiorityn=503 · primary completion 2028-08 · moderate hypo vs SBRT vs EBRT+SBRT boost; BF, toxicityactive Standard Moderately Hypofractionated RT vs. Ultra-hypofractionated Focal Lesion Ablative Microboost in Prostate Cancer Phase NAn=484 · primary completion 2032-01 · UHF focal microboost vs 20-fx moderate hypo, int/high risk
- Late biochemical failure beyond 5-year median follow-up
📚 Sources · 📄 1 paper
High-risk T1-T2N0 breast, LRR without PMRT
ForT1-T2N0 breast, mastectomy + SLNB, ≥1 high-risk feature, no PMRT
TL;DRCrude LRR 4.7% at median 5.6y after mastectomy without PMRT in T1-T2N0 with ≥1 high-risk feature; only tumor size predicted LRR (HR 1.70).
Regional failure without any RT was 2.6%, already below the 4.2% control-arm regional rate in EORTC 22922, which leaves little room for nodal or chest wall RT to add benefit in this group. Tumor size is the one feature that held up (HR 1.70 continuous). Note that axilla-only failures after SLNB alone were overrepresented.
In T1-T2N0 post-mastectomy pts getting indicated systemic therapy, LVI, age <40, multifocality, high grade or medial location alone do not support PMRT referral in this series; it does not address T2 tumors with several features, where data were sparse. The longer read
Regional failure without RT was 2.6%, below the 4.2% EORTC 22922 control-arm regional rate, so nodal RT in high-risk N0 post-mastectomy has little absolute room to work. Tumor size (HR 1.70) is the only feature that predicted LRR, which argues for weighting size over feature counting when weighing PMRT for T2N0.
15 details 1 trial watching
Single-institution retrospective cohort at MSKCC, mastectomies January 2006 to December 2011. Median follow-up 5.6y. LRR defined as biopsy-proven ipsilateral chest wall or axillary, internal mammary or supraclavicular recurrence.
T1-T2N0 invasive breast cancer with ≥1 high-risk feature (age <40y, multifocal/multicentric, LVI, medial/central location, high nuclear grade). N0 meant no tumor in the SLNs, including ITCs and micrometastases. Neoadjuvant chemo, bilateral and recurrent disease excluded; 15 PMRT pts excluded, leaving 657.
98% had SLNB alone. 86% received adjuvant systemic therapy: 41% chemo plus endocrine, 14% chemo alone, 32% endocrine alone. 70% of HER2+ pts got trastuzumab.
No PMRT in the analyzed cohort. Only 15 of 672 (2%) received PMRT over the study period, so no RT comparator exists.
LRR 4.7% (31 pts), local and regional each 2.6%. Tumor size HR 1.70 (95% CI 1.26-2.29); systemic therapy HR 0.40 (95% CI 0.17-0.92). Number of risk factors not associated with LRR (P=.54).
EORTC 22922 and MA.20 showed DFS benefit from regional nodal RT in populations that included high-risk N0 disease; per the source, N0 made up 10% of MA.20 and 44% of EORTC. The regional recurrence here without RT (2.6%) sits below the EORTC 22922 control arm (4.2%). SUPREMO, which includes high-risk N0 pts, is the randomized test of this question.
Only 32 pts had 4-5 features (Fig 1), so the null risk-count finding is underpowered where it matters most. Surgery was done by high-volume breast surgeons, and axilla-only failures after SLNB suggest a false-negative contribution not addressed by PMRT decisions alone.
Authors attribute the low LRR to contemporary systemic therapy and argue conventional features do not by themselves mandate PMRT. The data establish baseline risk without RT, not the size of any PMRT benefit, so the question for T2 tumors carrying several features stays open.
Single-institution retrospective series with no PMRT comparator; describes baseline LRR risk, cannot estimate PMRT benefit. Small ≥4-feature subgroup limits the null risk-factor finding.
- Does PMRT benefit T2N0 tumors with multiple high-risk features? recruiting Trial Evaluating Role of Post Mastectomy Radiotherapy in Women With Node Negative Early Breast Cancer Phase NAn=1022 · primary completion 2028-12 · PMRT in pT1-2N0 with multiple adverse prognostic factors
- Does regional nodal RT add benefit in high-risk N0 after mastectomy?
- How much axillary failure reflects false-negative SLNB?
📚 Sources · 📄 1 paper
Abstract
21-gene Recurrence Score and locoregional recurrence in node-positive breast cancer (SWOG 8814 correlative)
ForPostmenopausal ER/PR+ node-positive breast, mastectomy without PMRT
TL;DR10-yr LRR 16.5% vs 9.7% for RS ≥18 vs <18 (P=.02) in ER/PR+ node-positive breast; widest split at 1-3 nodes after mastectomy without RT.
In mastectomy-only pts with 1-3 nodes, 10-yr LRR was 1.5% at RS <18 vs 11.1% at RS ≥18 (P=.051, n=165). That gives the PMRT de-escalation hypothesis TailorRT is testing a biological basis. At ≥4 nodes low RS offered no protection (25.9% vs 27.0%), so a low score is no reason to drop PMRT in pN2a.
In a postmenopausal ER/PR+ pN1 pt after mastectomy with RS ≥18, this argues against treating the score as reassurance when discussing PMRT; it does not support omitting PMRT at RS <18 outside a trial, and does not apply to ≥4 positive nodes. The longer read
In mastectomy-only pN1 pts, 10-yr LRR was 1.5% at RS <18 vs 11.1% at RS ≥18 (P=.051), which supports the TailorRT hypothesis and argues for PMRT discussion at higher RS. At ≥4 nodes LRR was 25.9% vs 27.0% irrespective of RS, so pN2a PMRT is unchanged.
10 details
Retrospective translational cohort within phase 3 SWOG S8814, which enrolled 1989-1995. RT use was not randomized: it was expected after BCS and left to physician discretion after mastectomy. Reported under REMARK guidelines.
Postmenopausal, ER/PR+, node-positive women from the tamoxifen-only and CAF-T arms who had RS assayed. Final N=316: BCS + RT or mastectomy without RT. Pts who received PMRT were excluded, so the mastectomy cohort is the group whose physicians judged RT unnecessary.
Tamoxifen 20 mg daily for 5 y, alone or after 6 cycles of CAF (CAF-T). The concurrent CAF + tamoxifen arm was excluded.
Primary: LRR (breast, chest wall, axillary, infraclavicular, supraclavicular or IMN), censored at distant recurrence or death. The primary analysis used continuous RS; the secondary analysis compared RS <18 vs ≥18.
The continuous-RS primary analysis was not significant (P=.11). The categorical split and the subset tables carry the signal.
| Cohort | n | RS 0-17 | RS ≥18 | P |
|---|---|---|---|---|
| All pts | 316 | 9.7% | 16.5% | .02 |
| Mastectomy, no RT | 252 | 7.7% | 16.8% | .03 |
| Mastectomy, no RT, 1-3 nodes | 165 | 1.5% | 11.1% | .051 |
| Mastectomy, no RT, ≥4 nodes | not stated | 25.9% | 27.0% | .27 |
| Variable | HR (95% CI) | P |
|---|---|---|
| Intermediate or high RS | 2.36 (1.02-5.45) | .04 |
| ≥4 nodes | 3.37 (1.69-6.72) | .001 |
| Mastectomy | 1.11 (0.45-2.71) | .82 |
| Chemotherapy | 0.58 (0.29-1.15) | .12 |
Direction agrees with NSABP B-28, where RS also independently predicted LRR. Absolute LRR at 1-3 nodes was higher here than in B-28, which treated every pt with chemo and allowed no PMRT. MA.20 and EORTC 22922 show a nodal RT DFS benefit even where LRR is low, so LRR alone may underestimate what RT buys.
Treatment era: CAF and tamoxifen only, with no taxanes or AIs, both of which may lower baseline LRR. LRR was censored at distant recurrence, which can undercount local failures. The ≥4-node mastectomy subset had no n reported.
RS looks prognostic for LRR beyond nodal count, but it cannot yet select pN1 pts for PMRT omission. That question belongs to TailorRT (MA.39), which randomizes only low-RS pN1 pts. Nodal burden still dominates the risk at ≥4 nodes.
Retrospective correlative of a chemo trial with nonrandomized RT. Prespecified continuous-RS analysis null (P=.11); the cut at 18 was confirmed post hoc; nodal subsets exploratory with few events.
- Is PMRT omission safe in pN1 with low RS?
- Does RS predict LRR under modern systemic therapy?
- Does low LRR risk predict lack of RT DFS benefit?
📚 Sources · 📄 1 paper
Locoregional recurrence after neoadjuvant chemotherapy: pooled analysis of nine trials
ForPrimary breast cancer after anthracycline/taxane NACT, incl. cT4a-d
TL;DR5-yr LRR 4.1% with pCR vs 9.5% without (multivariate HR 3.33); TNBC non-pCR 18.5%. Surgery type not independent after NACT.
Residual disease interacts with subtype: TNBC non-pCR LRR was 18.5% at 5y versus 4.2% after pCR, and HR-/HER2+ 14.8% vs 3.1%. With RT use unrecorded, these rates show where post-neoadjuvant RNI/PMRT escalation trials should focus. Within pCR, only cN+ trended toward risk (HR 1.61, p=0.054), relevant to node-based de-escalation.
In TNBC or HR-/HER2+ breast cancer with residual disease after NACT, this backs a high-LRR-risk read when weighing PMRT and nodal coverage; after pCR it shows low LRR across subtypes but cannot say whether omitting RT is safe, because RT delivery was not recorded. The longer read
Residual-disease TNBC (18.5%) and HR-/HER2+ (14.8%) carry the 5-yr LRR burden, while pCR flattens every subtype to 3.1-4.8%. RT delivery was unrecorded, so this sets risk strata for PMRT/RNI decisions after NACT rather than proving that RT can be omitted after pCR.
Mastectomy's crude LRR excess (11.3% vs 7.8% for BCS) disappears on multivariate analysis, and surgery type predicted LRR in no subtype. After NACT, choosing mastectomy over BCS did not independently improve local control; response and biology did.
13 details 4 trials watching
Exploratory individual-patient-data pooled analysis of 9 prospective GBG/AGO-B neoadjuvant trials (GeparDuo through GeparSepto, PREPARE, TECHNO), 1998-2013. N=10,075; median follow-up 67 mo. Pathologic response was analysed with landmarking (multivariate set N=9552).
Histologically confirmed primary invasive breast cancer, tumour mostly ≥2 cm; locally advanced cT4a-c and inflammatory cT4d eligible in all trials except GeparDuo. 63.6% HR-positive, 28.1% HER2-positive; pCR (ypT0 ypN0) in 20.4%.
Anthracycline/taxane-based NACT in all trials. Anti-HER2 therapy varied by trial (trastuzumab, lapatinib, pertuzumab in later trials; none in GeparDuo, GeparTrio, PREPARE). Endocrine therapy ≥5 years for ER/PgR-positive pts.
Protocols recommended adjuvant RT per national guidelines, with RNI indicated mainly by nodal stage. No patient-level RT data were available, so receipt, fields and dose are unknown.
LRR as first event (breast/chest wall, axillary, infra/supraclavicular nodes) measured from surgery; distant recurrence, second malignancy and death were competing events.
5-yr LRR 7.8% BCS vs 11.3% mastectomy, but surgery type was not an independent predictor in multivariate analysis. Age, cN, grade, subtype and pCR were independent; non-pCR HR 3.33 and TNBC HR 2.72.
| Stratum | pCR | Non-pCR |
|---|---|---|
| HR+/HER2- | 3.9% | 5.9% |
| HR+/HER2+ | 4.8% | 8.1% |
| HR-/HER2+ | 3.1% | 14.8% |
| TNBC | 4.2% | 18.5% |
| BCS | 4.0% | 8.8% |
| Mastectomy | 3.9% | 11.3% |
The authors place this alongside the EBCTCG meta-analysis, which found higher local recurrence after NACT than after adjuvant chemotherapy, especially with suboptimal local therapy. The NSABP B-51 question (RNI after nodal pCR) is the RT decision these data frame but cannot answer.
Anti-HER2 therapy was inconsistent across eras, which the authors use to explain the lower LRR in HR+/HER2+ disease. gBRCA status incomplete; the univariate surgery effect is likely confounded by selection.
Biology and response drive LRR after NACT more than surgery type. The non-pCR TNBC and HR-/HER2+ groups are where locoregional escalation has the most room to show benefit. With RT unrecorded, the low post-pCR rates are not evidence that RT can be omitted.
Large mature IPD pool of prospective trials confirming known LRR predictors after NACT. Exploratory, prognostic only, and blind to RT delivery, so it cannot test an RT decision.
- Is RNI or PMRT safely omitted after nodal pCR in initially cN+ pts? active Standard or Comprehensive Radiation Therapy in Treating Patients With Early-Stage Breast Cancer Previously Treated With Chemotherapy and Surgery Phase NAn=1636 · primary completion 2023-09 · randomized regional nodal XRT vs none after chemo + surgeryn=100 · primary completion 2028-06 · RNI de-escalation in biopsy-proven cN1 → ypN0 after NATrecruiting Axillary Management in Breast Cancer Patients With Needle Biopsy Proven Nodal Metastases After Neoadjuvant Chemotherapy Phase NAn=1900 · primary completion 2030-02 · omit ALND + axillary RT if SLN negative post-NACT, cN1
- Does locoregional RT escalation reduce LRR in non-pCR TNBC? recruiting Internal Mammary Lymph Nodes Irradiation in High-risk Breast Cancer After Neoadjuvant Chemotherapy Phase 3n=722 · primary completion 2032-07 · phase 3 IMN RT vs none, ypN+ after NACT, DFS endpoint
- Do post-neoadjuvant T-DM1 or capecitabine lower LRR?
📚 Sources · 📄 1 paper
PMRT selection in T1-T2, 1-3 node-positive breast cancer
ForpT1-T2, 1-3 N+ breast after mastectomy + ALND, no PMRT
TL;DR10y KM LRR±SDR 15.9% without PMRT in pT1-T2 1-3 N+; age <45 with >25% nodes positive reached 58.0%.
Clavicular nodes carried 19 of 57 regional recurrences (33%) versus 2 for internal mammary, so the residual risk this model flags sits mostly in the axillary-supraclavicular field. In women ≥45 with ≤25% nodes positive, 10y LRR±SDR was 10.8%, near the authors' <10% omission threshold, while medial or ER-negative tumors pushed that subset to approximately 20%.
In a woman ≥45 with a lateral, ER-positive pT1-T2 tumor and ≤25% of ALND nodes positive, this supports discussing PMRT omission; it does not extend to SLNB-only staging, where the nodal-ratio factor cannot be computed. The longer read
Clavicular nodes carried 19 of 57 regional recurrences (33%) versus 2 for internal mammary, pointing PMRT coverage at the supraclavicular field. Age <45, >25% nodes positive, medial location and ER-negative status each moved 10y LRR above 20%, giving a factor-based frame for the 1-3 N+ PMRT discussion.
11 details
Retrospective population-based cohort from the BCCA Breast Cancer Outcomes Unit database. N=821 of 1117 identified, after excluding 296 who received RT. Cox multivariable modeling, then a classification model built from the significant factors. Median follow-up 7.7y.
pT1-T2, 1-3 positive axillary nodes, diagnosed 1989-1997, all treated with modified radical mastectomy and axillary dissection. Excluded pT3-T4, ≥4 N+, M1 and unknown pTN. Median age 62.
Adjuvant systemic therapy in 94% per BCCA guidelines: chemo alone 21.7%, hormonal alone 57.1%, both 15.1%. Chemo was AC, CMF or FAC; hormonal therapy was mostly tamoxifen.
No pt received locoregional RT; the study defines baseline no-PMRT risk to inform selection, not RT efficacy. Authors anchor benefit estimates on an RT relative LRR reduction of approximately two-thirds.
Primary: isolated LRR (chest wall, axillary, infraclavicular, IMN as first site) and LRR±simultaneous distant recurrence. Secondary: BCSS and OS.
Overall 10y LRR±SDR 15.9%. Each of age <45, T2, grade 3, ER-negative, medial location, >1 N+ or >25% N+ alone conferred >20% 10y LRR on univariate analysis. Age was the first model split (29.3% vs 13.7%, p<0.0001).
| Factor | ILRR HR (95% CI), p | LRR±SDR HR (95% CI), p |
|---|---|---|
| Age <45 vs ≥45 | 3.44 (1.68-7.07), p=0.001 | 3.22 (1.54-6.75), p=0.002 |
| >25% vs ≤25% nodes positive | 2.00 (0.99-4.05), p=0.05 | 2.61 (1.31-5.22), p=0.006 |
| Medial vs lateral | 2.46 (1.15-5.26), p=0.002 | 3.69 (2.17-6.29), p=0.0001 |
| ER-negative vs positive | 2.02 (1.16-3.54), p=0.01 | 1.82 (1.05-3.17), p=0.03 |
| Subgroup | N | ILRR | LRR±SDR |
|---|---|---|---|
| Age <45, >25% N+ | 19 | 47.6% | 58.0% |
| Age <45, ≤25% N+ | 104 | 18.5% | 23.8% |
| Age ≥45, >25% N+ | 122 | 20.6% | 26.7% |
| Age ≥45, ≤25% N+ | 570 | 8.7% | 10.8% |
No-PMRT LRR here (13-16% at 10y) sits well below the ~30% in DBCG 82b/82c and nearer the BCCA randomized trial (16% at 10y) and systemic-therapy trial cohorts (12-20%). Authors attribute the gap to axillary staging, systemic therapy and selection differences.
Excluding the 296 PMRT recipients likely removed higher-risk pts, biasing baseline risk downward. The >25% nodes positive ratio depends on ALND node yield, and its ILRR HR CI (0.99-4.05) touches 1. The ER status row in Table 1 shows a transposition in the source.
Authors propose <10% 10y LRR as a low-risk group that may be spared PMRT, >30% as justifying it, and 15-20% as the threshold for discussion. The model supports considering PMRT in all women <45 and recommending it when >25% of nodes are positive.
Retrospective single-province no-RT cohort; excluded PMRT recipients; data-driven breakpoints, no validation set; pre-taxane, ALND-era systemic therapy limits transfer to modern pts.
- Does the risk model validate with modern systemic therapy?
- Nodal-ratio factor usable after SLNB-only axillary staging?
- Do genomic risk scores refine PMRT selection in 1-3 N+?
📚 Sources · 📄 1 paper
CPS+EG staging and local-regional recurrence after neoadjuvant chemotherapy
ForBreast cancer post-NACT without trastuzumab, cStage III or ypN+
TL;DR5-yr freedom from LRR by CPS+EG score spanned 71% to 99%, vs 86% to 97% by clinical or pathologic stage, in 1697 pts after NACT.
The PMRT read is in the CPS+EG ≤2 slice of the PMRT-indicated cohort (cStage III or ypN+): 5-yr LRR-free survival did not differ by local therapy (P=0.73), but only 72 pts had mastectomy alone. ER-positive or low-grade biology drives those low scores, so the proposed de-escalation gate is biology on top of residual nodal stage.
In cStage III or ypN+ disease after anthracycline/taxane NACT with ER-positive or low-grade biology (CPS+EG ≤2), this is hypothesis-level support for discussing PMRT omission; it does not extend to pts treated with neoadjuvant trastuzumab or to CPS+EG ≥3. The longer read
The omission signal sits in ypN+ or cStage III pts with CPS+EG ≤2 (N=358, P=0.73 across local therapies), the group PMRT policy treats by default. Field design, dose and target volumes are not reported, so nothing here speaks to nodal coverage or de-escalated volumes, only to the yes/no PMRT decision.
Mastectomy alone carried the highest crude LRR (8.1% vs 5.5% BCT) and significantly higher LRR risk on MVA vs BCT. After NACT, choosing mastectomy does not reduce local-regional risk on its own; BCT outcomes held across the cohort.
15 details 1 trial watching
Retrospective analysis of two MD Anderson cohorts used to build (932 pts, 1997 to 2003) and validate (804 pts, 2004 to 2005) CPS+EG; 39 excluded, N=1697. Median f/u 51 mo.
All pts received neoadjuvant anthracycline and/or taxane chemotherapy; median age 50. Neoadjuvant trastuzumab and preoperative RT excluded; 20 pts missing ER or grade also excluded.
Local therapy: BCT 656 (39%), mastectomy alone 297 (17%), mastectomy + PMRT 744 (44%). Institutional PMRT indications were clinical stage III, ypN+, or select cT1/T2N1 with high-risk features. Dose, fractionation and fields not reported in source.
LRR = invasive cancer in ipsilateral breast, chest wall or regional nodes, counted regardless of distant timing. Objectives: CPS+EG vs stage for LRR stratification, and whether a score threshold could identify pts safely omitting PMRT.
5-yr freedom from LRR 71% to 99% by CPS+EG vs 86% to 97% by clinical or pathologic stage. In the PMRT-indicated cohort with CPS+EG ≤2, local therapy type made no difference (P=0.73).
| Local therapy | N | LRR events | Crude LRR |
|---|---|---|---|
| Breast conserving therapy | 656 | 36 | 5.5% |
| Mastectomy alone | 297 | 24 | 8.1% |
| Mastectomy + PMRT | 744 | 50 | 6.7% |
| CPS+EG score | 5-yr LRR-free (%) | 95% CI (%) |
|---|---|---|
| 0 | 97.8 | 91.3–99.5 |
| 1 | 98.6 | 95.8–99.5 |
| 2 | 95.3 | 92.4–97.1 |
| 3 | 93.5 | 90.2–95.7 |
| 4 | 85.4 | 79.8–89.6 |
| 5 | 79.0 | 67.5–86.8 |
| 6 | 70.8 | 49.8–84.3 |
| Subgroup | BCT N | Mastectomy alone N | Mastectomy + PMRT N | P |
|---|---|---|---|---|
| CPS+EG 0-2 (N=358) | 114 | 72 | 172 | 0.73 |
| CPS+EG 3-6 (N=745) | 202 | 51 | 492 | 0.0006 |
NSABP B-18/B-27 (cited) reported 10-yr LRR of 10.3% with BCT and 12.3% with mastectomy but gave no PMRT, so cannot address it. The MD Anderson Prognostic Index omitted ER and grade. NSABP B-51 later randomized regional nodal RT in cN+ → ypN0, a different population from the ypN+ pts here.
Prose direction for the CPS+EG ≥3 subgroup (mastectomy alone favored) contradicts the MVA; overall LRR is reported as both 6.5% and 6.1%. Median f/u of 51 mo is short for ER-positive disease, the biology driving the favorable scores.
The stratification claim is sound and adds biology to anatomic staging for LRR. The omission claim is a null comparison in a small, selected subgroup with no equivalence margin, so it frames a trial question rather than settling one.
Retrospective single-institution cohort; the PMRT-omission claim rests on a non-randomized subgroup with confounding by indication and only 72 mastectomy-alone pts.
- Is PMRT omission safe in ypN+ pts with CPS+EG ≤2 beyond 5 years?
- Does CPS+EG stratify LRR after modern anti-HER2 or immunotherapy NACT?
- Prospective validation of biology-based PMRT selection after NACT active Standard or Comprehensive Radiation Therapy in Treating Patients With Early-Stage Breast Cancer Previously Treated With Chemotherapy and Surgery Phase NAn=1636 · primary completion 2023-09 · randomized regional nodal XRT vs none in ypN0 after NAC
📚 Sources · 📄 1 paper
Long-term impact of regional nodal irradiation after neoadjuvant systemic therapy
ForcN+ stage II-III breast, NAT then BCS/mastectomy with ALND
TL;DRAdjusted LRR HR 0.497 and DR HR 0.731 with RNI after NAT in cN+ stage II-III breast; unadjusted 10-yr LRR 9.4% vs 8.1%, P=.62.
The unadjusted 10-yr LRR curves barely separate (9.4% vs 8.1%), yet RNI held up in residual-nodal disease on MVA (HR 0.476), which is where most RNI is already given. The axillary pCR arm stays uninformative: 5.5% vs 4.6% with too few events to model, so it does not answer the omission question.
In cN+ breast with residual axillary disease after NAT and ALND, this supports keeping RNI in the plan; it does not establish safe RNI omission after axillary pCR. The longer read
The unadjusted 10-yr LRR curves barely separate (9.4% vs 8.1%), yet RNI held up in residual-nodal disease on MVA (HR 0.476), where nodal coverage is already standard. The axillary pCR group (5.5% vs 4.6%) had too few events to model, so it cannot support omission.
12 details 3 trials watching
Single-institution retrospective cohort, N=1289, 1989-2007. Median follow-up 10.2 yrs after definitive surgery. LRR and DR by cumulative incidence with competing risks; Cox multicovariate models.
Stage II-III breast cancer with cytologically confirmed axillary metastases, NAT, then BCS or mastectomy with ALND. Axillary pCR in 368 (28.5%).
RNI defined as RT purposely directed to at least one regional nodal basin, at physician discretion, given to 1080 (83.8%). Median breast/chest wall 50 Gy/25 fx, median boost 10 Gy/5 fx; institutional standard covered undissected axilla, SCV and IMN, with variable field design. Of 209 without RNI, 142 had no RT at all.
LRR (breast or regional nodes) and DR (LRR or DM, first event), plus DSS and OS.
Univariate RNI effect null for LRR and DR. Adjusted, RNI reduced LRR (HR 0.497) and DR (HR 0.731), with the largest DR effect in HER2+ pts on trastuzumab (HR 0.237). No DSS or OS effect.
| Endpoint | No RNI | RNI | P |
|---|---|---|---|
| LRR, all pts | 9.4% | 8.1% | .62 |
| LRR, axillary pCR | 5.5% | 4.6% | .98 |
| LRR, no axillary pCR | 12.5% | 9.3% | .24 |
| DR, all pts | 31.3% | 36.5% | .16 |
| DR, axillary pCR | 20.3% | 15.9% | .25 |
| DR, no axillary pCR | 40.4% | 43.4% | .68 |
Authors read the benefit as carrying over the LRR and DM reductions seen in EORTC 22922 and MA.20 after adjuvant chemo into the NAT setting. They contrast prior HER2+ series (Danish 82b/c, SweBCG91-RT) suggesting relative radioresistance, and the ALTTO subset showing no RNI effect.
RNI pts had more adverse baseline features, so adjustment does heavy lifting. 'No RNI' may include unrecorded high tangents. Half the HER2+ cohort predated trastuzumab and was excluded from MVA, shrinking the subgroup behind the HR 0.237 estimate.
Supports RNI after NAT when nodal disease persists. Does not settle omission after axillary pCR; the authors defer that to B-51.
Retrospective, discretionary RNI with marked baseline imbalance; benefit appears only after covariate adjustment, univariate null. HER2+ trastuzumab DR signal is a subgroup estimate.
- Is RNI omission safe after cN1 to ypN0 conversion? active Standard or Comprehensive Radiation Therapy in Treating Patients With Early-Stage Breast Cancer Previously Treated With Chemotherapy and Surgery Phase NAn=1636 · primary completion 2023-09 · randomised regional nodal XRT vs breast/chestwall alonen=100 · primary completion 2028-06 · RNI de-escalation in biopsy-proven cN1 → pN0 after NATrecruiting Axillary Management in Breast Cancer Patients With Needle Biopsy Proven Nodal Metastases After Neoadjuvant Chemotherapy Phase NAn=1900 · primary completion 2030-02 · omits ALND + axillary RT in cN1 → ypN0 on SLNB, DFS 1° EP
- Does the HER2+ RNI benefit persist with modern HER2-directed NAT?
- Does the nomogram validate in an SLNB-staged cohort?
📚 Sources · 📄 1 paper
EBCTCG 20-year recurrence after 5 years of endocrine therapy
ForER+ T1-T2, 0-9 nodes, disease-free after 5y adjuvant endocrine therapy
TL;DRAfter stopping endocrine therapy at 5y, distant recurrence in years 5-20 ran from 13% (T1N0) to 41% (T2N4–9), at a steady annual rate.
In ER+ T1-T2 early breast cancer disease-free at 5 years, this frames the extension discussion around TN status, with T1N0 still carrying 13% distant risk over years 5 to 20; it does not address genomic-assay-selected or trastuzumab-treated HER2+ pts. The longer read
11 details
EBCTCG individual patient data meta-analysis of 88 trials. Kaplan-Meier and Cox regression, stratified by trial and treatment, from year 5 to year 20.
62,923 women with ER-positive T1-T2 disease, 0-9 positive nodes, diagnosed before age 75, scheduled to stop endocrine therapy at 5 years and event-free at year 5. 63% tamoxifen, 17% AI, 20% a tamoxifen-AI sequence; all had lymph-node dissection.
Distant recurrence, any breast-cancer event (distant, locoregional, contralateral), and death from breast cancer by log-rank subtraction.
Recurrences continued at a steady rate from year 5 to 20 in every TN category. Given TN status, grade and Ki-67 carried only moderate independent value after year 5; PR and HER2 status were not predictive.
| Nodal status | T1 | T2 |
|---|---|---|
| N0 | 13% | 19% |
| N1–3 | 20% | 26% |
| N4–9 | 34% | 41% |
| Grade | Distant recurrence | Any recurrence or contralateral BC |
|---|---|---|
| Low | 10% | 17% |
| Moderate | 13% | 22% |
| High | 17% | 26% |
| Nodal status | Distant recurrence | Death from breast cancer |
|---|---|---|
| N0 | 22% | 15% |
| N1–3 | 31% | 28% |
| N4–9 | 52% | 49% |
The source restates EBCTCG data that 5y tamoxifen cut recurrence by about 30% in years 5-10 versus no therapy. Extension trials such as ATLAS and MA.17 test the intervention; this analysis supplies the untreated baseline risk that their proportional benefit acts on.
Grade and Ki-67 were often locally assessed, and Ki-67 was available in only 7692 pts. Few pts received trastuzumab (2%), and treatment eras predate modern staging and systemic therapy.
No TN subgroup had a late risk low enough to dismiss extension outright, even low-grade T1N0 at 10% distant recurrence. Whether extension actually lowers mortality, and in whom it outweighs toxicity, is left to randomised data.
Large multi-trial IPD prognostic analysis, not a randomised test of extension. Quantifies baseline late risk; extended-therapy benefit must come from separate randomised trials.
- Does a genomic low-risk score identify pts safe to stop at 5 years?
- Does extended endocrine therapy reduce breast-cancer mortality, not just recurrence?
- How much do modern-era treatments lower these late risks?
📚 Sources · 📄 1 paper
SAKK 23/82
ForGood-risk ILRR after mastectomy, post excision + RT, TAM-naive
TL;DR5-yr DFS 61% vs 40% with tamoxifen after excision + RT for good-risk post-mastectomy ILRR; OS unchanged (median 11.5 vs 11.2 yr, P=0.79).
For the RT reader, failure after excision plus 5000 cGy at 200 cGy/fx was mostly further local recurrence, and TAM mainly reduced that, not distant spread. Endocrine therapy works here as a local-control partner to chest wall RT. ILRR is also not always a metastatic marker: about 30% stayed relapse-free on local therapy alone.
In a postmenopausal woman with ER+ isolated chest wall or nodal recurrence after mastectomy, resected and irradiated, this supports adding endocrine therapy for DFS. It does not cover premenopausal pts, who gained no DFS, or pts who already had adjuvant TAM. The longer read
Even after excision plus 5000 cGy at 200 cGy/fx, further local recurrence was the dominant failure, and TAM mainly reduced it. The trial supports full-dose curative-intent RT for good-risk ILRR combined with endocrine therapy as a local-control partner, not a replacement.
The DFS gain from TAM was confined to postmenopausal women (5-yr 61% vs 33%, P=0.006) and did not translate into OS. Because pts with prior adjuvant TAM were excluded, the trial does not say which agent to use for today's endocrine-pretreated ER+ ILRR.
11 details
Phase III randomized, central telephone randomization at SAKK, stratified by menopausal status, adjuvant chemo and axillary nodes at diagnosis. 178 randomized, 11 ineligible (6%). Median f/u 11.6 yr for surviving pts.
Good-risk ILRR after mastectomy: first recurrence in the ipsilateral chest wall, shoulder, neck or upper arm, or in regional nodes. Eligibility required an ER+ recurrence, or ER unknown with DFI >12 mo and <4 nodules ≤3 cm. Pts with prior adjuvant TAM were excluded.
Every pt had radical excision, then 5000 cGy at 200 cGy/fx, 5 days a week, to the involved region. RT was fixed across arms, so the trial tests systemic therapy added to full local therapy.
Tamoxifen 20 mg/d orally until progression vs observation.
DFS favored TAM (log-rank P=0.053, Gehan-Wilcoxon P=0.008), with no OS difference (P=0.79). The benefit was confined to postmenopausal pts (5-yr DFS 61% vs 33%, P=0.006). In the multivariate model, TAM and DFI >12 mo predicted longer DFS.
| Endpoint | TAM | Observation | P |
|---|---|---|---|
| Median DFS | 6.5 yr | 2.7 yr | 0.053 log-rank; 0.008 Gehan-Wilcoxon |
| 5-yr DFS | 61% | 40% | n/a |
| Median OS | 11.5 yr | 11.2 yr | 0.79 |
| 5-yr OS | 73% | 79% | n/a |
| Subgroup | TAM | Observation | P |
|---|---|---|---|
| Premenopausal DFS | 60% | 60% | n/a |
| Postmenopausal DFS | 61% | 33% | 0.006 |
| Premenopausal OS | 67% | 90% | 0.175 |
| Postmenopausal OS | 75% | 75% | n/a |
No deaths from pulmonary embolism or endometrial cancer attributable to TAM in either menopausal group.
The authors describe this as the only randomized trial of systemic therapy for ILRR to reach its accrual goal. IBCSG Trial 27 was opened to test chemotherapy vs local treatment alone in LRR, a question this trial does not address.
The early-weighted test carries the DFS result while log-rank misses 0.05. The menopausal split rests on small subgroups. Receptor status was not determined in about a third of pts.
The DFS benefit has persisted since the first analysis, but OS is unchanged, possibly because there were few events and competing mortality in postmenopausal pts. The premenopausal OS deficit with TAM is unexplained and nonsignificant, so it reads as noise more than harm.
Mature phase III, but small, 1980s accrual, borderline log-rank DFS and no OS gain. Backs current endocrine therapy after resected ILRR without defining it for TAM-pretreated pts.
- Aromatase inhibitor benefit after ILRR in tamoxifen-pretreated pts
- Role of chemotherapy for poor-risk ILRR
- Optimal RT dose and volume after ILRR excision
📚 Sources · 📄 1 paper
Node-negative post-mastectomy LRR and prognostic factors
ForNode-negative breast, T1-3, mastectomy + ALND, no PMRT
TL;DR10y LRR 6.0% overall in N0 post-mastectomy pts without PMRT, rising to 40.6% with 3 risk factors (size >2 cm, margin <2 mm, premenopausal, LVI).
Chest wall was the failure site in 80.4% of total LRRs, which is the basis for the authors' chest wall-only field proposal in high-risk N0. The 3-factor stratum (10y LRR 40.6% ± 13.8%) sits near the node-positive LRR range where PMRT gained survival, but its wide error makes it a threshold argument, not an indication.
In node-negative pts after mastectomy with T2+ tumor, deep margin <2 mm and LVI (or premenopausal with any 2 of these), this supports discussing chest wall PMRT; it does not extend to N0 pts with 0 or 1 factors (10y LRR 1.2% and 10.0%). The longer read
Chest wall was the failure site in 80.4% of total LRRs, supporting chest wall-only fields over regional nodal coverage in high-risk N0. The 3-factor stratum (10y LRR 40.6% ± 13.8%) frames a risk threshold for discussing PMRT, not proof of benefit.
13 details 1 trial watching
Retrospective single-institution cohort (Massachusetts General Hospital), 1980-2000, identified via tumor registry and breast center databases. Median f/u 100 mo. LRR estimated by cumulative incidence (CIF); KM results reported as slightly higher, not substantially different.
877 node-negative invasive cases (870 pts) after mastectomy + axillary dissection, no PMRT; T4 excluded. Median age 64, median 15 nodes examined. Systemic therapy in 276 cases (148 hormones alone, 74 chemo alone, 54 both).
Total LRR (first event, with or without simultaneous distant mets) and isolated LRR (no distant mets for ≥4 mo). Only total LRR reported for prognostic factors.
10y total LRR 6.0%. Size >2 cm, deep margin <2 mm, premenopausal status and LVI independent on MVA with similar HRs (range 2.6 to 3.8). 3 factors: 10y LRR 40.6%; only 1 pt had all 4.
| Risk factors | 10y LRR |
|---|---|
| 0 | 1.2% ± 0.9% |
| 1 | 10.0% ± 2.9% |
| 2 | 17.9% ± 7.5% |
| 3 | 40.6% ± 13.8% |
| Factor | Adverse | Favorable | p |
|---|---|---|---|
| Deep margin | Close 22%, positive 21% | Negative 5.1% | <0.001 |
| LVI | Present 19.8% | Other 5.0% | 0.0001 |
| Tumor size | >2 cm 11% | ≤2 cm 3.1% | 0.001 |
| Menopausal status | Pre 11.1% | Post 5.1% | 0.01 |
| Grade | G3 10%, G2 5.3% | G1 0% | 0.03 |
| Site | Isolated LRR | Total LRR |
|---|---|---|
| Chest wall | 28 (87.5%) | 37 (80%) |
| Axilla | 2 (6%) | 3 (7%) |
| Supraclavicular | 1 (3%) | 5 (11%) |
| IMC | 1 (3%) | 1 (2%) |
No RT delivered. Chest wall was the site in 87.5% of isolated and 80.4% of total failures, so the authors propose chest wall-only PMRT without regional nodes for high-risk N0 to limit toxicity.
Converges with the IBCSG analysis of 1,275 N0 women on size, LVI and menopausal status, and adds margin status, which IBCSG could not assess. The M. D. Anderson series (141 N0 pts) did not report absolute LRR for its N0 subset.
Most cases (601/877) had no systemic therapy, so absolute risks likely overstate the modern setting. Receptor subtype not reported. LVI not recorded was pooled with absent, and the risk count assumes equal weights.
Authors suggest considering PMRT for postmenopausal pts with all 3 of T2+, close/positive margin and LVI, and premenopausal pts with any 2. Benefit of PMRT in these strata is inferred from risk level, never tested.
Retrospective single-institution 1980-2000 cohort with no PMRT arm; stepwise risk model unvalidated, high-risk strata small with wide SEs. Defines who might benefit, not benefit itself.
- Does chest wall-only PMRT reduce LRR in high-risk node-negative pts? recruiting Trial Evaluating Role of Post Mastectomy Radiotherapy in Women With Node Negative Early Breast Cancer Phase NAn=1022 · primary completion 2028-12 · PMRT in pT1-2N0 with adverse prognostic factors
- Do modern systemic therapy and receptor subtype lower these LRR estimates?
- Can biomarkers refine LRR risk beyond clinicopathologic factors?
📚 Sources · 📄 1 paper
NSABP B-15/B-16/B-18/B-22/B-25 IBTR and LRR prognosis
ForNode-positive breast, lumpectomy + WBI + adjuvant chemo and/or tamoxifen
TL;DRAfter lumpectomy + WBI in node-positive pts, IBTR (HR 2.58) and other LRR (HR 5.85) predicted death; 5-yr OS 59.9% vs 24.1%.
Supraclavicular failure is the RT-relevant read: it made up 81 of 165 oLRRs and carried 5-yr DDFS 12.1% vs 31.5% after axillary recurrence. oLRR reached 14.6% at 10 yrs with ≥10 positive nodes, so nodal burden frames the regional-field question after BCS; field design was not reported in source.
In a node-positive pt with an isolated in-breast or regional recurrence after lumpectomy and WBI, this supports treating the event as a marker of high distant risk when weighing restaging and systemic options; it does not describe recurrence risk under taxane or HER2-directed therapy. The longer read
Supraclavicular failure dominated oLRR (81 of 165) and had 5-yr DDFS 12.1%, while oLRR hit 14.6% at 10 yrs with ≥10 nodes. This frames the regional-field question after BCS in node-positive disease, though WBI technique and nodal coverage were not reported in source.
An oLRR carried mortality HR 5.85 and an IBTR 2.58, with 5-yr DDFS 18.8% and 51.4% after each, so a locoregional relapse signals high distant risk. Whether chemotherapy at relapse helps was unresolved; regimens predate taxanes and HER2-directed therapy.
11 details
Pooled secondary analysis of 5 NSABP node-positive adjuvant trials (B-15, B-16, B-18, B-22, B-25). Cumulative incidence for IBTR and oLRR; IBTR and oLRR entered Cox models as time-varying covariates. Median time on study 13.3 yrs.
Of 10,010 women entered, 2,669 had breast-conserving surgery and were eligible. Negative margins were required; about two thirds had 1-3 positive nodes. B-18 contributed only its postoperative chemotherapy arm.
AC, CMF, PF/PAF and tamoxifen-based adjuvant regimens from 1984-1994, including AC cyclophosphamide intensification in B-22 and B-25. Pts aged >50 received tamoxifen in several protocols; premenopausal women did not receive tamoxifen irrespective of ER status.
All pts received whole-breast irradiation after lumpectomy. Dose, fractionation, boost and any regional nodal coverage are not reported in source.
Cumulative incidence of IBTR and oLRR; DDFS and OS after each event; mortality modeled with clinical factors plus IBTR or oLRR.
oLRR carried roughly double the mortality hazard of IBTR (HR 5.85 vs 2.58), and supraclavicular recurrence had the poorest DDFS. Arm-level values are in the detail table.
| Endpoint | IBTR | oLRR |
|---|---|---|
| Pts with event | 259 (9.7%) | 165 (6.2%) |
| 10-yr cumulative incidence | 8.7% | 6.0% |
| Events within 5 yrs | 62.2% | 80.6% |
| 5-yr DDFS after event | 51.4% | 18.8% |
| 5-yr OS after event | 59.9% | 24.1% |
| Mortality HR (time-varying Cox) | 2.58 (95% CI 2.11-3.15) | 5.85 (95% CI 4.80-7.13) |
| Adjusted HR, distant disease | 2.72 | 6.68 |
| Protocol | Pts at risk | 10-yr IBTR % | 10-yr oLRR % |
|---|---|---|---|
| B-15 | 624 | 10.0 | 7.6 |
| B-16 | 340 | 4.8 | 5.4 |
| B-18 | 210 | 9.1 | 8.7 |
| B-22 | 596 | 10.1 | 6.1 |
| B-25 | 899 | 8.3 | 4.5 |
| Total | 2,669 | 8.7 | 6.0 |
Consistent with the NSABP B-06 IBTR literature the authors cite and with the EBCTCG overview linking local failure to breast cancer mortality. The supraclavicular-dominant oLRR pattern is the population later addressed by randomized RNI trials such as MA.20 and EORTC 22922.
Lumpectomy was not the randomized variable, so the 2,669-pt subset is self-selected. Site-specific DDFS estimates rest on small numbers with wide CIs, and no HER2 or RT technique data are available.
oLRR clusters with nodal burden and receptor negativity, the same drivers of distant failure, so it may flag disseminated disease rather than cause it. Later IBTRs fared better, consistent with the authors' view that many are new primaries. The role of chemotherapy at recurrence was unresolved at publication.
Post-hoc pooled analysis of a non-randomized lumpectomy subset; LRR is a prognostic marker here, not a tested intervention target. Pre-taxane, pre-HER2 era therapy.
- Does regional nodal RT reduce supraclavicular failure in this population?
- Does chemotherapy at isolated locoregional recurrence improve survival?
- Can molecular profiling separate true IBTR from new ipsilateral primaries?
📚 Sources · 📄 1 paper
Abstract
T1-2N1 mastectomy without PMRT (MSKCC)
ForT1-2N1 breast, mastectomy + ALND, no neoadjuvant chemo
TL;DR10y LRR 7.0% without PMRT vs 4.0% with it (p=0.32) in T1-2N1 after mastectomy; age <40 + LVI reached 28% without PMRT.
The RT read is the no-PMRT stratification: 10y LRR 28% for age <40 with LVI vs 2% for ≥40 without LVI. Supraclavicular nodes carried 27% of LRRs and the axilla only 15.9%, so where PMRT is chosen for the high-risk stratum, the regional field targets where these pts actually failed.
In a woman ≥40 with T1-2N1, no LVI, after mastectomy with completion ALND and no neoadjuvant chemo, this supports omitting PMRT; it does not extend to a positive-sentinel axilla left undissected or to post-NAC pts. The longer read
Without PMRT, 10y LRR spans 2% (≥40, no LVI) to 28% (<40, LVI), defining whom to offer RT. Supraclavicular nodes carried 27% of LRRs versus 15.9% axillary involvement, supporting chest wall plus SCV coverage when PMRT is chosen.
The low LRR without PMRT rests on ALND in 94.2% with a median 18 nodes removed; the authors state omission does not apply to positive sentinel nodes without completion ALND. For women <40 with LVI, they suggest axillary RT may replace completion ALND.
13 details 4 trials watching
Single-institution retrospective cohort from a prospectively maintained database, mastectomy 1995-2006. PMRT given at physician discretion. Median follow-up 10.8 yr.
T1-2N1 (1-3 positive nodes), N=1087. Excluded T3/T4, neoadjuvant chemotherapy, and isolated tumor cells. Median age 51, median tumor 1.8 cm; 58% had one positive node.
All PMRT pts received chest wall RT; supraclavicular field in 137/163 (84%), axilla 7 (4%), IMN 6 (4%). Dose and fractionation not reported in source.
Systemic therapy in 98%; chemo 88%, mostly anthracycline and/or taxane. All ER+ pts received hormone therapy; trastuzumab in 51/123 HER2-amplified.
Without PMRT, age <40 (HR 4.15) and LVI (HR 3.47) independently predicted LRR. Chest wall (51%) and supraclavicular nodes (27%) dominated failure sites.
| Endpoint | PMRT (n=163) | No PMRT (n=924) | p |
|---|---|---|---|
| LRR | 4.0% | 7.0% | 0.32 |
| RFS | 75% (95% CI 69-82) | 73% (95% CI 69-76) | 0.46 |
| OS | 81% (95% CI 73-86) | 80% (95% CI 77-82) | 0.44 |
| Subgroup | 5-yr LRR | 10-yr LRR |
|---|---|---|
| <40, LVI | 15% | 28% |
| <40, no LVI | 6% | 11% |
| ≥40, LVI | 6% | 8% |
| ≥40, no LVI | 1% | 2% |
The EBCTCG 1-3 node subset showed 20.3% 10-yr LRR without PMRT, versus 7.0% here, a gap the authors attribute to modern systemic therapy and thorough ALND (median 18 nodes). EORTC 22922 included lumpectomy and stage I-III pts, limiting direct comparison.
Dose and target-volume data absent, so the 4.0% PMRT LRR cannot be tied to a technique. Pathology not re-reviewed, and HER2-directed therapy was incomplete in the cohort. The 10-yr LRR 28% subgroup CI as printed (11.0-22.1) excludes its own estimate.
The useful product is a risk filter for omission, not a PMRT efficacy estimate. It shows age and LVI separating a 2% from a 28% 10-yr LRR in unirradiated pts, which is the decision a T1-2N1 consult turns on.
Retrospective, non-randomized; PMRT selected for higher-risk pts, so null LRR/RFS/OS difference cannot estimate PMRT effect. Risk-stratification value lies in the no-PMRT cohort only.
- Does age/LVI risk stratification hold after SLNB without completion ALND? n=82 · primary completion 2024-12 · upfront mastectomy, 1-2 SN macromets, LRC with RTn=1900 · primary completion 2026-07 · 1-2 SN macromets, no axillary tx, age-stratified, incl…recruiting The T-REX Trial: Tailored Regional External Beam Radiotherapy in Clinically Node-negative Breast Cancer Patients With 1-2 Sentinel Node Macrometastases. Phase NAn=1350 · primary completion 2028-12 · randomised omission of regional RT, cN0 1-2 SN macromets
- Should intermediate-risk T1-2N1 pts (one of age <40 or LVI) receive PMRT? n=1106 · primary completion 2026-12 · phase 3 PMRT vs no PMRT in pN1, 7y DFS non-inferiority
- Does modern HER2-directed therapy lower LRR further without PMRT?
📚 Sources · 📄 1 paper
Close or positive margin after mastectomy and chest wall irradiation
ForT ≤5cm, 0-3 positive nodes, close (≤6mm) or positive deep margin, post-MRM
TL;DR8yr cumulative chest wall recurrence 28% age ≤50 vs 0% age >50 (p=0.04) with close/positive margin, T ≤5cm, 0-3 nodes, no PMRT.
Margin distance itself did not separate risk (≤2mm 24% vs 2.1-6mm 7%, p=0.36); age did, with 28% vs 0% chest wall failure at 8yr. For the PMRT decision in an otherwise low-risk mastectomy pt, this argues for weighting age ≤50 over margin proximity alone, and supports omission in older women with a close margin.
In a woman ≤50 after MRM with T1-T2 disease, 0-3 positive nodes and a deep margin ≤5mm, this supports discussing chest wall RT despite systemic therapy; it does not support PMRT for the margin alone in women >50, where no chest wall failures occurred in 12-13 pts. The longer read
Margin distance did not separate chest wall risk (≤2mm 24% vs 2.1-6mm 7%, p=0.36); age ≤50 did (28% vs 0% at 8yr). Supports considering chest wall RT for a close margin in younger women and questions it in women >50 with T ≤5cm and 0-3 nodes.
Gross deep-margin assessment missed 43% of tumors grossly >5mm but <1cm that were microscopically ≤5mm, while gross ≤5mm calls were 90% specific. Microscopic deep-margin assessment changes who is labelled close, and therefore who is referred for PMRT.
11 details
Retrospective single-institution review of 789 mastectomy pts at Fox Chase; 136 (17%) had tumor within 1cm of the deep margin. 34 pts met criteria and received no postoperative RT. Median f/u 59 mo (range 7-143).
Invasive breast cancer, clinical T ≤5cm, 0-3 positive nodes, microscopic deep margin ≤1cm, MRM in all. Median age 43 (29-76); 65% node-negative, 35% 1-3 positive nodes; no deep muscle involvement.
Chemo ± tamoxifen in 23 pts (CMF 12, CAF 10, AC 1); tamoxifen alone in 7. Systemic therapy tracked age: 91% of women ≤50 got chemo vs 25% of women >50.
5 chest wall recurrences, median interval 26 mo. Cumulative incidence 9% at 5yr, 18% at 8yr. Age ≤50 vs >50: 28% vs 0% at 8yr (p=0.04); margin ≤2mm vs 2.1-6mm 24% vs 7% (p=0.36). 5yr OS 82%, DFS 74%.
The source cites Ahlborn (margin ≤4mm 5.7% vs >4mm 3%) and Mentzer (≤5mm 11% vs >5mm 3%), neither significant and both crude rates at short f/u. This series adds the age interaction those did not report.
Age band estimates rest on 11-12 pts per group. 19 of 34 margins were not centrally re-reviewed. Systemic therapy is pre-taxane, pre-HER2-targeted, so absolute risks likely overstate contemporary failure rates.
The title's claim is really two claims: margin alone does not drive risk, and young age does. The first rests on a non-significant comparison in 34 pts, which is absence of evidence rather than evidence of no effect.
Retrospective single-institution series, 5 events; age subgroup confounded with chemo use (91% vs 25%); no RT comparator arm, so PMRT benefit inferred not measured.
- Does young age add chest wall risk independent of grade and systemic therapy?
- Absolute chest wall risk with modern systemic therapy for close margins
- Is PMRT omission safe for close margins in women over 50?
📚 Sources · 📄 1 paper
Isolated local-regional recurrence after mastectomy: radiotherapeutic management
ForFirst isolated LRR after mastectomy, no prior PMRT, no distant mets
TL;DR5-yr freedom from chest wall re-recurrence 75% with whole-chest-wall fields vs 36% with small fields (p=0.0001) in 224 pts irradiated for isolated LRR.
Field size carries the strongest signal: 67% of small-field failures landed outside the portal but within the chest wall, supporting whole-CW coverage. Elective SCV RT cut SCV failure 16% to 6%, while elective axillary RT raised arm edema 11% vs 1%, so cover the SCV fossa and leave the uninvolved axilla alone.
In a first isolated chest wall or nodal recurrence after mastectomy without prior PMRT, this supports whole-chest-wall plus supraclavicular coverage over involved-field RT; it does not extend to re-irradiation after prior PMRT or to the elective uninvolved axilla. The longer read
Two thirds of small-field failures landed outside the portal but within the chest wall, supporting whole-CW coverage. Elective SCV RT cut SCV failure 16% to 6%, while elective axillary RT raised arm edema 11% vs 1%, arguing for SCV coverage and omission of the uninvolved axilla.
15 details
Single-institution retrospective review, Mallinckrodt Institute and affiliates, 1964-1986, N=224 irradiated with curative intent. Median follow-up 46 mo (range 24-241); actuarial life-table method.
First isolated local-regional recurrence after radical (34%), modified radical (61%) or total (5%) mastectomy. Excluded prior postmastectomy RT, pts failing salvage elsewhere, and clinical or radiographic distant mets. Chest wall alone in 134 (60%).
Entire chest wall via tangents, 1.5-6.0 MV to 4500-5000 cGy with bolus and a 6-12 MeV electron boost to gross disease; SCV AP field to 4500-5000 cGy at 3 cm. About 90% treated at 180-200 cGy/d; small 1-2 cm-margin fields used early in the series.
At recurrence, 49 pts received chemotherapy (most often CMF or CAF) and 69 hormonal therapy, usually tamoxifen. Combined-modality vs RT-alone analysis deferred to a later report.
5-yr LRC 57%; whole-CW fields gave 75% vs 36% 5-yr freedom from CW re-recurrence vs small fields (p=0.0001). For <3 cm lesions, 100% controlled at ≥6000 cGy vs 76% lower; larger lesions about 50% even at 7000 cGy.
| Site | 5-yr OS | 5-yr RFS | 5-yr LRC |
|---|---|---|---|
| Chest wall alone | 50% | 35% | 63% |
| Nodal alone | 36% | 15% | 45% |
| Chest wall + nodal | 19% | 5% | 27% |
| p | 0.0002 | 0.0001 | 0.0084 |
| Field | 5-yr | 10-yr |
|---|---|---|
| Large (entire CW) | 75% | 63% |
| Small (1-2 cm margin) | 36% | 18% |
| p | 0.0001 | 0.0001 |
| Uninvolved site | Elective RT | No RT | p |
|---|---|---|---|
| Supraclavicular fossa | 6% | 16% | 0.0489 |
| Chest wall (any dose) | 17% | 27% | .32 |
| Chest wall (≥5000 cGy) | 12% | 27% | .20 |
Grade 2 sequelae 9%, grade 3 1%, none fatal. Arm edema 11% vs 1% with vs without elective axillary RT; pneumonitis higher with a parasternal field (8% vs 2% tangents alone).
Toonkel and co-workers, cited here, found a survival advantage with comprehensive nodal RT, while Deutsch reported the opposite, with that elective-nodal group carrying more extensive disease. Chen saw 27% failure in an uninvolved site after involved-field RT, consistent with this series' case for elective CW and SCV coverage.
Small-field group was only 14 pts and clustered in the early era, so the field-size effect also captures changes in staging workup and systemic therapy. The elective CW p-value is printed as both .32 and .33, and dose was set by physician preference.
The pattern of failure argues the whole chest wall carries subclinical disease, which favors comprehensive fields over excision alone or small portals. Large, diffuse or combined CW-plus-nodal recurrences stay poorly controlled at any dose, and the authors point to hyperthermia, altered fractionation or systemic combinations in prospective trials.
Single-institution retrospective spanning 22 years; field size, dose and elective coverage chosen by era and physician preference, so selection and era effects confound every comparison.
- Elective nodal RT benefit with contemporary systemic therapy
- Better local control for large or diffuse chest wall recurrences
📚 Sources · 📄 1 paper
Nomogram for four or more involved nodes in SLN-positive breast cancer
ForcN0 invasive breast, 1-3 H&E-positive SLNs, no neoadjuvant therapy
TL;DRAUC 0.83 in derivation and 0.81 in external validation for predicting ≥4 involved nodes after 1-3 positive SLNs, using 7 pathologic factors.
The RT question is field design. With a <5% predicted ≥4-node risk as the threshold, 34% of the derivation and 37% of the validation cohort were candidates to drop the SCV/apex field. The source ties adding that field to lymphedema rising from 2% to 8% to approximately 9% to 24%. The case for omission rests on high tangents covering most of levels I-II.
In cN0 pts with 1-3 H&E-positive SLNs and no completion ALND, a low predicted ≥4-node risk informs whether to add an SCV/apex field. It does not extend to post-neoadjuvant pts or keratin-only SLN deposits. The longer read
This informs the SCV/apex field when ALND is omitted. A <5% predicted ≥4-node risk covered 34% to 37% of pts, and the source ties adding the third field to lymphedema rising from 2% to 8% to approximately 9% to 24%. There are no regional-failure data behind the reduced field.
The model estimates residual nodal burden after 1-3 positive SLNs from pathology, including the number of negative SLNs and SLN metastasis size, without completion dissection. It informs whether completion ALND would change staging, but it was derived only in pts who had ALND with ≥6 nodes.
13 details 2 trials watching
Retrospective two-center review (MGH n=248, BWH n=154), N=402. Univariate and multivariate logistic regression, forward stepwise selection. External validation in a separate, previously published community-hospital set of 206 pts.
Clinically node-negative invasive breast cancer with 1-3 H&E-positive SLNs and completion ALND, defined as ≥6 nodes examined. No neoadjuvant systemic therapy. Mastectomy 46%, breast conservation 53%.
Outcome modeled: ≥4 involved axillary nodes (SLN plus non-SLN). Model performance was assessed by AUC, Hosmer-Lemeshow, sensitivity and NPV.
Seven independent factors: tumor size, lobular histology, LVSI, ENE, number of positive SLNs, macrometastasis, and number of negative SLNs. AUC 0.83 in derivation, 0.81 in validation. At a 5% cutoff, NPV 94.7% and sensitivity 97.5%.
The authors' hypothesis is that pts below 5% predicted risk could be treated with modified high tangents instead of comprehensive nodal RT to the SCV fossa and axillary apex. That would have spared 34% (derivation) and 37% (validation).
Similar in aim to the MD Anderson mastectomy series, where pts without three risk features had <2% risk of ≥4 nodes, and to Chagpar et al's 1,133-pt model. This model adds LVSI and SLN metastasis size. It predates the Z0011 and AMAROS axillary-management era.
The ≥6-node ALND definition may include axillary samplings. The abstract and results disagree on the count of ≥4-node pts (87 vs 81). Validation underestimated observed cases, and the validation set was chosen for availability.
The tool estimates nodal burden, a surrogate for the risk of regional failure. Whether tangent-only RT is safe in the low-risk group needs outcome data the paper doesn't have.
Retrospective model built on dissected pts with one small external validation. It predicts nodal burden, not regional recurrence after RT field reduction; the omission hypothesis was never tested.
- Is tangent-only RT safe for regional control in the <5% group? n=1900 · primary completion 2026-07 · RCT no axillary tx vs axillary tx, 5y axillary recurrencerecruiting The T-REX Trial: Tailored Regional External Beam Radiotherapy in Clinically Node-negative Breast Cancer Patients With 1-2 Sentinel Node Macrometastases. Phase NAn=1350 · primary completion 2028-12 · RCT omitting regional RT, 1-2 SN macromets, ER+/HER2-
- Does the nomogram stay calibrated in pts who never have completion ALND?
- Should field decisions use predicted nodal count at all?
📚 Sources · 📄 1 paper
Abstract
Nomogram for locoregional recurrence in T1-2N1 breast cancer (PMRT decision-making)
ForT1-2N1 breast, mastectomy + ALND, no neoadjuvant therapy
TL;DRHigh-risk nomogram tier (score >18): PMRT 5y LRR 2.2% vs 14.9%, HR 0.164; no LRR association in low or intermediate tiers.
The omission case is the low-risk tier: 5y LRR 0.4% without PMRT and 0/160 vs 2/252 events, so any RT gain there is bounded near zero. Benefit concentrates above score 18 (14.9% → 2.2% LRR, 7.0% BCM reduction) with chest wall plus supraclavicular/infraclavicular fields at 46-50 Gy, i.e. standard comprehensive PMRT.
In T1-2N1 pts after mastectomy and ALND without neoadjuvant therapy, ER-positive, grade I-II, LVI-negative T1 disease with 1-2 nodes, this supports a PMRT omission discussion; it does not address pts after neoadjuvant therapy. The longer read
Low-risk tier baseline 5y LRR is 0.4% with 0/160 vs 2/252 events, bounding any PMRT gain near zero and supporting omission. The high-risk tier (score >18) carries the benefit, 14.9% → 2.2% LRR, with standard chest wall plus supraclavicular/infraclavicular fields at 46-50 Gy.
13 details 3 trials watching
Retrospective single-institution cohort of 1141 consecutive pts treated 2001-2012. Nomogram from Fine and Gray competing-risks regression in 623 unirradiated pts; risk tiers by decision tree (CHAID); internal bootstrap validation only. Median follow-up 74.9 mo.
T1-2, 1-3 positive axillary nodes, mastectomy with negative margin plus ALND (median 17 nodes dissected). Excluded neoadjuvant therapy, synchronous metastases, other malignancy. All received adjuvant chemotherapy, 90.5% anthracycline- or taxane-based; median age 47.
46-50 Gy in 23-25 fx, CT-based planning. Fields: ipsilateral chest wall, infraclavicular and supraclavicular; IMN only for central tumors, axilla only with ECE.
LRR as first event (chest wall or regional nodes), DR and BCM, all as cumulative incidence with death as a competing risk.
Nomogram C index 0.73. Risk tiers by score: low ≤10 (n=412), intermediate (n=385), high >18 (n=344). PMRT associated with lower LRR, DR and BCM only in the high-risk tier.
| Group | LRR | DR | BCM |
|---|---|---|---|
| All pts (n=1141) | 1.6% vs 6.0%, HR 0.248 (0.121-0.509), P<.001 | HR 0.608 (0.425-0.871), P=.006 | P=.130 |
| Low risk (n=412) | P=.930 | P=.220 | P=.390 |
| Intermediate risk (n=385) | P=.240 | P=.500 | P=.430 |
| High risk (n=344) | 2.2% vs 14.9%, HR 0.164 (0.067-0.403), P<.001 | 8.4% vs 17.6%, HR 0.491 (0.288-0.837), P=.009 | 6.3% vs 13.3%, HR 0.371 (0.191-0.719), P=.003 |
EBCTCG showed PMRT benefit in 1-3 node pts, but its control 10-yr LRR of 21% is well above this cohort's 6.0% 5-yr unirradiated rate, which is the gap a risk model tries to exploit. SUPREMO (NCT00966888) is the prospective test of selective PMRT in this setting.
PMRT recipients skewed to adverse features, so within-tier comparisons carry residual confounding. Era of low trastuzumab use (26.2%) and no capture of nodal size or margin width; a prior 242-pt nomogram (Wadasadawala) used different factors.
The model mostly formalizes features clinicians already weigh (T stage, node count, ER, grade, LVI) into a score. Its value is the low-risk tier's very low baseline LRR, which supports omission, but the benefit estimates need external validation before they guide individual decisions.
Retrospective, clinician-allocated PMRT; risk cutoffs data-derived and tested on the same cohort without external validation. Low-risk null rests on 2 events.
- External validation in an independent, contemporary cohort
- PMRT benefit in the intermediate-risk tier with adequate events n=1106 · primary completion 2026-12 · phase 3 PMRT vs no PMRT in pN1, 7y DFS endpoint
- Role of PMRT after neoadjuvant therapy active Standard or Comprehensive Radiation Therapy in Treating Patients With Early-Stage Breast Cancer Previously Treated With Chemotherapy and Surgery Phase NAn=1636 · primary completion 2023-09 · randomised chestwall/nodal XRT after chemo + surgeryn=100 · primary completion 2028-06 · RNI de-escalation in cN1 → ypN0 after neoadjuvant tx
📚 Sources · 📄 1 paper
Chest wall recurrence outcome by initial stage
ForPost-mastectomy isolated CWR, no prior PMRT, no distant mets
TL;DR5-yr OS after isolated CWR 79.9% vs 41.9% vs 29.1% (T1-T2N0 vs T1-T2 1-3 N+ vs T3-T4/>4 N+); 1-3 N+ salvage as poor as advanced stage.
The RT read has two parts. Omitting RT for the CWR carried OS OR 4.524 on MVA, and pts with T1-T2 1-3 N+ disease salvaged no better than T3-T4/>4 N+ (5-yr OS 41.9% vs 29.1%). The PMRT decision in 1-3 N+ therefore rests on preventing CWR, not on rescuing it. Salvage dose and field are not reported.
In T1-T2 breast cancer with 1-3 positive nodes after mastectomy, this supports counting salvage of a chest wall recurrence as unreliable when weighing PMRT; it does not extend to T1-T2N0 pts, whose 5-yr OS after CWR was 79.9%. The longer read
Omitting RT for the CWR carried OS OR 4.524 on MVA, and pts with T1-T2 1-3 N+ disease salvaged no better than T3-T4/>4 N+ (5-yr OS 41.9% vs 29.1%). The PMRT discussion in 1-3 N+ should treat salvage as unreliable. Salvage dose and field are not reported.
17 details 1 trial watching
Single-institution retrospective chart review of pts seen for CWR at MD Anderson 1988-1998. Kaplan-Meier, log-rank and Cox regression; time 0 = CWR diagnosis. Median f/u 41.4 mo from CWR.
N=96 post-mastectomy pts with pathologically confirmed CWR, no prior PMRT, no distant mets at CWR. Groups: T1-T2N0 (n=41), T1-T2 with 1-3 N+ (n=20), T3-T4 or >4 N+ (n=35). Group 3 had more LVI (62.9%) and neoadjuvant therapy (40.0%).
XRT was part of CWR salvage in 70.7% / 75.0% / 68.6% (p=0.879). Of the 29 not irradiated, reasons included refusal (6), progression on systemic therapy (6), no referral (3) and unknown (10). Dose, fractionation and target volume are not reported.
OS and DMFS from the date of CWR.
5-yr OS 79.9% vs 41.9% vs 29.1% (p=0.0001); 5-yr DMFS 75.2% vs 33.6% vs 25.9%. Group 1 beat Groups 2 and 3, and Group 2 vs 3 did not differ (MVA OR 1.544, p=0.330). No XRT for CWR independently predicted worse OS (OR 4.524) and DMFS (OR 4.024).
| Feature | T1-T2N0 | T1-T2 1-3 N+ | T3-T4/>4 N+ | p |
|---|---|---|---|---|
| LVI present | 8 (19.5%) | 8 (40.0%) | 22 (62.9%) | <0.001 |
| Neoadjuvant therapy | 2 (4.9%) | 0 (0%) | 14 (40.0%) | <0.001 |
| Adjuvant systemic therapy | 15 (36.6%) | 17 (85.0%) | 27 (77.1%) | <0.001 |
| XRT for CWR | 29 (70.7%) | 15 (75.0%) | 24 (68.6%) | 0.879 |
| Surgery for CWR | 29 (70.7%) | 9 (45.0%) | 16 (45.7%) | 0.045 |
| Factor | OR (95% CI) | p |
|---|---|---|
| Group 1 vs 2 | 4.871 (1.756-13.510) | 0.002 |
| Group 1 vs 3 | 7.521 (2.761-20.482) | <0.001 |
| Group 2 vs 3 | 1.544 (0.645-3.699) | 0.330 |
| No XRT for CWR | 4.524 (2.064-9.918) | <0.001 |
| Interval to CWR ≤24 mo | 4.636 (2.106-10.206) | <0.001 |
The PMRT trials the authors cite showed ~30% → ~10% 10-yr LRR and a 9% absolute OS gain in high-risk populations, which supports PMRT for T3-T4 or ≥4 N+. This series adds the salvage half of the argument for 1-3 N+, where the authors describe the LRR risk without RT as ~10-15%.
Cox estimates are labeled 'OR'. Group 3 5-yr OS differs between abstract (29.1%) and Table 2 (21.8%), and the DMFS pairwise ORs duplicate the OS values. The benefit of salvage XRT is confounded by indication: pts progressing on systemic therapy were not irradiated.
If salvage of a CWR in 1-3 N+ disease is as poor as in advanced stage, then the PMRT decision has to rest on prevention, which means the absolute LRR reduction becomes the deciding number. The series cannot say what that reduction is worth in OS. The authors defer that to the randomized Intergroup trial.
Single-institution retrospective, n=20 in the key 1-3 N+ group, non-uniform salvage, internal table/text discrepancies; PMRT benefit inferred from salvage outcomes, never tested.
- Does PMRT improve OS in T1-T2 with 1-3 positive nodes? recruiting The T-REX Trial: Tailored Regional External Beam Radiotherapy in Clinically Node-negative Breast Cancer Patients With 1-2 Sentinel Node Macrometastases. Phase NAn=1350 · primary completion 2028-12 · RCT omitting regional RT, T1-2 cN0, 1-2 SLN macromets
- Does salvage outcome after CWR hold with modern systemic therapy?
- Optimal salvage RT dose and field for isolated CWR
📚 Sources · 📄 1 paper
RT CHARM (Alliance A221505) NCT03414970
ForPost-mastectomy, T0-3 N0-2a M0, immediate or delayed reconstruction
12.3% vs 10.2%
difference -2.1% (95% CI -6.5 to 2.2), noninferiority p=0.0001
TL;DR24-mo reconstruction complications 12.3% (42.56 Gy/16 fx) vs 10.2% (50 Gy/25 fx), difference -2.1% (95% CI -6.5 to 2.2); noninferior.
Reconstruction timing mattered more than fractionation: delayed reconstruction carried OR 2.96 for complications in either arm, while arm was not a predictor. LRR at 3 yr was 1.5% vs 2.2% and G2 dermatitis halved (20% vs 42%), so this supports 16 fx PMRT for reconstructed pts, including implant-only.
In a woman needing PMRT for T0-3 N0-2a disease with immediate or planned delayed reconstruction, implant or autologous, this supports 16-fraction PMRT over 25 fractions; it does not extend to T4, N3, positive margins or prior thoracic RT. The longer read
Supports 42.56 Gy/16 fx PMRT with reconstruction in place or planned: complications noninferior, 3-yr LRR 1.5% vs 2.2%, G2 dermatitis 20% vs 42%. Target volumes and boost use are not in the source excerpt, so nodal-coverage transferability still needs the full protocol.
Reconstruction timing, not RT schedule, drove complications: delayed vs immediate OR 2.96 (1.4-6.2) regardless of arm. Implant-only trended higher (OR 1.65, p=0.07). Fear of hypofractionation should no longer shape reconstruction type or timing choices.
13 details 2 trials watching
Unblinded 2-arm randomized noninferiority trial, 1:1, 209 US and Canadian sites, enrolled 2018-2021. N=898 enrolled, 825 evaluable (38 withdrew before RT, 35 ineligible). Median f/u 3.9 yr.
T0N1-2a, T1N1-2a, T2N1-2a or T3N0-2a, M0 after mastectomy, ECOG 0-1, with completed, ongoing or intended reconstruction. Excluded T4, N3, positive margins, collagen vascular disease, bilateral or prior ipsilateral cancer, prior thoracic RT. Median age 49, N1 76%, 51% neoadjuvant chemo.
50 Gy/25 fx over 5 wk vs 42.56 Gy/16 fx over 3 wk. IROC plan QA: 90% per-protocol or acceptable, 4% unacceptable. Target volumes and boost not stated in source excerpt.
Primary: composite reconstruction complications at 24 mo (wound healing, readmission, capsular contracture, unplanned reoperation, failure). NI margin 10%. Secondary: local/locoregional recurrence, acute and late toxicity.
NI met in ITT and in the 631 pts who completed reconstruction within 18 mo. Fractionation effect did not appear to differ by reconstruction type or timing.
| Endpoint | 42.56 Gy/16 fx | 50 Gy/25 fx | Effect |
|---|---|---|---|
| 24-mo reconstruction complications (ITT) | 12.3% (52/422) | 10.2% (41/403) | -2.1% (95% CI -6.5 to 2.2), NI p=0.0001 |
| Completed reconstruction within 18 mo (n=631) | 12.6% | 10.4% | -2.2% (95% CI -7.2 to 2.8), p=0.001 |
| 3-yr local/LR recurrence, cumulative incidence | 1.5% (0.7-3.2) | 2.2% (1.1-4.3) | Gray's test ns |
| 3-yr local/LR RFS | 97.0% (95.4-98.7) | 96.2% (94.3-98.2) | HR 1.01 (0.53-1.96), p=0.97 |
| Acute G3+ non-reconstruction toxicity | 5.0% | 7.7% | p=0.11 |
| Acute G2 dermatitis | 84 (20%) | 171 (42%) | p<.0001 |
| Acute G3 dermatitis | 3 (1%) | 11 (3%) | p=0.048 |
Acute G3+ non-reconstruction toxicity 5.0% vs 7.7% (p=0.11). RT-attributed toxicity similar except dermatitis, less frequent with hypofractionation. Late toxicity not statistically different.
Extends the hypofractionation evidence from post-lumpectomy trials (START, FAST-Forward) and post-mastectomy without reconstruction to the reconstructed chest wall, the setting where adoption lagged. Sits alongside FABREC, which tested the same 16-fraction schedule in implant reconstruction; RT CHARM adds autologous and delayed reconstructions.
Margin of 10% was powered on an assumed 25% control rate, but control ran 10.2%, so the margin is relatively generous. Unblinded assessment of complications; 35 pts lacked reconstruction forms at freeze. Late contracture and failure need longer f/u.
Reconstruction timing (delayed OR 2.96) moved complication risk far more than fractionation. The remaining questions are long-term reconstruction durability and whether shorter schedules (5 fx) hold up in this setting.
Randomized NI met across 209 sites with low LRR; wide 10% absolute margin against a 10.2% control rate and 3.9-yr f/u keep it short of practice-changing.
- Late capsular contracture and reconstruction failure beyond 4 years recruiting Hypofractionated vs. Conventionally Fractionated Postmastectomy Radiotherapy After Implant-Based Reconstruction Phase NAn=534 · primary completion 2033-10 · hypo vs conv PMRT post-implant; unplanned reoperation EP
- Five-fraction PMRT safety with reconstruction
- Optimal reconstruction timing relative to PMRT recruiting Breast Reconstruction and Radiotherapyn=750 · primary completion 2027-08 · cohort: reconstruction before vs after RT, complications
📚 Sources · 📄 1 paper
Abstract
AUA 2026: Consolidative local therapy after EV+pembro response (surgery vs radiation vs surveillance)
TL;DRRT-based preservation, cystectomy and surveillance each argued for cCR after neoadjuvant EV+pembro in MIBC; no randomized data compare the three options.
Reported via UroToday →
This point-counterpoint session asked how to manage the bladder in MIBC after cCR on neoadjuvant EV+pembro. The RT case held that clinical restaging misses residual disease, and that RT-based preservation keeps the bladder with better sexual function and body image than cystectomy. The surgical case held that all level 1 EV+pembro data include cystectomy, and that cCR predicts pCR only 51% of the time. The surveillance case shifted the question from pCR to MFS. It rested on a 97% PPV of cCR for 2-year MFS and on local recurrence coming before metastasis, which would allow salvage. ctDNA was presented as promising but not yet able to select pts.
- No data were shown on RT consolidation after EV+pembro; the RT case rests on chemo-era cohorts and observational TMT vs RC QOL comparisons, where pts chose their modality.
- The 97% PPV comes from GC + nivo in HCRN GU16-257; applying it to EV+pembro assumes a cCR means the same thing under a different regimen.
- The 51% cCR-pCR concordance measures residual pathology, not whether that residual changes MFS once surveillance and salvage are in place, so the surgical case treats pCR as if it were an outcome.
- RETAIN-1 vs RETAIN-2 is a cross-trial comparison in small surveillance cohorts (N=22 in RETAIN-2) after AMVAC-based therapy, not EV+pembro, and no trial compares RT, cystectomy and surveillance head to head.
KEYNOTE-905/EV-303KEYNOTE-B15/EV-304SWOG 0219RETAIN-1RETAIN-2HCRN GU16-257ARCHERBRIGHT
For RT, the key observation is the failure pattern: in RETAIN-2, no pt developed mets without a prior local recurrence, which is the premise behind both salvage RT and surveillance. BRIGHT (55 Gy/20 fx whole bladder, then pembro) is the trial that will test whether RT consolidation after cT0–T1 response adds bladder control beyond surveillance. No EV-era RT data exist yet.
In MIBC with cCR after neoadjuvant EV+pembro, the evidence leaves cystectomy, RT-based preservation and surveillance all open, each supported only by non-randomized or chemo-era data. It does not apply to pts with residual MIBC on restaging TURBT. The longer read
No EV-era data support RT consolidation after cCR yet. BRIGHT (55 Gy/20 fx whole bladder, then pembro for 12 mo) is the test. The local-before-metastatic failure pattern in RETAIN is what makes salvage RT a credible backstop for pts on surveillance.
Both phase III EV+pembro trials mandated cystectomy, and pooled cCR-pCR concordance is 51%, so omitting RC means leaving level 1 evidence behind. ctDNA negativity does not rule out ≥pT2 disease (67% residual), so a negative test cannot yet justify skipping surgery.
11 details 4 trials watching
AUA 2026 point-counterpoint session with three advocates (RT, cystectomy, surveillance), reported in a UroToday write-up. It argues across published and presented data and reports no new trial result.
MIBC (cT2–T4aN0M0 in the cited trials) with clinical complete response after neoadjuvant EV+pembro, i.e. the population treated per KEYNOTE-905/EV-303 and KEYNOTE-B15/EV-304.
The slide shows the BRIGHT schema: RT 55 Gy/20 fx to the whole bladder, then pembro 200 mg q21 days for 12 months, in pts with a cT0–T1 response confirmed by TURBT with systematic biopsies after ≥3 cycles of NAT. The ARCHER arm regimens were not legible on the slide.
In EV-303 and EV-304, every pt was planned for cystectomy, so the EFS and OS benefits (EV-303 EFS HR 0.40, OS HR 0.50) reflect EV+pembro plus RC. Organ-sparing evidence comes from RETAIN-1/2 and HCRN GU16-257, which used chemo or chemo-IO backbones, not EV+pembro.
The disagreement comes down to which endpoint cCR has to predict. Against pCR, cCR fails often (51% concordance); against MFS, it looked accurate in one GC + nivo trial (PPV 97%). If local failure reliably comes before metastasis, salvage keeps that miss from costing a cure, but this has not been shown after EV+pembro.
The trial IDs for ARCHER and BRIGHT differ between the write-up and the slide. The QOL comparison mixes TMT cohorts where pts chose their modality, and it shows worse pain and emotional functioning with TMT.
| Option | Core argument | Evidence cited |
|---|---|---|
| Bladder-preserving RT | cCR does not guarantee eradication; RT gives durable bladder control with a QOL advantage | SWOG 0219, RETAIN-2, TMT vs RC patient-reported outcomes |
| Radical cystectomy | Cystectomy is the backbone of all level 1 EV+pembro data; cCR is not pCR | KEYNOTE-905/EV-303, KEYNOTE-B15/EV-304, Roessler meta-analysis, RETAIN ctDNA |
| Surveillance | Most pts had pCR at cystectomy anyway; the real question is whether cCR predicts MFS | HCRN GU16-257, RETAIN failure patterns, ctDNA (Epstein, ASCO GU 2026) |
| Outcome | RETAIN-1 | RETAIN-2 |
|---|---|---|
| Local recurrence | 62% | 36% |
| Metastatic recurrence | 36% | 14% |
| MFS with intact non-irradiated bladder | 48% | 68% |
- Does cCR after EV+pembro predict MFS as it did after GC + nivo? not yet A Phase 2 Study Evaluating Bladder Preservation With Enfortumab Vedotin Plus Pembrolizumab in Patients With Muscle-Invasive Urothelial Cancer Phase 2n=25 · primary completion 2034-11 · EV+P clinical response-based sparing, no RC or RT
- Does RT consolidation improve bladder control over surveillance after cCR? recruiting Enfortumab Vedotin in Combination With Pembrolizumab vs. Concurrent Chemoradiotherapy (cCRT) in People With Muscle Invasive Bladder Cancer (EV-309) Phase 3n=390 · primary completion 2030-03 · phase 3 EV+P alone vs chemoRT for bladder preservationn=56 · primary completion 2031-04 · response-adapted EV+P induction, then RT, CRT or RC
- Can ctDNA select pts to safely omit cystectomy? recruiting NEO-BLAST: Neoadjuvant Therapy for Bladder Cancer Followed by Active Surveillance vs Treatment Phase 2/3n=688 · primary completion 2028-12 · ctDNA/MRI-selected surveillance vs definitive therapy
📚 Sources · 📄 1 paper
Abstract
PACE-A (sexual function, 5-year) NCT01584258
ForLocalised prostate cT1-T2, Gleason ≤3+4, PSA ≤20, surgical candidates, no ADT
TL;DR5y median EPIC-26 sexual score change -42 after prostatectomy vs -17 after SBRT (p=0.02); IIEF-5 median 5 vs 19 (p<0.001).
No ADT was permitted, so the SBRT trajectory (median EPIC-26 79 to 58) is attributable to 36.25Gy/5 fractions alone, not a hormonal confound. By the trial's own p<0.01 rule only IIEF-5 (median 19 vs 5) is positive, and clinician-graded ED was similar (27% vs 35%). Counselling data, not a claim of preserved function.
In men with cT1-T2, Gleason ≤3+4 localised prostate cancer who are prostatectomy candidates and weight erectile function heavily, this informs the SBRT vs surgery discussion with randomised 5-year PRO data; it does not extend to disease treated with ADT or address cancer control. The longer read
No ADT was permitted, so the SBRT trajectory (median EPIC-26 79 to 58) is attributable to 36.25Gy/5 fractions alone. By the trial's own p<0.01 rule only IIEF-5 (median 19 vs 5) is positive, and clinician-graded ED was similar (27% vs 35%). Counselling data, not a claim of preserved function.
Median EPIC-26 sexual score fell from 62 to 17 after prostatectomy, with 18/22 (82%) crossing the MCID. Approach was mixed (open, laparoscopic, robot assisted) and nerve-sparing use is not reported, so the figure may not reflect a contemporary nerve-sparing robotic series. Analysis was by treatment received.
Also covered Sep 28
12 details
PACE is a phase III open-label multiple-cohort RCT; PACE-A randomised 1:1 to SBRT or prostatectomy. 123 randomised (60 prostatectomy, 63 SBRT) between August 2012 and February 2022. Sexual outcomes analysed by treatment received.
Early localised prostate cancer, cT1-T2, Gleason ≤3+4, PSA ≤20 ng/mL, and suitable for prostatectomy. Baseline median EPIC-26 sexual domain score was 62 in the prostatectomy group and 79 in the SBRT group.
36.25Gy/5 fractions delivered in 1-2 weeks. ADT not permitted. Platform, margins and target volume not stated in source.
Comparator was prostatectomy by open, laparoscopic or robot-assisted approach. Nerve-sparing status not stated in source.
Co-primary (previously reported): 2-year bowel and urinary symptoms. Secondary, reported here through 5 years: EPIC-26 sexual domain score, proportion with MCID (≥11-point reduction), IIEF-5, clinician-reported CTCAE grade ≥2 erectile dysfunction. Significance threshold p<0.01.
All patient-reported measures favoured SBRT in direction; only IIEF-5 met the prespecified p<0.01 threshold. Clinician-graded erectile dysfunction was similar between groups.
| Endpoint | SBRT | Prostatectomy | p |
|---|---|---|---|
| EPIC-26 sexual domain, median baseline → 5y | 79 → 58 | 62 → 17 | n/a |
| EPIC-26 median change from baseline | -17 (IQR -43 to 0) | -42 (IQR -58 to -24) | 0.02 |
| MCID (≥11-point reduction) | 19/35 (54%) | 18/22 (82%) | 0.03 |
| IIEF-5 median | 19 | 5 | <0.001 |
| CTCAE G≥2 erectile dysfunction | 13/48 (27%) | 13/37 (35%) | 0.48 |
ProtecT randomised prostatectomy against external beam RT given with ADT, so its sexual-function comparison carried a hormonal confound that PACE-A avoids. PACE-A is described by its authors as the first randomised comparison of SBRT and prostatectomy with long-term sexual outcomes.
Baseline sexual scores were unbalanced (median 62 vs 79), and the MCID analysis rests on 22 and 35 men. Surgical approach was mixed and nerve-sparing use is not reported. Accrual ran from 2012 to 2022, so technique on both sides spans a decade.
The direction is consistent across three patient-reported measures, which carries more weight than any single p-value here. SBRT still produced a decline (median change -17), so the result is a relative advantage, not preserved function. Cancer control is not reported in this abstract.
CONSORT flow
Secondary PRO endpoint, open-label, analysed as treated; EPIC-26 and MCID p-values miss the trial's own p<0.01 threshold. PRO return 60% and 63% at 5y.
- Does the sexual-function gap hold against nerve-sparing robotic prostatectomy alone?
- Does SBRT erectile function keep declining beyond 5 years?
- Oncologic outcomes for SBRT vs prostatectomy in PACE-A
📚 Sources · 📄 1 paper
Abstract
NRG/RTOG 9601 (transcriptomic analysis)
ForProstate cancer, salvage RT ± high-dose bicalutamide, GC score available
TL;DRSecondary analysis, n=352, 18.2y median f/u: GC per 0.1 prognostic for PCSM, sHR 1.34 (1.17-1.54); AAT benefit by GC showed no significant interaction.
The sRT decision in play is hormone omission at low pre-sRT PSA: at PSA <0.7, 15y PCSM benefit from AAT was -2% with GC <0.6 vs 16% with GC ≥0.6. At PSA ≥0.7 the gradient reverses (12% vs 6%), so GC here ranks risk more reliably than it selects for hormones.
In sRT candidates with pre-sRT PSA <0.7 and GC <0.6, this informs the discussion of sRT without hormone therapy as hypothesis-level evidence (15y PCSM benefit with AAT -2%); it does not extend to contemporary ADT, which this trial did not test. The longer read
The sRT decision in play is hormone omission at low pre-sRT PSA: at PSA <0.7, 15y PCSM benefit from AAT was -2% with GC <0.6 vs 16% with GC ≥0.6. At PSA ≥0.7 the gradient reverses (12% vs 6%), so GC ranks risk more reliably than it selects for hormones. RT dose and volume not reported.
11 details
Secondary analysis of NRG/RTOG 9601, a phase 3 trial of sRT ± high-dose bicalutamide, using GC scores (Veracyte) from a prior translational project. GC-available cohort n=352, median follow-up 18.2 years. Multivariable Cox or Fine-Gray models, adjusted (s)HR with 95% CI.
Pts treated with sRT on NRG/RTOG 9601 who had a GC score. Median GC 0.59 (Q1-Q3 0.42-0.76); 29%, 23%, 38% and 11% were low, intermediate, high and very high risk. Other baseline features not reported in source.
sRT with or without high-dose bicalutamide (AAT). Bicalutamide dose and duration not reported in source.
Salvage RT in both arms. Dose, fractionation and target volume not reported in source.
Primary objective: prognostic impact of GC (per 0.1) on PCSM. Secondary: OS, MFS, DM. Additional: PCSM and OS by pre-defined GC strata, and PCSM benefit of AAT by GC (<0.6 vs ≥0.6) within pre-sRT PSA subgroup (<0.7 vs ≥0.7).
GC was independently prognostic for every profiled endpoint (tables above). The AAT-by-GC estimates are absolute 15-year PCSM differences with no significant interaction in either PSA stratum.
| Endpoint | Adjusted (s)HR | 95% CI |
|---|---|---|
| PCSM (primary objective) | sHR 1.34 | 1.17-1.54 |
| OS | HR 1.18 | 1.09-1.27 |
| MFS | HR 1.16 | 1.08-1.25 |
| DM | sHR 1.20 | 1.07-1.35 |
| Endpoint at 15 years | Low GC | Very high GC | Difference |
|---|---|---|---|
| PCSM | 4% | 52% | 48% |
| OS | 75% | 25% | 50% |
| Pre-sRT PSA | GC <0.6 | GC ≥0.6 |
|---|---|---|
| <0.7 | -2% | 16% |
| ≥0.7 | 12% | 6% |
Extends the earlier GC validation in this same trial with final outcomes, and layers GC onto the prior 9601 finding that pre-sRT PSA predicts AAT benefit. GETUG-AFU 16, NRG/RTOG 0534 (SPPORT) and RADICALS-HD tested ADT with post-prostatectomy RT; none is addressed in this source.
AAT benefit by GC is given as point estimates only: no CIs, no cell sizes. PCSM was chosen as primary for this secondary analysis because of suspected other-cause mortality with bicalutamide, which sets aside the endpoint where AAT harm would show. Whether the GC-available subset matches the full trial is not reported.
The prognostic claim is well supported at long follow-up. The predictive claim is not: the GC gradient runs in opposite directions in the two PSA strata. The authors frame GC-guided selection for modern ADT in early sRT as a hypothesis, which is the right ceiling.
Secondary biomarker analysis of a GC-available subset; predictive claim rests on non-significant interactions, and the hormone agent was high-dose bicalutamide, not contemporary ADT.
- Does GC predict benefit from contemporary ADT with early sRT?
- Do intermediate and high GC strata separate on 15-year PCSM and OS?
- Does the AAT-by-GC pattern hold for OS, not just PCSM?
📚 Sources · 📄 1 paper
Abstract
NRG-GU003
ForPostprostatectomy, pT2/3 pNX/0: detectable PSA, or undetectable with pT3/margin+
TL;DR5-yr: G3 GU AEs 13% HYPORT (62.5 Gy/25 fx) vs 3% COPORT (66.6 Gy/37 fx), p=0.003; EPIC scores and 5-yr BF (21% vs 18%) no different.
Physician-graded and patient-reported toxicity diverge: grade 3 cystitis (7% vs 0%) and hematuria (6% vs 0.7%) are higher with 62.5 Gy/25 fx, yet 5-yr EPIC urinary change (-8.0 vs -5.7, p=0.4) does not separate, on 56% EPIC compliance. The decision is prostate-bed hypofractionation with a disclosed bleeding-type GU risk, not a toxicity-neutral swap.
In men after prostatectomy with pT2/3 pNX/0 disease and a detectable PSA, or an undetectable PSA with pT3 or margin-positive pT2, this supports prostate-bed HYPORT as an option alongside COPORT; it does not extend to pelvic nodal RT, which the source does not report. The longer read
62.5 Gy/25 fx to the prostate bed carries more physician-graded grade 3 cystitis (7% vs 0%) and hematuria (6% vs 0.7%) than 66.6 Gy/37 fx, while 5-yr EPIC urinary change (-8.0 vs -5.7, p=0.4) and 5-yr BF (21% vs 18%, p=0.3) do not separate. This informs the prostate-bed fractionation choice, with bleeding risk part of consent.
12 details 3 trials watching
Phase 3 trial, 296 men randomized (152 COPORT, 144 HYPORT). This is the 5-year report; median follow-up 7 years (range: 0 to 8). Blinding, stratification and site count are not stated in source.
Postprostatectomy men with either a detectable post-op PSA (source prints "=0.1 ng/mL") and pT2/3 pNX/0 disease, or an undetectable PSA (<0.1 ng/mL) with pT3 disease or pT2 with a positive surgical margin. The split between these two groups is not reported in source.
HYPORT: 62.5 Gy to the prostate bed in 25 fractions of 2.5 Gy. COPORT: 66.6 Gy in 37 fractions of 1.8 Gy, 48% more fractions. Pelvic nodal RT, technique and ADT use are not reported in source.
Primary (reported at 2 years): patient-reported GU and GI toxicity by EPIC, where HYPORT was noninferior. Secondary, reported here: EQ-5D quality of life, AEs, overall survival, prostate-cancer specific survival, and biochemical failure (PSA 0.4 ng/mL and rising; source prints the operator as "=").
Arm-level figures are in the table. No difference in 5-yr EPIC bowel or urinary change scores, EQ-5D change, or 5-yr BF; 31 deaths, 4 (13%) due to prostate cancer.
| Endpoint | HYPORT | COPORT | p |
|---|---|---|---|
| Grade 3 AEs | 16% (23 men) | 7% (11 men) | p=0.02 |
| Grade 3 renal and urinary disorders | 13% (18 men) | 3% (5 men) | p=0.003 |
| Noninfective cystitis | 7% | 0% | not reported |
| Hematuria | 6% | 0.7% | not reported |
| 5-yr EPIC bowel change score | -2.0 | 0.6 | p=0.1 |
| 5-yr EPIC urinary change score | -8.0 | -5.7 | p=0.4 |
| EQ-5D change, baseline to 5 yr | 0.0 | -0.01 | p=0.5 |
| 5-yr biochemical failure | 21% | 18% | p=0.3 |
Grade 3 AEs 16% (23 men) HYPORT vs 7% (11 men) COPORT, p=0.02, driven by grade 3 renal and urinary disorders, 13% vs 3% (p=0.003): noninfective cystitis 7% vs 0%, hematuria 6% vs 0.7%. No grade 4-5 RT-related AEs, one grade 3 stricture (COPORT), and time to grade 3 AEs did not differ (p=0.4).
Moderate hypofractionation for the intact prostate rests on large randomized trials such as CHHiP and PROFIT; the postoperative bed has lacked comparable randomized data. The authors state the grade 3 GU rates, including the excess with HYPORT, were consistent with contemporary series, which the source does not name.
The patient-reported reassurance rests on 56% EPIC and 51% EQ-5D compliance at 5 years, with no account of who dropped out. BF is a secondary endpoint with no stated noninferiority margin, and p-values for the cystitis and hematuria differences are not given.
HYPORT buys a shorter course at the cost of a physician-reported grade 3 cystitis/hematuria excess that patient-reported scores do not register. Biochemical control looks comparable (5-yr BF 21% vs 18%, p=0.3) but the trial was built around toxicity, so equivalence of disease control is suggested, not established.
CONSORT flow
Phase 3 RCT with its primary PRO noninferiority endpoint met at 2 yr; 5-yr update agrees on PROs and BF but adds a physician-reported G3 GU excess. Abstract only.
- Does prostate-bed hypofractionation hold with pelvic nodal RT or concurrent ADT?
- Ultrahypofractionated (SBRT) prostate-bed RT vs moderate hypofractionation recruiting Post-prostatectomy Radiation Therapy--Moderate Versus Ultra-hypofractionated (Also Known as Stereotactic Body Radiation Therapy [SBRT]) Phase 2n=136 · primary completion 2026-11 · randomized ph2 SBRT vs mod hypofx post-RP, 2-yr QOLrecruiting Salvage Stereotactic Body Radiotherapy of the Prostate Bed for Biochemical Recurrence After Radical Prostatectomy. Phase NAn=284 · primary completion 2029-02 · randomized ph2/3 salvage bed SBRT vs SOC RTn=206 · primary completion 2031-09 · ph3 5-fx bed SBRT vs mild hypofx, PRO QOL non-inferiority
- Do grade 3 cystitis/hematuria events keep accruing beyond 7-yr follow-up?
📚 Sources · 📄 1 paper
Abstract
SOFT Preop
ForResectable, borderline or LA type A PDAC, ECOG 0-2, post >1 mo neoadj chemo
41% vs 38%
SBRT vs Chemo-RT, p = 0.754, ns; chemo-RT superiority hypothesis not met
TL;DRPath node positivity 41% SBRT vs 38% chemo-RT (p = 0.754) preop in PDAC; mOS 26.04 vs 42.96 mo (p= 0.639); QOL favored SBRT.
Local/regional recurrence split 6 SBRT vs 2 chemo-RT (8 events, 7.8%) at median follow-up 3.4 years, with elective nodes at 25 Gy/5 and primary at 33-40 Gy in 5, mostly on 1.5 T adaptive MR guidance. The preop fractionation choice moves toward SBRT on QOL only where that nodal volume and platform are reproduced.
In resectable, borderline, or LA type A PDAC already through >1 month of neoadjuvant chemo and planned for preop RT, this informs choosing 5-fraction SBRT over 28-fraction chemo-RT on QOL grounds; it does not address whether preop RT adds to chemo alone. The longer read
Local/regional recurrence split 6 SBRT vs 2 chemo-RT (8 events, 7.8%) at median follow-up 3.4 years, with elective nodes at 25 Gy/5 and primary at 33-40 Gy in 5, mostly on 1.5 T adaptive MR guidance. The fractionation choice moves toward SBRT on QOL only where that nodal volume and platform are reproduced.
83/98 (84.7%) reached resection, 41 SBRT and 42 chemo-RT, with no difference in surgical complications, so the 5-fraction course did not cost operability. Node positivity was 41% vs 38%; margin negativity and pathologic response are called equal but no figures appear in the abstract.
11 details 1 trial watching
Prospective, randomized phase II, 1:1 allocation after neoadjuvant chemo. 102 pts targeted and enrolled, anticipating a 15% drop out before surgery; 4 withdrew after enrollment. Median follow-up among all enrolled pts 3.4 [2.6, 5.1] years.
Resectable, borderline, or locally advanced (LA) type A PDAC, ECOG 0-2, > 1 month of neoadjuvant chemo. Median age 65 (34-82); 38%/42%/20% resectable, borderline, and LA type A. Prior chemo was FOLFIRINOX (79%), gemcitabine/nab-paclitaxel (12%), or other (9%), with 92% receiving more than 2 months.
Chemo-RT: 50.4 Gy/28 fractions with weekly gemcitabine or capecitabine. SBRT: 25 Gy/5 to elective nodes and 33-40 Gy in 5 to the primary, without concurrent chemo. Most SBRT pts were treated using 1.5 T adaptive MRI guidance.
Primary: pathologic node positivity, hypothesizing lower rates with chemo-RT. Secondary: PFS, OS, patient-reported QOL (PROMIS), physician-reported toxicity, surgical complications, translational endpoints.
Arm-level figures are in the table. 83/98 (84.7%) completed all intended therapy including surgical resection, equal in both arms.
| Endpoint | SBRT | Chemo-RT | p |
|---|---|---|---|
| Path node positivity | 41% | 38% | p = 0.754 |
| Median OS | 26.04 mo (95% CI 17.9 to 59.28) | 42.96 mo (95% CI 18.72 to 54.72) | p= 0.639 |
| Alive at 3 years | 42.6% | 57.5% | p = 0.198 |
| PFS | 14.28 mo (95% CI 9-29.64) | 21.6 mo (95% CI 10.56-38.04) | p = 0.96 |
| Local/regional recurrence (events) | 6 | 2 | not reported |
| Completed all therapy incl. resection | 41 | 42 | not reported |
No difference in surgical complications; no rates given. Physician-reported toxicity was a secondary endpoint but is not reported in the abstract. PROMIS physical function, global physical health, and fatigue were better preserved with SBRT (p = < 0.05).
Alliance A021501 tested preop SBRT or hypofractionated RT against chemotherapy alone, and PREOPANC established gemcitabine-based preop chemo-RT against upfront surgery. Neither compared one RT schedule with another. The authors describe this as the first randomized trial comparing SBRT with chemo-RT in the neoadjuvant setting for PDAC.
Abstract only: no per-arm allocation counts, no QOL magnitudes or timepoints, and no figures for pathologic response or margin negativity despite the conclusion citing them. QOL is patient-reported in an unblinded comparison. Concurrent agent varied in the chemo-RT arm and primary SBRT dose ranged 33-40 Gy.
The trial shows SBRT is deliverable preop with equal resection completion and better QOL, and it does not show nodal sterilization differs. It does not settle survival equivalence: median OS 26.04 vs 42.96 mo and LRR 6 vs 2 point the same direction in a sample too small to resolve them.
Randomised phase II, N=102, built to show chemo-RT superiority on nodal positivity and null. Not an equivalence design; survival and LRR lean numerically toward chemo-RT.
- Is preop SBRT non-inferior to chemo-RT for OS in PDAC?
- Does 25 Gy/5 elective nodal SBRT give adequate regional control?
- Does any preop RT add to neoadjuvant FOLFIRINOX alone? recruiting Preoperative mFOLFIRINOX (or Gem-Nab-P) +/- Isotoxic High-dose SBRT for Borderline Resectable Pancreatic Adenocarcinoma Phase 2n=256 · primary completion 2027-12 · preop mFOLFIRINOX +/- isotoxic high-dose SBRT in BRPC
📚 Sources · 📄 1 paper
Abstract
NRG-HN009 (p16-negative phase II toxicity)
Forp16-negative locoregionally advanced SCCHN, 70 Gy RT + concurrent cisplatin
T-score ratio 1.11
90% upper confidence bound 1.33, p=0.77 · phase III criteria not met
TL;DRT-score ratio (weekly/Q3) 1.11, p=0.77: weekly cisplatin not less toxic with 70 Gy in p16-negative locoregionally advanced SCCHN, no phase III.
6-mo LRF was 4.6% (Q3) vs 9.6% (weekly), absolute difference 5.0% (95% CI 1.0, 8.9), despite worse RT QA on Q3 (81% vs 94% per protocol or acceptable). RT quality does not explain the gap. With 70 Gy fixed, schedule choice rests on toxicity type, not total G3-4 burden.
In p16-negative locoregionally advanced SCCHN receiving 70 Gy with concurrent cisplatin, this questions choosing weekly 40 mg/m2 on tolerability grounds, since G3-4 event counts were not lower; it does not extend to the p16-positive cohort, reported separately. The longer read
6-mo LRF was 4.6% (Q3) vs 9.6% (weekly), absolute difference 5.0% (95% CI 1.0, 8.9), despite worse RT QA on Q3 (81% vs 94% per protocol or acceptable). RT quality does not explain the gap. With 70 Gy fixed, the concurrent schedule is the variable to weigh for locoregional control.
Weekly 40 mg/m2 traded toxicities instead of lowering them: G3-4 AKI 11% vs 3% and nausea 12% vs 4% on Q3, WBC decrease 28% vs 14% and hypomagnesemia 8% vs 2% on weekly. Chemotherapy delivery was per protocol or acceptable in 80% on Q3 vs 98% on weekly; cumulative dose not reported.
12 details 1 trial watching
Randomized phase II/III; this is the phase II acute toxicity report for the p16-negative cohort. 234 randomized (118 Q3, 116 Q1) between Oct 2021 and Sept 2025; 91% completed all follow-up up to 6 months. QA modality reviews were done on a random sample of cases.
p16-negative locoregionally advanced SCCHN. Median age 60; 76% male; 58% Zubrod 0; 87% former or current smokers, 70% >10 pack-years. 57% larynx, 28% oropharynx, 15% hypopharynx; 83% T1-3 and 74% node-positive.
Cisplatin 100 mg/m2 Q3 weeks (Q3) vs cisplatin 40 mg/m2 weekly (Q1), each with RT. Chemotherapy delivery scored per protocol or acceptable variation in 80% on Q3 vs 98% on Q1. Cumulative cisplatin dose delivered is not reported in source.
70 Gy in both arms; fractionation, technique and target volumes are not reported in source. RT reviews were completed for 91% of sampled pts, scored per protocol or acceptable variation in 81% on Q3 vs 94% on Q1.
acute toxicity by T-score, the number of all treatment-related grade 3-4 AEs during treatment or within six months. To proceed to phase III, the mean T-score ratio (Q1/Q3) had to be below 1 at 1-sided p<0.1, together with a 6-month locoregional failure difference criterion (printed as '= 8%' absolute in the portal text).
The cohort did not meet criteria for continuing to phase III; arm-level values are in the tables.
| Endpoint | Q1 Cis (weekly) | Q3 Cis | Effect |
|---|---|---|---|
| Mean T-score | 2.48 (95% CI 1.97, 2.99) | 2.23 (95% CI 1.81, 2.65) | Ratio 1.11 (90% upper bound 1.33), p=0.77 |
| 6-month locoregional failure | 9.6% | 4.6% | Absolute difference 5.0% (95% CI 1.0, 8.9) |
| AE term | Q3 Cis | Q1 Cis |
|---|---|---|
| Nausea | 12 | 4 |
| WBC decreased | 14 | 28 |
| Dehydration | 9 | 1 |
| Hypomagnesemia | 2 | 8 |
| Acute kidney injury | 11 | 3 |
Total G3-4 burden was similar, but the profile differed by schedule. Q3 carried more G3-4 nausea (12% vs 4%), dehydration (9% vs 1%) and acute kidney injury (11% vs 3%); weekly carried more WBC decrease (28% vs 14%) and hypomagnesemia (8% vs 2%). Late toxicity is not reported in source.
The Tata Memorial randomized trial (Noronha et al.) favored Q3 over a lower weekly dose for locoregional control in a mostly postoperative population, while JCOG1008 supported weekly dosing after surgery. This cohort tests the schedule question with 70 Gy RT in p16-negative disease and gives no toxicity support for weekly; the source draws no comparison to either trial.
The T-score weighs every G3-4 event equally, so marrow and renal events are interchangeable in the primary. QA was scored on a random sample, not all cases, and per-arm cumulative cisplatin dose is missing. The portal text has lost the inequality in the LRF criterion, so the abstract alone does not show whether that half of the rule passed.
The tolerability premise for weekly cisplatin did not hold here: toxicity was redistributed, not reduced. The LRF difference favors Q3 but rests on a 6-month read in a toxicity-driven phase II, so it is a direction, not an efficacy result. Pooled results for all 475 pts were deferred to the presentation.
CONSORT flow
Randomized, prespecified phase II go/no-go analysis; weekly failed its toxicity criterion, leaving Q3 as the reference schedule. Abstract only; 6-month LRF is immature and not an efficacy test.
- Does the 6-month LRF gap persist in longer-term locoregional control and survival?
- Do pooled p16+ and p16- results (475 pts) show the same toxicity pattern?
- Late toxicity and hearing outcomes by cisplatin schedule n=100 · primary completion 2028-09 · randomized weekly LD vs HD cisplatin CRT, p16-stratified
📚 Sources · 📄 1 paper
Abstract
30 Gy vs 40 Gy consolidative RT, limited-stage DLBCL
ForStage I-II DLBCL, CR/CRu after anthracycline-based chemo ± rituximab
90.5% vs 87.2%
HR 0.87, 95% CI 0.59-1.28; one-sided P = 0.0013 for non-inferiority
TL;DR5-yr PFS 90.5% (30 Gy) vs 87.2% (40 Gy), HR 0.87 (0.59-1.28), non-inferiority met in stage I-II DLBCL in CR after chemo.
The local-regional read backs the PFS headline: locoregional recurrence did not differ between 30 Gy and 40 Gy involved-site/field RT, though no rates are given in the source text. Toxicity, including second malignancies, was also comparable at 7.2 years median f/u, so the late-effect gain from de-escalation is inferred, not shown.
In stage I-II DLBCL in CR/CRu after anthracycline-based chemo with or without rituximab, this supports 30 Gy over 40 Gy as the consolidative dose; it does not extend to pts short of CR, and it does not test omitting RT. The longer read
The local-regional read backs the PFS headline: locoregional recurrence did not differ between 30 Gy and 40 Gy involved-site/field RT, though no rates are given in the source text. Toxicity, including second malignancies, was also comparable at 7.2 years median f/u, so the late-effect gain from de-escalation is inferred, not shown.
12 details 1 trial watching
Multicenter, open-label, non-inferiority phase 3, randomized 1:1. 432 pts enrolled April 14, 2010 to July 1, 2019; median follow-up 7.2 years. Non-inferiority margin not reported in source.
Newly diagnosed stage I-II DLBCL achieving CR/CRu after anthracycline-based chemo with/without rituximab. Age criterion printed as '=15 years' in the portal text. Bulk, IPI and PET status at response not reported in source.
30 Gy vs 40 Gy consolidative involved-site/field RT. Fraction size, technique and the split between involved-site and involved-field volumes are not reported in source.
Primary: 5-year PFS, tested for non-inferiority of 30 Gy. Also reported: OS, locoregional recurrence, acute and late toxicity including second malignancies.
Primary endpoint met (table). OS and locoregional recurrence showed no difference between arms; the source gives no rates or HRs for either.
| Endpoint | 30 Gy | 40 Gy | Effect |
|---|---|---|---|
| Randomized | n=216 | n=216 | 1:1 |
| ITT analysis | 212 | 213 | n/a |
| 5-yr PFS (95% CI) | 90.5% (86.5-94.7) | 87.2% (82.7-91.9) | HR 0.87 (0.59-1.28), one-sided P = 0.0013 for non-inferiority |
Acute and late toxicities, including second malignancies, were comparable between arms. No rates or grades reported in source, so no measured toxicity advantage for 30 Gy.
The source states no prior randomized trial compared these two doses in DLBCL specifically. The UK NHL dose-reduction RCT (Lowry et al.) asked a similar de-escalation question in aggressive NHL more broadly, and ILROG guidance already favors the lower consolidative dose after CR, so this result is concordant with that direction.
Enrollment spans 2010 to 2019 with rituximab optional and response graded as CR/CRu, so systemic therapy and response assessment may not match current PET-adapted practice. Mixed involved-site/field volumes are not broken out. Abstract only: no event counts, no margin.
With PFS near 90% in both arms and locoregional recurrence no different, the higher dose bought no measurable disease control in pts already in CR. What the trial does not settle is whether the lower dose reduces late effects (not shown at 7.2 years) and whether any RT is needed after a PET-negative response.
CONSORT flow
Randomised phase 3, prespecified non-inferiority primary met at 7.2-year median f/u; source calls 30 Gy the new standard. Caveats: margin and fractionation unreported, rituximab optional.
- Can consolidative RT be omitted after PET-negative CR in limited-stage DLBCL?
- Does 30 Gy reduce late toxicity or second malignancies with longer follow-up?
- Is a dose below 30 Gy adequate after CR to rituximab-containing chemo? active Dose-Reduced Consolidation Radiation Therapy in Patients With Diffuse Large B-cell Lymphoma Phase NAn=243 · primary completion 2025-07 · 30 Gy to 20 Gy consolidation RT after PET-neg R-chemo
📚 Sources · 📄 1 paper
Abstract
TORCH-iTNT NCT06281405
ForpMMR LARC, T3-4/N+ M0, 96.6% with at least one high-risk feature
61.5% vs 37.1%
48/78 with SCRT vs 26/70 without; no p-value or CI reported
TL;DRCR (pCR + cCR) 61.5% with SCRT 25Gy/5Fx → CAPOX + toripalimab vs 37.1% without RT in pMMR LARC; no p-value reported.
The RT read sits in cCR, not pCR: 25 pts after SCRT 25Gy/5Fx vs 7 without RT reached cCR and went to W&W, so the short course is what opened the organ-preservation route. The no-RT arm still carried adjuvant chemoradiotherapy for positive circumferential margins, at a rate the source does not report.
In pMMR LARC (T3-4/N+ M0) with high-risk features where organ preservation is the aim, this supports retaining SCRT ahead of CAPOX plus PD-1 inhibitor; it does not extend to dMMR disease, and it does not show that omitting RT preserves function. The longer read
The RT read sits in cCR, not pCR: 25 pts after SCRT 25Gy/5Fx vs 7 without RT reached cCR and went to W&W, so the short course is what opened the organ-preservation route. The no-RT arm still carried adjuvant chemoradiotherapy for positive circumferential margins, at an unreported rate.
CAPOX plus toripalimab without RT gave a 37.1% (26/70) CR rate in pMMR LARC, but with no chemotherapy-alone arm the PD-1 inhibitor's contribution is unmeasured. G3-4 thrombocytopenia was similar across arms (12.9% vs 14.1%), so adding SCRT did not visibly cost hematologic tolerance of six cycles.
Omitting RT sent more pts to resection: 58 of 70 in the no-RT arm had surgery vs 52 of 78 after SCRT, with 7 vs 25 entering W&W. pCR among resected was 32.8% vs 44.2%. Margin status, sphincter preservation and anorectal function are not yet reported.
11 details 1 trial watching
Multicenter randomized phase II, 192 pMMR LARC pts enrolled. Initial results as of January 31, 2026 cover the 148 who completed treatment (70 in Group A, 78 in Group B). Allocation ratio, stratification and follow-up duration are not stated in source.
pMMR LARC, T3-4/N+ M0. Baseline characteristics described as balanced. 96.6% (143/148) had at least one high-risk feature: low tumor location, cT4, cN2, MRF+ or EMVI+.
Group A: 6 cycles of CAPOX plus toripalimab. Group B: SCRT followed by the same 6 cycles. cCR pts were offered W&W, non-cCR pts were recommended for surgery.
SCRT 25Gy/5Fx before immunochemotherapy in Group B. Group A received no neoadjuvant RT, with adjuvant chemoradiotherapy reserved for positive circumferential margins. Target volumes, technique and the interval from SCRT to response assessment are not reported in source.
Primary: complete response rate, defined as pCR plus cCR. Secondary: organ preservation rate, anorectal function, adverse events and survival outcomes.
Thrombocytopenia was the most common grade 3-4 AE, 12.9% in Group A and 14.1% in Group B. No other AE data, and no RT-attributable or surgical toxicity, are reported in source.
TORCH, the same group's predecessor, tested induction vs consolidation sequencing of SCRT with CAPOX and toripalimab; this trial asks instead whether SCRT can be dropped. UNION set SCRT followed by immunochemotherapy against long-course chemoradiotherapy. PROSPECT asked the RT-omission question with chemotherapy alone in a lower-risk population than the one enrolled here.
cCR criteria and the assessment timepoint are not stated, and cCR calls cannot be blinded to arm. The pCR denominator in Group B excludes the 25 cCR pts who went to W&W, so resected-only pCR is not a like-for-like comparison. No chemotherapy-alone arm, so toripalimab's contribution is unmeasured.
The gap in CR is carried mostly by clinical responses, which is the outcome that matters for W&W and also the softer of the two components. The rationale for the no-RT arm was functional sparing, yet 58 of 70 Group A pts went to surgery vs 52 of 78 in Group B, and anorectal function is not yet reported. Regrowth after W&W will decide whether the cCR advantage holds.
Initial results in 148 completers of 192 enrolled; no p-value or CI; CR is an early response endpoint, and organ preservation, function and survival readouts are pending.
- Local regrowth rate after W&W in each arm not yet the Efficacy of MR-guided Online Adaptive Radiotherapy for Locally Advanced Rectal Cancer Phase NAn=49 · primary completion 2026-12 · SCRT on MR-linac; W&W local recurrence rate endpoint
- Anorectal function with vs without SCRT
- Does toripalimab add to CAPOX alone in pMMR LARC without RT?
📚 Sources · 📄 1 paper
Abstract
STELLAR II NCT05484024
ForMid-to-low pMMR LARC; T3-4 94.9%, node-positive 92.9%
51.9% vs 26.8%
150/289 vs 78/291, P<0.001; phase 3 primary 3-year DFS not yet reported
TL;DROverall CR 51.9% vs 26.8% (P<0.001) adding sintilimab to SCRT (5 Gy x5) + CAPOX TNT in pMMR LARC; 3-year DFS pending.
The RT backbone is 5 Gy x5 with 100% completion, so the CR gain comes on a schedule any department can deliver. The surgical denominators (211 iTNT vs 247 TNT) show fewer iTNT pts reached the OR, though the per-arm split of the 92 W&W pts is not reported. The decision in play is SCRT-based TNT plus PD-1 blockade as an organ-preservation route.
In mid-to-low pMMR LARC planned for SCRT-based TNT where organ preservation is a goal, this supports sintilimab as a CR-raising addition at the cost of more grade 3-4 toxicity; it does not yet inform DFS and does not extend to long-course CRT-based TNT. The longer read
The RT backbone is 5 Gy x5 with 100% completion, so the CR gain comes on a schedule any department can deliver. Fewer iTNT pts reached surgery (211 vs 247 operated), though the per-arm W&W split is not reported. This informs SCRT-based TNT plus PD-1 blockade as an organ-preservation route; technique and target volumes are not in source.
Sintilimab was the only randomized variable on a fixed SCRT + CAPOX backbone, and 86.1% received at least 4 cycles without loss of chemo completion (92.9% vs 94.1%). The price is grade 3-4 toxicity of 27.7% vs 19.9%. This is a checkpoint-inhibitor signal in pMMR disease, with DFS still unreported.
pCR was 41.7% (88/211) vs 19.4% (48/247) among operated pts, and 92 pts (15.6%) entered W&W after cCR. In a cohort with 71.3% lower tumors, that bears on sphincter preservation. Regrowth rates, salvage outcomes and surgical morbidity are not reported in source.
9 details 4 trials watching
Multicenter, randomized, phase 2/3 trial. 658 screened and 588 randomized from August 2022 to August 2025 (296 iTNT, 292 TNT). Data as of February 6, 2026; blinding not stated in source.
Mid-to-low pMMR LARC. Median age 59, 71.1% male. T3-4 94.9%, node-positive 92.9%, lower tumors 71.3%, MRF+ 48.8%, EMVI 45.4%.
SCRT followed by 4 cycles of CAPOX with sintilimab (iTNT) or the same regimen without sintilimab (TNT). After evaluation, resection or W&W, then 2 additional cycles of the same prior regimen.
SCRT 5 Gy x5 in both arms, delivered first. All pts completed SCRT. Technique, target volumes and the interval to surgery are not reported in source.
Primary: CR rate for phase 2 and 3-year DFS for phase 3. This report covers short-term efficacy and safety only.
Arm-level CR, pCR, toxicity and compliance are in the table above. 92 pts (15.6%) adopted W&W after cCR, and 458 had undergone surgery with 8 awaiting.
| Endpoint | iTNT (SCRT + CAPOX + sintilimab) | TNT (SCRT + CAPOX) | P |
|---|---|---|---|
| Overall CR | 51.9% (150/289) | 26.8% (78/291) | P<0.001 |
| pCR (operated pts) | 41.7% (88/211) | 19.4% (48/247) | not reported |
| Grade 3-4 toxicity | 27.7% | 19.9% | not reported |
| 4-cycle chemo completion | 92.9% | 94.1% | not reported |
Grade 3-4 toxicities 27.7% (iTNT) vs 19.9% (TNT). Grade 3-5 immune-related AEs in 3.4% of pts. Chemotherapy completion was similar (92.9% vs 94.1%); surgical morbidity is not reported.
Per the source, several phase II studies suggested that adding immunotherapy to TNT raises CR, but phase 3 comparisons of TNT with vs without immunotherapy were lacking. RAPIDO and the original STELLAR trial established SCRT-based TNT, while UNION and TORCH tested SCRT plus checkpoint blockade without an otherwise-identical immunotherapy-free TNT control.
Overall CR pools pathological and clinical response, and whether cCR assessment was blinded is not stated. pCR is computed on operated pts only, with unequal denominators (211 vs 247). The per-arm W&W split is not reported.
The randomized variable is sintilimab alone, so the trial isolates the drug and says nothing about SCRT vs long-course CRT as its partner. A higher CR opens an organ-preservation route, but whether it converts to DFS in pMMR disease is unsettled until the phase 3 primary reads out.
CONSORT flow
Randomized and fully accrued, but this is a short-term CR readout; the phase 3 primary (3-year DFS) and W&W regrowth data are not yet reported.
- Does the higher CR rate translate into a 3-year DFS benefit?
- Regrowth rate and durability of W&W after iTNT recruiting CAPOX and PD-1 Antibody Combined With or Without Radiotherapy for MSS Locally Advanced Rectal Cancer Phase 2n=192 · primary completion 2026-06 · W&W for cCR after SCRT + toripalimab-CAPOX iTNTrecruiting Personalized Long-course Radiotherapy Plus Chemotherapy With or Without Immunotherapy for LARC: PALACE Study Phase 3n=184 · primary completion 2027-07 · CR endpoint requires cCR sustained over 1 year
- Does the PD-1 benefit hold with long-course CRT-based TNT? recruiting Personalized Long-course Radiotherapy Plus Chemotherapy With or Without Immunotherapy for LARC: PALACE Study Phase 3n=184 · primary completion 2027-07 · phase 3 long-course RT + chemo ± serplulimab, CR endpointrecruiting Neoadjuvant Chemoradiotherapy Followed by Chemotherapy With or Without Tislelizumab for Resectable Ultra-low Rectal Cancer: The RELIEVE-02 Study Phase 3n=196 · primary completion 2027-12 · phase 3 long-course CRT then CAPOX ± tislelizumab, pMMR
📚 Sources · 📄 1 paper
Abstract
CHN HYPOPMRT (10-year) NCT00793962
ForHigh-risk breast cancer, post-mastectomy and axillary dissection
HR 1.13
90% CI 0.77-1.66; 9.6% hypofractionated vs 8.6% conventional
TL;DR10yr LRR 12.0% (43.5 Gy/15fx) vs 10.3% (50 Gy/25fx), HR 1.19 (95% CI 0.79-1.82); G1-2 pulmonary fibrosis 19.7% vs 11.7%.
Late lung is the additive read: G1-2 pulmonary fibrosis 19.7% with hypofractionation vs 11.7% (p=0.008), against no G4-5 late toxicity and no brachial plexopathy at median 11.5 yr. Fields were chest wall plus supraclavicular only, so the plexus safety transfers to that volume, not to IMN-inclusive RNI.
In high-risk breast cancer after mastectomy and axillary dissection, this supports 43.5 Gy in 15 fractions to chest wall and supraclavicular region as an alternative to 50 Gy in 25; it does not extend to reconstruction or IMN-inclusive fields, which the source does not describe. The longer read
Late lung is the additive read: G1-2 pulmonary fibrosis 19.7% with hypofractionation vs 11.7% (p=0.008), against no G4-5 late toxicity and no brachial plexopathy at median 11.5 yr. Fields were chest wall plus supraclavicular only, so the plexus safety transfers to that volume, not to IMN-inclusive RNI.
11 details 3 trials watching
Open-label, phase 3, randomized, non-inferiority trial at a single national cancer center in China, 1:1. 820 enrolled (June 2008 to June 2016), 810 in mITT (409 conventional, 401 hypofractionated). Median follow-up 11.5 yr (IQR 9.6 to 13.8).
Women with high-risk breast cancer after mastectomy and axillary dissection. Stage, nodal burden, receptor status, systemic therapy and reconstruction status are not given in the source.
43.5 Gy in 15 fractions over 3 weeks vs 50 Gy in 25 fractions over 5 weeks, to the chest wall and supraclavicular region. Technique, IMN or axillary coverage, bolus and boost are not described in the source.
Primary: 5-year cumulative incidence of locoregional recurrence. Secondary: DFS, OS, late radiation-related toxicity. Outcomes through 10 years were analyzed descriptively.
LRR and fibrosis by arm are in the table. 10-yr DFS (65.2% vs 69.9%) and OS (72.9% vs 77.5%) showed no significant difference; the source does not make the arm order explicit for these two.
| Endpoint | 43.5 Gy/15 fx | 50 Gy/25 fx | Effect |
|---|---|---|---|
| 5-yr LRR (1° EP) | 9.6% | 8.6% | HR 1.13 (90% CI 0.77-1.66; 95% CI 0.72-1.79) |
| 10-yr LRR | 12.0% | 10.3% | HR 1.19 (95% CI 0.79-1.82) |
| Late G1-2 pulmonary fibrosis | 19.7% | 11.7% | p=0.008 |
No G4-5 late toxicity and no brachial plexopathy in either arm. G1-2 pulmonary fibrosis was more frequent with hypofractionation: 19.7% vs 11.7%, p=0.008. Other late endpoints (lymphedema, skin, cardiac) are not reported in the source.
The START trials established moderate hypofractionation mainly for whole-breast RT after breast conservation, with few mastectomy pts and limited nodal irradiation. This trial fills that PMRT plus supraclavicular gap with long follow-up. DBCG Skagen and HypoG-01 address hypofractionated nodal RT, and RT CHARM and FABREC address the reconstructed chest wall.
The source does not restate the non-inferiority margin, and the 10-yr 95% CI reaches 1.82. Fibrosis ascertainment method is not stated, and grading was unblinded. Accrual ran 2008 to 2016 with RT technique undescribed, so transfer to modern planning is uncertain.
The 10-yr data show no late divergence in locoregional control and no plexus injury after a hypofractionated supraclavicular field. What it leaves open is whether the low-grade fibrosis excess is specific to this schedule and era, and whether the result holds with IMN coverage or reconstruction.
Randomized phase 3 with non-inferiority already shown at 5 yr per source; 10-yr read is descriptive, single-center, open-label. Aligns with the field's adoption of hypofractionated PMRT.
- Does hypofractionated PMRT hold with IMN-inclusive regional nodal fields? recruiting Conventionally Fractionated vs. Hypofractionated Comprehensive Nodal Irradiation for Breast Cancer Using Pencil Beam Scanning Proton Therapy Phase 3n=276 · primary completion 2038-02 · phase 3 hypo vs conv proton RNI, IMN in target volume
- Safety of hypofractionated PMRT with breast reconstruction n=506 · primary completion 2029-03 · phase 3 43.5 Gy/15fx vs 50 Gy/25fx after implant reconrecruiting Hypofractionated vs. Conventionally Fractionated Postmastectomy Radiotherapy After Implant-Based Reconstruction Phase NAn=534 · primary completion 2033-10 · randomized NI, 1° EP unplanned reoperation, implant recon
- Is the G1-2 pulmonary fibrosis excess clinically relevant with modern planning?
📚 Sources · 📄 1 paper
Abstract
NRG/RTOG 0815 Decipher GC
ForIntermediate-risk prostate cancer, dose-escalated RT, biopsy Decipher GC available
p-interaction <0.001
10-yr DM absolute benefit 11% high GC vs 1% low GC
TL;DR10-yr DM absolute benefit from adding STAD to dose-escalated RT: 11% in high GC vs 1% in low GC, p-interaction <0.001.
The omission read is the low-GC group: 44% of the cohort had GC <0.45 and a 10-yr DM absolute difference of 1% with STAD. The slide pools int/high GC at 8% while the abstract gives 11% for high GC alone, so where GC 0.45-0.6 falls is not resolved in source. RT dose and fractionation are not stated.
In intermediate-risk prostate cancer planned for dose-escalated RT, a low Decipher GC (<0.45) supports discussing STAD omission and a GC >0.6 argues against it; it does not settle the GC 0.45-0.6 group or pts outside intermediate-risk disease. The longer read
The omission read is the low-GC group: 44% of the cohort had GC <0.45 and a 10-yr DM absolute difference of 1% with STAD added to dose-escalated RT. Slide pools int/high GC at 8% vs 11% for high GC alone in the abstract, so GC 0.45-0.6 stays unresolved. RT dose and fractionation not stated in source.
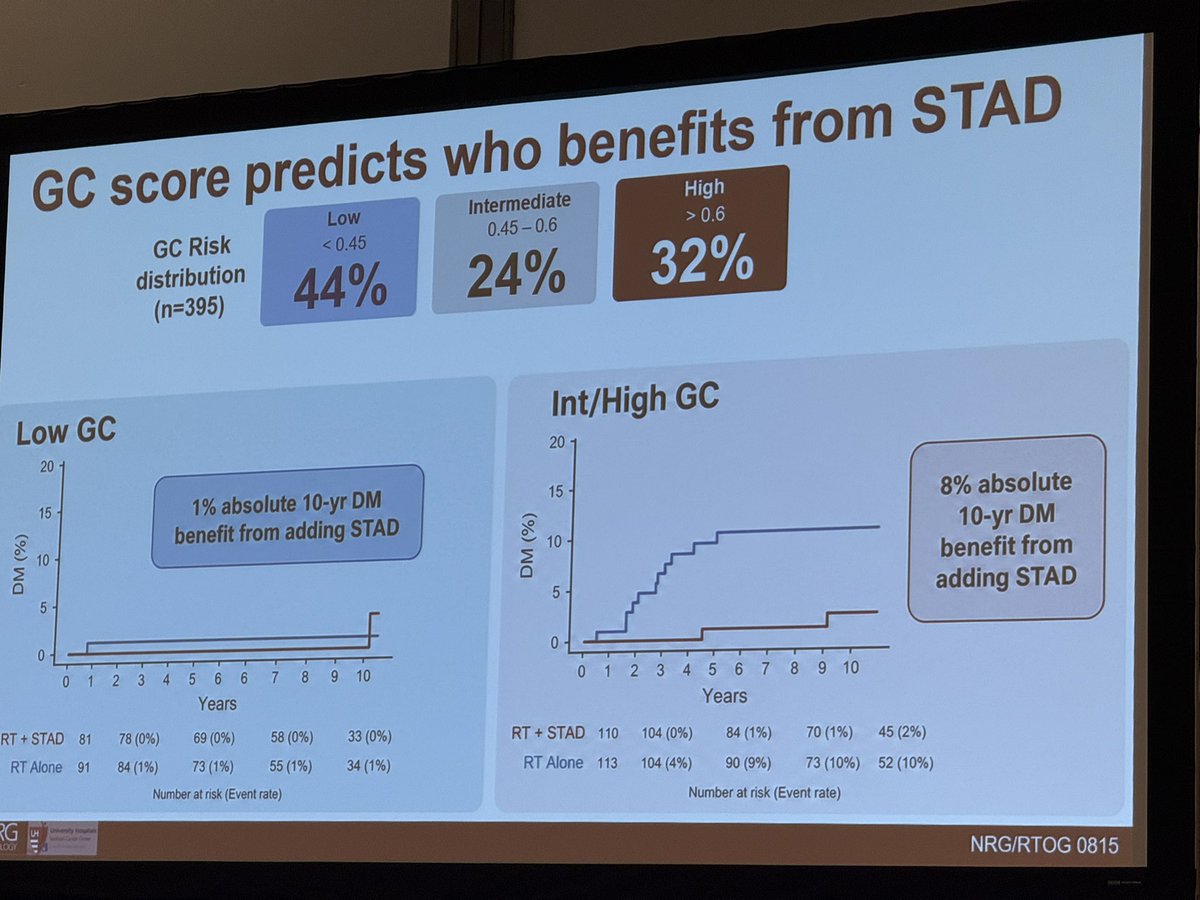
| GC group | Absolute 10-yr DM benefit from adding STAD |
|---|---|
| Int/High GC | 8% |
| Low GC | 1% |
+1 more figure
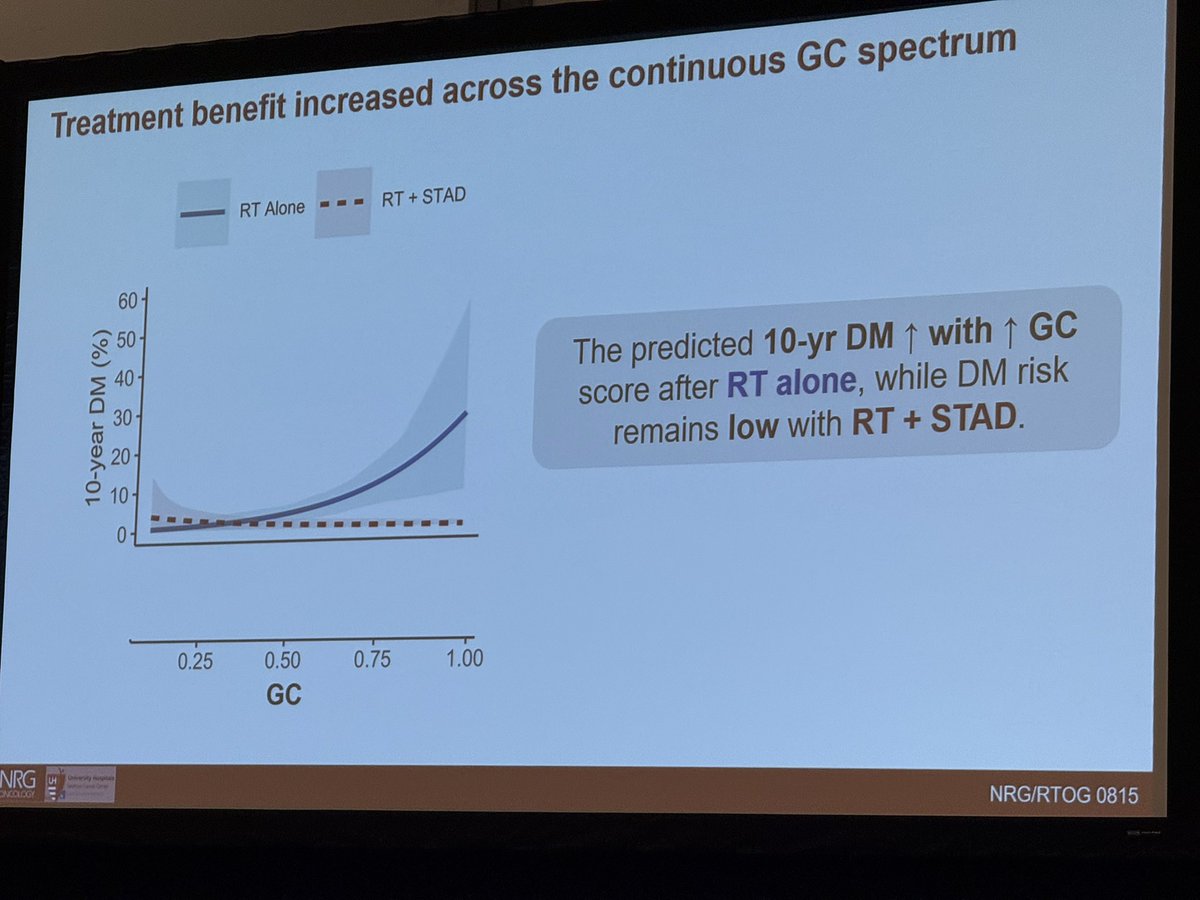
12 details 2 trials watching
Ancillary study of NRG/RTOG 0815, a phase 3 randomized trial of dose-escalated RT with or without 6 months of STAD. Prespecified analysis plan with NCI approval, GC data linked to updated outcomes at 10.2 years median follow-up (IQR 8.4-11.4).
Intermediate-risk prostate cancer. GC scores were obtained for 395 pts of 856 with available tissue, with baseline characteristics balanced between arms. GC distribution: low (<0.45) 44%, intermediate (0.45-0.6) 24%, high (>0.6) 32%.
6 months of STAD added to dose-escalated RT vs RT alone. Agents not stated in source.
Dose-escalated RT in both arms. Dose, fractionation, modality mix and target volume are not stated in source, though RT modality was a covariate in the multivariable models.
Primary: distant metastasis. Secondary: biochemical failure, MFS, PCSM, OS. Cox and Fine-Gray competing risk MVA adjusted for age, race, clinical risk factors, comorbidity score and RT modality.
GC-STAD interaction for DM p<0.001 and for PCSM p-interaction <0.001. 10-yr DM absolute difference 1% in low GC vs absolute benefit 11% in high GC. Slide 2 shows predicted 10-yr DM rising with GC score after RT alone and staying low with RT + STAD.
| Endpoint | sHR (95% CI) | p |
|---|---|---|
| Biochemical failure | 2.19 (1.36-3.53) | <0.001 |
| Distant metastasis | 4.89 (0.98-24.3) | 0.05 |
The parent NRG/RTOG 0815 trial set the question of STAD with dose-escalated RT for intermediate-risk disease as a whole. Decipher has prior ancillary validation in NRG/RTOG 0126 and 9601. This analysis adds a treatment interaction inside a trial that randomized the therapy in question.
The slide and the abstract cut the cohort differently (int/high GC pooled at 8% vs high GC at 11%), leaving the GC 0.45-0.6 group unresolved. The prognostic DM estimate has a CI of 0.98-24.3. No favorable vs unfavorable intermediate-risk breakdown in source.
The predictive claim is for DM and PCSM, not OS or MFS, for which no interaction is reported in source. The low-GC finding is the clinically usable half, since it identifies a large group with no clear benefit from intensification. The authors themselves defer to NRG GU010 for prospective validation.
Ancillary biomarker analysis in the 395 pts with GC scores; interaction rests on 16 DM and 7 PCSM events. Prespecified plan, but prospective validation (NRG GU010) pending.
- Does GC-guided STAD omission hold prospectively in NRG GU010? n=2050 · primary completion 2026-11 · phase 3 Decipher-guided de-intensification in UIRn=222 · primary completion 2027-12 · phase 2 SBRT without ADT in UIR, Decipher-guided
- STAD benefit in intermediate GC (0.45-0.6) reported on its own?
- Does the interaction hold within favorable vs unfavorable intermediate-risk disease?
📚 Sources · 🐦 1 tweet · 📄 1 paper
🚨Decipher score predictive of ADT benefit for preventing metastasis in patients with intermediate-risk #ProstateCancer in secondary analysis of @NRGonc RTOG 0815 RCT@angela_jia_ @ASTRO_org #ASTRO26 pic.twitter.com/YokjDQVxKa
— Tyler Seibert MD PhD (@TylerSbrt) September 29, 2026
Abstract
NRG/RTOG 0534 PAM50
ForPost-RP salvage RT, PSA 0.1-2.0 ng/mL, pT2 or pT3 N0M0, Gleason ≤9
TL;DR5-y FFP benefit from adding ADT to post-RP salvage RT was 31% vs 10% by PAM50 Luminal B status (p-int=.01), secondary biomarker analysis.
The decision in play is ADT with salvage RT, not target volume. The FFP interaction (P=0.01) rests on pooled STADT arms vs PBRT alone, HR 0.34 (0.23-0.52) in one subtype panel. In the three-arm slide, Arm 3 vs 2 reads HR 0.64 (0.34-1.20), p=0.16, so what PLNRT adds within subtype is unresolved.
In men post-RP with PSA 0.1-2.0 ng/mL and pT2 or pT3 N0M0 disease heading to salvage RT, PAM50 Luminal B status supports the case for adding STADT; it does not establish that non-Luminal B men can omit ADT. The longer read
The decision in play is ADT with salvage RT, not target volume. The FFP interaction (P=0.01) rests on pooled STADT arms vs PBRT alone, HR 0.34 (0.23-0.52) in one subtype panel. In the three-arm slide, Arm 3 vs 2 reads HR 0.64 (0.34-1.20), p=0.16, so what PLNRT adds within subtype is unresolved.
For the ADT decision, PAM50 Luminal B is offered as a selection marker: 5-y FFP benefit 31% vs 10% (p-int=.01), with a weaker 10-y MFS interaction (p-int=.05). STADT duration and agent are not reported in source, and the non-Luminal B estimate is too imprecise to support omission.
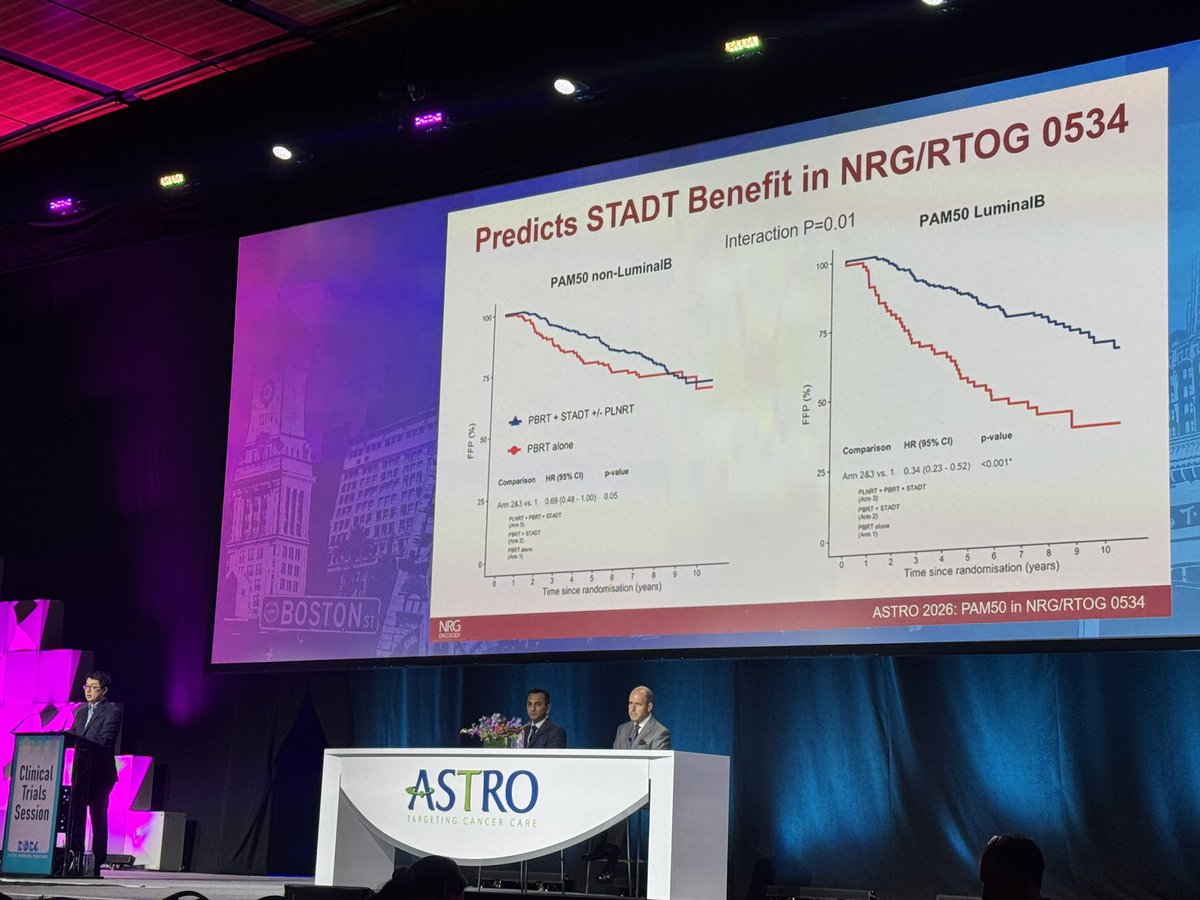
+2 more figures
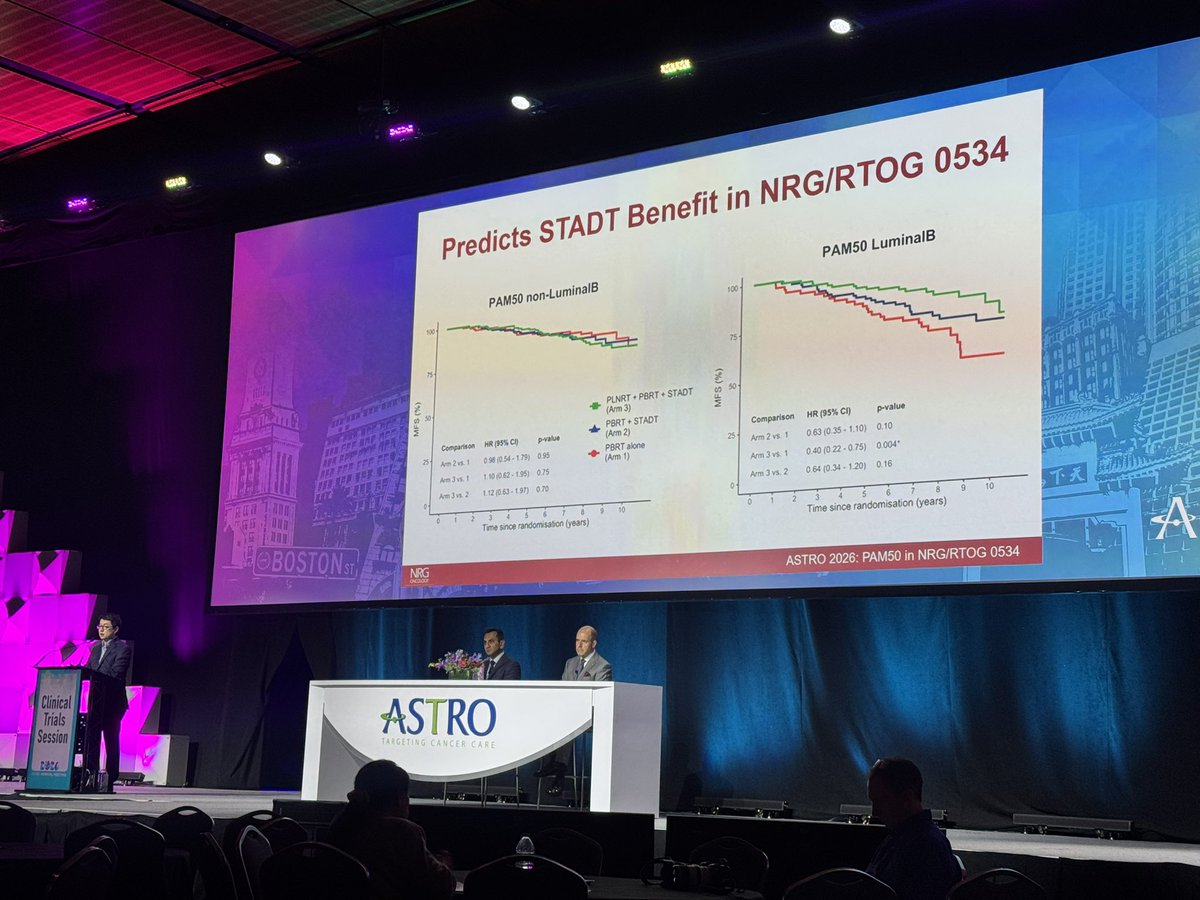
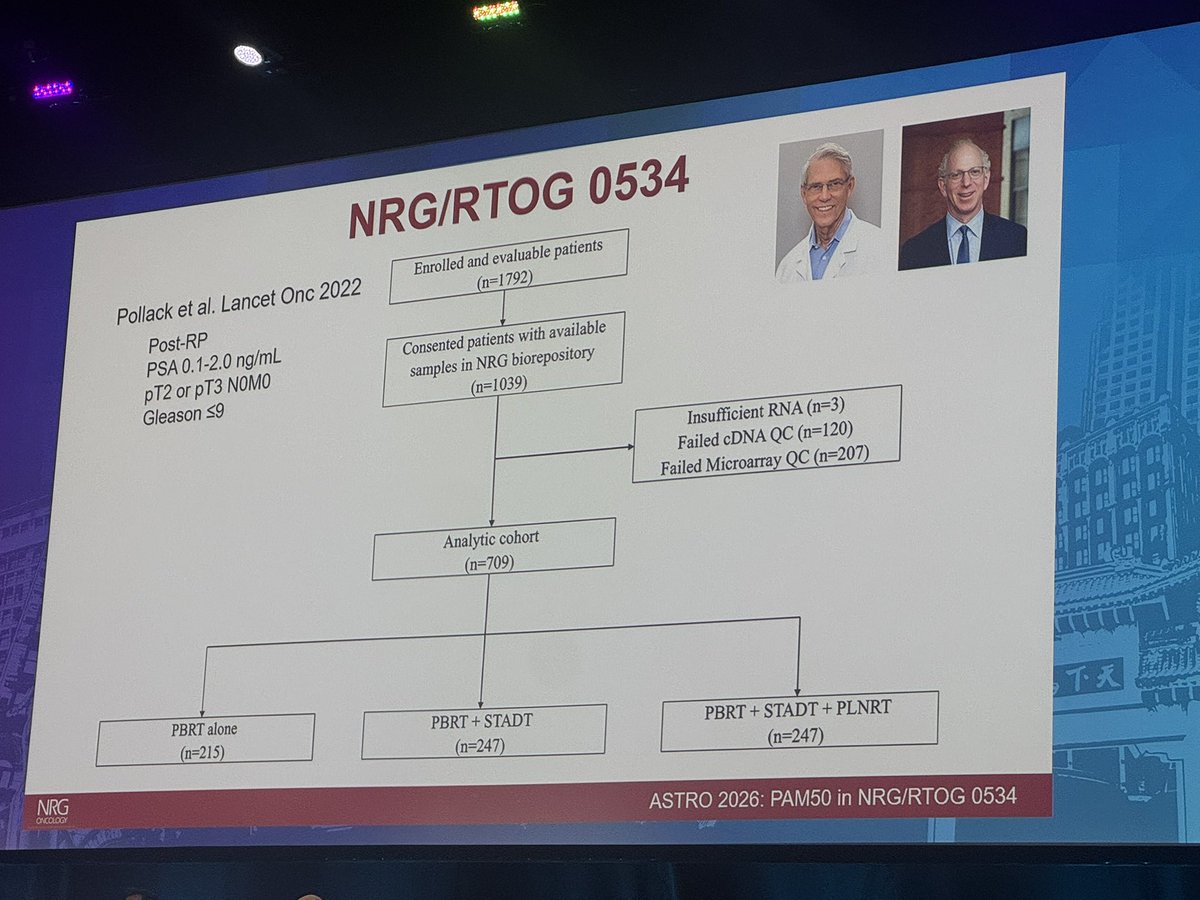
10 details
PAM50 molecular subtyping on biorepository tissue from NRG/RTOG 0534, a three-arm randomised trial of post-prostatectomy salvage RT. Analytic cohort n=709 from 1792 enrolled and evaluable. Phase, prespecification of this analysis and median follow-up are not stated in source.
Parent trial eligibility per slide: post-RP, PSA 0.1-2.0 ng/mL, pT2 or pT3 N0M0, Gleason ≤9. Of 1039 consented pts with samples, 3 had insufficient RNA, 120 failed cDNA QC and 207 failed microarray QC.
Arm 1 PBRT alone (n=215), Arm 2 PBRT + STADT (n=247), Arm 3 PBRT + STADT + PLNRT (n=247). Dose, fractionation, pelvic nodal volume and STADT duration are not reported in source tweets.
Reported: FFP at 5 y and MFS at 10 y, each tested for subtype-by-treatment interaction. The primary endpoint of this biomarker analysis is not stated in source.
Tweet: 5-y FFP benefit from postop ADT 31% vs 10% (p-int=.01) and 10-y MFS 20% vs -3% (p-int=.05). FFP slide: pooled STADT arms vs PBRT alone HR 0.34 (0.23-0.52), p<0.001 in one subtype panel; the other panel's HR is garbled in OCR with CI 0.43-1.00.
The parent trial (Pollack et al, Lancet Onc 2022) is the slide's stated reference for the unselected result. GETUG-AFU 16 and RADICALS-HD tested ADT with post-RP RT without molecular selection, and NRG GU006 used PAM50 subtype prospectively with salvage RT; none of their figures appear in source.
Subtype panel labels and one HR are not legible in OCR, so effect sizes by subtype rest partly on the tweet's framing. The MFS interaction sits at p-int=.05. No multiplicity handling, event counts or Luminal B prevalence in source.
A treatment-by-subtype interaction on FFP is the claim that would let PAM50 select for ADT; a prognostic signal alone would not. The MFS interaction is weaker and the three-arm comparisons are underpowered within subtype, so this reads as support for biomarker-directed ADT rather than a rule for omission.
Biomarker subset analysis of a completed randomised trial, prespecification not stated; analytic cohort is a tissue- and QC-selected fraction. Interaction on MFS is borderline.
- Does PAM50 Luminal B predict ADT benefit independent of entry PSA and grade?
- Can non-Luminal B men omit ADT with salvage RT?
- Does pelvic nodal RT benefit differ by PAM50 subtype?
📚 Sources · 🐦 1 tweet
New #ASTRO2026 data from @NRGOnc /RTOG 0534 SPPORT 🔬🧬 presented by Shuang (George) Zhao @UTMDAnderson. PAM50 Luminal B = both prognostic & predictive of benefit from postop ADT.
— Lauren Henke, MD, MSCI (@lauren_henke) September 27, 2026
📈 5-y FFP benefit: 31% vs 10% (p-int=.01)
🎯 10-y MFS: 20% vs -3% (p-int=.05)#Pcsm @Astro_org pic.twitter.com/BRJsYDWiQS
GETUG P05 NCT02271659
ForIntermediate-risk prostate cancer, no ADT, IPSS ≤15, no T3a or nodal disease
87.8% vs 88.8%
brachy boost vs EBRT 80 Gy, p=0.86; primary not met
TL;DR5-yr PSA-PFS 87.8% vs 88.8% (p=0.86): brachy boost no better than 80 Gy EBRT in intermediate-risk prostate cancer without ADT, with more late GU toxicity.
Late GU toxicity is the cost side: any-grade 82.2% vs 63.6% (p=0.0006) and grade 2 34.1% vs 17.9% with brachy boost, for near-identical 5-yr PSA-PFS. The control was 80 Gy at 2 Gy/fraction to prostate only without ADT, so the read applies to conventionally fractionated dose-escalated EBRT; hypofractionated and SBRT comparators were not tested.
In intermediate-risk prostate cancer treated without ADT, this questions adding an LDR or HDR brachytherapy boost to 46 Gy EBRT over dose-escalated 80 Gy EBRT for 5-yr biochemical control; it does not extend to T3a, node-positive, or ADT-treated pts. The longer read
The boost decision is the read: an LDR 110 Gy or HDR 14 Gy boost after 46 Gy gave the same 5-yr PSA-PFS as EBRT to 80 Gy at 2 Gy/fraction, with late GU toxicity 82.2% vs 63.6% (p=0.0006). Applies to intermediate-risk disease without ADT; hypofractionated and SBRT comparators were not tested.
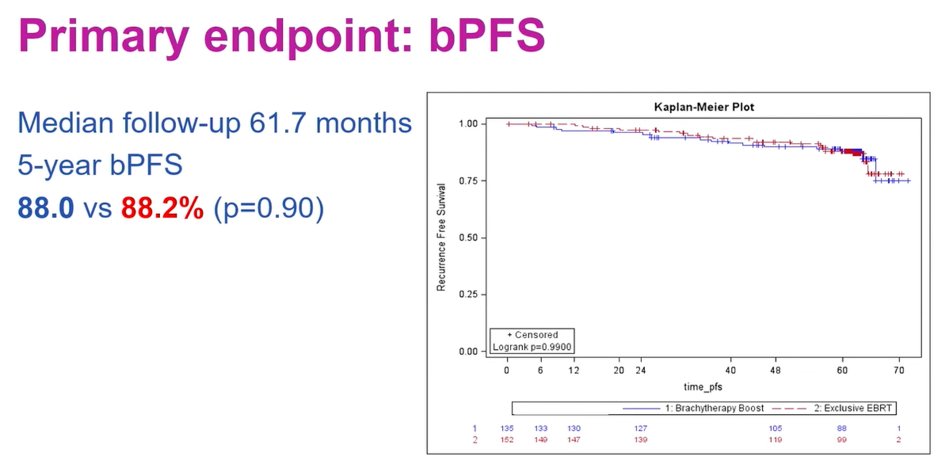
+3 more figures
| Toxicity | Brachytherapy boost | Exclusive EBRT | p |
|---|---|---|---|
| Acute GU, all grades | 79.3% | 79.7% | 0.92 |
| Acute GI, all grades | 29.9% | 41.2% | 0.03 |
| Late global, all grades | 96.3% | 91.4% | 0.02 |
| Late global, grade 3 | 10.4% | 6.6% | n/a |
| Late GU, all grades | 82.2% | 63.6% | 0.0006 |
| Late GU, grade 2 | 34.1% | 17.9% | n/a |
| Late GU, grade 3 | 3.0% | 1.3% | n/a |
| Late GI, all grades | 50.4% | 43.7% | 0.48 |

12 details 2 trials watching
Open-label randomized phase III, 1:1, 298 randomized at 27 centers (16/12/2013 to 20/03/2017), 296 evaluable: 141 brachytherapy boost, 155 EBRT. Median PFS follow-up 61.7 months (55.5-62.8).
Intermediate-risk prostate cancer: PSA 10 to 20 ng/ml and/or Gleason 7 and/or T2b; age 18-80, ECOG PS ≤ 2, expected survival ≥ 10y. Excluded: ADT, T3a, nodal or distant disease, IPSS >15, active inflammatory bowel disease. Median age 69; 60.5% Gleason 3+4, 27% 4+3, 12.5% Gleason 6; mean PSA 8.90.
Both arms: EBRT 46 Gy at 2 Gy/fraction to prostate + first cm of seminal vesicles. Arm A: brachytherapy boost to prostate, I-125 permanent implant 110 Gy or Ir-192 HDR 14 Gy, technique chosen by center (79 LDR, 55 HDR, 7 unknown). Arm B: EBRT boost 34 Gy at 2 Gy/fraction to prostate only, total 80 Gy.
Primary: PSA-PFS at 5 years by Phoenix criteria. Secondary: OS, PCSS, MFS, adverse events, QoL (IPSS, IIEF-5, QLQ-C30). PCSS and MFS results not reported in source.
5-yr PSA-PFS 87.8% vs 88.8% (brachy vs EBRT, p=0.86) on 35 events; 5-yr OS 96.0% vs 92.7% (p=0.30). No benefit in either the 3+4 or 4+3 subgroup, and LDR vs HDR did not influence PSA-PFS.
Abstract: more acute and late urinary toxicity with brachy boost (55% vs 26%, p<0.0001; 82% vs 64%, p=0.0007), mostly grade 1-2 (pollakiuria, dysuria), no difference in grade 3, no grade 4. The slide's acute GU all-grade rates (79.3% vs 79.7%, p=0.92) and its acute GI difference (29.9% vs 41.2%, p=0.03) do not match the abstract text.
ASCENDE-RT is the randomized trial that established a biochemical control advantage for an LDR boost over dose-escalated EBRT, in a higher-risk cohort that all received ADT. GETUG P05 asks the same question in intermediate-risk disease without ADT and finds no PSA-PFS difference.
35 events leaves room for a modest difference either way, and the source states neither the hypothesized effect nor power. Two boost techniques at center discretion make the experimental arm heterogeneous. Toxicity figures differ between the abstract and the presented slide.
For intermediate-risk disease without ADT, 80 Gy EBRT matched a brachytherapy boost on 5-yr biochemical control with less late GU toxicity. It does not settle whether curves separate later, or whether a boost adds value in unfavorable intermediate-risk disease managed with ADT.
Completed randomized phase III with a prespecified primary endpoint, null for brachy boost where prior randomized data favored it. Low event count and internally inconsistent toxicity reporting are secondary caveats.
- Does PSA-PFS diverge with follow-up beyond 5 years?
- Brachy boost value in unfavorable intermediate-risk disease treated with ADT
- Brachy boost vs moderately hypofractionated or SBRT dose escalation recruiting Androgen Suppression Combined With Nodal Irradiation and Dose Escalated Prostate Treatment Phase 3n=710 · primary completion 2032-10 · phase 3 SBRT vs EBRT + brachy boost, unfavourable risk + ADTrecruiting PRO-BOOST-LC: Whole-Gland Boost Strategies Versus SBRT Monotherapy in PSMA-Staged Localized and Locally Advanced Prostate Cancer Phase 2/3n=1000 · primary completion 2033-12 · phase 2/3 HDR/LDR/SBRT boost vs SBRT monotherapy
📚 Sources · 🐦 1 tweet · 📄 1 paper
GETUG P05: Ph 3 RCT of 46 Gy EBRT + LDR/HDR brachy boost vs dose-escalated 80 Gy EBRT in IR PCa, no ADT (n=288)
— Rashid K. Sayyid (@RKSayyid) September 28, 2026
🔹5-yr bPFS: 88% vs 88.2% (p=0.90)
🔹No bPFS benefit in iether GG2 or 3 pts
🔹5-yr OS: 96% vs 92.7% (p=0.30)
🔹Acute GI toxicity lower w/ brachy: 30% vs 41% (p=0.03)… pic.twitter.com/qoxDCnJV4b
Abstract
PROSTOX Ultra (SCIMITAR, EXCALIBUR)
ForPost-prostatectomy prostate cancer, 5-fx SBRT to prostate fossa ± pelvic nodes
TL;DRContinuous AUC 0.814 (SCIMITAR) and 0.824 (EXCALIBUR) for late G2+ GU AEs after post-prostatectomy SBRT; intact-prostate 0.50 cutoff failed, 0.25 recalibrated.
Reported via UroToday →
The cutoff, not the signature, is what breaks post-op: in EXCALIBUR every pt with toxicity scored below 0.50, and the median score with toxicity was 0.338. A result reported against the intact-prostate 0.50 threshold can therefore read low-risk in a man who goes on to late G2+ GU toxicity after 5-fx fossa SBRT.
In men post-prostatectomy weighing 5-fraction SBRT to the prostate bed ± nodes, this questions reading a PROSTOX Ultra score against the intact-prostate 0.50 cutoff; it does not extend to conventionally fractionated post-op RT, which neither cohort tested. The longer read
The cutoff, not the signature, is what breaks post-op: in EXCALIBUR every pt with toxicity scored below 0.50, and the median score with toxicity was 0.338. Read against the intact-prostate threshold, a score can look low-risk before late G2+ GU toxicity after 5-fx fossa SBRT (30-34 Gy in SCIMITAR).
12 details
Biomarker evaluation in two prospective post-op SBRT cohorts (SCIMITAR, EXCALIBUR). Risk scores came from the original intact-prostate model without refitting. Discrimination assessed as continuous AUC and as dichotomized performance at the prespecified 0.50 threshold, then exploratory threshold recalibration; AUCs bootstrapped (1,000 iterations) and pooled by fixed-effects meta-analysis.
Post-prostatectomy pts receiving SBRT to the prostate fossa. SCIMITAR: 100 enrolled, 89 evaluable. EXCALIBUR: 74 evaluable. Adjuvant vs salvage mix, PSA at RT and ADT use not reported in source.
SCIMITAR: 30-34 Gy in 5 fractions to the prostate fossa ± pelvic nodes. EXCALIBUR: 5-fraction SBRT to the prostate bed ± nodes, dose not reported in source. Toxicity by nodal coverage not reported in source.
Outcome: late grade 2+ GU adverse events. Predictor: PROSTOX Ultra score, continuous and dichotomized. Toxicity scale and follow-up duration not reported in source.
Per-cohort discrimination is in the table. Pooled AUC at 0.25 was 0.748. Clinical covariates (age, baseline pad use, IPSS, time from RP to SBRT) were not associated with toxicity (all p>0.2).
| Metric | SCIMITAR | EXCALIBUR |
|---|---|---|
| Continuous AUC | 0.814 | 0.824 |
| Binary AUC at 0.50 (intact cutoff) | 0.755 | <0.50 |
| Specificity at 0.50 | 0.985 | 0.926 |
| Sensitivity at 0.50 | 0.546 | not reported in source |
| Binary AUC at 0.25 (post-op cutoff) | 0.750 | 0.727 |
| Median score, toxicity vs none | 0.547 vs 0.049, p<0.0001 | 0.338 vs 0.043, p=0.009 |
The signature was built and thresholded for late GU AEs after intact-prostate SBRT, where 0.50 was prespecified. Post-op, risk ordering held (continuous AUC 0.814 and 0.824) but the 0.50 cutoff did not transfer: EXCALIBUR binary AUC was <0.50.
Sensitivity and specificity at 0.25 are not reported in the source text, only AUC. EXCALIBUR's event count and both cohorts' follow-up duration are missing, so the stability of the EXCALIBUR estimates cannot be judged. Source is a trade-press account of a talk, not a full report.
The read is a stable germline signal with a downward-shifted trigger after prostatectomy. That supports the biology and leaves the clinical tool unfinished: a cutoff tuned on these cohorts needs an independent post-op set before it gates fractionation or counseling.
Prespecified 0.50 threshold failed in EXCALIBUR; the 0.25 cutoff is exploratory, chosen and scored on the same two cohorts with no external validation.
- Independent prospective validation of the 0.25 post-op threshold
- Does a high score warrant conventional fractionation, lower dose, or smaller volume?
- Does the signature predict late GU toxicity after conventionally fractionated post-op RT?
📚 Sources · 📄 1 paper
Abstract
NRG/RTOG 0815
ForNon-metastatic intermediate-risk prostate cancer, GS 7 in 92%, median age 68
HR 0.87
95% CI 0.72-1.04, p=0.13 (ns); 14-y OS 53% vs 58%
TL;DR14-y OS 53% vs 58% (HR 0.87, p=0.13) adding 6 mo STAD to dose-escalated RT in intermediate-risk prostate cancer; PSA failure HR 0.60.
Dose escalation did not make STAD redundant: local failure still fell (HR 0.44) and the PSA-failure benefit held in single-risk-factor pts (HR 0.66). With 88% treated by EBRT alone to 79.2 Gy, the trial cannot say whether a brachytherapy boost substitutes for ADT. 422 of 446 deaths were non-prostate, which is why OS stayed flat.
In non-metastatic intermediate-risk prostate cancer planned for dose-escalated EBRT, this supports discussing 6 months of STAD as a disease-control gain (PSA failure, distant metastasis, salvage ADT) without a proven OS gain; it does not extend to pts with all 3 risk factors and ≥50% positive cores, who were ineligible. The longer read
Dose escalation did not make STAD redundant: local failure still fell (HR 0.44) and the PSA-failure benefit held in single-risk-factor pts (HR 0.66). With 88% treated by EBRT alone to 79.2 Gy, the trial cannot say whether a brachytherapy boost substitutes for ADT.
Six months of LHRH agonist/antagonist plus antiandrogen roughly halved later salvage ADT (15% vs 7% at 14 y) and cut distant metastasis (40 vs 14 events) without an OS gain. The cost is more grade ≥3 cardiac (26 vs 10) and metabolic (20 vs 4) events, though non-prostate mortality was not higher (HR 0.93).
| Arm | 10-yr OS | 14-yr OS | HR (95% CI) | p |
|---|---|---|---|---|
| RT Alone | 70% | 53% | Referent | n/a |
| RT + STAD | 74% | 58% | 0.87 (0.72, 1.04) | 0.13 |
+3 more figures
| Arm | 10-yr PSA failure | 14-yr PSA failure | HR (95% CI) | p |
|---|---|---|---|---|
| RT Alone | 25% | 34% | Referent | n/a |
| RT + STAD | 16% | 19% | 0.60 (0.48, 0.76) | < 0.001 |

10 details
Phase III prospective randomized trial, accrued 1538 pts 2009-2016, 1493 eligible for analysis (751 RT alone, 742 RT + STAD). Stratified by number of risk factors (1 vs 2-3), ACE-27 (≥2 vs <2), and RT modality. Median follow-up 9.4 years (10.3 years in survivors).
Non-metastatic intermediate-risk prostate cancer with ≥1 of: clinical stage T2b-T2c, Gleason score 7, PSA >10 but ≤20 ng/mL. Ineligible: all 3 risk factors with ≥50% positive cores. Median age 68, 67% single risk factor, 92% Gleason 7, median PSA 8.1 ng/mL, 67% ACE-27 <2.
STAD: LHRH agonist/antagonist plus oral antiandrogen for 6 months, added to dose-escalated RT. Protocol-compliant or acceptable variation in 91% for the LHRH component and 87% for the antiandrogen.
Physician's choice of EBRT alone to 79.2 Gy or EBRT 45 Gy plus LDR or HDR brachytherapy boost. EBRT alone in 88% (abstract) to 89% (slide). Over 90% of RT plans scored per protocol or variation acceptable for contours and dose.
Primary: overall survival, powered to detect 5-year OS 90% to 93% (HR 0.66) with 85% power. Secondary: biochemical failure, local failure, distant metastasis, prostate cancer death, initiation of salvage therapy, non-prostate cancer death.
Primary OS not met (HR 0.87, p=0.13). Every disease-control secondary favored STAD, including local failure HR 0.44 (per-arm local failure rates not reported in source).
| Endpoint | RT + STAD | RT alone | Effect size |
|---|---|---|---|
| MFS, 10-y | 72% | 67% | n/a |
| MFS, 14-y | 57% | 50% | HR 0.83 (0.69-0.99), p=0.042 |
| Distant metastasis, events | 14 | 40 | HR 0.35 (0.19-0.64), p<0.001 |
| Prostate cancer deaths | 5 | 19 | HR 0.26 (0.10-0.70), p=0.004 |
| PCSM, 10-y | 0.4% | 2.7% | n/a |
| PCSM, 14-y | 2.1% | 3.3% | n/a |
| Salvage ADT, 10-y | 7% | 13% | n/a |
| Salvage ADT, 14-y | 7% | 15% | HR 0.53 (0.38-0.75), p<0.001 |
| Non-prostate cancer deaths | 202 | 220 | HR 0.93 (0.77-1.13) |
Overall late grade ≥3 AEs did not differ (HR 1.08, 95% CI 0.84-1.40). With STAD: grade ≥3 metabolic/lab 20 vs 4, grade 3 sexual function 71 vs 38, grade ≥3 cardiac 26 vs 10 (each p<0.01). EPIC hormone and sexual domains dropped early with STAD and largely converged by 60 months; urinary and bowel domains were similar.
The case for short-term ADT in intermediate-risk disease was built by RTOG 9408 and the D'Amico Dana-Farber trial with conventional-dose RT, leaving open whether dose escalation would erase the benefit. This trial tests that directly and finds the disease-control benefit persists with dose-escalated RT, in line with EORTC 22991.
Disease-control gains are secondary endpoints, and the source states no multiplicity adjustment. MFS (p=0.042) is driven mostly by deaths, with only 40 vs 14 distant metastasis events. Brachytherapy-boost strata are small, and subgroup HRs for OS and MFS are not reported in source.
STAD buys fewer PSA failures, fewer metastases, less salvage ADT and fewer prostate cancer deaths, not a demonstrated survival gain, in a cohort where 422 of 446 deaths were non-prostate. The investigators could not identify a subgroup without benefit for PSA failure and distant metastasis, so omission still rests on competing risk and toxicity tolerance rather than trial-defined selection.
CONSORT flow
Completed phase III with mature f/u; primary OS not met, but durable secondary disease-control gains align with existing STAD use. Powered for HR 0.66, so a smaller OS effect is unresolved.
- Does a brachytherapy boost remove the need for STAD in intermediate-risk disease?
- Can genomic classifiers or MMAI select intermediate-risk pts who can omit STAD?
📚 Sources · 🐦 1 tweet · 📄 2 papers
NRG/RTOG 0815: Ph 3 RCT of dose-escalated RT ± 6 mo STAD in IR PCa (n=1493; median f/u 10.3 y)
— Rashid K. Sayyid (@RKSayyid) September 28, 2026
🚨OS: 10-y 70% (RT alone) vs 74% (RT+STAD); 14-y 53% vs 58% (HR 0.87; p=0.13)
🔹PSA failure: 25% vs 16% at 10 y; 34% vs 19% at 14 y (HR 0.60; p<0.001)
🔹MFS: 67% vs 72% at 10 y; 50%… pic.twitter.com/G5qfgfc9CI
Abstract
Abstract
Biomarkers in Post-operative Prostate Cancer (Spratt)
TL;DR5y MFS 95% vs 82% (HR 0.27) with apalutamide + salvage RT in PAM50 luminal B, flat in non-luminal B (NRG GU006).
Reported via UroToday →
MARCAPPOSEIDONRTOG 9601RTOG 0534NRG GU002NRG GU006BALANCESYMPHONY
Pre-RT PSA, not pathology, sorted hormone therapy benefit in POSEIDON: OS HR 1.14 at PSA ≤0.20 ng/mL vs 0.72 at 0.51-1.0 and 0.69 above 1.0, while adverse feature count showed no interaction (p = 0.40). That weakens GG4-5 or SVI alone as the reason to add ADT to early salvage RT.
In post-RP men with PSA 0.1-1.0 ng/mL and N0M0 disease, a PAM50 luminal B result supports considering systemic intensification with salvage RT; non-luminal B showed no bPFS or MFS separation, and none of this extends to N+/M+ recurrence. The longer read
Pre-RT PSA, not pathology, sorted hormone therapy benefit in POSEIDON: OS HR 1.14 at PSA ≤0.20 ng/mL vs 0.72 at 0.51-1.0 and 0.69 above 1.0, while adverse feature count showed no interaction (p = 0.40). That weakens GG4-5 or SVI alone as the reason to add ADT to early salvage RT.
The systemic read is agent and duration: 24 months of ADT did not beat 4-6 months for OS (HR 0.96), and NRG GU006 tested 6 months of apalutamide, not ADT. Luminal B selected for benefit (5-year MFS 95% vs 82%); non-luminal B did not (90% vs 89%).
14 details 3 trials watching
Trade-press write-up of a single ASTRO 2026 talk (Spratt) covering the POSEIDON IPD meta-analysis (6 randomized trials, 6,057 pts, median f/u 9.0 years), an adverse-feature IPD meta-analysis, NRG GU006 (BALANCE), retrospective PAM50 work in RTOG 0534, and an MMAI digital pathology biomarker in NRG/RTOG 9601 and 0534.
NRG GU006: post-radical prostatectomy, PSA 0.1-1.0 ng/mL, N0M0, PAM50 subtyped before randomization. RTOG 0534: post-radical prostatectomy, PSA 0.1-2.0 ng/mL, N0M0.
GU006: blinded 1:1 randomization to salvage RT + 6 months of apalutamide vs RT + 6 months of placebo. RTOG 0534 arms included RT alone and RT with 6 months of ADT. POSEIDON compared short-term ADT of 4-6 months with long-term ADT of 24 months.
RT dose, fractionation and target volume for the reported trials are not stated in source. The planned SYMPHONY program tests the RT questions directly: 5-fraction vs conventional 20-33 fraction prostate bed SBRT, reduced vs normal dose, and added elective nodal RT.
Effect sizes are in the tables above. The pattern across datasets: hormone therapy benefit tracks pre-RT PSA above 0.50 ng/mL and PAM50 luminal B, and does not track adverse pathologic feature count.
| Pre-RT PSA (ng/mL) | OS HR (95% CI) | p |
|---|---|---|
| ≤0.20 | 1.14 (0.83-1.57) | 0.42 |
| 0.21-0.50 | 0.94 (0.74-1.19) | 0.70 |
| 0.51-1.0 | 0.72 (0.54-0.96) | 0.02 |
| >1.0 | 0.69 (0.48-0.98) | 0.03 |
| Endpoint | Luminal B: apalutamide vs placebo | Luminal B HR | Non-luminal B: apalutamide vs placebo | Non-luminal B HR |
|---|---|---|---|---|
| 5-year bPFS | 72% vs 54% | 0.45 (95% CI 0.24-0.86; p = 0.0062) | 70% vs 71% | 0.95 (80% CI 0.65-1.41; p = 0.44) |
| 5-year MFS | 95% vs 82% | 0.27 (95% CI 0.07-0.95; p = 0.029) | 90% vs 89% | 1.06 (95% CI 0.41-2.78; p = 0.90) |
| Sub-study | Question | Planned per arm | Planned overall |
|---|---|---|---|
| SYMPHONY-PRESTO | Prostate bed SBRT: conventional 20-33 fraction vs 5-fraction | 474 | 948 |
| SYMPHONY-ADAGIO | Normal-dose vs reduced dose RT | 474 | 948 |
| SYMPHONY-CRESCENDO | Prostate bed RT alone vs added elective nodal RT | 435 | 870 |
| SYMPHONY-FULL-SCORE | MDT vs added prostate-bed/nodal treatment in N+/M+ | 240 | 480 |
The talk frames PAM50 against Decipher, which the speaker's figure places at Simon level 1B via prospective-retrospective validation in randomized cohorts including RTOG 9601 and RTOG 0534. PAM50 is presented as a step past that, a level 1A predictive biomarker, because NRG GU006 stratified on it prospectively.
The RTOG 0534 PAM50 analysis is post-hoc and only one of three luminal B comparisons reached p = 0.004; the other two were p=0.10 and p = 0.16. MMAI figures are approximate curve reads. The write-up does not say how N0M0 was staged.
The case for intensification in luminal B is better supported than the case for omission in non-luminal B: the non-luminal B MFS estimate (HR 1.06, 95% CI 0.41-2.78) cannot exclude either benefit or harm. GU006 tested apalutamide, so it does not by itself answer whether PAM50 selects for ADT.
- Does PAM50 luminal B predict benefit from ADT, not only apalutamide, with salvage RT?
- Can non-luminal B pts safely omit systemic therapy with salvage RT?
- Does 5-fraction prostate bed SBRT match conventional fractionation after prostatectomy? recruiting Post-prostatectomy Radiation Therapy--Moderate Versus Ultra-hypofractionated (Also Known as Stereotactic Body Radiation Therapy [SBRT]) Phase 2n=136 · primary completion 2026-11 · randomized ultra- vs moderate hypofx post-RP, 2y QoLrecruiting Salvage Stereotactic Body Radiotherapy of the Prostate Bed for Biochemical Recurrence After Radical Prostatectomy. Phase NAn=284 · primary completion 2029-02 · randomized phase II/III salvage SBRT vs SOC RTn=206 · primary completion 2031-09 · phase 3: 5-fx bed SBRT vs mild hypofx, QoL non-inferiority
📚 Sources · 📄 1 paper
Abstract
REVELUTION (relugolix vs leuprolide + RT, PROs)
ForLocalized intermediate/high-risk prostate cancer, RT + ADT, ADT-naive
TL;DRAt 12 mo, relugolix vs leuprolide with RT: IPSS 5.66 vs 9.22 (p=0.039), EPIC-CP total 12.25 vs 17.25 (p=0.02); post hoc.
The PRO gap tracks with faster testosterone recovery on relugolix (mean 199.7 vs 142.0 ng/dL at 12 mo, P=.010), which plausibly explains better urinary and EPIC-CP total scores. For RT + short-course ADT, that recovery kinetic is the relevant variable when choosing GnRH agent; whether it costs anything in biochemical control is untested here.
In an ADT-naive man with localized intermediate- or high-risk prostate cancer starting RT + ADT, this offers hypothesis-level support for relugolix on 12-mo urinary and overall PRO burden; it says nothing about biochemical or oncologic control.
In RT + ADT for localized intermediate/high-risk disease, relugolix was linked to lower IPSS (5.66 vs 9.22) and EPIC-CP total (12.25 vs 17.25) at 12 mo, with higher mean testosterone. That informs agent choice when RT-related urinary and bowel symptoms are the concern, pending oncologic data.
Mean testosterone at 12 mo was higher on relugolix (199.7 vs 142.0 ng/dL), consistent with faster recovery after an oral antagonist. The PRO benefit may reflect that recovery; disease control with relugolix in this curative RT setting is not addressed by this analysis.
Also covered Jun 16
+2 more figures
| Arm | Mean testosterone at 12 MONTHS (ng/dL) | P |
|---|---|---|
| Relugolix | 199.7 | .010 |
| Leuprolide | 142.0 | .010 |

9 details 1 trial watching
Post hoc QoL analysis of a 1:1 randomized trial, N=65. Parent trial primary: 12-month change in total coronary plaque volume by coronary CT angiography.
Localized intermediate- or high-risk prostate cancer, receiving RT + ADT, no prior ADT.
Relugolix oral daily vs leuprolide injection every 3 months, each with RT.
Relugolix favored on IPSS and EPIC-CP total at 12 mo; incontinence, irritation, sexual and SHIM did not differ (all P≥.15). Mean testosterone at 12 mo 199.7 vs 142.0 ng/dL (P=.010), higher on relugolix.
| Endpoint | Relugolix + RT | Leuprolide + RT | p |
|---|---|---|---|
| IPSS | 5.66 | 9.22 | 0.039 |
| EPIC-CP total | 12.25 | 17.25 | 0.02 |
HERO compared relugolix with leuprolide in advanced prostate cancer; this analysis extends the comparison to the curative RT setting, but only on PROs and testosterone, not disease control.
Open route difference (oral vs injection) could bias self-reported outcomes. Whether pts were still on ADT at 12 mo is not stated, so the testosterone and PRO gaps may reflect recovery timing rather than on-treatment tolerability.
The urinary and global PRO advantage aligns with faster testosterone recovery on relugolix. Whether that recovery trades against biochemical control after RT is the unanswered question.
Post hoc QoL analysis of a trial powered for coronary plaque, N=65; PRO differences not a prespecified endpoint and route of administration unblinded.
- Does faster testosterone recovery on relugolix affect biochemical control after RT?
- Do PRO differences hold in a prespecified, larger trial? n=110 · primary completion 2027-07 · relugolix vs leuprolide, 6 mo ADT, QoL as stated aim
📚 Sources · 🐦 1 tweet
Relugolix vs Leuprolide + RT for Localized PCa: PROs in the REVELUTION RCT @urotoday #ASTRO26
— Zach Klaassen (@zklaassen_md) September 30, 2026
Relugolix vs Leuprolide:
📌T @ 12 mos: 199.7 vs 142.0 ng/dL; p=0.01
📌@ 12 mos:
- ⬇️ IPSS (5.66 vs 9.22; p=0.039)
- ⬇️ EPIC-CP total (12.25 vs 17.25; p=0.02)
- ⬇️ EPIC-CP bowel… pic.twitter.com/Ek2xLZsl3u
RTOG 3506 (STEEL)
ForPost-RP BCR with ≥1 high-risk feature, receiving SRT + 24mo ADT
HR 0.62
80% CI 0.42-0.91, one-sided p=0.052
TL;DRPFS HR 0.62 (80% CI 0.42-0.91, one-sided p=0.052) adding enzalutamide to SRT + 24mo ADT in high-risk post-RP BCR; BF at 2y 11% vs 19%.
Both arms received SRT + 24 months GnRHa, so the trial isolates ARSI intensification, not the RT contribution; SRT dose and field are not reported in source. BF at 2y dropped 19% to 11%, but Gr 3-4 lymphopenia rose 15% vs 5%, worth weighing if pelvic nodal fields are in the plan.
In post-RP BCR with Gleason 8-10, SVI, pN1, persistent PSA or PSA ≥0.7 already planned for SRT + 24 months ADT, this supports discussing enzalutamide as investigational intensification; it does not extend to lower-risk BCR or shorter ADT courses.
RT was fixed across arms, so this informs what to pair with SRT, not dose or field; technique is not reported in source. BF at 2y 11% vs 19% suggests the SRT + 24mo ADT backbone still leaves room for intensification in high-risk BCR.
Enzalutamide 160 mg on top of 24 months GnRHa cut PFS hazard (HR 0.62, 80% CI 0.42-0.91) in a screening design. Gr 3-4 lymphopenia 15% vs 5% and hypertension 8% vs 5% are the toxicity trade to weigh pending phase III.

| Arm | PFS HR (80% CI) | p |
|---|---|---|
| SRT+ENH ADT | 0.62 (0.42, 0.91) | one-sided p=0.052 |
| SRT+STD ADT | Referent | n/a |
+2 more figures
| AE (all grades) | SRT + enhanced AR suppression (N=89) | SRT + standard ADT (N=98) |
|---|---|---|
| Lymphocyte count decreased | 19 (21%) | 11 (11%) |
| Hot flashes | 72 (81%) | 69 (70%) |
| WBC decreased | 15 (17%) | 8 (8%) |
| Anemia | 23 (26%) | 11 (11%) |
| Diarrhea | 44 (49%) | 57 (58%) |
| Urinary incontinence | 15 (17%) | 24 (24%) |
| Hyperglycemia | 11 (12%) | 3 (3%) |
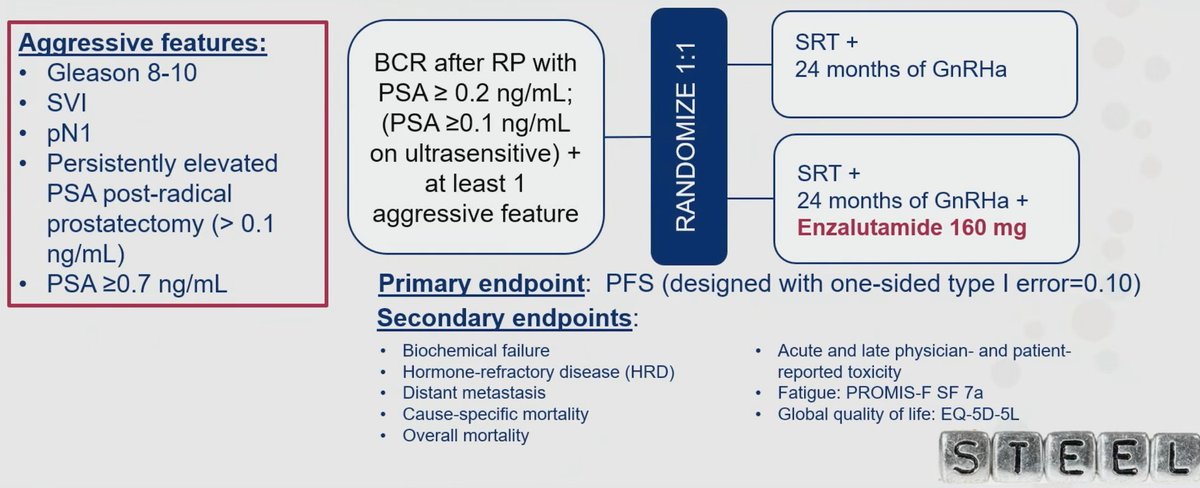
8 details
Randomized phase II, 1:1, n=188, final results. Median follow-up 33.1 mos. Designed with a one-sided type I error of 0.10.
BCR after RP with PSA ≥0.2 ng/mL (or ≥0.1 ng/mL ultrasensitive) plus ≥1 aggressive feature: Gleason 8-10, SVI, pN1, persistently elevated post-RP PSA >0.1 ng/mL, or PSA ≥0.7 ng/mL.
Control: 24 months GnRHa. Experimental: 24 months GnRHa + enzalutamide 160 mg.
Salvage RT in both arms. Dose, fractionation and target volume (prostate bed vs pelvic nodes) are not reported in source.
Primary: PFS. Secondary: biochemical failure, hormone-refractory disease, distant metastasis, cause-specific and overall mortality, physician- and patient-reported toxicity, fatigue (PROMIS-F SF 7a), global QoL (EQ-5D-5L).
PFS HR 0.62 (80% CI 0.42-0.91), one-sided p=0.052. BF at 2 yrs 11% vs 19%.
More Gr 3-4 lymphopenia with enza, 13 (15%) vs 5 (5%), and Gr 3-4 hypertension 7 (8%) vs 5 (5%). All-grade hot flashes 81% vs 70%.
RTOG 9601, GETUG-AFU 16 and SPPORT established adding ADT to SRT; STEEL asks the next question, whether an ARSI on top of long-course ADT adds further. EMBARK tested enzalutamide in high-risk BCR without RT, a different setting.
SRT technique not reported, so RT transferability can't be judged. PFS definition and blinding not stated in source. The 24-month ADT control is itself intensified relative to many current practices.
The signal clears the trial's own screening threshold, but no OS or metastasis data in source, so the cost in lymphopenia and hypertension is set against a surrogate benefit only. The question is now phase III-ready, not practice-ready.
Randomized phase II screening design: one-sided α 0.10, 80% CI, surrogate PFS endpoint, 33mo median f/u. Needs phase III confirmation before ARSI intensification with SRT.
- Does PFS gain translate to MFS or OS?
- Phase III confirmation of ARSI intensification with salvage RT
- Role of pelvic nodal RT alongside enhanced AR suppression
📚 Sources · 🐦 1 tweet
Final Results from RTOG 3506 (STEEL): Randomized Ph II -- 24 mos of Enza + ADT vs ADT in HR Pts with BCR Undergoing Salvage RT @EdwinPosadasMD @urotoday #ASTRO26
— Zach Klaassen (@zklaassen_md) September 29, 2026
📌n=188, mFU 33.1 mos
📌Enza + ADT vs ADT, PFS: HR 0.62, 80%CI 0.41-0.91; p = 0.052
📌BF @ 2 yrs: 11% vs 19% pic.twitter.com/fkHw8hzOri
PACE-A NCT01584258
ForLocalised low/intermediate-risk PCa, Gleason ≤3+4, PSA ≤20, RP candidate
TL;DRSBRT 36.25 Gy/5fx vs prostatectomy: 13 BCF events, HR 0.48 (95% CI 0.16-1.46), p=0.18; 5-yr BCF-free 94.8% vs 94.1% in localised low/intermediate-risk PCa.
Failure was scored at nadir+2 ng/ml after SBRT but >0.2 ng/ml after prostatectomy, so the BCF comparison is not symmetric; salvage is the cleaner read (RT in 5 prostatectomy pts, surgery in 1 SBRT pt). At 36.25 Gy in 5 fractions without ADT, this informs counselling surgical candidates on definitive SBRT.
In a man with low or intermediate-risk localised prostate cancer (cT1-T2, Gleason ≤3+4, PSA ≤20) who is a prostatectomy candidate, this supports presenting SBRT without ADT as a definitive alternative; it does not extend to disease above Gleason 3+4 or PSA 20. The longer read
Failure was scored at nadir+2 ng/ml after SBRT but >0.2 ng/ml after prostatectomy, so the BCF comparison is not symmetric; salvage is the cleaner read (RT in 5 prostatectomy pts, surgery in 1 SBRT pt). At 36.25 Gy in 5 fractions without ADT, this informs counselling surgical candidates on definitive SBRT.
For the operating surgeon the functional contrast is the read: ≥1 urinary pad at 5 years in 14/29 (48%) after prostatectomy vs 3/36 (8.3%) after SBRT, with 5 prostatectomy pts going on to salvage RT. Approach (open, laparoscopic, robot assisted) was mixed and its split is not reported in source.
Also covered Oct 4
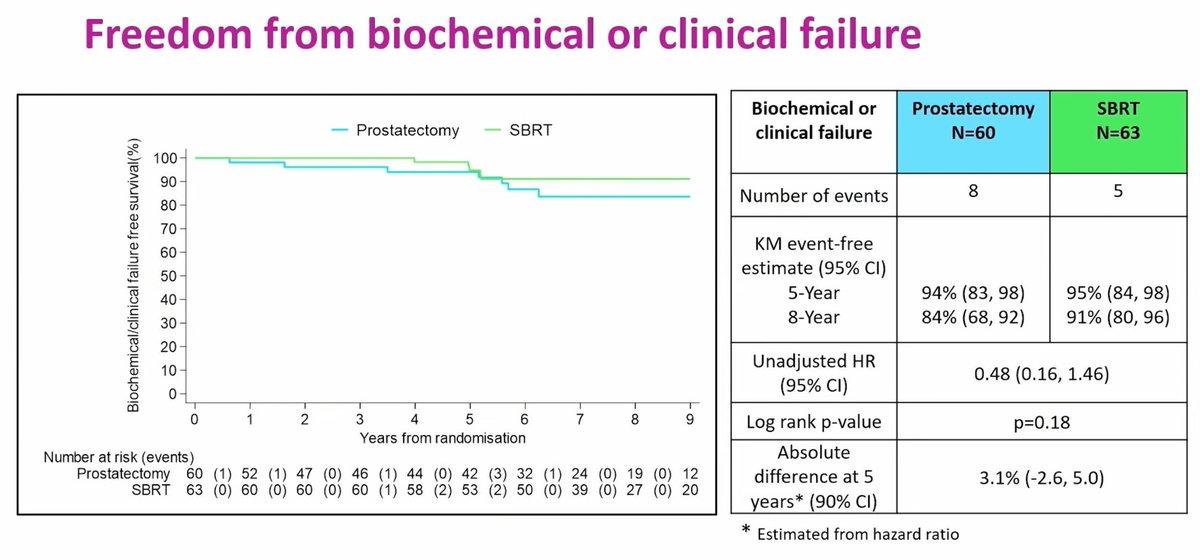
| Arm | N | Events | 5-Year event-free (95% CI) | 8-Year event-free (95% CI) |
|---|---|---|---|---|
| Prostatectomy | 60 | 8 | 94% (83, 98) | 84% (68, 92) |
| SBRT | 63 | 5 | 95% (84, 98) | 91% (80, 96) |
+2 more figures

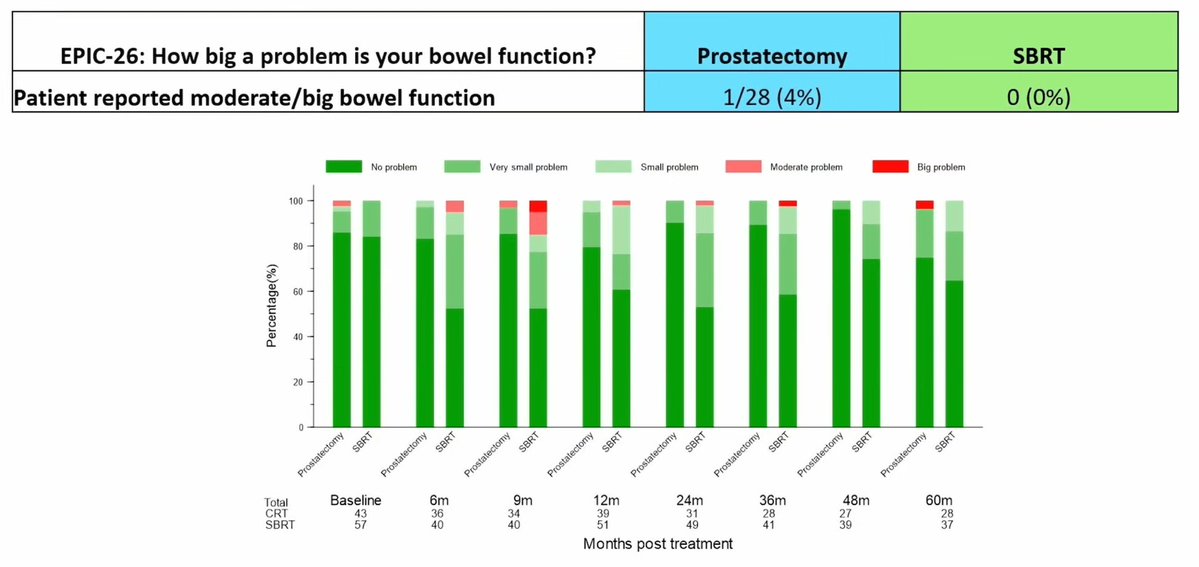
14 details
Phase III, open-label, multicohort RCT (PACE); PACE-A randomised 1:1 to SBRT or prostatectomy. N=123 (63 SBRT, 60 prostatectomy) from 8 centres per the abstract, August 2012 to February 2022. Median follow-up 8 years (IQR 6.1-8.0); analysis by intention to treat.
Men with localised prostate cancer, cT1-T2, Gleason ≤3+4, PSA ≤20 ng/mL, MRI staged, who were suitable candidates for prostatectomy. Median age 65.5 years (IQR 60.5-68.6), median PSA 7.9 ng/mL (IQR 5.9-11.0); 5.7% low-risk and 94.3% intermediate-risk.
SBRT 36.25 Gy in 5 fractions over 1-2 weeks, with no ADT permitted. Target volume, margins, platform and any intraprostatic boost are not reported in source.
Comparator was radical prostatectomy by open, laparoscopic or robot-assisted approach. The split between approaches and nodal dissection practice is not reported in source.
Freedom from biochemical/clinical failure: PSA rise (nadir+2 ng/ml post-RT or >0.2 ng/ml post-prostatectomy), ADT start, recurrence, metastases or prostate cancer death. The source does not state whether this was the prespecified primary endpoint or give a non-inferiority margin. Function by EPIC-26 and clinician-reported CTCAE.
13 BCF events (5 SBRT, 8 prostatectomy), unadjusted HR 0.48 (95% CI 0.16-1.46; p=0.18). BCF-free at 5 years 94.8% (84.6, 98.3) SBRT vs 94.1% (82.6, 98.1) prostatectomy; at 8 years 91.2% (80.1, 96.2) vs 83.7% (68.4, 92.0). Seven deaths, none from prostate cancer.
| Endpoint | SBRT | Prostatectomy |
|---|---|---|
| ≥1 urinary pad at 5 yrs (EPIC-26) | 3/36 (8.3%) | 14/29 (48%) |
| Moderate/big bowel problem (EPIC-26) | 0 | 1/28 (3.6%) |
| CTCAE G≥2 GI | 1/54 (2%) | 0 |
| CTCAE G≥2 GU | 2/53 (3.8%) | 1/40 (2.5%) |
At 5 years, ≥1 urinary pad in 3/36 (8.3%) SBRT vs 14/29 (48%) prostatectomy. Moderate/big bowel problem in 0 SBRT vs 1/28 (3.6%) prostatectomy. Clinician-reported G≥2 GI 1/54 (2%) vs 0 and G≥2 GU 2/53 (3.8%) vs 1/40 (2.5%), SBRT vs prostatectomy. Sexual function is not reported in source.
ProtecT is the randomised reference for surgery against radiotherapy in localised disease, using conventionally fractionated RT rather than SBRT. PACE-B, a sibling cohort of the same trial, compared SBRT with longer-course RT in men not headed for surgery. This is the direct randomised SBRT against prostatectomy efficacy comparison that the abstract describes as lacking.
Failure thresholds differ by arm, so PSA failure is detectable earlier after surgery than after SBRT. The 5-year pad figures rest on 36 and 29 respondents of 63 and 60 randomised. The tweet reports 10 centres against the abstract's 8, and the slide labels the absolute-difference interval 90% CI where the abstract says 95%.
The 5-year rates are near identical and the 8-year gap rests on few men at risk, so the defensible read is no detectable difference, not SBRT superiority. The continence contrast is the largest effect in the dataset and the bowel penalty usually set against RT is not visible here. It does not settle metastasis or mortality outcomes.
CONSORT flow
Randomised phase III supporting an already-listed SBRT option, but only 13 events, a CI spanning both directions, no non-inferiority margin, and arm-specific failure definitions. Supports, does not prove, equivalence.
- Metastasis and prostate cancer mortality by arm with more events
- SBRT vs prostatectomy above Gleason 3+4 or with ADT
- Sexual function by arm, not reported in source
📚 Sources · 🐦 1 tweet · 📄 1 paper
#ASTRO26 Plenary -- PACE-A: 5-yr Outcomes of RP vs SBRT for GG1-2 PCa @nickva1 @urotoday
— Zach Klaassen (@zklaassen_md) September 28, 2026
📍n=123 (60 RP, 63 SBRT), mFU 8 yrs, 10 🇬🇧 centers
📍13 BCF events: HR 0.48, 95% CI 0:16-1.46
📍7 deaths (no PCa): HR 0.55, 95% CI 0.12, 2.46
📍EPIC-26 >=1 urinary pad: 14/29 (48%) RP vs… pic.twitter.com/tSYdMxDayT
Abstract
LAVA-CRLM NCT03654131
For1-3 oligometastatic CRLM ≤4 cm (treated ≤3 cm), Child-Pugh A, curative intent
HR 0.87
95% CI 0.43-1.74, p=0.70; 1-yr 83.0% vs 77.7%, not met
TL;DR1-yr freedom from local progression 83.0% SBRT vs 77.7% MWA (HR 0.87, p=0.70); treatment-related G2+ toxicity 3% vs 25% in oligometastatic CRLM.
The dose and platform set the transfer bar: 45 Gy/3 fx at the 67% isodose, BED10 >173 Gy to GTV, 88% on MR-linac with daily adaptation, and no G3+ toxicity vs 4 (8%) after MWA. SBRT's case rests on that toxicity gap for small lesions, not on a local control win.
In pts with 1-3 CRLM ≤3 cm judged suitable for both ablation and SBRT, this supports SBRT as a non-invasive alternative when ablation access or procedural risk is the concern; it does not extend to 3-4 cm lesions or to settings without ablative-dose delivery. The longer read
Ablative dosing (45 Gy/3 fx, BED10 >173 Gy to GTV) on MR-linac with daily adaptation produced no G3+ toxicity and a 1-yr FFLP of 83.0%. The transfer question is platform: only 5 pts were treated on a conventional linac, so non-MR centres lack direct support.
For HPB teams, MWA carried 4 (8%) G3+ events including a fatal hepatic necrosis with perforation, vs none with SBRT, at no detectable local control cost for lesions ≤3 cm. Resection remains standard; this informs the non-resection choice, where SBRT can spare anaesthesia and open or laparoscopic access.
10 details
Investigator-initiated randomised phase II, 1:1, two Danish centres, no stratification. N=100 randomised Jan 2019 to Dec 2024; mITT 92. Open-label, with masked 1° endpoint imaging review.
1-3 CRLM, each ≤4.0 cm, Child-Pugh A, liver volume ≥700 mL, no prior liver RT. MDT-deemed suitable for both MWA and SBRT; limited extrahepatic disease allowed if curative strategy feasible. Median lesion 1.2 cm; 78% had a single metastasis.
45 Gy/3 fx preferred, 50 Gy/5 fx when OAR constraints required, prescribed to the 67% isodose; PTV 10 mm craniocaudal, 5 mm radial. BED10 >173 Gy to GTV in all. 88% on MR-linac with daily online adaptation.
Primary: patient-level freedom from local progression of treated lesions (new lesions not events). Secondary: OS, treatment-related G3+ toxicity, late G2+ toxicity; EORTC QLQ-C30.
Acute G2+ 1 (3%) SBRT vs 13 (25%) MWA; G3+ only after MWA, 4 (8%) including one death from hepatic necrosis with capsular perforation. Liver pain G1 in 3 (7.5%) SBRT vs 25 (48%) MWA. QoL did not differ.
Authors cite MWA local control exceeding 90% and 1-yr SBRT LC ranging 50% to 95% in prior, largely retrospective series. Dose here clears Kang's BED10 >117 Gy threshold for ~90% 1-yr LC, so a dose deficit does not explain SBRT's result.
KRAS-mutant disease was 45% vs 24% in the MWA vs SBRT arms, with no molecular stratification; Hong reported KRAS-mutant 1-yr LC 43% vs 72%, a large enough modifier to move arm estimates. Single institutional network; post-protocol systemic therapy uncontrolled.
The trial gives the first randomised head-to-head data, not an equivalence claim; a null HR with CI 0.43-1.74 leaves room for either modality to be meaningfully better. What it settles more firmly is that SBRT avoids the invasive-procedure harms MWA carries.
| Endpoint | SBRT | MWA | Effect |
|---|---|---|---|
| 1-yr FFLP, mITT | 83.0% (72.3-95.4) | 77.7% (66.5-90.9) | HR 0.87 (0.43-1.74), p=0.70 |
| 1-yr FFLP, per-protocol | 86.0% (75.3-98.2) | 77.7% (66.5-90.9) | HR 0.78 (0.37-1.63), p=0.50 |
| 3-yr OS, mITT | 71.5% (58.3-87.7) | 63.3% (49.3-81.2) | HR 0.91 (0.48-1.70), p=0.80 |
| Toxicity | SBRT | MWA | Test |
|---|---|---|---|
| G2+ acute (≤1 mo) | 1 (3%) | 13 (25%) | n/a |
| G3+ acute (≤1 mo) | 0 (0%) | 4 (8%), incl 1 death | Fisher p=0.13 |
| 1-yr cumulative G2+ | 7.5% (1.9-18.4) | 20.7% (10.6-33.1) | Fine-Gray HR 0.51 (0.21-1.24) |
| 3-yr cumulative G2+ | 24.6% (9.8-42.9) | 32.7% (18.5-47.6) | Gray's p=0.13 |
CONSORT flow
Randomised but small phase II powered for HR 0.38, not equivalence; null 1° EP with wide CI cannot establish SBRT matches MWA. Toxicity underpowered.
- Does SBRT match MWA for 3-4 cm colorectal liver metastases?
- Does KRAS/TP53 status modify SBRT vs MWA local control?
- Would a powered non-inferiority trial confirm local control parity?
📚 Sources · 📄 1 paper
ROAM/EORTC-1308
ForNewly diagnosed WHO grade 2 atypical meningioma after Simpson I–III resection
HR 0.51
95% CI 0.27–0.97, p=0.0396
TL;DRAdjuvant IMRT 60 Gy/30 fx vs observation after complete resection of WHO grade 2 atypical meningioma: DFS HR 0.51 (0.27–0.97); 5-yr DFS 79.9% vs 64.3%.
The RT effect is probably understated: 12 of 78 assigned pts never started RT, and DFS counts out-of-field and new meningiomas that a 5–10 mm CTV was never aimed at. The planned patterns-of-failure analysis will decide whether dural margins can tighten under modern IGRT, which is the next dosimetric question once adjuvant RT is adopted.
For a newly diagnosed WHO grade 2 atypical meningioma after surgeon-assessed Simpson I–III resection, this supports adjuvant fractionated RT over observation when recurrence prevention is the priority; it does not address subtotal resection, NF2, multiple or radiation-induced meningiomas. The longer read
IMRT 60 Gy/30 fx to a 5–10 mm CTV halved the DFS hazard (HR 0.51) with no G3+ AEs among RT-related events and one G2 necrosis. The pending patterns-of-failure analysis decides whether dural margins can tighten.
Surgeon-assessed Simpson I–III resection without early postop MRI still left 30% recurrence under observation at 64 mo. GTR alone is not definitive for atypical meningioma; authors suggest observation mainly where re-resection is easy, such as convexity tumours.
10 details 1 trial watching
International open-label phase 3 RCT, 1:1, 58 hospitals in 11 countries, stratified UK vs non-UK. N=157 randomised from 990 screened; median follow-up 64 mo.
Age ≥16, newly diagnosed atypical meningioma after surgeon-assessed GTR (Simpson I–III), WHO PS ≤2, able to start RT within 12 weeks. Excluded NF2, multiple or radiation-induced meningiomas, optic nerve sheath tumours.
IMRT 60 Gy in 30 fx over 6 weeks, median 2.50 mo from surgery. CTV 5–10 mm isotropic from GTV plus 3–5 mm PTV, with prospective central plan review before treatment.
Primary: DFS, surgery to MRI-confirmed recurrence or death. Secondary: HRQoL, neurocognition (UK/Ireland), time to second-line treatment, OS, cost-effectiveness.
Early RT-related AEs in 30 (45%), all G1-2; late in 17 (26%). G2 or 3 RT-related SAEs 5 (8%), including one G2 radiation necrosis and one G2 optic neuritis; no treatment-related deaths.
Before this, evidence was retrospective series and two non-randomised phase 2 cohorts reporting 3-yr PFS 88.7% (60 Gy/30 fx) and 93.8% (54 Gy/30 fx). NRG BN003 asks the same randomised question and will be the replication test.
No central pathology review (5 pts would now be grade 3) and no mandated early postop MRI. HRQoL data fell to 38% at 5 years and neurocognition was UK/Ireland-only with ~45% missing by 24 mo, so the null QoL and cognitive findings are weak.
With 70% of observed pts recurrence-free at 5 years, the result supports offering RT rather than mandating it. Methylation class stratifies risk but did not erase the RT effect, so it cannot yet select who to observe.
| Endpoint | Radiotherapy (n=78) | Observation (n=79) | Effect |
|---|---|---|---|
| Meningioma recurrence | 11 (14%) | 24 (30%) | n/a |
| 5-yr DFS | 79.9% (67.6–87.9) | 64.3% (51.9–74.2) | Diff 15.6 pp (0.6–30.5) |
| DFS, ITT | n/a | n/a | HR 0.51 (0.27–0.97), p=0.0396 |
| DFS, as-treated | 10/66 (15%) recurred | 25/91 (27%) recurred | HR 0.54 (0.28–1.04), p=0.0642 |
| Deaths | 7 (9%) | 6 (8%) | 5-yr OS OR 0.91 (0.27–3.05) |
| Second-line treatment | 8 (10%) | 16 (20%) | n/a |
CONSORT flow
First randomised evidence and primary DFS met, but accrual closed at 41 of 46 planned events, CI upper bound 0.97, and recurrence was read locally without masking.
- Do patterns of failure support tighter dural margins?
- Can methylation class identify pts safe to observe? n=210 · primary completion 2026-03 · DNA methylation signature for recurrence after GTR
- Is adjuvant RT cost-effective vs active monitoring?
📚 Sources · 📄 1 paper
BIG 3-07/TROG 07.01 NCT00470236
ForNon-low-risk DCIS after BCS, ≥1 mm clear radial margins
TL;DRTumour bed boost after WBI in resected non-low-risk DCIS: 5-yr freedom from LR 97.1% vs 92.7%, HR 0.47 (0.31-0.72), p<0.001.
The boost gain held on a 42.5 Gy/16 fx WBI backbone as well as 50 Gy/25 fx, so boost is not tied to conventional fractionation. The cost is G2+ induration 14% vs 6%, which is the number to weigh when deciding boost vs omission after ≥1 mm margins in non-low-risk DCIS.
In a woman with resected non-low-risk DCIS and ≥1 mm margins planned for WBI, this supports offering a 16 Gy/8 fx boost against a higher G2+ induration and pain rate; it does not address low-risk DCIS or pts with <1 mm margins. The longer read
Boost 16 Gy/8 fx cut LR hazard (HR 0.47) on both 50 Gy/25 fx and 42.5 Gy/16 fx WBI backbones, so it transfers to hypofractionated practice. The trade is G2+ induration 14% vs 6%, which frames the boost-or-omit conversation in non-low-risk DCIS with ≥1 mm margins.
7 details 4 trials watching
International randomised, unmasked, factorial phase 3, 136 centres across six trial groups in 11 countries. N=1608 accrued 2007-2014; median f/u 6.6 yr.
Women ≥18y with unilateral, histologically proven non-low-risk DCIS after breast-conserving surgery with ≥1 mm clear radial margins.
WBI either 50 Gy/25 fx (n=831) or 42.5 Gy/16 fx (n=777), randomised in a 4-arm factorial or chosen per centre. Boost 16 Gy/8 fx to tumour bed after WBI.
Primary: time to local recurrence. Toxicity reported as G2+ breast pain and induration.
Boost raised G2+ breast pain (14% vs 10%, p=0.003) and G2+ induration (14% vs 6%, p<0.001).
Older DCIS trials (NSABP B-17, EORTC 10853) established WBI after lumpectomy but did not test boost; the EORTC boost trial tested it only in invasive disease. This is the first randomised boost evidence in DCIS.
The fractionation-sensitivity result is not reported in the source abstract, so hypofractionation non-inferiority in DCIS cannot be read from it. Toxicity is assessor-unmasked, and no survival endpoint is reported.
A boost roughly halves local recurrence hazard in non-low-risk DCIS at a real cost in G2+ breast morbidity. It does not settle which non-low-risk subsets carry enough baseline risk to justify that trade.
CONSORT flow
Adequately powered phase 3 RCT, primary endpoint hit with 6.6-yr median f/u; first randomised boost data in DCIS. Qualified by unmasked design and added G2+ toxicity.
- Which non-low-risk DCIS subsets derive most boost benefit
- Local recurrence with hypofractionated vs conventional WBI in DCIS n=301 · primary completion 2020-11 · randomised hypo vs standard WBI, DCIS eligiblen=72 · primary completion 2026-12 · 1-wk vs 3.1-wk WBI, DCIS eligible, local control EP
- Boost role with ultra-hypofractionated or partial-breast RT recruiting Ultra Hypo-fractionated Adjuvant Whole Breast Radiation Therapy With Simultaneous Integrated Boost for Early-Stage Breast Cancer (H-ASSIST) Phase 2n=90 · primary completion 2028-02 · 5-fx WBI + SIB tumour bed boost, DCIS includedrecruiting 5 vs. 9-day Course of Whole Breast Radiotherapy With Boost for Early-stage Breast Cancer Phase 2n=144 · primary completion 2030-05 · randomised 5 vs 9 day WBI with boost, DCIS eligible
📚 Sources · 📄 1 paper
Abstract
Gamma Knife vs LINAC-based radiosurgery for vestibular schwannoma (retrospective review)
ForVestibular schwannoma, mostly Koos II solid, intracanalicular or mixed
TL;DRLocal control 98.8%; no difference in new vertigo, gait disturbance or facial palsy with GKRS (n=36) vs LINAC (n=49) SRS for vestibular schwannoma.
The 98.8% local control is freedom from further VS-directed intervention; volumetric enlargement still occurred in 6/36 GKRS and 9/49 LINAC pts. The LINAC arm pools margin-free 12 Gy to the 80-99% IDL with post-May 2017 frameless 12 Gy plus a 5 mm PTV margin, era split unreported, so it cannot say which LINAC approach matches GK.
In small, mostly Koos II vestibular schwannoma, this supports GK or LINAC single-fraction SRS chosen by local availability when weighing new vertigo, gait disturbance or facial palsy; it does not inform hearing preservation, which the series did not report. The longer read
The 98.8% local control is freedom from further VS-directed intervention; volumetric enlargement still occurred in 6/36 GKRS and 9/49 LINAC pts. The LINAC arm pools margin-free 12 Gy to the 80-99% IDL with post-May 2017 frameless 12 Gy plus a 5 mm PTV margin, era split unreported, so it cannot say which LINAC approach matches GK.
9 details
Retrospective chart review across multiple sites of a single institution, VS treated 2008-2017; N=85 (36 GKRS, 49 LINAC). Platform set by provider preference, as GKRS and LINAC sit at different centers. Median follow-up 27 mo.
Vestibular schwannoma, 95.3% solid, intracanalicular (45.9%) or intra- plus extracanalicular (43.5%); Koos II majority with no Koos difference between cohorts (p=0.65). Pre-SRS symptoms were common: tinnitus 62.4%, gait disturbance 48.2%, vertigo 30.6%.
All single-fraction SRS. GKRS: 12.5 Gy to the 50% IDL, stereotactic head frame. LINAC: 12 Gy to the 80-99% IDL with no CTV/PTV margin, then from May 2017 frameless, 12 Gy to the 100% IDL with a 5 mm PTV margin by VMAT.
No primary endpoint stated in source. Outcomes were new tinnitus, vertigo, gait disturbance and facial palsy (HB grade 3 or higher) in pts free of each at baseline, plus volumetric MRI tumor control. Hearing not reported; trigeminal dysfunction excluded for inconsistent documentation.
Local control 98.8%, with 1/85 pts needing salvage (surgery, LINAC arm). No difference in direction of tumor size change (p=0.199).
| New symptom | GKRS | LINAC | p |
|---|---|---|---|
| Tinnitus | 1/13 (7.7%) | 1/19 (5.5%) | 0.0007 (MVA) |
| Vertigo | 1/28 (3.6%) | 2/31 (6.5%) | 0.785 |
| Gait disturbance | 4/18 (22.3%) | 4/26 (15.4%) | 1.000 |
| Facial palsy (HB ≥3) | 0/34 (0.0%) | 2/48 (4.2%) | 0.509 |
| Tumor outcome | GKRS (n=36) | LINAC (n=49) |
|---|---|---|
| Decreased or stable | 30/36 | 40/49 (81.6%) |
| Increased size | 6/36 (16.7%) | 9/49 (18.4%) |
| Salvage required | None | 1/49 (2.0%) |
Both new LINAC facial palsies resolved (2/2); none occurred after GKRS. New gait disturbance resolved in 3/4 GKRS and 2/4 LINAC pts, and the single new GKRS tinnitus persisted.
Authors position this against prior series reporting favorable local control with GKRS or LINAC individually, where direct symptom and QOL comparisons were lacking. The source names no randomized GK vs LINAC comparison; the authors call for prospective data.
The 'QOL' outcomes are chart-abstracted symptoms, with HB grade assigned by the reviewing author when not documented. Mean follow-up differs (24 vs 36 mo), and the tinnitus p=0.0007 on multivariable analysis rests on 1 event per arm. Methods and results disagree on pre-2017 LINAC immobilization.
Median follow-up of 27 mo sits inside the 3-year window in which the authors cite 20-30% pseudoprogression, so the enlargements in both arms are not yet resolved as benign. The data show no signal of platform-specific vestibular or facial harm; they do not show parity.
Retrospective, provider-preference allocation, N=85; symptom comparisons use difference tests on single-digit event counts, so the 'interchangeable' conclusion is not something this design can establish.
- Does hearing preservation differ between GK and LINAC SRS?
- Does a 5 mm PTV margin on frameless LINAC add cranial nerve toxicity?
- Tumor control beyond the 3-year pseudoprogression window
📚 Sources · 📄 1 paper
TORPEdO
ForLocally advanced oropharyngeal SCC, 96% p16+, cisplatin-eligible, no N3
18% vs 7%
adj OR 2.80 (97.5% CI 0.75–10.41), p=0.079, not met; UW-QoL p=0.56
TL;DR18% vs 7% 12-mo G-tube dependence/≥20% weight loss (p=0.079), UW-QoL 78.3 vs 77.1 (p=0.56): IMPT not superior to IMRT, locally advanced oropharyngeal SCC.
Lower OAR doses on IMPT did not become function: 12-mo UW-QoL 78.3 vs 77.1, and ≥20% weight loss ran higher on IMPT (20/110 vs 3/53), persisting at 24 mo in 12 of 95. Dutch NTCP-enriched pts also showed no clear gain (78.2 vs 75.8), undercutting model-based IMPT referral in locally advanced oropharyngeal SCC.
In cisplatin-eligible locally advanced oropharyngeal SCC, mostly p16-positive, planned for 70 Gy in 33 fractions with bilateral neck RT, this does not support IMPT over optimised IMRT for 12-mo swallowing, nutrition or QoL; it does not extend to N3 disease, induction chemo, or post-operative RT. The longer read
The RT read: IMPT against IMRT planned to identical 70 Gy/33 fx targets and OAR priorities gave no 12-mo functional gain (UW-QoL 78.3 vs 77.1), while ≥20% weight loss ran 20/110 vs 3/53. Dutch NTCP-enriched pts showed 78.2 vs 75.8, weakening model-based IMPT referral.
11 details 2 trials watching
Phase 3, multicentre, open-label RCT at 20 UK NHS hospitals, 2:1 by minimisation, N=205 (136 IMPT, 69 IMRT). IMPT delivered at two proton centres, IMRT at the local referring centre. Median follow-up 28.3 mo (IQR 26.5 to 39.3).
Newly diagnosed locally advanced oropharyngeal SCC suitable for concurrent CRT including bilateral neck treatment; 197/205 (96%) p16-positive, 99 (48%) T3 or T4. Excluded: N3, upfront neck dissection, induction chemo, prior H&N RT, or a feeding tube needed before treatment.
70 Gy to the therapeutic target and 56 Gy to lower-risk volumes in 33 daily fractions over 6.5 weeks, RBE 1.1 for IMPT, same OAR planning priorities in both arms. IMPT plans checked against 3-mm setup and 3.5% range uncertainty, with daily CBCT and a week-3 repeat planning CT in both arms.
Concurrent cisplatin 100 mg/m² every 3 weeks x2. 138 (69%) of 199 received both cisplatin cycles; 49 (25%) received cisplatin then carboplatin.
Co-primary at 12 mo: gastrostomy-tube dependence or severe (≥20%) weight loss, and UW-QoL physical composite score; either reaching significance counted as success (α=0.025 each). LRC and OS were exploratory.
Neither co-primary met. Composite events were driven by weight loss (20/110 vs 3/53); G-tube dependence was 2% in both arms.
| Endpoint | IMPT | IMRT | Effect |
|---|---|---|---|
| G-tube dependence or ≥20% weight loss, 12 mo (co-primary) | 21/119 (18%) | 4/59 (7%) | adj OR 2.80 (97.5% CI 0.75–10.41), p=0.079 |
| ≥20% weight loss, 12 mo | 20/110 (18%) | 3/53 (6%) | n/a |
| G-tube dependence, 12 mo | 2/119 (2%) | 1/59 (2%) | n/a |
| UW-QoL physical composite, 12 mo (co-primary) | 78.3 | 77.1 | diff 1.3 (97.5% CI –3.7 to 6.2), p=0.56 |
| UW-QoL physical composite, 3 mo | 70.8 | 66.8 | diff 4.0 (99% CI –1.4 to 9.5) |
| UW-QoL physical composite, 24 mo | 81.6 | 79.9 | diff 1.7 (99% CI –3.6 to 7.0) |
| 24-mo freedom from LRR | 94% (99% CI 86–98) | 97% (82–100) | HR 2.6 (99% CI 0.3–20.3), p=0.24 |
| 24-mo OS | 95% (86–98) | 95% (81–99) | HR 1.6 (99% CI 0.3–8.8), p=0.47 |
14 serious AEs in 12 pts, treatment-related in one IMPT vs four IMRT; no treatment-related deaths. Grade 3 weight loss persisted at 24 mo in 12 (13%) of 95 IMPT pts vs none on IMRT.
PARSPORT made parotid-sparing IMRT the photon benchmark. TORPEdO asks whether IMPT adds function over IMRT planned to the same OAR targets; at 12 mo it did not.
Feeding-tube policy was set per centre and prophylactic placement was lower on IMPT (26% vs 38%), confounding tube and weight endpoints. IMPT delivery was more disrupted (replanning 61% vs 30%, cyclotron-driven interruptions), so a mature proton service may perform differently.
The composite leaned against IMPT on weight loss (18% vs 6% at 12 mo), opposite to the dosimetric hypothesis, though p=0.079 does not establish harm. With OAR doses lower on IMPT for most structures and no functional gain, the gap between dosimetric advantage and patient-reported benefit is now the open question.
CONSORT flow
Randomised phase 3, both co-primaries null, source concludes IMRT remains SOC. Open-label, N=205, 2:1 allocation: wide CIs cannot exclude a meaningful difference either way.
- Does IMPT reduce late toxicity beyond 24 months? n=440 · primary completion 2031-12 · phase 3 IMPT vs IMRT, stage III-IVB OPSCC, side effects
- Why did severe weight loss run higher with IMPT?
- Can any NTCP threshold select pts who gain function from IMPT? n=400 · primary completion 2030-04 · phase 3 randomises NTCP-selected pts, protons vs photons
📚 Sources · 📄 1 paper
PROTEUS
ForHigh-risk prostate cancer, perioperative setting
TL;DR5-yr BCR-FS 44%, MFS 71%, CSS 92% at 60-mo median f/u in a real-world high-risk prostate cancer benchmark cohort.
7 details 1 trial watching
Design not stated in source; described as a real-world benchmark. Median follow-up 60 mo.
Reported: 5-yr BCR-FS, 5-yr MFS, 5-yr CSS. No primary endpoint or effect size stated.
Framed as a reference point for perioperative treatment strategies in high-risk disease, not a test of one. Useful only once the cohort definition and treatments received are known, since those determine which trial populations it can benchmark.
| Endpoint | 5-yr estimate |
|---|---|
| BCR-FS | 44% |
| MFS | 71% |
| CSS | 92% |
Descriptive benchmark with no comparator, N, eligibility, or treatment details in source; cannot classify impact on any perioperative decision.
- Which perioperative strategies improve on this BCR-FS benchmark? active COACTION Trial - COmbination Androgen bloCkade in inTermediate to hIgh-risk prOstate caNcer Phase 4n=144 · primary completion 2026-03 · RCT neoadjuvant leuprorelin+darolutamide pre-RP, pCR EP
- Cohort high-risk definition and treatments received
📚 Sources · 🐦 1 tweet
🔹 Median follow-up: 60 mo
— Can Aydogdu (@CanDAydogdu) August 28, 2026
🔹 5-yr BCR-FS: 44%
🔹 5-yr MFS: 71%
🔹 5-yr CSS: 92%
Providing a real-world benchmark to contextualize perioperative treatment strategies in this high-risk population.
📄 https://t.co/NyszMg9uCA#ProstateCancer #PROTEUS #Urology
MARCAP Consortium
ForLocalized prostate cancer, NCCN intermediate to high risk, definitive RT
TL;DRIPD meta-analysis, 10,853 pts: ADT added to RT improved MFS HR 0.83 and OS HR 0.86; dose escalation improved bRFS only.
Reported via UroToday →
The dose-invariance result is the load-bearing one: ADT's benefit was identical at ≥74 Gy and <74 Gy (both HR 0.83), so escalating dose does not buy out the ADT decision. Adjuvant prolongation carries the benefit (MFS HR 0.84), neoadjuvant prolongation does not (HR 0.95), which moves sequencing, not just duration.
In NCCN intermediate- and high-risk localized prostate cancer receiving definitive RT, this supports adding and prolonging ADT on the adjuvant side rather than substituting dose escalation; it does not address node-positive or post-prostatectomy salvage settings. The longer read
ADT's benefit was identical at ≥74 Gy and <74 Gy (HR 0.83 both), so escalation does not buy out the hormone decision, and HEAT showed escalation to 79.2 Gy improved biochemical RFS but not MFS or OS. Adjuvant prolongation carries the survival benefit; neoadjuvant prolongation (HR 0.95) does not.
The duration and sequencing read: extending adjuvant ADT from 4-6 to 18-36 months gave MFS HR 0.84 and OS HR 0.85, while extending neoadjuvant ADT from 3-4 to 6-9 months gave HR 0.95 for both. Relative benefit held across NCCN groups, so risk stratification changes NNT, not effect size.
9 details 5 trials watching
Individual patient data meta-analysis from the MARCAP Consortium, 12 eligible trials, 10,853 patients, median follow-up 11.4 years (IQR 9.0-15.0). Three intensification questions analyzed separately: ADT use, neoadjuvant ADT prolongation, adjuvant ADT prolongation.
Localized prostate cancer treated with definitive radiotherapy, stratified by NCCN prognostic risk group. The RT ± ADT comparison ran 2,557 control vs 2,579 experimental (NCCN high 32.6% vs 32.8%, intermediate 47.6% vs 48.7%); the adjuvant-prolongation comparison was high-risk enriched at 71.5% vs 71.1% NCCN high across 1,900 vs 1,874 pts.
Dose was analyzed as a binary ≥74 Gy vs <74 Gy split, with the companion HEAT analysis using 64 to <74 Gy vs ≥74 Gy and escalation up to 79.2 Gy. Brachytherapy boost is discussed as an escalation route alongside external-beam dose.
ADT addition improved MFS HR 0.83 (0.77-0.89) and OS HR 0.86 (0.80-0.92). Adjuvant prolongation improved MFS HR 0.84 (0.78-0.91) and OS HR 0.85 (0.78-0.94); neoadjuvant prolongation did neither (MFS HR 0.95, OS HR 0.95). 10-yr MFS 61% (59-63) with ADT vs 52% (50-54) without; 10-yr OS 65% (63-67) vs 57% (55-59).
| Intervention | Intermediate risk | High risk |
|---|---|---|
| ADT addition | 18.0 | 8.4 |
| Adjuvant ADT prolongation | 16.1 | 10.4 |
The 2022 HEAT network meta-analysis (13 trials, 11,862 pts) found dose escalation improved biochemical RFS but not MFS or OS, and named high-dose RT plus long-term ADT the best strategy. PROG 05/09 and GETUG-18 are invoked to explain the gap: a 21% 5-year biochemical benefit in low risk where metastasis is rare, versus 3% in high risk where it is not.
The pooled trials span 30+ years of practice, so the RT technique behind the <74 Gy stratum is not the technique a reader delivers today. The stated optimal durations (closer to 12 months high risk, 24+ months very high risk) come from DHARMA, accepted but unpublished, so that specific number is not yet auditable.
The framing claim is that dose escalation and ADT are not interchangeable levers: escalation buys biochemical control, ADT buys metastasis-free and overall survival, and the two do not substitute. The dogma that dose escalation obviates ADT is named as widely repeated and never demonstrated.
IPD meta-analysis of randomised trials, large N, long f/u. Reinforces ADT intensification over dose escalation; no new randomisation, and duration guidance rests on unpublished DHARMA.
- Optimal adjuvant ADT duration by prognostic risk group active A Study of Shorter Course Hormone Therapy and Radiation for High-risk Prostate Cancer Phase 2n=50 · primary completion 2026-10 · shorter-course ADT with brachy + hypofx EBRT, high-riskrecruiting Artificial Intelligence Driven Personalisation of Radiotherapy and Concomitant Androgen Deprivation Therapy for Prostate Cancer Patients (the HypoPro Trial) Phase 2n=30 · primary completion 2026-10 · MMAI classifier individualises ADT duration, high-risk
- Does dose escalation change ADT benefit with modern brachytherapy boost active Comparative Study of Radiotherapy Treatments to Treat High Risk Prostate Cancer Patients Phase 3n=307 · primary completion 2028-12 · phase 3 HDR brachy boost vs dose-escalated RT + ADTrecruiting Androgen Suppression Combined With Nodal Irradiation and Dose Escalated Prostate Treatment Phase 3n=710 · primary completion 2032-10 · phase 3 SBRT vs EBRT + brachy boost, all on ADTrecruiting PRO-BOOST-LC: Whole-Gland Boost Strategies Versus SBRT Monotherapy in PSMA-Staged Localized and Locally Advanced Prostate Cancer Phase 2/3n=1000 · primary completion 2033-12 · randomised brachy or SBRT boost vs SBRT alone, + ADT
- Whether intermediate-risk subsets warrant long-term ADT
📚 Sources · 📄 1 paper
Abstract
STAR-TREC
ForRectal adenocarcinoma ≤40 mm, mrT1-T3bN0, no EMVI, ECOG 0-1
78.5% vs 60.6%
HR 1.90 (95% CI 1.29-2.81); 30-mo organ-preservation 1° EP not yet reported
TL;DR12-mo TME-free survival 78.5% vs 60.6% (HR 1.90) favouring LCCRT over SCRT for organ preservation in mrT1-T3bN0 rectal cancer ≤40 mm.
RT delivery does not explain the gap: completion was 99% with LCCRT and 100% with SCRT, with 18 (11%) needing a capecitabine dose change, so the difference tracks fractionation plus concurrent chemo, which this design cannot separate. Nodes in 22% of TME specimens despite MRI N0 make mesorectal coverage relevant; target volume is not in source text.
In MRI node-negative rectal adenocarcinoma ≤40 mm (mrT1-T3bN0) choosing organ preservation, this supports LCCRT over SCRT as the response-adapted backbone at 12 mo; it does not extend to EMVI-positive, node-positive, or >40 mm tumours. The longer read
RT delivery does not explain the gap: completion was 99% with LCCRT and 100% with SCRT, so the TME-free survival difference tracks fractionation plus concurrent capecitabine, which this design cannot separate. Nodes in 22% of TME specimens despite MRI N0 make mesorectal coverage relevant; target volume is not in source text.
Primary TME carried G≥3 SAEs in 18%, anastomotic-leak perforation in 15% and one death, and 86% of phase 3 pts chose organ preservation. LCCRT-OP kept more pts TME-free at 12 mo, but nodes in 22% of TME specimens despite MRI N0 frame the surveillance and salvage question.
9 details 1 trial watching
Open-label, randomised phase 2/3 at 37 sites in five European countries. Phase 2 randomised 1:1:1 to LCCRT-OP, SCRT-OP or primary TME (N=120); phase 3 used a partially randomised patient-preference design, with OP choosers randomised 1:1. Bayesian framework; this 12-month analysis covers 426 pts recruited before Aug 8, 2023 (409 mITT).
Rectal adenocarcinoma ≤40 mm, mrT1-T3bN0 on MRI, ECOG 0-1, with primary TME judged reasonable. Excluded: MRI nodal involvement or EMVI, tumour within 1 mm of the mesorectal fascia, anterior tumours above the peritoneal reflection, predominantly mucinous histology, metastases. mrT2 in 242 (73%) OP pts; 266 (80%) below the peritoneal reflection.
LCCRT-OP: 50 Gy in 25 fractions with oral capecitabine 825 mg/m² twice daily. SCRT-OP: 25 Gy in five fractions. Response assessed at 16-20 weeks with TAE for near-complete response; target volume not in source text.
Phase 2 primary: feasibility, recruitment at months 12 and 24 against thresholds of ≥4 and ≥6 randomisations/month (achieved 3 and 6). Phase 3 primary: organ preservation at 30 months (no TME, stoma or local recurrence), not yet reported. This analysis reports 12-month TME-free survival, response and safety.
Phase 2 alone gave HR 3.7 (95% CI 1.7-8.0), with median TME-free survival 7.6 mo after SCRT-OP vs not reached after LCCRT-OP; pooling phase 3 pulled the estimate toward the null.
| Endpoint | LCCRT-OP (n=163) | SCRT-OP (n=168) | Effect |
|---|---|---|---|
| TME-free survival | 78.5% (95% CI 72.4-85.1) | 60.6% (53.6-68.4) | HR 1.90 (1.29-2.81), posterior P >99.5% |
| cCR at 16-20 wk | 104 (64%) | 61 (36%) | not reported |
| TAE for near-cCR | 38 (23%) | 68 (40%) | not reported |
| Endpoint | LCCRT-OP | SCRT-OP | Primary TME |
|---|---|---|---|
| G3-4 GI SAEs | 4 (2%) | 6 (4%) | 6 (8%) |
| G3-4 procedural SAEs | 3 (2%) | 5 (3%) | 5 (6%) |
| G≥3 SAEs within 4 wk of RT/CRT | 9/163 (6%) | 2/168 (1%) | n/a |
Primary TME: G≥3 SAEs in 14 (18%) of 78, intraperitoneal perforation from anastomotic leak in 12 (15%), and one postoperative death from sepsis. After TAE, perineal fistulation occurred in two (1%) OP pts. Capecitabine dose modification in 18 (11%) of 161.
At design, primary TME without neoadjuvant therapy was standard for this population. OPRA addressed watch-and-wait after neoadjuvant therapy in locally advanced disease; STAR-TREC is a randomised test of which radiation schedule best supports response-adapted organ preservation in smaller, node-negative tumours.
The shrinking HR from phase 2 to the pooled cohort suggests early overestimation, and phase-difference analyses are exploratory post-hoc. Occult nodes in 17 (22%) TME specimens imply MRI N0 misses nodal disease that organ-preserving arms never sample. Median follow-up was 34 and 35 mo, but outcomes were censored at 12 mo.
At 12 months, a longer RT course with capecitabine buys more complete responses and fewer TMEs than SCRT, at the cost of more acute SAEs. What it does not settle is durable organ preservation, local regrowth and function, all tied to the 30-month endpoint.
Governance-led interim at 12 mo; prespecified 30-mo organ-preservation endpoint not yet reached. Open-label, TME-free survival only, TME comparison non-randomised in phase 3.
- Does the LCCRT advantage persist at the 30-month organ-preservation endpoint?
- Local regrowth and bowel function after LCCRT vs SCRT organ preservation
- Can consolidation chemo after SCRT close the complete-response gap? n=66 · primary completion 2025-09 · SCRT or LCCRT → mFOLFOXIRI, organ preservation, cT2-4a
📚 Sources · 📄 1 paper
Focal Ablation vs IMRT Toxicity (SEER-Medicare)
ForLocalized prostate cancer, fee-for-service Medicare, mean age ~73
TL;DRGI toxicity favored focal therapy at 24mo (11.0% vs 21.5%, OR 0.45) but GU toxicity favored IMRT (41.7% vs 29.3%, OR 1.69).
The GI advantage rests on diagnosis claims alone: procedure-code-only GI events were too few to report and not significantly different, while the GU excess with FT was concrete (incontinence therapy 17.4% vs 7.5%). For an RT reader counseling an older man weighing ablation, that asymmetry is the point.
In an older man with localized prostate cancer choosing between focal ablation and IMRT, this supports counseling that the tradeoff runs GU-for-GI rather than uniformly lower toxicity with ablation; it does not extend to SBRT or proton patients, who were excluded. The longer read
The IMRT comparator is a 2010-2017, ≥20-fraction cohort with SBRT, protons and rectal hydrogel excluded, so the GI toxicity attributed to radiation predates spacer-era rectal sparing. That caps how much of this GI gap should carry into a current consent conversation, while the GU result (incontinence therapy 17.4% vs 7.5% favoring IMRT) transfers intact.
For ablation, the toxicity cost is concrete and periurethral: incontinence therapy 17.4% vs 7.5% and erectile dysfunction 18.2% vs 13.1%, both P<.01. The offsetting GI advantage collapsed in the procedure-only analysis, so the low-morbidity premise for cryotherapy and laser ablation in older men is weaker than the headline suggests.
10 details 5 trials watching
Retrospective SEER-Medicare claims analysis of localized prostate cancer diagnosed 2010-2017. 797 focal therapy patients Mahalanobis matched 2:1 to 1,594 IMRT patients on demographics, Medicaid eligibility, comorbidity, flu vaccination, primary care access, year, cancer characteristics and ADT. Logistic regression at 6, 12 and 24 months.
Fee-for-service Medicare beneficiaries with localized PCa as first and only cancer, continuously enrolled parts A and B from 12 months pre-diagnosis through 24 months post-treatment. New York, Idaho and Massachusetts registries excluded for missing AJCC staging. Patients who died within 24 months of treatment were excluded.
IMRT defined as external beam with no surgery plus ≥20 IMRT fractions and an IMRT planning code; a gap of ≥30 days between radiation dates counted as a separate course. SBRT and proton patients were excluded, as were patients with rectal hydrogel spacer, so the IMRT arm is conventional fractionation without a rectal spacer.
Presence of claims indicative of a GI or GU complication within 6, 12 and 24 months of treatment, assessed both as combined diagnosis and procedure codes and as procedure codes only. No patient-reported outcomes and no graded toxicity scale.
Direction reversed by organ system: GI favored focal therapy from 12 months onward, GU favored IMRT at every window measured. The 0-6 month GI comparison was null (OR 1.06, P=.81).
| Toxicity / window | FT | IMRT | OR (95% CI) |
|---|---|---|---|
| GI 0-6 mo | 3.6% | 3.5% | 1.06 (0.67-1.67), P=.81 |
| GI 0-12 mo | 6.2% | 9.5% | 0.63 (0.45-0.88) |
| GI 0-24 mo | 11.0% | 21.5% | 0.45 (0.35-0.58) |
| GU 0-12 mo | 34.6% | 15.8% | 2.69 (2.21-3.28) |
| GU 0-24 mo | 41.7% | 29.3% | 1.69 (1.42-2.01) |
GU excess with focal therapy was driven by incontinence therapy (17.4% vs 7.5%) and erectile dysfunction (18.2% vs 13.1%), both P<.01. GI events with IMRT were predominantly rectal bleeding and colitis; the authors note related procedures were rare and not significantly different.
Focal therapy patients were disproportionately rural (6.4% vs 1.9%) and lower-income (51.5% vs 38.7% in the lowest two quintiles) before matching, so claim-generating behavior may differ by arm independent of toxicity. Baseline continence and erectile function were unmeasured, which matters most for the two endpoints driving the GU result.
The GI result is fragile in a specific way the abstract does not foreground: it collapses to one diagnosis subcategory and disappears in the procedure-only analysis. The GU result is the more robust half, and it runs against the premise that ablation is the lower-toxicity option.
Claims-based retrospective matching, not randomised; toxicity defined by diagnosis codes, and the GI difference vanished when restricted to procedure codes. No PROs, no baseline function.
- Does the tradeoff hold vs SBRT or spacer-era IMRT? n=184 · primary completion 2027-06 · IRE vs prostatectomy or RT, side-effect endpointn=356 · primary completion 2029-08 · focal therapy vs usual care RCT, ISUP 2/3
- Do patient-reported outcomes track the claims-based GU signal? n=300 · primary completion 2030-12 · prospective validated urinary/sexual PROs after HIFUn=200 · primary completion 2032-03 · questionnaire outcomes across HIFU, cryo, laser, IRE
- Do HIFU and RFA carry the same GU profile as cryo/laser? n=354 · primary completion 2028-12 · HIFU hemi-ablation, continence + toxicity endpoints
📚 Sources · 📄 1 paper
Abstract
NRG-GU005 NCT03367702
ForLocalized favorable intermediate-risk prostate, T1-T2b, GG1-2, PSA <20
88.6% vs 92.1%
SBRT not superior; adjusted HR 1.40 (0.91-2.13), P=.12
TL;DR3yr DFS 88.6% SBRT vs 92.1% MH-IMRT, superiority rejected (adjusted HR 1.40, 0.91-2.13); bowel and GU toxicity favored SBRT.
The number that should move practice is biochemical failure: 7.8% vs 4.2% at 3yr (adj HR 1.82, 1.01-3.27), while local failure was flat at 1.2% vs 1.0%. The SBRT prescription was deliberately modest, 36.25 Gy/5 fx with dose uniformity prioritized and urethral max held to 38.78 Gy, so this reads as a dose and margin question, not a verdict on 5 fractions.
In favorable intermediate-risk localized prostate cancer choosing between 5-fraction SBRT and moderate hypofractionation, this supports the toxicity and convenience case for SBRT while flagging a 3-year PSA-failure gap; it does not speak to unfavorable intermediate or high-risk disease, or to dose-escalated SBRT regimens. The longer read
Biochemical failure, not DFS, carries the read: 7.8% vs 4.2% at 3yr (adj HR 1.82, 1.01-3.27) with local failure flat at 1.2% vs 1.0%. The prescription was deliberately uniform, 36.25 Gy/5 fx with urethral max 38.78 Gy and no focal boost, so this argues about dose and margin rather than about 5 fractions.
Also covered Jul 8
13 details 5 trials watching
Phase 3, international, open-label, 1:1 randomized superiority trial across 136 centers, accruing November 2017 to June 2022 with last follow-up October 2024. N=698 randomized (353 SBRT, 345 MH-IMRT), median follow-up 3.2 years. Two coprimary end points, patient-reported QoL and DFS, each tested at 2-sided alpha .05 with no study-wise correction, so both had to be positive for a positive trial.
Localized cT1-T2b, either Gleason 3+4 (GG2) with PSA <20 ng/mL or Gleason 3+3 (GG1) with PSA 10-20 ng/mL. Median age 68 (range 42-84); 80% White, 13% Black, 3% Asian; 81.7% T1c and 88.1% Zubrod 0. Stratified by risk group and by rectal manipulation, of whom 55.6% used spacer alone and 40.3% no device.
SBRT 36.25 Gy in 5 fractions (7.25 Gy per fraction), delivered as prescribed in 96.6%; MH-IMRT 70 Gy/28 fx in 70.6% or 60 Gy/20 fx in 26.6%. Rectal constraints were max 38 Gy to 0.03 mL and 18 Gy to 50%; bladder 39 Gy and 15 Gy. Where PTV max exceeded 38.78 Gy the urethra had to be contoured and capped at 38.78 Gy, a deliberately uniform, non-escalated prescription. Protocol-compliant or acceptable variation in 97.7% and 97.2% of arms.
Coprimary: MCID frequency in EPIC-26 urinary irritative/obstructive and bowel domains at 24 months, and DFS at 3 years (powered for HR 0.62). Secondary: the other EPIC-26 domains at 12 and 24 months, overall survival, biochemical DFS, regional and distant failure. EPIC-26 adherence was 82% at 1yr and 84% at 2yr.
Urinary irritative/obstructive MCID was flat (35.4% vs 33.7%, P=.68); bowel MCID favored SBRT (34.9% vs 43.8%, P=.03). DFS superiority was rejected at a 91-event interim (HR 1.38, 0.91-2.09), with 3yr rates 88.6% vs 92.1% and no adjusted difference (HR 1.40, P=.12).
| Endpoint | SBRT | MH-IMRT | Effect |
|---|---|---|---|
| Biochemical failure | 7.8% | 4.2% | adj HR 1.82 (1.01-3.27), P=.046 |
| Local failure | 1.2% | 1.0% | P=.97 |
| Overall survival | n/a | n/a | P=.65; adj HR 1.15 (0.55-2.41), P=.70 |
Grade 3+4 GU adverse events were lower with SBRT (0.6% vs 2.5%, P=.04), as were any-grade rectal hemorrhage (10.5% vs 17.3%, P=.01) and fatigue (39.2% vs 50.8%, P=.002). Longitudinal bowel scores favored SBRT (LS mean 2.68 [1.02-4.34], P=.002) and urinary incontinence scores likewise (LS mean 2.91 [0.85-4.97], P=.006).
PACE-B and HYPO-RT-PC established that 5-fraction prostate SBRT is tolerable and non-inferior on biochemical control; this trial asked the harder superiority question and lost it, and adds a rectal-manipulation stratification neither predecessor used, which balanced spacer use across arms rather than leaving it a center-level confounder.
The biochemical failure signal, the one result that argues against SBRT, sits on 3-year rates with a CI whose lower bound touches unity (adj HR 1.82, 1.01-3.27) and cannot be separated from the higher benign PSA bounce rate after SBRT, which the trial was not designed to distinguish from true failure. Local, regional and distant failure events were too few to analyze (8 vs 7, 4 vs 2, 4 vs 4), so the mechanism behind the PSA gap is unobserved.
The authors attribute the PSA-control gap to a possible lower biologically effective dose and smaller SBRT margins, the same two choices that plausibly produced the bowel benefit. If that trade is real, it is tunable: focal boost to the dominant intraprostatic lesion was explicitly excluded here and is where the next version of this question belongs.
CONSORT flow
Randomised phase 3, prespecified coprimary endpoints, ITT: the DFS superiority hypothesis was rejected and biochemical failure ran higher with SBRT, contesting the assumption 5 fractions cost nothing.
- Whether benign PSA bounce explains the biochemical failure gap
- Does focal boost to the dominant intraprostatic lesion close it recruiting Image-guided Focal Dose Escalation- Primary pc Treated With Primary External Beam Hypofract.Stereotactic rt Phase NAn=374 · primary completion 2025-08 · randomised focal dose escalation, SBRT vs IMRT/IGRTn=186 · primary completion 2032-08 · randomised DIL boost vs whole-gland boost in SBRTrecruiting Phase III Adaptive Adaptive Stereostactic Body Radiotherapy (SBRT) With Dose Escalation for High-Risk Prostate Cancer Phase NAn=390 · primary completion 2033-04 · DIL dose-escalated SBRT vs mod hypofx, high risk
- Late GI/GU toxicity and QoL beyond 2 years n=68 · primary completion 2025-10 · 5y cumulative GI/GU/sexual toxicity, MR-linac SBRTactive Germline DNA-Based Radiosensitivity Biomarker Influence on Toxicity Following Prostate Radiotherapy, GARUDA Trial Phase NAn=208 · primary completion 2027-12 · long-term physician-scored GU toxicity after SBRT
📚 Sources · 📄 1 paper
Abstract
Moderately hypofractionated partial breast reirradiation
ForIsolated IBTR after BCS + WBI, T1-2, unifocal, ≥48mo interval, age ≥50
TL;DR40Gy/15fx PBI re-RT after second lumpectomy: 3yr LR-FS, DR-FS and OS all 86%, no grade 3+ late events (N=11).
The transferable read is the fractionation, not the outcome: 40 Gy / 2.67 Gy daily PBI met every OAR objective with heart Dmean 1.44 Gy and ipsilateral lung V16Gy 7.74%, so a once-daily 15-fraction re-RT can be planned inside standard constraints. That removes the BID-visit burden that limits RTOG 1014 uptake, though no plan sum with the first WBI course was possible.
For the woman with an isolated T1-2 IBTR ≥4 years after BCS plus WBI who wants to keep her breast, this supports offering once-daily hypofractionated PBI re-RT rather than only BID schedules; it says nothing about multifocal, T4, or short-interval recurrence, where mastectomy remains the comparator. The longer read
The transferable detail is the plan, not the outcome: 40 Gy / 2.67 Gy daily PBI with direct-planning IMRT achieved heart Dmean 1.44 Gy and ipsilateral lung V16Gy 7.74%, well inside objectives, in previously whole-breast-irradiated tissue. That makes a once-daily 15-fraction re-RT schedule planable without the BID burden, though no plan sum with the first course was possible.
Repeat lumpectomy rather than salvage mastectomy held in 9 of 11 at 3 years, with recurrences at 11 and 15 months. Selection was tight: unifocal T1-2 on triple imaging, ≥48 months from primary treatment. SLNB was attempted in 8 and failed to identify a node in 2, which is worth flagging when planning axillary staging at second conservation.
16 details 2 trials watching
Retrospective review of a departmental re-RT database, single institution (Porto), treated 2017-2021. Thirteen identified, two excluded (different fractionation; T4 treated with WBI), leaving N = 11. Median follow-up 41 months (27-62), Kaplan-Meier estimates with two-sided log-rank comparisons.
Isolated ipsilateral breast tumor recurrence after BCS plus whole-breast irradiation, all T1-2, clinically node negative, no metastatic disease before second BCS. Inclusion required age ≥ 50, unifocal disease on ultrasound, mammography and MRI, size < 2-3 cm, and an interval of ≥ 48 months from primary treatment. Median age at recurrence 63 (41-81), ECOG 0-1 in all.
Initial course was whole-breast irradiation at 2 Gy/fraction in all 11, with a 10 Gy / 5 fraction boost in 2. Re-RT was partial breast, 40 Gy at 2.67 Gy daily, direct-planning IMRT, supine, without DIBH. Median interval between courses 107 months (27-239).
No registered primary. LR-FS, DR-FS and OS by Kaplan-Meier from the day of re-RT completion, with adverse events graded by CTCAE v5.0 (acute < 90 days, late > 90 days) and cosmesis by the Harris scale.
At 3 years, 9/11 free from local recurrence, 10/11 from distant recurrence, 9/11 alive, each 86%. Two local recurrences, at 11 and 15 months. TAM-stratified LR-FS was 100% low risk, 80% intermediate, 100% in the single high-risk patient; the OS difference between low and intermediate risk was not significant (p = 0.75).
| Parameter | Objective | Achieved mean (range) |
|---|---|---|
| PTV V95% | > 98% | 98.36 (98-99.45) |
| PTV V107% | < 2% | 0 (0) |
| Ipsi lung V16Gy | < 15% | 7.74 (1.41-14.98) |
| Ipsi lung V8Gy | < 35% | 13.22 (2.78-34.58) |
| Heart Dmean | < 3.2 Gy | 1.44 (0.48-3.09) |
| Heart V16Gy | < 5% | 1.53 (0-4.89) |
| Contra lung V4Gy | < 10% | 1.09 (0-8.74) |
No grade 3 or higher late reactions. Acute events were skin-limited, most commonly grade 1-2 dermatitis (8 grade 1 erythema, 2 grade 1 pigmentation, 1 pruritus). At 1 year, grade 1 fibrosis in 9 and grade 1-2 oedema in 5, breast pain grade 1 in 2. No cardiopulmonary events, no rib fractures. Cosmesis good in 6, fair in 2, poor in 3.
RTOG 1014 (45 Gy / 1.5 Gy BID, 3D-CRT, n = 66) reported 7% late grade 3 and no grade 4-5 at 5.5 years; Janssen 2018 (n = 83, 45 Gy / 1.8 Gy daily) reported a 15% LR rate at 35 months. Brachytherapy series sit at 94-100% third-IBTR-free survival with 8-11% grade 3-4 complications. This cohort's toxicity is at or below all of them, on a fraction of the patient numbers and follow-up.
The first course's dose distribution was unavailable, so no composite plan sum could be produced and cumulative OAR dose stays uncharacterized, which is the number that actually gates re-RT safety. Cosmesis was scored unblinded by the treating radiation oncologist, and the reported confidence intervals (46-62%, 52-65%, 47-63%) do not contain their own 86% point estimates as printed.
The contribution is schedule feasibility, not efficacy: a once-daily 15-fraction re-RT plan met every published constraint with wide margin, which is what a department needs before abandoning BID. Whether 40 Gy in 15 fractions matches 45 Gy BID for in-breast control remains untested; two events in 11 patients cannot answer it.
Retrospective single-arm series, N=11, 2 events, median f/u 41 months. No comparator vs mastectomy or vs the established BID re-RT schedules.
- Does 40 Gy/15fx match 45 Gy BID for in-breast control? n=30 · primary completion 2025-08 · same 40Gy/15fx re-RT schedule, skin toxicityn=171 · primary completion 2027-06 · rPBI 5fx after prior WBI, in-breast recurrence
- Late fibrosis beyond 4 years in the overlap volume
- Cumulative OAR dose without a first-course plan sum
📚 Sources · 📄 1 paper
NSABP B-35 margin-width analysis
ForPostmenopausal HR+ DCIS after lumpectomy, WBI and 5yr endocrine therapy
5.6% vs 4.0%
1mm cutoff, absolute difference 1.6%; 2mm cutoff 5.3% vs 3.8%
TL;DR10yr IBTR 5.6% vs 4.0% at 1mm cutoff (abs diff 1.6%), 5.3% vs 3.8% at 2mm (abs diff 1.5%).
Reported via The ASCO Post →
The RT-relevant read is that every patient here got whole-breast irradiation plus 5 years of endocrine therapy, so the 1.5% to 1.6% margin penalty is the residual after full adjuvant treatment. That gates transfer: it says nothing about a close margin when RT is omitted or refused, which is where the margin question actually bites.
In a postmenopausal woman with HR+ DCIS whose lumpectomy margin is under 2mm and who will complete whole-breast RT plus 5yr endocrine therapy, this argues re-excision buys little; it does not extend to premenopausal, HR-negative, or RT-omitted pts. The longer read
Every patient here received whole-breast irradiation with an optional boost plus 5yr endocrine therapy, so 1.5% to 1.6% is the residual margin effect after full adjuvant treatment. Boost use by margin group is not reported in source, which matters: it determines whether a close margin was tolerated or quietly compensated.
A margin under 2mm carried a 10yr IBTR of 5.3% vs 3.8% for ≥2mm, an absolute 1.5% penalty, in the largest randomised-trial population yet examined. That directly gates the return-to-theatre decision, though margin width was not randomised and the narrow group is enriched for disease that could not be cleared.
9 details 1 trial watching
Secondary margin-width analysis of NRG Oncology/NSABP B-35, a double-blind randomised trial of tamoxifen vs anastrozole that enrolled 3,104 postmenopausal women 2003-2006. Because local recurrence did not differ between the two endocrine arms, the arms were pooled and margin width analysed across the whole population. Margin data were collected prospectively by participating pathologists.
Postmenopausal women with hormone receptor-positive DCIS treated with lumpectomy. Two overlapping analysis cohorts: n=2,707 with margins classifiable as <1mm (close/indefinite) vs ≥1mm, and n=2,546 with the closest margin measured, permitting a <2mm vs ≥2mm cutoff.
All patients received whole-breast irradiation with an optional boost. Dose, fractionation and boost uptake are not reported in the source, so the RT exposure behind these recurrence rates cannot be characterised beyond "whole breast, boost optional".
Primary endpoint of interest: cumulative incidence of ipsilateral breast tumor recurrence at 10 years, analysed at both the 1mm and 2mm cutoffs. A secondary analysis of all breast cancer events, including contralateral disease, was also performed.
The prevailing 2mm threshold rests largely on the SSO/ASTRO/ASCO DCIS consensus, whose meta-analytic base drew heavily on series with variable and often absent adjuvant therapy. This analysis puts the same question to a uniformly irradiated, uniformly endocrine-treated randomised trial population, which is why the residual margin effect looks so much smaller.
Margin width was not randomised, and patients re-excised on trial carry their final margin, so the narrow-margin group is enriched for disease that could not be cleared. Source reports no hazard ratios, confidence intervals or event counts, and no multivariable adjustment for grade, size, age or boost use.
The claim is that a 1.5% to 1.6% absolute 10-year difference does not justify routine reoperation, which is a value judgment about the trade against anxiety, cosmesis and cost rather than a statistical one. The difference was statistically significant at the 1mm cutoff, so the argument turns on clinical meaningfulness, and a patient who weighs local recurrence heavily could reasonably read the same number differently.
| Cutoff | Narrow margin | Wider margin | Absolute difference |
|---|---|---|---|
| 1 mm | 5.6% (n=502) | 4.0% (n=2,205) | 1.6% |
| 2 mm | 5.3% (n=879) | 3.8% (n=1,667) | 1.5% |
Prospectively collected margin data from a large RCT population directly contests the 2mm re-excision threshold, but the margin comparison itself is non-randomised and abstract-only.
- Does the finding hold when whole-breast RT is omitted? not yet Assessment of Biosignature Classification of DCIS for RadioTherapy Benefit Post Lumpectomy (ABCD RT) Phase 3n=5270 · primary completion 2039-07 · randomises RT omission in biosignature-low DCIS
- Boost use and dose by margin group
- Applicability to premenopausal or HR-negative DCIS
📚 Sources · 📄 1 paper
Abstract
Cardiac Risk After Heart-Sparing Breast Radiotherapy
ForLeft-sided breast cancer, 3D-CRT or IMRT, 2008-2018
TL;DRMax LAD ≥12 Gy EQD2: sHR 1.81 (1.04-3.16) for cardiac events; mean heart dose ≥2 Gy null (P=.99), 2223 left-sided pts.
The number that reaches the planning system is the physical-dose translation: 12 Gy EQD2 max LAD is about 10.5 Gy at 42.5 Gy/16 fx and 7 Gy at 26 Gy/5 fx. Discrimination was weak for both metrics (C index 0.58 vs 0.53), so this argues for adding an LAD max objective and motion management, not for retiring mean heart dose.
In left-sided breast cancer planned with 3D-CRT or IMRT, this supports carrying an LAD max objective alongside the usual heart constraint; it does not extend to right-sided disease, which sat outside the primary analysis. The longer read
The actionable number is the physical-dose translation: 12 Gy EQD2 max LAD is about 10.5 Gy at 42.5 Gy/16 fx and 7 Gy at 26 Gy/5 fx, both checkable at the workstation. Discrimination was weak for both metrics (C index 0.58 vs 0.53), so this adds an LAD max objective and breath-hold rather than retiring the heart constraint.
9 details 4 trials watching
Cross-sectional cohort of 4908 breast cancer pts treated with 3D-CRT or IMRT from 2008 to 2018 at one Canadian tertiary center, 2223 left-sided in the primary analysis. Median follow-up 10.8 years (IQR 8.4-13.1). Dosimetry auto-segmented from planning CT, converted to EQD2; competing-risks (Fine and Gray) regression adjusted for cardiovascular risk factors.
Breast cancer treated with 3-dimensional conformal or intensity-modulated RT, 2008 to 2018, with the primary analysis restricted to left-sided disease. Systemic cardiotoxic exposure (anthracycline, trastuzumab) is not reported in source.
3D-CRT or IMRT across the heart-sparing era; LAD and heart automatically segmented and dose converted to EQD2. The threshold is a max point dose to the LAD, not a mean, and the reference schedules are moderate hypofractionation (42.5 Gy in 16 fx) and ultrahypofractionation (26 Gy in 5 fx).
Adverse cardiac events: MI, or admission / ED visit for unstable angina, arrhythmia, heart failure, pericarditis, myocarditis. Coronary angiography and revascularization captured separately as CAD. Discrimination compared by ROC C index, adjusted association by competing-risks regression.
10-year cumulative incidence of cardiac event or CAD was 5.0% (95% CI 4.1-6.0). Metric-by-metric comparison is in the table above.
| Metric | Max LAD dose | Mean heart dose |
|---|---|---|
| Discrimination (C index) | 0.58 (95% CI 0.52-0.64) | 0.53 (95% CI 0.47-0.60) |
| Adjusted association | ≥12 Gy EQD2: sHR 1.81 (1.04-3.16), P=.04 | ≥2 Gy: not associated, P=.99 |
| Schedule | Physical max LAD dose |
|---|---|
| 42.5 Gy / 16 fx | approx 10.5 Gy |
| 26 Gy / 5 fx | approx 7 Gy |
Current whole-heart constraints descend from population dose-response work on cohorts irradiated when incidental cardiac exposure was far higher (Darby, NEJM 2013), the era in which mean heart dose had usable spread. This is the modern counterpart of those series, and the reversal it reports is what you would expect if heart-sparing planning compressed mean heart dose below its discriminating range. The referenced schedules, 42.5 Gy in 16 fractions and 26 Gy in 5 fractions (FAST-Forward), are current practice, so the dosimetric translation transfers.
The mean heart dose null is hard to separate from restricted range: a 2 Gy dichotomy inside a heart-sparing cohort may not span enough exposure for a gradient to show. The endpoint counts coronary angiography and revascularization, which track ascertainment and access as well as biology. Systemic cardiotoxic exposure is not reported in source, leaving an obvious confounder unaddressed.
The asymmetry that matters is cost: an LAD max objective plus breath-hold usually costs optimization time, not target coverage, so a weak association is enough to justify it, while it would not justify trading away chest wall or nodal coverage. The measurement problem cuts the other way, since a max point dose to a small mobile auto-segmented vessel is among the least reproducible quantities to write into a protocol. Motion management carries the least methodological baggage of the two recommendations: it lowers LAD dose and heart dose together.
Cross-sectional single-center cohort with a cut point derived in the same data; C index 0.58 barely above chance and its interval overlaps mean heart dose's.
- External validation of the 12 Gy EQD2 LAD cut point
- Whether LAD-directed planning prospectively lowers cardiac events n=400 · primary completion 2026-04 · DIBH vs free-breathing cardiac dose, paired plansn=750 · primary completion 2027-12 · IMPT vs IMRT/VMAT, cardiac toxicity endpoint
- Generalizability to regional nodal irradiation and 5-fraction schedules active Postmastecomy Internal Mammary Nodal Irradiation for High-risk Breast Cancer Patients Phase 3n=2400 · primary completion 2025-11 · phase 3 IMN irradiation vs none, n=2400recruiting Ultra-Hypofractionated vs. Hypofractionated Radiation for Node-Positive Breast Cancer Phase 2n=220 · primary completion 2034-04 · randomised ultra-hypofx vs hypofx with nodal RT
📚 Sources · 📄 1 paper
Abstract
STELLAR NCT02533271
ForDistal/middle-third rectal adeno, cT3-4 and/or cN+, age 18-70, ECOG 0-1
64.5% v 62.3%
HR 0.883, 1-sided 95% CI to 1.11, P<.001 for noninferiority
TL;DR3yr DFS 64.5% v 62.3% (HR 0.883, NI margin 1.43, P<.001 NI): 5x5Gy then CAPOX non-inferior to 50Gy/25f CRT in LARC.
Every pt got IMRT, unlike RAPIDO, Polish II or PRODIGE 23, and 3yr LRR was 8.4% v 11.0% with 25Gy/5fx to a full elective pelvic CTV, so the short-course arm did not trade local control for convenience. Compliance was the mechanism: 100% completed 5x5Gy with no dose reduction. This supports offering 5x5Gy over 50Gy/25f when the systemic phase is the priority.
In cT3-4 or node-positive mid/low rectal cancer where getting full-dose neoadjuvant chemo delivered is the constraint, this supports 25Gy/5fx followed by CAPOX instead of long-course chemoradiation; it does not extend to upper rectal tumors or pts over 70, both excluded. The longer read
All pts received IMRT with full elective pelvic CTV coverage, unlike RAPIDO, Polish II or PRODIGE 23, and 3yr LRR was 8.4% v 11.0% with 25Gy/5fx. Every TNT pt completed all five fractions with no dose reduction. This supports 5x5Gy over 50Gy/25f without conceding local control.
Moving CAPOX preoperatively raised full-dose preop completion of the systemic phase but cut it the other way on delivery overall, 74.8% v 93.2%. Four preop cycles produced no distant-metastasis benefit (3yr DM 22.8% v 24.7%), unlike the heavier RAPIDO and PRODIGE 23 programs, so cycle number may matter for distant control.
TME at 6-8 weeks after short-course RT plus chemotherapy gave R0 resection in 91.5% v 87.8% (P=.189) and grade III+ complications of 14.0% v 15.7% (P=.625), so the compressed schedule did not degrade the operation. Sustained cCR was higher after TNT (21.8% v 12.3% for pCR plus sustained cCR), enlarging the nonoperative-management pool to 9.4% v 3.4%.
12 details 5 trials watching
Multicenter open-label randomized phase III noninferiority trial, 16 hospitals across 11 provinces of China, accrual August 2015 to August 2018, N=599 randomly assigned 1:1 (TNT 302, CRT 297). Stratified by tumor location, clinical stage and MRF status; median follow-up 35.0 months (range 8.3-63.9).
Age 18-70, ECOG 0-1, rectal adenocarcinoma of the distal or middle third (0-10cm from anal verge), cT3-4 and/or node-positive, no distant metastases, no prior anticancer treatment. Arms were balanced: cT4 15.9% v 12.8%, MRF involvement 56.3% v 56.2%, clinical stage III 85.8% v 83.5%.
TNT arm received 25Gy in 5 fractions over one week; CRT arm 50Gy in 25 fractions over 5 weeks with concurrent capecitabine 825mg/m2 twice daily. All patients received IMRT, a departure from RAPIDO, Polish II and PRODIGE 23. CTV covered mesorectum, presacral space, internal iliac, obturator nodes and ischiorectal fossa; superior border at the sacral promontory, inferior 2-3cm distal to the tumor, external iliacs added only for cT4b; CTV-to-PTV expansion 0.5-1.0cm.
TNT arm: 4 cycles CAPOX (oxaliplatin 130mg/m2 day 1, capecitabine 1,000mg/m2 twice daily days 1-14) starting 7-14 days after radiotherapy, then TME, then 2 further cycles. CRT arm: concurrent capecitabine during radiotherapy, then TME, then 6 cycles CAPOX. Total mesorectal excision was scheduled 6-8 weeks after preoperative treatment in both arms; a watch-and-wait pathway was permitted for clinical complete responders.
Primary: 3-year disease-free survival, noninferiority claimed if the upper bound of the 95% CI of the HR was at or below 1.43 (an 11% absolute margin against an assumed 65% CRT rate). Secondary endpoints were overall survival, metastasis-free survival, locoregional recurrence and surgical complications. Target accrual 600 with at least 194 DFS events for 80% power at one-sided alpha 0.05.
Acute grade III-V toxicity during preoperative treatment was 26.5% with TNT versus 12.6% with CRT (P<.001), driven almost entirely by hematologic events (grade 3-4 15.8% v 2.0%, P<.001) rather than by anything the radiotherapy added. Radiotherapy delivery itself was cleaner in the short-course arm, with no dose reductions at all, and grade III+ surgical complications were comparable (14.0% v 15.7%, P=.625). Grade III-IV toxicity during adjuvant chemotherapy ran lower after TNT (3.3% v 11.8%, P=.003).
STELLAR is the third randomized trial of short-course radiotherapy plus neoadjuvant chemotherapy against long-course CRT, after Polish II and RAPIDO, with PRODIGE 23 addressing the adjacent question of chemotherapy sequencing around long-course CRT. Its 3-year LRR of 8.4% with TNT sits alongside RAPIDO and PRODIGE 23 (4%-8.3%) and well below Polish II (21%-22%), which enrolled a heavier fixed cT3/cT4 population. Unlike RAPIDO and PRODIGE 23, STELLAR showed no reduction in distant metastasis (3-year DM 22.8% v 24.7%), and its OS advantage mirrors the early Polish II signal that later disappeared at 8 years.
The 11% noninferiority margin is wide, and the authors concede in retrospect that a narrower margin or larger sample would have been defensible given how close the arms proved. Distant metastasis, the endpoint short-course TNT was designed to move, did not separate at all (22.8% v 24.7%), which weakens the mechanistic case for the OS difference. Adjuvant chemotherapy completion also differed between arms (60.0% v 48.3%, P=.009), so postoperative treatment intensity is not held constant across the comparison.
The defensible read is the primary endpoint: 25Gy in 5 fractions followed by CAPOX delivers the same 3-year DFS and the same locoregional control as 50Gy in 25 fractions, in one week of radiotherapy instead of five. The 11.4-point OS separation is the number that will be quoted and the one least supported, since neither MFS nor LRR moved and the same pattern in Polish II did not survive longer follow-up. What transfers most reliably is the technique: full elective pelvic coverage with IMRT at 5x5Gy, delivered without a single dose reduction.
| Endpoint (3yr) | TNT | CRT | Effect size |
|---|---|---|---|
| DFS (1°) | 64.5% (58.3-70.7) | 62.3% (56.1-68.5) | HR 0.883, 1-sided 95% CI to 1.11, P<.001 NI |
| OS | 86.5% (82.1-90.8) | 75.1% (69.4-80.8) | HR 0.67 (0.46-0.97), P=.033 |
| MFS | 77.1% (71.7-82.6) | 75.3% (70.0-80.7) | HR 0.88 (0.63-1.24), P=.475 |
| LRR | 8.4% (4.6-12.2) | 11.0% (6.5-15.5) | HR 0.80 (0.45-1.44), P=.461 |
| Subgroup | DFS HR (95% CI), P | OS HR (95% CI), P |
|---|---|---|
| cT4 | 0.621 (0.328 to 1.177), .144 | 0.362 (0.152 to 0.859), .021 |
| Distance to anal verge ≤5cm | 0.706 (0.485 to 1.028), .070 | 0.540 (0.318 to 0.916), .022 |
| cT2-3 | 0.916 (0.674 to 1.245), .575 | 0.752 (0.493 to 1.149), .187 |
| Distance >5cm | 1.120 (0.744 to 1.687), .587 | 0.808 (0.468 to 1.394), .443 |
CONSORT flow
Prespecified noninferiority met on 3yr DFS with adequate accrual, but open-label, 35mo follow-up only, and the OS gain is a secondary endpoint unsupported by MFS or LRR.
- Does the 3yr OS advantage survive 5-10 year follow-up active Short RT Versus RCT,Followed by Chemo.and Organ Preservation for Interm and High-risk Rectal Cancer Patients Phase 3n=702 · primary completion 2023-09 · ACO/ARO/AIO-18.1: 5x5Gy vs 54Gy CRT, n=702
- Optimal number of preoperative chemotherapy cycles with short-course RT n=42 · primary completion 2026-11 · 5x5Gy then 9 cycles mFOLFOX6, CR rate 1° EPactive Preoperative Sequential Short-course Radiation Therapy and FOLFOX for Locally Advanced Rectal Cancer Phase 2n=364 · primary completion 2028-12 · SCRT then 4 cycles FOLFOX vs CRT, n=364n=608 · primary completion 2029-12 · phase 3 SCRT+CAPOX vs SCRT+CAPOXIRI, n=608
- Late toxicity and quality of life, not yet reported recruiting Short Course Radiation Therapy and Combination Chemotherapy for the Treatment of Stage II-III Rectal Cancer Phase 1n=25 · primary completion 2026-10 · SCRT then chemo with QoL assessment as endpoint
📚 Sources · 📄 1 paper
Abstract
TNTCRT NCT03177382
ForHigh-risk stage II/III rectal cancer, cT4/cN2/MRF+/EMVI, age ≤70
HR 0.674
95% CI 0.489-0.929, P=.016; 3-year DFS 74.8% v 66.0%
TL;DR3-year DFS 74.8% v 66.0%, HR 0.674, for doublet CAPOX bracketing long-course chemoradiation vs conventional nCRT in high-risk LARC.
RT is fixed in both arms, so the RT read is what intensified chemo does around it: locoregional failure stayed 6.03% v 6.19% and the DFS gain is distant. The pCR jump (26.37% v 9.80%) is the lever for organ-preservation selection. LCRT dose and fractionation are not reported in source text.
In MRI-defined high-risk stage II/III rectal cancer at or under age 70, this supports doublet CAPOX bracketing long-course chemoradiation over nCRT plus adjuvant chemo; it does not extend to pts over 70 or to short-course RT based TNT. The longer read
RT is identical in both arms, so the read is what intensified chemo does around a fixed LCRT backbone: locoregional failure held at 6.03% v 6.19%, and the DFS gain is distant. Dose, fractionation and target volume are not reported in source text.
The same doublet moved from postoperative to preoperative, with oxaliplatin added concurrent to RT. Grade ≥3 toxicity front-loads into the neoadjuvant phase (27.59% v 8.56%) but whole-course severe toxicity is comparable, so the decision this moves is sequencing, not drug choice.
Intensification did not degrade operability: major postoperative complications 3.98% v 2.94%, and roughly 87% v 90% reached total mesorectal excision. pCR 26.37% v 9.80% widens the pool for a nonoperative discussion, though watch-and-wait was not tested here.
8 details 5 trials watching
Multicenter randomized phase III, N=458, accrual June 6, 2017 to December 27, 2023, median follow-up 51 months. Primary endpoint: DFS. Blinding is not reported and the two regimens are not maskable.
Stage II/III LARC aged 18 to 70 with at least one MRI high-risk feature (cT4a-b, cN2, mesorectal fascia involvement, or cT3c-d with EMVI). Baseline burden was heavy: cT4 47.82%, cN2 75.98%, threatened MRF 70.96%, EMVI 54.80%.
Experimental: one cycle induction CAPOX, LCRT with two cycles concurrent CAPOX, three cycles consolidation CAPOX, then surgery, so all cytotoxic therapy precedes resection. Control: LCRT with concurrent capecitabine, surgery, then six cycles adjuvant CAPOX at 4 to 8 weeks.
Long-course RT in both arms, so RT is the fixed element and the randomized variable is chemotherapy timing plus oxaliplatin exposure. Dose, fractionation, technique and target volume are not reported in the source text, nor is whether concurrent doublet chemotherapy altered RT delivery.
Primary: DFS. Secondary results reported here: MFS, pCR, locoregional failure, overall survival, grade ≥3 adverse events, major postoperative complications.
Primary endpoint met, with MFS moving in step and pCR strongly favoring the experimental arm, while locoregional failure and 3-year OS did not separate. See the efficacy table.
| Endpoint | Doublet-LC TNT | nCRT | Effect size |
|---|---|---|---|
| 3-year DFS (primary) | 74.8% | 66.0% | HR 0.674 (0.489-0.929), P=.016 |
| 3-year MFS | 77.7% | 67.6% | HR 0.655 (0.469-0.915), P=.013 |
| pCR | 26.37% | 9.80% | P<.001 |
| Locoregional failure | 6.03% | 6.19% | P=.943 |
| 3-year OS | 90.2% | 87.5% | P=.167 |
| Measure | Doublet-LC TNT | nCRT | P |
|---|---|---|---|
| Grade ≥3 AE, neoadjuvant phase | 27.59% | 8.56% | <.001 |
| Severe toxicity, entire course | 28.02% | 24.32% | .371 |
| Major postoperative complications | 3.98% | 2.94% | .567 |
Grade ≥3 toxicity front-loads into the neoadjuvant phase with the doublet, but severe toxicity across the entire treatment course and major postoperative complications were comparable. Total mesorectal excision was performed in approximately 87% (TNT) and 90% (nCRT).
Sits alongside RAPIDO, PRODIGE-23 and STELLAR, the trials that established TNT, but keeps long-course chemoradiation as the RT backbone rather than short-course RT. Unlike RAPIDO's longer follow-up, intensification here did not increase locoregional failure.
Control-arm adjuvant CAPOX delivery and completion are not reported, and a TNT advantage partly reflects therapy planned but not received when postoperative chemotherapy under-delivers. Accrual spanned 2017 to 2023, during which TNT became routine, so control-arm contemporaneity drifted. Age was capped at 70.
The gain is distant, not local: MFS tracks DFS while locoregional failure is flat and low in both arms, which says long-course chemoradiation with a fluoropyrimidine is near its local ceiling in this population and the remaining room is systemic. The pCR tripling is the organ-preservation lever, but pCR is a resection-specimen endpoint and this trial did not test nonoperative management.
CONSORT flow
Randomized phase III, primary DFS met at 51mo median f/u, but TNT is already established by RAPIDO, PRODIGE-23, STELLAR; this refines regimen rather than the paradigm.
- Doublet long-course TNT versus short-course RT based TNT head to head active Short-Course Radiotherapy Followed by Neoadjuvant Chemotherapy and Camrelizumab in Locally Advanced Rectal Cancer (UNION) Phase 3n=231 · primary completion 2023-03 · randomised SCRT+CAPOX vs long-course CRT then CAPOX, pCRrecruiting Optimizing Immunotherapy Combined With Neoadjuvant Chemoradiotherapy for Locally Advanced Rectal Cancer Phase 2n=228 · primary completion 2027-06 · SCRT vs long-course CRT with CAPOX in one TNT trialn=608 · primary completion 2029-12 · SCRT plus CAPOX arm, doublet vs triplet consolidation
- Benefit-risk of this intensified regimen above age 70 not yet CGA Guided Ultrafractionated RT and Systemic Treatment in Elderly or Frail Patients with Inoperable Localized CRC Phase 2n=124 · primary completion 2027-11 · CGA-guided RT plus systemic tx, enrols age 70 and over
- Whether the higher pCR converts to durable organ preservation recruiting Organ Preservation First Strategy and Intentional Watch and Wait for MRI Defined Low-risk Rectal Cancer Phase NAn=96 · primary completion 2025-09 · organ-preservation rate after IMRT plus consolidation CapeOX
📚 Sources · 📄 2 papers
Abstract
SIB-CRT vs Standard CRT for LARC (NCT02195141) NCT02195141
ForStage II/III rectal adenocarcinoma, neoadjuvant chemoRT candidates
15.2% vs 18.4%
P=0.695, primary endpoint not met
TL;DR9yr LC 87.1% vs 70.1% (HR 0.40, P=0.038) and OS 74.3% vs 48.9% (HR 0.43) favoring SIB dose escalation.
The boost was 56 Gy to PGTV and 60 Gy to involved lateral nodes on a 50 Gy/25 fx pelvic base, a deliverable prescription with acute G3 toxicity 14.5% vs 19.6%. LC 87.1% vs 70.1% is the mechanistically coherent signal; the OS and MFS separation on 106 pts is not, and gates any move to boost outside a trial.
In stage II/III LARC where perioperative chemotherapy is not planned or not tolerated, this supports testing an integrated boost to gross disease and involved lateral nodes; it gives no read on pts receiving modern TNT, where the subgroup showed no added benefit. The longer read
The prescription is deliverable and specified: 56 Gy to PGTV, 60 Gy to involved lateral nodes, on a 50 Gy/25 fx pelvic base, with acute G3 toxicity 14.5% vs 19.6% and no late toxicity reported. LC 87.1% vs 70.1% is the endpoint a boost can own; treat the OS and MFS separation as hypothesis-generating for a boost trial, not license to escalate off-protocol.
The benefit was confined to pts who did not receive perioperative chemotherapy (9yr DFS 70.8%, HR 0.343, P=.014), with no additional benefit in those who did, and chemo receipt was not randomized. Read as a signal about RT dose in chemotherapy-ineligible pts rather than any argument against systemic intensification.
9 details 5 trials watching
Prospective randomized phase 2, 1:1, N=106 (55 SIB-CRT, 51 CRT), accrued August 2013 to February 2015. Median follow-up 116.6 months, which is the study's real asset.
Stage II/III rectal adenocarcinoma. Radical surgery planned 6 to 8 weeks after chemoradiotherapy. Perioperative chemotherapy was not randomized, and its receipt defines the subgroup that carries the result.
Both arms received 50 Gy/25 fx to the pelvis. The experimental arm added a simultaneous integrated boost of 56 Gy to PGTV and 60 Gy to lateral metastatic nodes where present, so the escalation targets gross primary and involved lateral nodes rather than the elective volume.
Primary: pCR rate. Secondary: DFS, OS, MFS, LC, CSS and toxicity. Every result the conclusion rests on is secondary.
Acute grade 3 toxicity 14.5% (SIB-CRT) vs 19.6% (CRT), primarily radiation dermatitis. Late toxicity is not reported in the source, which matters most for a boost delivered near bowel and for pts followed nearly a decade.
Neoadjuvant dose escalation in LARC has repeatedly raised pCR without translating to survival; this trial reports the mirror image, a null pCR (15.2% vs 18.4%) with survival separation. The result also sits against the TNT era, where systemic intensification rather than RT dose is the current lever, and the chemo-receiving subgroup here showed no additional benefit.
The survival claim is a secondary-endpoint result from 51 vs 55 pts, so a handful of events moves each HR, and no confidence intervals are reported in the source. The driving subgroup is defined by non-randomized chemotherapy receipt, and the higher rate of curative treatment in the SIB arm (89.1% vs 78.4%) is itself a plausible route to the OS difference independent of dose.
A pelvic boost has a defensible mechanism for LC 87.1% vs 70.1% and essentially none for MFS 70.8% vs 47.2%. The authors attribute the distant benefit to intensified control of micrometastases; the simpler reading is that a small trial with a large curative-treatment imbalance produced correlated secondary endpoints.
| Endpoint | SIB-CRT | CRT | Effect |
|---|---|---|---|
| DFS | 70.8% | 47.4% | HR 0.46, P=0.013 |
| OS | 74.3% | 48.9% | HR 0.43, P=0.008 |
| MFS | 70.8% | 47.2% | HR 0.48, P=0.017 |
| LC | 87.1% | 70.1% | HR 0.40, P=0.038 |
| CSS | 77.4% | 57.2% | P=0.027 |
| pCR | 15.2% | 18.4% | P=0.695 |
CONSORT flow
Randomized phase 2, N=106, primary endpoint (pCR) missed; survival gains are secondary endpoints with wide implied precision and a non-randomized chemo subgroup driving them.
- Does SIB add anything on a total neoadjuvant therapy backbone n=37 · primary completion 2026-05 · SIB-SCRT plus CAPOX and PD-1 in high-risk LARCn=156 · primary completion 2026-12 · randomises GTV SIB 58.75 vs 50 Gy/25f for CRrecruiting THeragnostic Utilities for Neoplastic DisEases of the Rectum by MRI Guided Radiotherapy Phase NAn=179 · primary completion 2027-01 · RT dose escalation gated by early regression index
- Late GI and GU toxicity of the boost beyond 9 years active Safety of a Boost (CXB or EBRT) in Combination With Neoadjuvant Chemoradiotherapy for Early Rectal Adenocarcinoma Phase 3n=148 · primary completion 2023-06 · safety endpoint for CXB vs EBRT boost after nCRTrecruiting Standard Dose Versus High Dose of Radiotherapy in Rectal Preservation With Chemo-radiotherapy in Rectal Cancer Patients Phase 3n=162 · primary completion 2026-12 · 62 Gy vs 50.4 Gy phase 3, dose-escalation toxicity
- Whether the curative-treatment rate imbalance explains the OS gap
📚 Sources · 📄 1 paper
Abstract
IROCK RCC SABR contouring guidelines
ForLocalized RCC treated with SABR, incl. IVC thrombus, recurrence, post-RFA
TL;DRFirst international consensus on target delineation for localized RCC SABR: 16 experts, median DSC 0.85 vs consensus, >0.70 in every case.
The two contested target calls are settled: include the entire tumor thrombus and the entire RFA cavity, and these were also the cases with most variation (DSC 0.85 and 0.75; HD 64.60 mm in Case 1). The 5 mm PTV assumes 4DCT, vacuum cushion, IV contrast and daily CBCT, so a center without those shouldn't copy the margin.
In a medically inoperable localized RCC with IVC tumor thrombus or recurrence after RFA, this supports covering the full thrombus or full ablation cavity in the iGTV; it does not settle the dose or fraction number, which the panel left institution-specific. The longer read
The two contested target calls are settled: include the entire tumor thrombus and the entire RFA cavity, the cases with most variation (DSC 0.85 and 0.75). The 5 mm PTV assumes 4DCT, vacuum cushion, IV contrast and daily CBCT, so it does not transfer unchanged to other workflows.
10 details
Contouring consensus: 16 IROCK radiation oncologists contoured 4 CT-only cases; a STAPLE algorithm produced the 95% consensus contour, refined over 2 online meetings (May and June 2024) until 100% agreement on statements.
Panel eligibility: ≥10 RCC SABR cases treated; 14 of 16 had treated ≥10 pts in the prior 12 months. Cases: >10 cm tumor with IVC thrombus, central tumor at the hilum, post-nephrectomy recurrence, post-RFA residual.
iGTV equals ITV since no microscopic-spread margin is added. Most common PTV: uniform 5 mm on iGTV with supine vacuum cushion, 4DCT, IV contrast and daily CBCT. Participants used 1, 3, or 5 fractions; OAR constraints drawn from FASTRACK-II and AQuOS-II protocols.
Overall median DSC 0.85 (range 0.40-0.95), MDA 2.17 mm, HD 9.00 mm; median DSC >0.70 in every case. Greatest variation in Case 1 (superior thrombus extent) and Case 4 (cavity inclusion).
| Case | Scenario | iGTV recommendation |
|---|---|---|
| 1 | Tumor >10 cm with IVC tumor thrombus | Primary tumor + entire tumor thrombus; exclude bland thrombus |
| 2 | Central tumor abutting renal hilum | All visible tumor, account for internal motion; may extend into hilum |
| 3 | Local recurrence post-nephrectomy | All visible gross tumor; surgical clips need not be included |
| 4 | Residual tumor post-RFA | Visible gross recurrence + entire ablation cavity |
| Case | DSC | MDA (mm) | HD (mm) |
|---|---|---|---|
| 1 | 0.85, 0.79-0.85 | 6.69, 5.88-8.79 | 64.60, 64.44-86.40 |
| 2 | 0.90, 0.84-0.93 | 1.55, 1.00-2.09 | 7.92, 5.35-9.98 |
| 3 | 0.91, 0.88-0.93 | 1.42, 1.18-1.89 | 6.18, 6.00-7.12 |
| 4 | 0.75, 0.60-0.79 | 2.50, 2.12-2.99 | 9.00, 9.00-12.39 |
FASTRACK-II established prospective phase II support for RCC SABR; this document standardizes the target and OAR definitions that trial-era protocols left variable. AQuOS-II is prospectively testing whether ipsilateral parenchyma and hilum contours matter for toxicity.
CT-only images; MRI might have reduced variation. Participants did not recontour after consensus, so the post-consensus agreement is assumed rather than measured.
The guideline chooses OAR priority over coverage and accepts heterogeneous target dose, which trades some target coverage for bowel safety. Whether hilum or cortex sparing reduces renal toxicity remains unanswered and is deliberately left optional.
Expert contouring consensus; agreement metrics measure contour overlap, not outcome. Standardizes target definition for an emerging indication; not validated prospectively.
- Does renal hilum or cortex sparing reduce renal toxicity?
- Patterns of failure with the 5 mm PTV margin
- Does MRI-based contouring reduce target variation?
📚 Sources · 📄 1 paper
GÖTEBORG-1 active surveillance, 25-year follow-up
ForScreen-detected very-low/low/intermediate-risk localized PC on AS
TL;DR25-yr PC-specific survival 94% (CI 91-98%) on AS, but 22-yr failure-free survival 68% and treatment-free survival 38%.
RT was the exit for 44 of 488 men, but the paper reports no outcomes by treatment, so the efficacy of delayed RT after AS can't be separated out. Failure kept accruing past 10 yr in every risk group. For a man choosing AS over upfront RT, the trade is decades of monitoring, not a 10-15 yr window.
In a screen-detected very-low or low-risk man, this supports AS as low risk for PC death out to 25 yr. In intermediate-risk disease (24-yr PCSS 85%, 19-yr FFS 55%), it supports discussing upfront definitive therapy as a real alternative. It does not extend to high-risk PC. The longer read
RT was the exit for 44 of 488 men, with no outcomes reported by treatment, so the efficacy of delayed RT can't be judged from this paper. Failure keeps accruing past 10 yr, which matters when counseling a man choosing between AS and upfront RT.
RP was the main exit from AS (141 of 232 discontinuations). Gleason score (HR 3.12) and PSA density (HR 1.78) at diagnosis predicted later failure, which helps identify men who might do better with upfront surgery than with prolonged surveillance.
12 details
Observational AS cohort inside the GÖTEBORG-1 PSA screening trial (1995 to 2014 diagnoses, follow-up to Dec 31, 2023). Data were collected prospectively, but AS was not randomized and followed no predefined protocol. Kaplan-Meier estimates plus a multivariable Cox model for failure.
Of 1052 screen-detected PCs, 494 (47%) were on AS and 488 were included: 251 very-low, 129 low, 108 intermediate risk. High-risk excluded. Median age 66, PSA 4.1 ng/ml, PSA density 0.12.
Treatment-free, failure-free (noncurative PSA relapse, starting HT, metastasis, or PC death), PC-specific, and overall survival, all measured from diagnosis.
RT was the active treatment for 44 men leaving AS, against 141 RP. Post-RT relapse was defined as nadir +2 ng/ml. No dose, technique, or RT-specific outcome is reported.
PCSS 94% at 25 yr against FFS 68% at 22 yr; 14 PC deaths and 81 failures. Gleason score (HR 3.12) and PSA density (HR 1.78) predicted failure.
| Endpoint | 15 yr | 20 yr | 22 yr | 25 yr |
|---|---|---|---|---|
| PC-specific survival | 97% (CI 95-99%) | 95% (CI 93-98%) | n/a | 94% (CI 91-98%) |
| Overall survival | 63% (CI 58-67%) | 46% (CI 41-51%) | n/a | 32% (CI 26-38%) |
| Treatment-free survival | 48% (CI 43-54%) | 43% (CI 37-50%) | 38% (CI 31-46%) | n/a |
| Failure-free survival | 81% (CI 77-85%) | 74% (CI 68-81%) | 68% (CI 60-78%) | n/a |
| Endpoint | Very low (n=251) | Low (n=129) | Intermediate (n=108) |
|---|---|---|---|
| TFS 19 yr | 55% (CI 48-63) | 35% (CI 26-47) | 30% (CI 18-48) |
| FFS 19 yr | 85% | 74% | 55% |
| PCSS 24 yr | 99% (CI 97-100) | 92% (CI 83-100) | 85% (CI 75-95) |
| OS 24 yr | 38% (CI 30-48) | 34% (CI 26-45) | 22% (CI 12-37) |
PC mortality falls in the range of ProtecT (3.4%) and the Toronto cohort (5.7% at 15 yr). It is roughly half of PIVOT (11.4%) and well below SPCG-4, a gap the authors attribute to screen detection versus clinical diagnosis.
Gleason reclassification after 2005 means some low-risk pts here would be intermediate risk today. Failure lumps PC death with untreated low-level PSA relapse. Risk-group differences in PCSS were not formally tested.
Failure hazard stayed roughly constant over time, and nearly half of failures came >10 yr after diagnosis, so there is no safe point to stop monitoring. Failures in Gleason 6 pts show that some Gleason 6 tumors do progress.
Nonrandomized AS cohort with no comparator arm and no predefined surveillance protocol. Pre-MRI sextant selection limits how far the result transfers to contemporary AS.
- Does MRI-based selection and monitoring lower long-term AS failure?
- Is there any safe point to stop AS monitoring?
- How does intermediate-risk AS perform under modern grading?
📚 Sources · 📄 1 paper
POSEIDON
ForPost-RP prostate cancer receiving PORT, median pre-PORT PSA 0.3 ng/mL
HR 0.87
95% CI 0.76–1.01, p=0.06; not met
TL;DRIPD meta-analysis of 6 RCTs: adding HT to PORT did not improve OS (HR 0.87, 95% CI 0.76–1.01, p=0.06); benefit confined to pre-PORT PSA >0.5 ng/mL.
MFS improved (HR 0.79) but never cleared the ICECaP 0.81 surrogate threshold at any pre-PORT PSA, so the bPFS/MFS gains behind GETUG-AFU 16 and RTOG 0534 were not expected to translate to OS. Duration showed no interaction (p=0.17); long-term HT OS benefit on splines appears only at PSA ≥1.6 ng/mL, above most modern early salvage.
In PET-negative BCR after RP heading to early salvage PORT at PSA ≤0.5 ng/mL, this questions adding HT for survival; above 0.5 ng/mL it supports HT, with no OS evidence favoring 24 over 4–6 mo; it does not extend to PSMA PET-positive nodal disease. The longer read
For early salvage PORT at pre-PORT PSA ≤0.5 ng/mL, HT added no OS benefit, so RT alone is a defensible default in PET-negative BCR. Above 0.5 ng/mL the OS HR falls to 0.72 to 0.69; long-term HT OS benefit on splines appears only at PSA ≥1.6 ng/mL.
Duration showed no OS interaction (p=0.17) and prolonging short to long course did not improve OS (HR 0.89), so 4–6 mo carries the supported benefit. MFS gains did not clear the ICECaP threshold, weakening MFS as a basis for systemic intensification with PORT.
14 details 5 trials watching
IPD meta-analysis of six randomised phase 3 trials via the MARCAP consortium (PROSPERO CRD42019134376), one-stage Cox stratified by trial. 6057 pts, median follow-up 9.0y (IQR 7.2–10.7).
Men receiving PORT after radical prostatectomy for recurrent prostate cancer. Median pre-PORT PSA 0.3 ng/mL in the any-HT and short-term sets, 0.5 ng/mL in the long-term set. Race and ethnicity data not available.
Short-term HT 4–6 mo (GETUG-AFU 16, NRG/RTOG 0534, RADICALS-HD two-way and three-way), predominantly GnRH agonist. Long-term HT 24 mo (RADICALS three-way, RTOG 9601); RTOG 9601 used high-dose bicalutamide monotherapy.
Primary: overall survival. Secondary: MFS, event-free survival, biochemical recurrence; prespecified interaction tests for pre-PORT PSA and HT duration.
No OS benefit overall (HR 0.87, p=0.06) despite MFS gain (HR 0.79, p<0.001). OS benefit limited to pre-PORT PSA >0.5 ng/mL (interaction p=0.02), with NNT 22 at 0.51–1.00 and 12 at >1.00 ng/mL.
| Comparison | N | OS HR (95% CI) | MFS HR (95% CI) |
|---|---|---|---|
| Any HT + PORT vs PORT | 5026 | 0.87 (0.76–1.01), p=0.06 | 0.79 (0.70–0.89), p<0.001 |
| Short-term HT (4–6 mo) | 3938 | 0.93 (0.77–1.11) | 0.82 (0.71–0.95) |
| Long-term HT (24 mo) | 1088 | 0.79 (0.63–1.00), p=0.049 | 0.74 (0.60–0.91), p=0.004 |
| Short → long prolongation | 1523 | 0.89 (0.68–1.16), p=0.37 | 0.76 (0.61–0.95), p=0.02 |
| Pre-PORT PSA (ng/mL) | OS HR (95% CI) | 10y OS PORT vs PORT+HT | 10y NNT (death) |
|---|---|---|---|
| ≤0.20 | 1.14 (0.83–1.57) | 89.9% vs 87.4% | negative |
| 0.21–0.50 | 0.94 (0.74–1.19) | 84.9% vs 84.5% | negative |
| 0.51–1.00 | 0.72 (0.54–0.96) | 76.4% vs 80.9% | 22 |
| >1.00 | 0.69 (0.48–0.98) | 72.4% vs 80.5% | 12 |
GETUG-AFU 16 and RTOG 0534 established HT with salvage RT on biochemical endpoints; per the ASCO Post write-up only RTOG 9601, a late-salvage trial, had shown an OS benefit. POSEIDON pools these trials and finds the OS signal tracks pre-PORT PSA rather than HT duration.
Duration comparison is confounded: long-term HT trials enrolled higher-PSA, higher-risk pathology. The PSA interaction is model-dependent (continuous PSA: one-stage p=0.19, two-stage p=0.04) and no multiplicity correction was applied. RT dose and field detail not reported in source excerpt.
The trial-level MFS gains held but did not clear the ICECaP surrogate threshold, so the historical case for routine HT with low-PSA salvage rests on endpoints that do not predict OS here. Short-term HT may suffice where HT is used; NRG GU006 (PAM50, apalutamide) tests biomarker selection.
Pooled randomised IPD with prespecified OS primary not met, undercutting routine HT with low-PSA PORT. The PSA >0.5 benefit rests on subgroup interaction, not a primary comparison.
- Does PSMA PET staging change which pts benefit from HT with PORT?
- Can a genomic classifier outperform pre-PORT PSA for selecting HT?
- Does ARSI-based short-term HT change the OS read? active Radiation Therapy With or Without Apalutamide in Treating Patients With Recurrent Prostate Cancer, the BALANCE Trial Phase 2n=298 · primary completion 2025-03 · ph2 SRT ± apalutamide, placebo-controlled, post-RPn=586 · primary completion 2026-11 · ph3 apalutamide added to ADT + RT, pN+ post-RPactive Combined Apalutamide, Radiotherapy, and LHRH Agonist in Prostate Cancer Patients After Prostatectomy Phase 3n=490 · primary completion 2028-09 · ph3 apalutamide + SRT + LHRHa vs SRT + LHRHa post-RPactive A Study of Adding Apalutamide to Radiotherapy and LHRH Agonist in High-Risk Patients With Hormone-Sensitive Prostate Cancer Phase 3n=691 · primary completion 2029-08 · ph3 apalutamide + RT + LHRHa post-RP, PSMA-PET 1° EPrecruiting Treating Prostate Cancer That Has Come Back After Surgery With Apalutamide and Targeted Radiation Based on PET Imaging Phase 3n=804 · primary completion 2032-12 · ph3 apalutamide+abiraterone added to SRT + short ADT
📚 Sources · 📄 2 papers
Abstract
Dose-escalated RT for MIBC (retrospective)
ForMIBC T2-3, M0 (node+ allowed), post-TURBT curative RT ± concurrent chemo
TL;DR2y invasive local recurrence 5.5% vs 27.5% with SIB dose escalation in MIBC TMT (adjusted SHR 0.20, p=0.035); no OS, MFS or G2+ toxicity difference.
Pattern of failure is the RT read: standard-dose invasive failures sat at the original tumour site (14 within vs 2 outside), and the escalated cohort had 1 invasive failure inside the boost. A 60Gy/20fx or 70Gy/32fx SIB to the primary on daily CBCT carried no G2+ GU/GI cost, which supports testing primary-tumour escalation in TMT.
In a unifocal MIBC TMT candidate without hydronephrosis, this supports a primary-tumour SIB as a trial-worthy option rather than routine practice; it does not extend to multifocal disease, which the escalated cohort never included. The longer read
Standard-dose invasive failures clustered at the original tumour site (14 within vs 2 outside), the dose-limited failure pattern a primary boost targets. The SIB (up to 60Gy/20fx or 70Gy/32fx) on daily CBCT added no G2+ GU/GI toxicity at 23 mo median f/u, so the open question is late effects rather than deliverability.
12 details 1 trial watching
Multicentre retrospective cohort from 3 centres, March 2015 to May 2025. N=107: 39 dose-escalated vs 68 standard. Median follow-up 23 mo (range 3-104).
Curative-intent MIBC after TURBT, RT with or without concurrent chemo; node-positive allowed if M0. Metastatic or palliative-intent pts excluded. 51% received no chemo, mostly for poor PS or comorbidity.
Standard: 55Gy/20fx or 64Gy/32fx whole bladder. Escalation: SIB up to 60Gy/20fx or 70Gy/32fx to the primary lesion. Empty-bladder CT sim, daily CBCT, MRI/FDG PET fusion in select pts.
2-year local control for invasive and non-invasive disease, metastasis-free survival, OS, bladder preservation and toxicity. Invasive recurrence analysed by Fine-Gray competing-risk models.
Invasive recurrence was the only endpoint that separated (adjusted SHR 0.20, p=0.035); non-invasive recurrence, metastasis and OS did not differ. Full arm values in the table.
| Endpoint | Escalated (n=39) | Standard (n=68) | Effect |
|---|---|---|---|
| 2y invasive local recurrence | 5.5% | 27.5% | SHR 0.20 (0.05-0.89), p=0.035 (MVA, T stage) |
| 2y non-invasive recurrence | 6.7% | 9.9% | SHR 0.88 (0.23-3.33); MVA p=0.79 |
| 2y metastasis | 21.1% | 32.3% | MVA p=0.75 |
| 2y OS | 71.1% | 64.4% | p=0.5 |
| G2+ GU toxicity | 17.9% | 22.1% | p=0.8 |
| G2+ GI toxicity | 5.1% | 7.4% | p=0.9 |
| Cohort / site | Invasive | Non-invasive |
|---|---|---|
| Escalated, within boost field | 1 | 0 |
| Escalated, outside boost field | 1 | 3 |
| Standard, within original tumour site | 14 | 2 |
| Standard, outside original tumour site | 2 | 5 |
G2+ GU 17.9% vs 22.1% and G2+ GI 5.1% vs 7.4% (escalated vs standard), no difference (p=0.8, p=0.9). G3 toxicity only in 2 standard-dose pts; no early cessation.
BC2001 and BCON built modern TMT on radiosensitisation of whole-bladder RT, not on dose to the primary. RAIDER tested tumour-focused adaptive escalation prospectively; this series adds a routine-practice, CBCT-era hypofractionated experience in the same direction.
Asymmetric outcome ascertainment: 3 standard-arm recurrences were imaging-only and presumed invasive, while every escalated recurrence was cystoscopy-confirmed. Chemo use (56% vs 44%) and hypofractionation (97% vs 87%) also favoured the escalated cohort, and f/u starts at 3 mo, short for late bladder toxicity.
The in-field failure pattern in the standard cohort gives escalation a mechanistic rationale; the magnitude is not trustworthy given selection. Bladder preservation was high in both groups partly because relapsed pts were unfit for cystectomy, so it conflates control with fitness.
Retrospective, non-randomised; escalated cohort selected (all unifocal, less hydronephrosis). Few invasive events (2 vs 16), adjusted for T stage only, so dose cannot be separated from selection.
- Does SIB primary-tumour escalation reduce invasive recurrence in a randomised TMT trial?
- Is the benefit preserved in multifocal MIBC?
- Late GU toxicity beyond 2 years with a 60Gy/20fx or 70Gy/32fx boost? recruiting Hypofractionated IMRT With Concurrent Chemotherapy in Muscle-invasive Bladder Cancer (HIRACUM) Phase NAn=53 · primary completion 2026-12 · MIBC chemo-hypo-IMRT 56-64Gy/20fx, toxicity + QoL
📚 Sources · 📄 1 paper
Proactive immune cell sparing SBRT (NCT04273893) NCT04273893
PREPRINTnot peer-reviewed
ForEarly-stage NSCLC, inoperable or declining surgery, SBRT without systemic therapy
13.4% (5.3%)
95% CI 2.8 to 24.0; p = 0.01
TL;DRImmune-sparing lung SBRT planning cut ALC loss: overall improvement 13.4% (95% CI 2.8-24.0), G3 lymphopenia 0% vs 15.4%; survival trend unpowered.
The dosimetric lever is low-dose spill, not the target: V5 to thoracic spine fell 87% and LN stations 58% with lung V5 down only 8%, all within RTOG 0813/0915 criteria. Benefit concentrated in central tumors (29.5% ALC gain) and was absent for peripheral PTV <20cc, so arc and beam-angle choices for central SBRT are where this plan change applies.
In a central early-stage NSCLC going to 5-fx SBRT without systemic therapy, this supports treating heart, great vessels, thoracic spine and LN stations as low-dose avoidance structures; it does not change planning for small peripheral PTVs under 20cc or establish a survival gain. The longer read
The lever is low-dose spill, not target coverage: thoracic spine V5 fell 87% and LN-station V5 58% with lung V5 down only 8%, inside RTOG 0813/0915 criteria. Gains concentrated in central tumors (29.5% ALC improvement) and vanished for peripheral PTV <20cc, so beam and arc choices for central SBRT are where this applies.
16 details
Randomized phase II, 1:1, stratified by tumor location, permuted blocks, not masked. Enrolled Feb 2020 to Apr 2023; 55 randomized, 51 analyzed (25 vs 26). Survival and subgroup analyses were unplanned and exploratory.
Early-stage NSCLC (AJCC v8), ECOG 0-2, unable or unwilling to undergo surgery; recurrent NSCLC eligible. Excluded RT within 2 yr and systemic therapy within 1 yr prior or 6 mo after. Median age 74 both arms.
45-60 Gy in 5 fx (majority 60 Gy/5), IMRT or VMAT, 4DCT ITV plus 5mm radial / 8mm sup-inf PTV margin. Optimized plans met standard RTOG 0813/0915 criteria while minimizing dose to heart, great vessels, thoracic spine and lymph-node-stations, contoured to a 40 cGy/fx low-dose envelope.
Primary: in vivo lymphocyte depletion at end of treatment, 4 wk and 6 mo; safety/toxicity (co-primary). Algorithm performance reported separately. OS and EFS descriptive only.
Central tumors drove the effect (29.5% overall ALC improvement, p=0.004); peripheral PTV <20cc showed no difference. G3 lymphopenia 0% vs 15.4% (p=0.04).
| Timepoint | Optimized | Standard | Between-group diff |
|---|---|---|---|
| End of SBRT | -16% | -31% | 15.1% (3.7-26.5), p=0.01 |
| 4 weeks | -22% | -34% | 12.3% (0.2-24.5), p=0.05 |
| 6 months | -16% | -26% | 10.4% (-4.7-25.5), p=0.17 |
| Population · endpoint | Optimized | Standard | p |
|---|---|---|---|
| All pts · OS | 82.1% | 65.1% | 0.23 |
| All pts · EFS | 62.3% | 56.7% | 0.27 |
| Tx-naive · OS | 93.4% | 69.4% | 0.14 |
| Tx-naive · EFS | 75.0% | 59.8% | 0.10 |
G3 AEs 2 (lung infection) optimized vs 4 standard (dyspnea, hypoxia, lung infection); all recovered. No G2+ pneumonitis or G4+ events in either arm.
Both arms sat inside RTOG 0813/0915 planning criteria, so the comparison isolates immune-OAR avoidance on top of current SBRT constraints. Prior lymphopenia-outcome links in thoracic RT are largely associative; this is a randomized test that planning alone moves ALC.
Arm imbalance in central (36.0% vs 23.1%) and treatment-naive (64.0% vs 88.5%) pts biases the survival comparison. Tx-naive OS reported as 93.4% and 94.1% in different sections. LN V5 OS split is a non-randomized dosimetric stratification.
Establishes feasibility and an ALC effect, not a clinical one. Whether sparing lymphocytes during SBRT translates to EFS/OS, or to better IO response when combined, needs the multi-institutional powered trial the authors call for.
Preprint, small randomized phase II with unmasked lymphocyte surrogate primary; survival analyses unplanned and unpowered. Arm imbalance in central and treatment-naive pts.
- Does lymphocyte-sparing SBRT improve EFS or OS in a powered trial?
- Does immune-sparing planning enhance SBRT plus immunotherapy outcomes?
- Optimal dose limits for thoracic spine and lymph-node-stations
📚 Sources · 📄 1 paper
Abstract
DBCG Skagen Trial 1
ForHigh-risk breast cancer with an indication for locoregional (nodal) radiotherapy
8.0% vs 9.4%
OR 0.84 (95% CI 0.62-1.14), P=.27; within +5pp NI margin
TL;DR3yr lymphedema 8.0% (40Gy/15fx) vs 9.4% (50Gy/25fx), OR 0.84 (0.62-1.14), noninferior; no recurrence or mortality differences at 8yr.
The lymphedema signal that kept 50Gy/25fx alive for nodal volumes does not appear: 8.0% vs 9.4% at 3yr, OR 0.84 (0.62-1.14). Locoregional recurrence HR 0.96 (0.62-1.51) says the shorter course does not trade control for convenience, so 15 fractions becomes defensible when the nodes are in the field.
In high-risk breast cancer needing nodal irradiation, this supports 40Gy/15fx over 50Gy/25fx on both arm morbidity and locoregional control; it does not speak to pts needing a boost regimen or reconstruction subgroups the abstract does not break out. The longer read
The morbidity objection to nodal hypofractionation does not hold: lymphedema 8.0% vs 9.4% at 3yr, OR 0.84 (0.62-1.14), with locoregional recurrence HR 0.96 (0.62-1.51). 40Gy/15fx to the full locoregional volume becomes the defensible default, with SIB and reconstruction still untested here.
Lymphedema is the shared surgical and radiation morbidity after axillary management, and fraction size is now off the list of drivers: 8.0% with 40Gy/15fx vs 9.4% with 50Gy/25fx at 3yr. Counseling about arm morbidity after nodal surgery plus RT should not attribute risk to the shorter course.
8 details 5 trials watching
Phase III noninferiority RCT, 17 centers, accrual 2015-2021. ITT cohort n=2,908 (1,444 at 50Gy, 1,464 at 40Gy). Accrual continued until 3-year lymphedema estimates were reported in 1,012 patients.
High-risk breast cancer with an indication for locoregional radiotherapy, the population where nodal coverage has kept 25 fractions standard in Denmark. Median age 57 (range 23-86).
Standard arm 50Gy/25fx, experimental arm 40Gy/15fx, both delivered to the locoregional volume rather than breast or chest wall alone. That target volume is the whole point: it is where the morbidity concern lives.
Primary: arm lymphedema at 3 years, with an assumed 10% incidence under 50Gy/25fx and noninferiority predefined as maximum 5 percentage points excess. Cancer endpoints (locoregional recurrence, distant recurrence, breast cancer mortality, all-cause mortality) were assessed within 8 years.
Lymphedema 8.0% vs 9.4%, OR 0.84 (0.62-1.14), P=.27, comfortably inside the margin. Cancer-outcome HRs are tabulated above and show no difference by random assignment.
| Endpoint | HR | 95% CI |
|---|---|---|
| Locoregional recurrence | 0.96 | 0.62 to 1.51 |
| Distant recurrence | 1.10 | 0.89 to 1.37 |
| BC mortality | 1.25 | 0.93 to 1.66 |
| All-cause mortality | 1.08 | 0.85 to 1.36 |
The UK hypofractionation programme (START A/B, then FAST-Forward) established 40Gy/15fx and shorter for breast and chest wall, but node-positive patients receiving comprehensive regional coverage were a small fraction, which left the nodal question open. Skagen 1 tests exactly that gap prospectively with morbidity as the primary endpoint.
Median lymphedema follow-up of 4.1 years captures the 3-year endpoint but not the later plateau, and the abstract reports no brachial plexopathy, shoulder, cardiac, or pulmonary late toxicity. The BC mortality HR 1.25 (0.93-1.66) runs the wrong way with a CI that does not exclude harm; the trial was sized for lymphedema, not survival.
The trial removes the specific objection that blocked hypofractionated nodal RT rather than merely adding another positive fractionation result. It does not settle very-long-term arm and shoulder function, nor whether the same holds with a simultaneous integrated boost or in reconstructed chest walls.
CONSORT flow
Phase III, prespecified noninferiority margin met on the morbidity endpoint that blocked nodal hypofractionation, with 8yr recurrence and mortality HRs showing no difference.
- Does 40Gy/15fx hold with a simultaneous integrated boost? active Hypofractionation With Simultaneous Integrated Boost vs. Standard Fractionation in Early Breast Cancer Phase NAn=2324 · primary completion 2019-01 · phase 3 hypofx SIB vs standard fx, n=2324n=132 · primary completion 2026-03 · 40.05Gy/15fx + SIB, 4y fibrosis endpointrecruiting 5 fr Ultrahypofractionated WBI and SIB for Breast Cancer With Unfavorable Characteristics Phase NAn=458 · primary completion 2029-06 · randomised vs 40.05Gy/15fx + 48Gy SIB control arm
- Lymphedema and shoulder function beyond 5 years
- Safety in immediate breast reconstruction n=20 · primary completion 2025-12 · post-surgical complications after RT then immediate reconactive Hypofractionated Regional Nodal Irradiation Clinical Trial for Women With Breast Cancer Phase NAn=137 · primary completion 2026-04 · hypofx RNI cohort stratified by post-mastectomy recon
📚 Sources · 📄 1 paper
Abstract
PACE-B
ForLow-/intermediate-risk localised prostate cancer, definitive RT
64% vs 69% leak-free
diff +5.51% (95% CI -2.70 to +13.72), p=0.19
TL;DR5-yr PROMs: leak-free 64% (164/258) SBRT vs 69% (172/249) CRT, p=0.19; no domain differed significantly.
The transient 2-yr urinary leakage excess after SBRT converged by 5 yr, which is the number that settles the fractionation conversation: 36.25 Gy/5 fx carried no durable continence penalty against 78 Gy/39 fx or 62 Gy/20 fx. Note the irritative/obstructive domain was not collected, so the symptom cluster patients complain of most after SBRT is unmeasured here.
In low-/intermediate-risk localised prostate cancer choosing between five-fraction SBRT and conventional or moderately hypofractionated RT, these 5-yr PROMs support fractionation choice on convenience rather than late continence, sexual, or bowel risk; they do not extend to high-risk disease, nodal treatment, or randomised comparison with prostatectomy. The longer read
The 2-yr urinary leakage excess after 36.25 Gy/5 fx converged by 5 yr, removing the late-toxicity argument for holding a low-/intermediate-risk patient on 78 Gy/39 fx or 62 Gy/20 fx. Caveat for consent: the EPIC-26 irritative/obstructive domain was not collected, so the urgency and flow symptoms patients ask about are unmeasured here.
11 details 4 trials watching
Phase 3 international randomised trial, 1:1 central allocation by ICR-CTSU with permuted blocks, stratified by centre and NCCN risk group. Treatment allocation was open-label. Of 874 randomised, 844 formed the analysis population (SBRT=414, CRT=430), median follow-up 85.7 and 85.6 mo.
Men with low-/intermediate-risk localised prostate cancer. Baseline characteristics balanced; baseline PROM data pooled across arms given equivalent pretreatment function.
SBRT 36.25 Gy in five fractions versus CRT 78 Gy in 39 fractions or 62 Gy in 20 fractions. Image-guidance method was not analysed as a variable, and rectal spacer use is not reported in this analysis.
Primary comparison: SBRT vs CRT at 5 yr for each PROM endpoint, using EPIC-26 urinary incontinence, sexual and bowel domains plus the Vaizey faecal incontinence score at baseline, 1, 2 and 5 yr. Binary outcomes by chi-squared with Wilson 95% CIs; continuous by Mann-Whitney.
All predefined between-group differences were nonsignificant. Sexual domain median score fell from 48.7 (IQR 22.2-77.8) to 26.3 (IQR 16.7-57) for SBRT and 54.2 (IQR 27.8-75.0) to 24.3 (IQR 16.7-52.8) for CRT, p=0.89.
Moderate or big urinary leakage problems reached 6% (15/250) SBRT and 4% (9/244) CRT; bowel problems 5% in both arms. Solid stool incontinence never/rarely in 94% (232/248) SBRT and 90% (217/241) CRT; liquid stool 92% in both.
PACE-B previously showed SBRT non-inferior to conventional and moderately hypofractionated RT for efficacy but with higher cumulative GU adverse events; these PROMs argue that excess did not persist to 5 yr. Against TrueNTH's robotic prostatectomy benchmark at 1 yr (42% leak- and pad-free, 6% of baseline-potent men retaining intercourse-adequate erections), the RT curves sit far better, and PACE-A reported pad use of 4.6% after SBRT versus 46.9% after prostatectomy.
The EPIC-26 irritative/obstructive domain was not included, removing the symptom cluster most often attributed to SBRT, though the authors note no 5-yr difference was seen in prior reporting. There is no untreated control arm, so age-related decline is unseparated from treatment effect, and no analysis by image-guidance method.
The clinically useful claim is narrow and real: five fractions buys convenience without a late functional cost relative to 20 or 39 fractions. The cross-modality framing against surgery is the weaker half, comparing separate cohorts at different timepoints with a shared instrument rather than a randomised contrast.
CONSORT flow
Prespecified 5-yr PROM analysis of a phase 3 RCT; all between-group differences nonsignificant, supporting five-fraction SBRT already in guideline use. Attrition to ~60% limits precision.
- Irritative/obstructive symptom trajectory at 5 yr after prostate SBRT active Stereotactic Body Radiation Therapy or Intensity-Modulated Radiation Therapy in Treating Patients With Stage IIA-B Prostate Cancer Phase 3n=692 · primary completion 2027-12 · phase 3 SBRT vs IMRT with QoL questionnaire endpointrecruiting Is Adaptive SBRT for Prostate vs Image-guided Radiotherapy a True Evolution (ASPIRE) Phase 3n=320 · primary completion 2030-02 · adaptive vs image-guided SBRT, urinary outcomes
- Whether rectal spacer or image-guidance method alters 5-yr PROMs n=179 · primary completion 2027-04 · phase 3 CT- vs MRI-guided SBRT, questionnaire PROMsn=500 · primary completion 2027-12 · SpaceOAR Vue for late GI toxicity in SBRT pts, n=500
- 5-yr PROMs for the TrueNTH prostatectomy cohort
📚 Sources · 📄 1 paper
Abstract
ProtecT (cribriform morphology secondary analysis)
ForPSA-screened clinically localized prostate cancer, cribriform status on diagnostic biopsy
TL;DRSecondary analysis: cribriform-negative disease (87% of reviewed cohort) got no significant 15-yr metastasis reduction from early radical treatment vs monitoring.
Reported via UroToday →
For the RT reader this is a selection question, not a technique one: it asks whether cribriform status identifies the ProtecT subgroup that actually earned the metastasis reduction from radical treatment. RT here was EBRT with 3-6mo neoadjuvant ADT, a dated backbone. No subgroup HRs, CIs or event counts appear in the source excerpt.
In PSA-screened clinically localized disease with cribriform-negative grade group 2 on biopsy, this analysis supports treating long-term metastasis risk as comparable to grade group 1; it says nothing about cribriform-positive pts, where guidelines already discourage surveillance. The longer read
The decision this moves is whether to offer definitive RT at all, not how to deliver it: cribriform-negative grade group 2 showed metastasis risk equivalent to grade group 1 at 15 years. The RT arm was EBRT with 3-6mo neoadjuvant ADT in a pre-MRI, systematic-biopsy cohort, so transferability to current practice is limited. No subgroup effect sizes in source.
Relevant to how neoadjuvant ADT exposure is weighed against a metastasis benefit that this analysis does not find in the 87% cribriform-negative majority. ProtecT's ADT was 3 to 6 months alongside EBRT. The result argues for a biomarker-gated rather than grade-group-gated treatment decision.
Bears on the counselling conversation before radical prostatectomy in grade group 2: cribriform-negative pts carried the same 15-year metastasis risk as grade group 1, supporting surveillance discussion in that stratum. Cribriform-positive disease is untouched by this read, and guidelines already discourage surveillance there.
9 details
Secondary pathological analysis of the ProtecT randomized trial (active monitoring vs radical prostatectomy vs EBRT with neoadjuvant ADT). Central review of biopsy slides retrieved for 712 of 1,643 randomized pts, with both intention-to-treat and per-protocol analyses, the latter accounting for crossover to radical treatment.
PSA-screened men with clinically localized prostate cancer, the original ProtecT eligibility. Slides were regraded under 2019 ISUP criteria rather than the trial-era 2005 criteria; the presenter reports regrading did not change the picture. Age, PSA and revised Gleason score did not differ significantly across arms in the reviewed subset.
The RT arm was external-beam radiotherapy with 3 to 6 months of neoadjuvant ADT. No dose, fractionation or target volume is given in the source. The presenter notes cribriform-positive disease was more prevalent in this arm, attributed to chance since cribriform status was not a randomization characteristic.
Primary: metastases at 15-year median follow-up, analysed by cribriform status. Multivariable Cox modelling was used to compare metastasis risk across grade groups within the cribriform-negative stratum.
Roughly 13% of the reviewed cohort was cribriform-positive. Among the 87% cribriform-negative, early radical treatment produced no statistically significant reduction in 15-year metastases vs active monitoring, in both ITT and per-protocol analyses. Cribriform-negative grade group 2 carried metastasis risk equivalent to grade group 1.
Slides were available for under half the randomized cohort, so the analysis rests on whichever centres have so far returned material. The source excerpt is a video interview that stops mid-presentation and reports no HRs, CIs or event counts, so the size of the null in the cribriform-negative group cannot be judged from it.
The interest here is the inverse of the usual cribriform argument. Rather than showing cribriform-positive pts do badly on surveillance, the useful signal is that cribriform-negative grade group 2 behaves like grade group 1 over 15 years, which is a de-escalation read. Whether the cribriform-positive stratum shows the reciprocal benefit is not in the source excerpt.
Post-hoc subgroup of a non-stratified variable in 712 of 1,643 pts, with a non-significant negative result and no effect sizes in the source.
- Metastasis outcomes in the cribriform-positive stratum on active monitoring
- Whether cribriform status holds as a marker in MRI-targeted biopsy cohorts
- Reproducibility of binary cribriform calls across pathologists
📚 Sources · 📄 1 paper
Abstract
ESTRO Prostate SBRT Consensus Recommendations
TL;DRDelphi: 36.25 Gy/5 fx standard, 100% vote against elective pelvic nodal RT with prostate SBRT outside trial.
PACE-BPACE-CHYPO-RT-PCNRG-GU005hypo-FLAMEMIRAGEPARTIQoL
Two operational lines move practice: elective pelvic nodal RT alongside prostate SBRT is rejected 100% (12 votes) outside a trial, and intra-fraction tracking is only carried by 71% (10 votes) once PTV margin drops below 5 mm, no consensus. Prior BPH surgery is permitted with a median 6-month wait (range 2-12).
In ISUP 2-3, cT1c-cT2c, PSA <20 ng/mL localised prostate cancer, this supports five-fraction SBRT as a standard option without elective pelvic nodal coverage or a rectal spacer; it does not extend to cT3b, ISUP 5, or pts needing nodal irradiation. The longer read
The actionable lines are operational: no elective pelvic nodal RT with prostate SBRT outside a trial (100%, 12 votes), no routine rectal spacer (85%, 11 votes), and intra-fraction tracking only at 71% (10 votes) once PTV margin falls under 5 mm. Standard is 36.25 Gy/5 fx to 95% PTV with 40 Gy to 95% CTV.
15 details 5 trials watching
ESTRO task force literature review, then two Delphi survey rounds with a purposively selected expert panel, refined at ESTRO 2025 in Vienna. Ten multiple-choice questions covered areas of controversy. Consensus was predefined at ≥75% agreement, strong consensus at ≥90%, thresholds borrowed from APCCC.
Panel: eleven radiation oncologists, three medical physicists, one RTT from nine European countries. Voting counts per question ran 12 to 14. Target patient population is localised prostate cancer, with ISUP 2-3, cT1c-cT2c, PSA <20 ng/mL carrying strong consensus for SBRT as standard treatment outside a trial.
Standard is 36.25 Gy in five fractions of 7.25 Gy to 95% of the PTV, with 40 Gy to 95% of the prostate CTV (PACE-B), or 42.7 Gy in seven fractions of 6.1 Gy (HYPO-RT-PC). Prostate is contoured on T2-weighted planning MRI registered to CT; seminal vesicles omitted in low risk, proximal 1 cm included for all in PACE, proximal 2 cm to 30 Gy/5 fx in Gleason 4+3 or NCCN high risk. Rectal, bladder, femoral head, bowel and optional urethra PRV / penile bulb / crura constraints are given for five-fraction schedules only.
ADT per existing international guidelines, independent of the radiation schedule (100%, 13 votes). Intermediate risk: short-term ADT with conventional fractionation improves overall and cancer-specific survival by 7%, with no added benefit beyond roughly four months. High risk: long-term ADT plus RT improves overall and disease-specific survival irrespective of dose escalation.
No efficacy endpoint. The output is a set of recommendations plus per-question panel agreement percentages, so every "result" here is opinion measured against opinion.
The dose recommendation tracks PACE-B rather than splitting the difference with HYPO-RT-PC, whose lower biologically effective dose was still non-inferior, which the authors read as evidence 40 Gy in five fractions may not be needed for everyone. The unresolved counterweight is NRG-GU005, presented in preliminary form at ASTRO 2025: 36.25 Gy in five fractions gave lower side effects but a slightly higher three-year biochemical relapse rate, cause not yet determined. On protons, PARTIQoL found no difference in outcomes or QoL versus IMRT, with pencil beam scanning in only 48% of cases.
High-risk practice is running ahead of its evidence: HYPO-RT-PC is the only phase III reporting oncologic outcomes in high-risk pts and they were 11% of participants, while PACE-C has published toxicity but not oncological outcomes. Urethral sparing is recommended on mechanistic and single-study grounds while a post hoc PACE-B analysis found no significant association between urinary substructure dose and late urinary toxicity, and the panel itself flags the PACE-B urethra V42 <50% constraint as possibly too permissive.
The document's real contribution is the negative recommendations: no elective pelvic nodal RT with prostate SBRT outside a trial (100%, 12 votes) and no routine rectal spacer (85%, 11 votes), both areas where practice has drifted ahead of randomised data. It does not settle prostate volume cut-off, prophylactic medication, or whether intra-fraction tracking is required below a 5 mm margin, all of which returned no consensus.
| Category | Recommend SBRT (% of votes) |
|---|---|
| ISUP 2 | 100% (13 votes) |
| ISUP 3 | 100% (13 votes) |
| ISUP 4 | 38% (5 votes) |
| ISUP 5 | 0% (0 votes) |
| cT1c-cT2a | 100% (13 votes) |
| cT2b-cT2c | 100% (13 votes) |
| cT3a | 38% (5 votes) |
| cT3b | 0% (0 votes) |
| cT4 | 0% (0 votes) |
| PSA <20 ng/mL | 100% (13 votes) |
| PSA 20-40 ng/mL | 8% (1 vote) |
| PSA >40 ng/mL | 0% (0 votes) |
| Question | Vote | Level |
|---|---|---|
| Elective pelvic nodal RT with prostate SBRT (Q6) | No 100% (12 votes) | Strong consensus against |
| Bladder/bowel prep protocol (Q8) | Yes 100% (14 votes) | Strong consensus |
| ADT per existing guidelines, fractionation-independent (Q7) | Yes 100% (13 votes) | Strong consensus |
| Rectal spacer (Q9) | No 85% (11 votes) | Consensus against |
| Max IPSS cut-off (Q3) | Yes 85% (11 votes) | Consensus; median 17, range 10-20 |
| Max prostate volume cut-off (Q2) | Yes 62% (8 votes) | No consensus; median 90 cc, range 70-150 |
| Prophylactic meds (α1-blockers etc, Q4) | No 46% (6 votes) | No consensus |
| SBRT after BPH surgery (Q5) | Selected pts with waiting period 100% (13 votes) | Strong consensus; median wait 6 mo, range 2-12 |
- Cause of higher 3y biochemical relapse with 36.25 Gy in NRG-GU005
- Whether focal GTV dose escalation improves outcome in high-risk SBRT recruiting Image-guided Focal Dose Escalation- Primary pc Treated With Primary External Beam Hypofract.Stereotactic rt Phase NAn=374 · primary completion 2025-08 · randomised focal dose escalation vs no boost, cN0n=54 · primary completion 2027-06 · SBRT + mpMRI focal boost, unfavourable/high-risk
- Whether online adaptive RT improves toxicity over non-adaptive SBRT recruiting Adaptive Radiation Therapy (ART) Stereotactic Ablative Body Radiotherapy (SABR) for Primary Localized Prostate Cancer Phase NAn=164 · primary completion 2026-08 · margin-less adaptive 2 fx vs standard 5 fx SABR QoLrecruiting Is Adaptive SBRT for Prostate vs Image-guided Radiotherapy a True Evolution (ASPIRE) Phase 3n=320 · primary completion 2030-02 · phase 3 adaptive vs image-guided SBRT, urinary EPrecruiting Image-Guidance and Online Adaptation With Stereotactic Body Radiation Therapy for the Treatment of Localized Prostate Cancer, MANTICORE Trial Phase NAn=186 · primary completion 2031-12 · online adaptation vs IGRT SBRT, toxicity endpoint
📚 Sources · 📄 1 paper
TROG 08.03 RAVES QOL Substudy
ForPost-RP prostate cancer with adverse pathology (margins, EPE, or SVI)
Severe urinary leakage 16% vs 2%
aRT vs no RT at 5 yr, p = 0.01
TL;DRSevere urinary leakage 16% vs 2% at 5yr with aRT vs no RT; timing of salvage RT unrelated to QOL.
The QOL benefit of a salvage approach is avoidance, not delay: 52% of the sRT arm never needed RT, and among men who did get RT, severe urinary leakage at 5 yr was the same whether early or late (16% vs 13%, p = 0.7), with no coefficient linking RP-to-RT interval to any domain. Dose was 64 Gy/32 fx fossa-only, no ADT, no nodes.
For a man with adverse pathology after RP and an undetectable PSA, this supports PSA surveillance with early salvage rather than adjuvant RT on functional grounds; it does not speak to men needing ADT, pelvic nodal RT, or Gleason 9 disease, who were sparse or excluded here. The longer read
Delay buys nothing functionally: among men who received RT, severe urinary leakage at 5 yr was 16% aRT vs 13% sRT (p = 0.7) and no RP-to-RT interval coefficient reached significance. The advantage of a salvage policy is that 52% of that arm never needed RT. Dose was 64 Gy/32 fx fossa-only, 3D-CRT era, no ADT or nodes.
For counselling after RP with adverse pathology, the functional cost quoted to a man should be conditional on recurring: irradiated men reported severe urinary leakage of 16% at 5 yr against 2% in those never irradiated, but that no-RT group is defined by not recurring, not by randomization. Continence counselling is unchanged by RT timing.
11 details
Protocol-planned secondary analysis of the TROG 08.03 RAVES phase 3 noninferiority RCT, 166 aRT vs 167 sRT. Median follow-up 6 yr (IQR 4 to 7.1) in both arms. Complete-case analysis, no imputation, chi-square per timepoint.
High-risk features after RP: positive margins, extraprostatic extension, or seminal vesicle invasion. 82% Gleason 7, 3% Gleason 8, 12% Gleason 9. Median age 63.8 vs 63.9 yr (p = 0.9).
64 Gy in 32 fractions to the prostate fossa in both arms, mostly 3D-CRT rather than IMRT. aRT within 6 mo of RP; sRT triggered at PSA 0.20 ng/ml and delivered within 4 mo. Concurrent ADT and pelvic nodal treatment were not permitted.
Primary: proportion with a minimal clinically important change, defined as a >0.5 SD decline from baseline on each QLQ-PR25 domain. MCIC thresholds were 7 points urinary, 2 points bowel, 14 sexual activity, 12 sexual functioning. Global QOL by QLQ-C30.
The RP-to-RT interval regression is the cleanest read: no coefficient approached significance at 3, 4, or 5 yr in any domain, with the largest estimate 0.20 (95% CI -0.29 to 0.70, p = 0.4).
| Endpoint at 5 yr | Adjuvant RT | No RT | p |
|---|---|---|---|
| MCIC bowel symptoms | 37% (40/109) | 12% (6/50) | not reported in source |
| Severe urinary leakage | 18/111 (16) | 1/50 (2) | 0.01 |
| Severe urinary leakage at 4 yr | 15/124 (12) | 1/59 (1.7) | 0.02 |
| Urinary urgency | 18/110 (16) | 3/50 (6) | 0.072 |
GETUG-AFU 17 and RADICALS reported the same directional late GU penalty for adjuvant RT, though cross-trial comparison is blocked by differing urinary grading. Prior clinician-rated series put CTCAE grade 2 incontinence at 10 to 20%, bracketing the 16% seen here.
The aRT versus never-irradiated comparison is not randomized: those 87 men were selected by not recurring, so comorbidity and baseline continence are unbalanced by construction. The sRT-received group's worse sexual activity at 3 and 4 yr is confounded by higher-risk disease and likely more ADT off-protocol, and the 5-yr sexual functioning cells are as small as n = 10.
The patient-reported bowel signal is invisible on CTCAE (RAVES showed no clinician-rated GI difference), and the patient-reported urinary trend never reached consistent significance despite a 70% vs 54% clinician-rated G2+ GU gap. The two instruments are measuring different things, and neither alone describes what a man experiences.
CONSORT flow
Protocol-planned secondary analysis of a randomized trial; supports the established early-salvage standard. Exploratory, unadjusted for multiple testing, 3D-CRT era.
- Long-term patient-reported QOL with hypofractionated postprostatectomy RT
- QOL impact of adding short-course ADT and pelvic nodal RT post-RP
- Whether IMRT eliminates the patient-reported bowel signal
📚 Sources · 📄 1 paper
STAMPEDE abiraterone ± enzalutamide in high-risk non-metastatic prostate cancer (meta-analysis) NCT00268476
ForHigh-risk non-metastatic prostate cancer (N+ or high-risk N0) starting ADT
HR 0.53
95% CI 0.44-0.64, p<0.0001; 6-yr MFS 82% vs 69%
TL;DRMFS HR 0.53 (0.44-0.64) and OS HR 0.60 (0.48-0.73) adding 2yr abiraterone ± enzalutamide to ADT in high-risk non-metastatic prostate cancer.
The MFS benefit held whether or not RT was planned: HR 0.54 (0.44-0.67) with RT vs 0.51 (0.34-0.76) without, interaction p=0.67. So abiraterone adds to prostate RT and does not stand in for it. The RT was 74 Gy/37 fx to prostate + SVs, and the source does not describe pelvic nodal fields for the 39% who were N+.
In N+ or high-risk N0 non-metastatic prostate cancer starting long-course ADT with prostate RT, this supports 2 yr of abiraterone + prednisolone without enzalutamide. It does not extend to men treated with prostatectomy, who were not studied. The longer read
The abiraterone benefit is independent of planned RT (MFS HR 0.54 with vs 0.51 without, interaction p=0.67), and RT was mandated for N0. It stacks on 74 Gy/37 fx to prostate + SVs with 3 yr ADT. The source does not describe pelvic nodal fields, and only 71% of N+ pts had RT planned.
Two years of abiraterone + prednisolone added to 3 yr ADT improved OS (HR 0.60). Adding enzalutamide gave no extra MFS benefit (interaction HR 1.02) and raised grade 3+ AEs to 58% vs 32%. Enzalutamide adds cost and toxicity without added efficacy.
Also covered Oct 24
11 details 4 trials watching
Prespecified IPD meta-analysis of two open-label, randomised (1:1) phase 3 trials in the STAMPEDE platform, run at 113 UK and Swiss sites. N=1974, randomised 2011-2016, with no overlapping controls. Median follow-up was 72 mo.
High-risk non-metastatic prostate cancer on conventional imaging: N+, or N0 with at least two of T3/T4, Gleason 8-10, or PSA ≥40 ng/mL. Pts relapsing with high-risk features were also eligible. Median age was 68, and 774 (39%) were node-positive. Clinically significant cardiovascular disease was excluded.
All pts received 3 yr ADT. The combination arm added abiraterone 1000 mg + prednisolone 5 mg daily for 2 yr, and the second trial also added enzalutamide 160 mg. If RT was omitted, treatment could continue until progression.
Per local guidelines: 74 Gy/37 fx to prostate + SVs or a hypofractionated equivalent. RT was mandated for N0 and encouraged for N+. RT was planned in 85% overall: 99% of N0, 71% of N+ and 7% of previously treated pts.
Primary: MFS, which was changed from OS before any efficacy inspection and approved by the steering committee on Dec 2, 2019. Secondary endpoints were OS, prostate cancer-specific survival, biochemical failure-free survival, PFS and toxicity.
Both trials showed the benefit on their own: MFS HR 0.54 in the abiraterone trial and 0.53 in the abiraterone + enzalutamide trial, with no between-trial heterogeneity (I² p=0.90).
| Endpoint | Combination | Control | HR (95% CI) |
|---|---|---|---|
| MFS (1°) | 6-yr 82% | 6-yr 69% | 0.53 (0.44-0.64), p<0.0001 |
| OS | 6-yr 86% | 6-yr 77% | 0.60 (0.48-0.73), p<0.0001 |
| Prostate cancer-specific survival | median not reached | median not reached | 0.49 (0.37-0.65), p<0.0001 |
| Biochemical failure-free survival | median not reached | median 86 mo | 0.39 (0.33-0.47), p<0.0001 |
| PFS | median not reached | median not reached | 0.44 (0.36-0.54), p<0.0001 |
| Subgroup | HR (95% CI) | p interaction |
|---|---|---|
| RT planned: yes | 0.54 (0.44-0.67) | 0.67 |
| RT planned: no | 0.51 (0.34-0.76) | 0.67 |
| N0 | 0.60 (0.46-0.78) | 0.22 |
| N+ | 0.49 (0.38-0.64) | 0.22 |
| WHO PS 0 | 0.47 (0.38-0.58) | 0.00656 |
| WHO PS 1-2 | 0.86 (0.58-1.28) | 0.00656 |
| NSAID/aspirin: no | 0.62 (0.51-0.77) | 0.0052 |
| NSAID/aspirin: yes | 0.32 (0.21-0.48) | 0.0052 |
| AE | Abi trial: combo | Abi trial: control | Abi+enza trial: combo | Abi+enza trial: control |
|---|---|---|---|---|
| Any grade 3+ | 37% | 29% | 58% | 32% |
| Hypertension | 5% | 1% | 14% | 2% |
| ALT increase | 6% | <1% | 13% | 1% |
Grade 3+ AEs in the first 24 mo were 37% vs 29% in the abiraterone trial and 58% vs 32% in the abiraterone + enzalutamide trial. The main drivers were hypertension and ALT elevation. There were 7 grade 5 events, all in the combination arms.
The backbone is long-course ADT with prostate RT, which the authors frame as standard for this population. Adding enzalutamide to abiraterone also gave no extra benefit here, consistent with the modest rPFS gains and absent OS benefit the authors cite from that combination in mCRPC.
Staging used conventional imaging only. Toxicity was reported only for the first 2 yr, and data on subsequent therapy are unreliable. Heterogeneity by PS 1-2 (HR 0.86, 0.58-1.28) makes the benefit less certain in less fit men.
Abiraterone intensification improved MFS and OS on top of ADT whether or not RT was planned. Enzalutamide added toxicity without extra efficacy. Open questions are the right duration, the benefit after prostatectomy, and the benefit in PSMA-staged disease, none of which were tested.
Pooled IPD from two randomised phase 3 trials, 72-mo f/u, with both MFS and OS improved. The OS→MFS switch was prespecified before efficacy was seen. Authors call it a new standard.
- Is 2 years the optimal abiraterone duration? recruiting Reduced Length of ADT and ARTA With XRT in High-Risk Prostate Cancer (RELAX): A Randomised Trial Phase 2n=206 · primary completion 2035-01 · 9mo ADT + 6mo ARTA vs 2y ADT with RT, high-risk N0M0
- Benefit after radical prostatectomy untested recruiting Treating Prostate Cancer That Has Come Back After Surgery With Apalutamide and Targeted Radiation Based on PET Imaging Phase 3n=804 · primary completion 2032-12 · post-RP BCR: apalutamide+abiraterone added to SRT+ADT
- Benefit in relapse after prior local therapy underrepresented active Finite Androgen Ablation With or Without Abiraterone Acetate and Prednisone in Treating Patients With Recurrent Prostate Cancer Phase 2n=310 · primary completion 2027-02 · recurrent PCa: finite ADT ± abiraterone, randomisedrecruiting Treating Prostate Cancer That Has Come Back After Surgery With Apalutamide and Targeted Radiation Based on PET Imaging Phase 3n=804 · primary completion 2032-12 · phase 3 ARSI intensification in post-RP BCR
📚 Sources · 📄 1 paper
SUPREMO
ForPost-mastectomy breast, node-negative high-risk or 1-3 positive nodes
TL;DREditorial critique: chest-wall-only RT cut 10yr CW recurrence 1.1% vs 2.5% (HR 0.45) but RNI was prohibited.
The RT-relevant number is buried in SUPREMO's supplement: node-positive LRR 3.3% vs 4.8%, HR 0.51 (0.27-0.96), significant even with chest-wall-only fields and RNI prohibited. With supraclavicular coverage in 12% and IMN in under 2%, this trial never tested comprehensive PMRT, so it cannot settle the elective nodal decision.
In a post-mastectomy patient with 1-3 positive nodes staged by SLNB alone, this argues SUPREMO does not license PMRT omission; it says nothing about node-negative pts without adverse features, where EBCTCG also found no benefit. The longer read
The supplement carries the number the headline drops: node-positive LRR 3.3% vs 4.8%, HR 0.51 (0.27-0.96), achieved even with RNI prohibited, supraclavicular coverage in 12% and IMN in under 2%. SUPREMO therefore constrains chest-wall-only treatment, not the elective nodal volume decision.
Axillary staging gates how far SUPREMO travels: only 14% had SLNB alone, and roughly 30% of SLNB pts with 1-3 positive nodes harbour further nodes at completion ALND. Choosing ALND to justify skipping PMRT trades a 8% five-year lymphedema risk with SLNB alone for 25% with ALND alone.
Also covered Jul 7
9 details
ASO Perspectives editorial in Annals of Surgical Oncology, not new trial data. Two radiation oncologists re-read SUPREMO against the PMRT and RNI evidence base. PMRT after neoadjuvant therapy is explicitly out of scope.
The central claim is that SUPREMO tested chest wall alone, not PMRT: RNI was prohibited, supraclavicular nodes were covered in 12% of PMRT-arm pts (n=97), and internal mammary irradiation occurred in fewer than 2% across both arms. Non-UK centres could give RNI in the observation arm, and 12 control pts received supraclavicular RNI.
Only 25% were truly node-negative and would not be offered PMRT under current guidelines; the majority had N1 disease (1-3 nodes). 65% were hormone-receptor positive, TNBC was 10%, and only 14% had SLNB alone with the majority undergoing ALND.
SUPREMO's 10-year chest-wall recurrence fell from 2.5% to 1.1% (HR 0.45) with no gain in overall LRR, DFS or OS. The supplement carries the signal the headline drops: LRR 4.8% to 3.3%, HR 0.51 (95% CI 0.27-0.96) in node-positive pts, not in node-negative.
| Approach | 5yr lymphedema risk |
|---|---|
| SLNB alone | 8% |
| SLNB + RNI | 11% |
| ALND alone | 25% |
| ALND + RNI | 30% |
EBCTCG 2014 found PMRT cut 10-year LRR by 17.9% and 20-year breast cancer mortality by 8% in 1-3 node-positive women, persisting with a single positive node, with no node-negative benefit. MA-20 and EORTC 22922 both showed RNI benefit in 1-3 node-positive disease despite near-universal ALND, and a later EBCTCG RNI meta-analysis showed gains at 15 years including in contemporary systemic-therapy trials.
This is a single-perspective editorial from two radiation oncologists, so the framing selects evidence favouring comprehensive RNI, and the reader gets no independent re-analysis of SUPREMO's data. Its strongest number, the node-positive LRR HR 0.51, comes from a supplementary subgroup the trial did not power for.
The authors leave the genuinely open questions to trials in progress: MA.39 (Tailor-RT) for RNI omission at low recurrence score, T-Rex for RNI omission in hormone-sensitive disease with one to two macrometastatic SLNs. They also note the surgical corollary, that ALND should not be chosen to earn a PMRT omission, since ALND is the dominant lymphedema driver.
Editorial, no new data; contests the omission reading of SUPREMO on field design and population grounds, aligning with ASTRO 2025 and NCCN rather than the trial's public messaging.
- RNI omission in 1-3 node-positive pts staged by SLNB alone
- Whether low Oncotype score permits comprehensive RNI omission
- PMRT effect in triple-negative disease after mastectomy
📚 Sources · 📄 1 paper
ASTRO 2024: SBRT for Unfavorable Intermediate-Risk Prostate Cancer
TL;DRConference education session on SBRT for UIR prostate: 5 fractions over 1-2wks, 1-2% bothersome toxicity vs 10-30% with 45-fraction 2D era.
Reported via UroToday →
RTOG 9408PACE BHYPO-RT-PCFLAME 2.0FORT
The actionable detail is the urethral-constraint critique of PACE-B: contouring was optional and constrained only "if visualized" (V44Gy <20%), so hotspots ≥120% put ~48Gy (≈121Gy EQD2) on the urethra. That reframes the 5.4% vs 3.7% G2+ GU gap as a planning artifact, not an SBRT property, and argues for contouring and constraining the urethra in 5-fraction prostate plans. The longer read
Contour and constrain the urethra in 5-fraction prostate plans: PACE-B made it optional ("if visualized", V44Gy <20%), and plausible ≥120% hotspots mean ~48Gy (≈121Gy EQD2) there, which reframes the 5.4% vs 3.7% G2+ GU gap as planning, not modality. Separately, RTOG 9408 keeps 4mo ADT tied to UIR, not FIR.
14 details 4 trials watching
ASTRO 2024 education session (EDU 16), not a trial report. Dr Daniel Spratt reviews risk stratification, fractionation history, and the SBRT evidence base for unfavorable intermediate-risk prostate cancer.
Unfavorable intermediate-risk disease, defined since 2013 by Gleason grade group 3 (HR 3.49 for distant mets) or ≥2 intermediate risk factors (HR 2.40). FIR and UIR also separate on cumulative PCSM incidence (p=0.013).
Options span brachytherapy and EBRT (protons or photons/IGRT) across conventional (~40fx), moderate hypofractionation (~20fx), and ultra-hypofractionation (~5fx). Era contrast: 1980s 2D delivered 45 fractions over 9 weeks with 10-30% bothersome GU/GI toxicity; modern SBRT is 5 fractions over 1-2 weeks with 1-2%.
RTOG 9408 secondary analysis anchors the ADT question: in UIR, 4mo ADT improved distant metastasis (HR 0.48, 0.28-0.83, P=.008) and PCSM (HR 0.40, 0.26-0.60, P<.001), with no benefit in FIR. PACE-B 5yr showed no significant EFS difference for SBRT vs conventional/moderate hypofractionation.
| Question | Endpoint | Result |
|---|---|---|
| UIR vs FIR prognosis | Distant metastasis | HR 2.36 (95% CI 1.44-3.89), P=.001 |
| UIR vs FIR prognosis | PCSM | HR 1.84 (95% CI 1.29-2.62), P=.001 |
| ADT benefit in UIR | Distant metastasis | HR 0.48 (95% CI 0.28-0.83), P=.008 |
| ADT benefit in UIR | PCSM | HR 0.40 (95% CI 0.26-0.60), P<.001 |
| ADT benefit in FIR | DM / PCSM | No improvement |
PACE-B G2+ GU 5.4% SBRT vs 3.7% control (p=0.28), no significant bowel difference. Pooled SBRT series: late grade ≥3 GU 2.0% (1.4-2.8%) and GI 1.1% (0.6-2.0%), with dose associated with both better biochemical control (P=.018) and worse late G3+ GU (P=.014).
The session's argument is that SBRT toxicity is a planning problem, not a modality problem: PACE-B did not require urethral contouring, so likely hotspots of ≥120% (≥48Gy, ~121Gy EQD2 to urethra) can explain the GU excess. Focal-boost work (36.25Gy/5fx + DIL to 45-50Gy; Loblaw's 35Gy prostate / 25Gy pelvis / 50Gy DIL) points the field toward whole-gland de-escalation with a boost.
Single-speaker synthesis with the speaker's own interpretive framing rather than a systematic review; the urethral-hotspot explanation for PACE-B GU toxicity is inference, not a reported dosimetric analysis. The captured excerpt truncates mid-FLAME 2.0 and never reaches the FORT trial named in the keywords.
- Does mandatory urethral constraint erase SBRT's GU excess? recruiting Daily Adaptive Radiation Therapy Using an Individualized Approach for Prostate Cancer Phase NAn=132 · primary completion 2026-07 · urethral-sparing adaptive SBRT, EPIC-26 acute GU 1° EPn=42 · primary completion 2028-01 · SUPR-SABR urethra sparing vs historical GU tox rates
- Does whole-gland de-escalation with DIL boost preserve biochemical control? n=58 · primary completion 2028-01 · microboost SBRT with whole gland dropped to 30-35 Gy
- Optimal DIL boost dose in 5 fractions n=132 · primary completion 2025-02 · 5-fraction MR-guided SBRT with SIB to the DIL
📚 Sources · 📄 1 paper
Abstract
HYDRA
ForLocalised prostate cancer, definitive external-beam RT
TL;DRNo PFS difference for either isodose (HR 0.92) or dose-escalated MHFRT (HR 0.94), but escalation raises late G2+ GI (OR 1.48).
The split that matters is isodose vs dose-escalated MHFRT, not hypofractionation itself: escalation adds no PFS (HR 0.94, 0.82-1.09) and costs bowel on both physician grading (OR 1.48) and patient report (OR 1.68). GU was unchanged in both strata. The schedule decision lands on 60 Gy in 20 fractions.
In a man with localised prostate cancer starting definitive prostate-only EBRT, this supports an isodose moderately hypofractionated schedule over a dose-escalated one; it does not extend to five-fraction ultrahypofractionation, post-prostatectomy salvage, or whole-pelvis treatment. The longer read
The decision this moves is schedule selection, not modality: escalated MHFRT shows no PFS gain (HR 0.94, 0.82-1.09) and raises late G2+ GI (OR 1.48) plus patient-reported bowel decrement (OR 1.68), while isodose shows neither. 60 Gy in 20 fractions is the defensible default for prostate-only volumes.
7 details 5 trials watching
IPD meta-analysis of randomised phase 3 CFRT vs MHFRT trials via the MARCAP consortium. Searches on Dec 15, 2023 and re-run Jan 8, 2025 screened 1696 records down to 7 eligible trials. Three separate analyses: efficacy, physician-scored late toxicity, and patient-reported outcomes.
Localised prostate cancer on trials that published patient-level efficacy AND late toxicity data. 3454 pts across three isodose trials, 2426 pts across four dose-escalated trials. Trials whose CFRT arm fell below modern dose were excluded.
The intervention split is the whole point: isodose MHFRT (same equivalent dose in fewer fractions, eg 60 Gy in 20 fractions) versus dose-escalated MHFRT. The CFRT comparator had to deliver ≥70 Gy in 2 Gy equivalents.
Primary (efficacy): progression-free survival. Co-primary toxicity endpoints: late grade 2 or higher GU and GI. Co-primary PRO endpoints: clinically-significant decrement in urinary or bowel quality of life.
The GI signal sits entirely in the dose-escalated stratum and shows up on both physician grading and patient report; the isodose stratum carries neither. GU odds ran above 1 in both comparisons with intervals crossing unity.
CHHiP and PROFIT established 60 Gy in 20 fractions as non-inferior to conventional fractionation. The escalated schedules were built on the premise that a higher equivalent dose in fewer fractions would improve control; pooled here that premise fails on PFS while adding bowel toxicity.
Toxicity scales and PRO instruments were not uniform across the seven trials, and the dose-escalated stratum pools four schedules that are not interchangeable, so the OR describes escalation as a class, not one regimen. Follow-up also differs between strata (5.4 vs 7.1 yrs).
With efficacy answered as a null, the schedule decision turns entirely on toxicity, and the toxicity difference runs one way. Escalating per-fraction dose beyond isodose buys no measurable PFS while adding bowel morbidity that pts themselves report, which leaves little argument for an escalated MHFRT schedule in intact localised disease.
Pooled IPD from seven randomised phase 3 trials, aligned with existing moderate-hypofractionation practice; refines which regimen rather than establishing a new modality or population.
- Does the escalation bowel signal extend to five-fraction ultrahypofractionation? recruiting Comparing Moderately Ultra Hypofractionated Radiation Treatments for Prostate Cancer Phase 2n=204 · primary completion 2030-11 · randomised 20fx vs 5fx post-op bed +/- pelvisrecruiting Salvage Moderate Hypofractionated Versus Ultrahypofractionated Radiotherapy for Biochemical Recurrence After Radical Prostatectomy in Prostate Cancer Phase 3n=270 · primary completion 2034-12 · phase 3 moderate vs ultrahypo salvage, toxicity EP
- Do rectal spacers and daily IGRT narrow the dose-escalated GI gap? n=500 · primary completion 2027-12 · SpaceOAR Vue for late GI toxicity under SBRTn=84 · primary completion 2027-12 · Barrigel anterior rectal sparing in post-op RT
- Same toxicity read when MHFRT covers whole-pelvis nodal volumes? n=18 · primary completion 2026-08 · 20/16/12fx pelvic nodal RT with prostate SIB
📚 Sources · 📄 1 paper
Abstract
ESTRO OCSCC Post-op CTV Delineation Guidelines
ForResected oral cavity SCC proceeding to post-operative radiotherapy
TL;DRFirst ESTRO guideline for post-op CTV delineation in oral cavity SCC: GTV-P pre-op + 10 mm composited with surgical defect/flap + 5 mm.
The margin recipe is asymmetric and that is the operative detail: 10 mm around the re-created pre-op GTV-P but only 5 mm around the surgical defect or flap, composited rather than either alone. Fig 3.1/3.2 shows why, the re-created GTV-P extended superiorly beyond the defect into infratemporal fossa, a geographical miss if you contour the defect alone.
In resected OCSCC going to PORT, this supports re-creating the pre-op GTV-P from diagnostic MRI alongside the defect or flap rather than contouring the operative bed alone; it does not extend to R2 resections or other head and neck subsites. The longer read
The margin recipe is asymmetric: 10 mm around the re-created pre-op GTV-P but 5 mm around the surgical defect or flap, composited rather than either alone. Nodal margin is pENE-gated at 5 mm versus 10 mm on GTV-N pre-op. Fig 3.1/3.2 shows the pre-op GTV extending past the defect into infratemporal fossa, a geographical miss if you contour the bed alone.
11 details 5 trials watching
ESTRO-convened multi-disciplinary expert group developing delineation guidelines through discussion and review of current evidence and international practice. Drafts were reviewed by HNSCC experts from countries outside the authorship (Japan, Hong Kong, Australia, Brazil, Mexico, Canada, Denmark, France, Spain, Poland, Ireland, UK) and modified on their feedback. No efficacy endpoint, no patient cohort.
Patients with oral cavity squamous cell carcinoma requiring post-operative radiotherapy, regardless of margin status and other histological risk factors. R2 resection (macroscopic residual disease) is explicitly out of scope. Companion background manuscript from the same group covers indications for PORT.
Planning CT 2.0 mm slices (range 1-3 mm), skull base to below sterno-clavicular joint, IV contrast mandatory, rigid co-registration with pre-op contrast-enhanced CT and/or MRI matched to C1-C3 vertebral bodies or nearby bone, not to soft tissue. CTV-P is the composite of GTV-P pre-op + 10 mm and surgical defect/flap + 5 mm, edited for bone, fascia, air, teeth and any intra-oral prosthesis. Nodal margin is 5 mm on GTV-N pre-op without pENE, 10 mm with pENE.
None. The stated aim is consistency of delineation to enable multi-institutional audit, clinical trials and RTQA. Authors position prospective audits of practice and outcomes as the route to establishing these volumes as standard of care.
Extends the 2018 international CTV-P consensus for definitive HNSCC RT, whose 5+5 mm geometric expansion supplies the 10 mm used here around GTV-P pre-op. Cites the DAHANCA finding that geometric expansion is more conformal than anatomical margins, a post-hoc De-ESCALaTE analysis correlating the anatomical-to-geometric protocol change with lower late dysphagia, and non-randomised Dutch series where reducing the high-risk margin 10 mm to 6 mm cut salivary and constrictor dose. GORTEC's 2020 flap delineation guidance is named as an adjunct.
The 5 mm and 10 mm margins are imported from definitive-setting geometry and one surgical pathology series (>95 % of microscopic infiltration within 5 mm of GTV-P edge), not from post-operative recurrence mapping. The dose to dissected but uninvolved levels rests on a 1993 MD Anderson observation never tested prospectively, and is left to clinician discretion (EQD2 50-60 Gy). The whole method assumes accurate pre-op to planning CT co-registration, and the fallback where it fails is to treat the entire involved level, a larger volume.
The novel move is refusing to pick between the two available surrogates for a resected tumour: re-created pre-op GTV and operative bed are contoured independently and unioned, because each fails in a different direction. Fig 3.1 shows a GTV-P pre-op extending superiorly past the defect toward the infratemporal fossa, and Fig 8.1 a pectoralis major pedicled flap whose composite volume extends outside the oral cavity and is trimmed back. What is left unsettled is dose de-escalation to central flap tissue, where the guideline offers a flap avoidance structure for standardisation while stating there is a lack of data and consequently a lack of consensus.
| Volume | Indication | EQD2 dose |
|---|---|---|
| CTV-P post-op | PTV associated with post-op primary CTV | 60 Gy |
| CTV-P high-risk | Positive (<1 mm) margin, whole CTV-P or localised strip | over 60 Gy, e.g. 64-66 Gy |
| CTV-N1 | Involved nodal levels | 60 Gy |
| CTV-N2 | Undissected at-risk levels | 50 Gy |
| CTV-N2, dissected at-risk levels | Optimal dose unknown | 50 Gy to 60 Gy, clinician discretion |
| CTV-N high-risk | Pathological extranodal extension | over 60 Gy, e.g. 64-66 Gy |
ESTRO expert guideline, no efficacy endpoint. Fills a documented gap (no prior post-op HNSCC CTV consensus); authors themselves position prospective audit as the validation step.
- Optimal dose to dissected but uninvolved nodal levels recruiting Preservation of Swallowing in Respected Oral Cavity Squamous Cell Carcinoma: Examining Radiation Volume Effects (PRESERVE): A Randomized Trial Phase 2n=90 · primary completion 2026-09 · OCSCC RCT: omit RT to dissected pN0 hemi-neckn=50 · primary completion 2029-01 · compartment-based post-op volume reduction in HNSCCrecruiting De-Intensification of Postoperative Radiotherapy in Patients With Squamous Cell Carcinoma of the Head and Neck Phase 2/3n=508 · primary completion 2031-12 · omits elective neck RT after neck dissection
- Whether flap dose de-escalation is safe not yet Lipiodal Injection Technique for Free Flap Sparing Adjuvant RT Planning in HNC Phase Early 1n=10 · primary completion 2026-03 · lipiodol marks flap borders for sparing plansn=348 · primary completion 2031-03 · phase 3 RCT: flap-sparing vs standard post-op RT
- Whether 10 mm post-op primary margin can be reduced as in definitive setting
📚 Sources · 📄 1 paper
NRG-GU005 (quality of life)
ForLocalized intermediate-risk prostate cancer, median age 68, no ADT specified
Bowel 33% vs 46% at 1 yr
p=0.002; 2yr bowel/UIO primary PRO endpoint not reported in source
TL;DRFewer MCID declines with SBRT at 1yr bowel (33% vs 46%, p=0.002) and sexual (34% vs 44%, p=0.026).
Reported via UroToday →
The QoL separation is domain-specific, not global: bowel and sexual at 1yr, urinary incontinence at 2yr, with no longitudinal effect in sexual or hormonal. Rectal manipulation (SpaceOAR 55%) and the 38.78 Gy PTV max cap gate transfer, since the bowel and GU signals came from a spacer-heavy, urethra-constrained delivery.
In localized intermediate-risk prostate cancer choosing between 5-fraction SBRT and moderate hypofractionation, this supports SBRT on patient-reported bowel, sexual, and continence grounds; it does not speak to high-risk disease, nodal coverage, or oncologic non-inferiority, which the trial's primary endpoint carries. The longer read
Domain-specific, not global: bowel and sexual at 1yr, incontinence at 2yr, with no longitudinal sexual or hormonal effect. The 38.78 Gy PTV max cap and 55% SpaceOAR use gate transfer, since the favorable GU and bowel profile came from a urethra-constrained, spacer-heavy delivery, not from five fractions alone.
Also covered Aug 14
11 details
Randomized, non-blinded phase III, 1:1, N=698 (MH-IMRT 345, SBRT 353), stratified by Gleason score, PSA, and rectal manipulation. The trial's oncologic primary endpoint sits elsewhere; this analysis reports the patient-reported secondary endpoints.
Localized intermediate-risk prostate cancer, median age 68 (IMRT) and 69 (SBRT). Two patients were ineligible (one high-risk, one PSA out of window). Baseline EPIC domains were balanced across arms, all p≥0.093.
SBRT 36.25 Gy in 5 fractions delivered 2-3 per week, PTV expansion 5mm except 3mm posteriorly and anteriorly, PTV max capped at 38.78 Gy unless the urethra was visualized and contoured (acceptable variation 43.5 Gy). MH-IMRT 70 Gy/28 fx or 60 Gy/20 fx, PTV expansion 8mm except 5mm posteriorly. CTV was prostate ± 1cm proximal seminal vesicles. Rectal manipulation was common: SpaceOAR in 55% overall.
EPIC-26 at baseline, 12 and 24 months. MCID thresholds: >5 points urinary irritative/obstructive, >6 urinary incontinence, >10 sexual, >4 bowel and hormonal. Individual MCID rather than group mean scores was the analytic unit, with an exploratory longitudinal linear model adjusted for baseline score, arm, stratification factors, T-stage, age, and race.
The arm-level MCID and toxicity comparisons are tabulated above. Longitudinal modeling of urinary incontinence gave a least square mean difference of 2.91 (95% CI 0.85-4.97, p=0.0058) favoring SBRT, while sexual and hormonal domains showed no significant treatment effect.
| Domain / timepoint | SBRT | MH-IMRT | p |
|---|---|---|---|
| Bowel, 1 yr | 33% | 46% | 0.002 |
| Sexual, 1 yr | 34% | 44% | 0.026 |
| Urinary incontinence, 2 yr | 26% | 35% | 0.023 |
| Event | SBRT | MH-IMRT | p |
|---|---|---|---|
| Treatment-related G≥3 GU | 0.6% | 2.5% | 0.04 |
| Rectal hemorrhage, any grade | 10.5% | 17.3% | 0.01 |
| Fatigue, any grade | 39.2% | 50.8% | 0.0025 |
Investigator-reported toxicity favored SBRT across the board: grade ≥3 GU 0.6% vs 2.5% (p=0.04), any-grade rectal hemorrhage 10.5% vs 17.3% (p=0.01), any-grade fatigue 39.2% vs 50.8% (p=0.0025). The GU finding is the one that most often runs the other way in ultrahypofractionation series, so it is worth reading as the trial's own answer to the pre-trial toxicity concern.
PACE-B is the other large randomized SBRT vs moderate hypofractionation comparison, and both trials show lower urinary incontinence decline with SBRT despite differing MCID definitions. Prior patient-level meta-analysis had suggested less clinically meaningful bowel and urinary irritative/obstructive decline at two years with SBRT, and the 1-year bowel result here is directionally consistent.
Differential attrition ran against the IMRT arm: 22 IMRT patients (6.4%) died or withdrew before year 1 versus 4 SBRT patients (1.1%), and 22 IMRT patients never received the assigned RT after withdrawal versus 1 in the SBRT arm. Completion was 79.9% (IMRT) and 84.0% (SBRT) at year 1. The domain-by-timepoint pattern (bowel and sexual at 1yr, incontinence at 2yr) is the kind of scattered significance that multiplicity should temper.
The trial was designed when the open question was whether five fractions cost the patient something. The PRO answer is that it does not, and the investigator-reported toxicity answer is that it may cost less. What the QoL data cannot do is settle whether SBRT is oncologically non-inferior, which is the primary endpoint and is not reported in this source.
CONSORT flow
Prespecified PRO secondary analysis of a phase III trial, non-blinded with patient-reported endpoints; aligns with PACE-B rather than establishing a new position. Oncologic primary endpoint not reported here.
- Oncologic non-inferiority of SBRT vs MH-IMRT in this trial
- Whether bowel benefit holds without rectal spacer
- Durability of QoL separation beyond 2 years
📚 Sources · 📄 1 paper
Abstract
10-yr SBRT Survival/Toxicity (Meier et al.)
ForLocalised low- or intermediate-risk prostate, no ADT, prostate volume up to 100 cc
TL;DR10-yr RFS 90% overall (94% LR, 86% IR) with 40 Gy/5 fx; grade 3 late toxicity 1.4-1.5%, no grade 4-5.
Two-thirds of relapses fell between 5 and 10 yr, so the reassurance PACE-B gives at 5 yr is provisional. The unfavorable IR subgroup sits at 77% (60-93) vs 92% for favorable IR (p=0.002), which is where the ADT-with-SBRT question actually lives, not in the pooled 86% IR number.
In unfavorable intermediate-risk prostate considered for 40 Gy/5 fx monotherapy, the 77% 10-yr RFS (vs 92% favorable IR) is the number that informs an ADT discussion; the favorable IR and low-risk data do not carry that concern. The longer read
Two-thirds of relapses fell between 5 and 10 yr, so PACE-B's 5-yr reassurance is provisional. Within IR, unfavorable pts sat at 77% (60-93) vs 92% favorable (p=0.002) with 40 Gy/5 fx and no ADT, which is where the ADT-addition question lives, not in the pooled 86%.
11 details 4 trials watching
Investigator-initiated phase 2 nonrandomized trial across 21 centers (community, regional, academic), enrolling Jan 2008 to Apr 2010. 310 evaluable pts, median age 68, median follow-up 9 yr. Kaplan-Meier estimation with log-rank comparison of LR vs IR.
172 low-risk (T1b-T2a, Gleason 6, PSA under 10) and 138 intermediate-risk (T1b-T2b, Gleason 7 or Gleason 6 with PSA 10-20), all confirmed by central pathologic review. IR pts subclassified favorable vs unfavorable by MSK criteria. Prostate volume up to 100 cc allowed; prior TURP and baseline AUA score were not exclusions.
40 Gy in 5 fractions (8 Gy x 5, equivalent to ~100 Gy at 2 Gy/fx assuming a/b = 2) on a noncoplanar robotic platform. Fiducial tracking with translational and rotational intrafractional motion correction was mandatory. Androgen suppression was not allowed, so the outcomes are RT-attributable.
Relapse defined as biochemical failure (nadir + 2), clinical failure, or administration of any salvage, antiandrogen, or systemic therapy. Late toxicity was physician-reported, CTCAE v3, events beyond 3 mo. Day 0 was the last day of treatment.
10-yr OS 84% (76-91). Freedom from local failure 96% (93-99) overall. The separation that matters is within IR: favorable 92% vs unfavorable 77%, p = 0.002, whereas LR vs IR overall was not significant (p = 0.19).
| Group | 10-yr RFS (95% CI) | p |
|---|---|---|
| Whole group | 92% (87-96) | n/a |
| Low risk | 94% (89-99) | 0.19 (LR vs IR) |
| Intermediate risk | 86% (77-94) | 0.19 (LR vs IR) |
| MSK favorable IR | 92% (90-100) | 0.002 (fav vs unfav) |
| MSK unfavorable IR | 77% (60-93) | 0.002 (fav vs unfav) |
Four pts had five grade 3 events, all GU, and no grade 4-5 events occurred. Cumulative 10-yr grade 3 rates were 1.4% LR and 1.5% IR, far below the 10% rate the trial deemed acceptable. Grade 2+ GU 14% exceeds grade 2+ GI 2.1% by roughly sevenfold; no new late grade 3+ events after year 5.
IR relapse-free survival (86%) sits above the 74-78% 10-yr RFS of dose-escalated EBRT in RTOG 0126, and the authors note an updated HYPO-RT-PC now shows superior 10-yr RFS in the 6.1 Gy x 7 arm. Toxicity matched Fuller's CyberKnife trial but was lower than the PACE-B SBRT arm and PATRIOT, both of which treated substantial fractions on a conventional linac.
The toxicity advantage over PACE-B and PATRIOT is confounded by platform, and the sponsor makes that platform, so the comparison cannot separate tracking from delivery-era and case-mix differences. Toxicity is physician-reported CTCAE only, with no patient-reported instrument, which understates GU bother relative to the EPIC-based comparators. Comparator EBRT series (RTOG 0126) predate modern IGRT.
The durability question, not the toxicity question, is what 10 yr answers here: two-thirds of relapses occurred between 5 and 10 yr, in this trial and in Fuller's. That timing means a 5-yr non-inferiority readout is structurally optimistic for both arms, and it reframes what PACE-B's 5-yr result can and cannot settle.
Single-arm nonrandomized phase 2, no concurrent comparator; sponsor-funded with device-specific delivery. Extends existing 5-yr SBRT data rather than testing a new question.
- Whether ADT improves outcomes for unfavorable intermediate-risk pts receiving SBRT n=310 · primary completion 2025-12 · phase 3 prostate SRT +/- short-term ADT, bDFSn=222 · primary completion 2027-12 · SBRT without ADT in UIR, Decipher-gatedn=392 · primary completion 2030-04 · SBRT + 6-mo ADT vs SBRT alone, NCCN UIR cohort
- Whether intrafractional tracking, not platform, drives the toxicity difference recruiting Is Adaptive SBRT for Prostate vs Image-guided Radiotherapy a True Evolution (ASPIRE) Phase 3n=320 · primary completion 2030-02 · adaptive vs image-guided SBRT, urinary endpoint
- 10-yr PACE-B relapse rates vs conventional fractionation
📚 Sources · 📄 1 paper
American Radium Society AUC: Local Intraprostatic Recurrence
ForIsolated intraprostatic recurrence after definitive prostate RT
TL;DRSevere GU toxicity 20% after salvage RP vs 5.6% SBRT, 9.6% HDR: panel prefers biopsy-confirmed reirradiation.
The modality recommendation is a toxicity argument, not an efficacy one: MASTER found adjusted 5-yr recurrence-free survival of 50% to 60% across modalities with no survival difference vs RP, so reirradiation wins on severe GU toxicity (5.6% SBRT, 9.6% HDR vs 20% RP). Target volume then follows concordance, focal when mpMRI and systematic biopsy agree, whole-gland when they do not.
In a man with rising PSA after conventionally fractionated definitive prostate EBRT whose PSMA PET and mpMRI show isolated intraprostatic recurrence, this supports biopsy confirmation before reirradiation rather than ADT alone; it does not extend to recurrence after primary brachytherapy or to nodal or distant failure. The longer read
Every accepted schema fits in six or fewer fractions (34 Gy or 40 Gy in 5 fractions, 36 Gy in 6 fractions per GETUG-AFU 31, HDR 27 Gy in 2 fractions), and focal CTV is mpMRI plus choline PET GTV with a 5-7 mm margin bound by the capsule. None of it was validated after hypofractionated primary RT.
ADT alone is recommended against for confirmed local recurrence. Only a short 4-6 mo LHRH agonist is endorsed, as a radiosensitizer with salvage SBRT, and the panel reached no agreement on relugolix (HERO's cardiac benefit was an unplanned secondary, PRONOUNCE did not replicate). Classic ADT is preferred over novel hormonal agents.
Salvage RP holds equivalent adjusted 5-yr recurrence-free survival in MASTER (50% to 60% across modalities, no survival difference vs RP), so the case against it is toxicity: severe GU 20% vs 5.6% after SBRT. Biopsy and ablation should not be combined in one procedure, since histologic confirmation must precede salvage.
9 details 4 trials watching
PRISMA systematic review of PubMed and Embase (searched 28 June 2022) across four topics, excluding conference abstracts, non-English publications and series of fewer than five patients. A 12-member multidisciplinary panel of radiation oncologists, urologists and medical oncologists voted in two rounds by modified Delphi, with RAND methodology defining disagreement.
Scope is tier A disease, local-only intraprostatic radiorecurrence after definitive RT, with BCR defined as PSA 2.0 ng/ml above nadir. Evidence was restricted to men whose primary treatment was conventionally fractionated EBRT, and prior brachytherapy patients were excluded from the synthesis. Every variant presumes the patient wants curative-intent local salvage.
All accepted salvage schemas fit in six or fewer fractions. For focal salvage, GETUG-AFU 31 defines GTV by mpMRI plus choline PET with a 5-7 mm margin bound by the prostatic capsule; whole-gland salvage SBRT has prospective support from the Fuller series. Dose constraints and IGRT method are out of scope.
Long hormone courses are recommended against across all salvage scenarios. A short 4-6 mo LHRH agonist carries moderate consensus as a radiosensitizer with salvage SBRT in patients without cardiac history, weaker consensus with cardiac comorbidity, and classic ADT is preferred over novel hormonal agents.
The toxicity read that drives the reirradiation preference comes from pooled retrospective data that could not evaluate sexual toxicity and included no PSMA PET selection. Approaches that combine biopsy and ablation in one procedure are discouraged, since histologic confirmation must precede salvage.
No prior consensus guideline addressed intraprostatic radiorecurrence exclusively. The hormone-only comparators being displaced (Crook intermittent vs continuous ADT, TOAD immediate vs delayed, EMBARK enzalutamide MFS benefit) all enrolled before PET-based selection and none isolated a biopsy-confirmed, local-only cohort. RTOG 0526 reported after MASTER closed, adding prospective LDR support.
The search closed 28 June 2022 with an acknowledged lag to publication. MASTER carries between-study heterogeneity and follow-up asymmetry favoring older modalities, so its flat efficacy comparison is not a randomised one. The hormone recommendation rests on no qualifying study and is extrapolated from de novo intermediate-risk data.
Settled: image, biopsy with both systematic and targeted cores, then prefer reirradiation over hormones alone. Not settled: the modality for a second salvage, for castrate-resistant local recurrence, for short PSA doubling time, or after prior grade 3 toxicity, all of which drew panel disagreement.
| Variant | Panel position |
|---|---|
| Variant 1: isolated intraprostatic recurrence | Reirradiation usually appropriate; cryotherapy or HIFU may be appropriate; ADT alone not recommended |
| Variant 2: short PSA doubling time, short interval to failure | HIFU may be appropriate, but disagreement across all interventions; ADT alone not recommended |
| Variant 3: castrate-resistant local recurrence | Disagreement on intervention; androgen suppression uniformly not recommended |
| Variant 4: second local salvage | Disagreement on which modality to select |
| Variant 5: prior grade ≥3 toxicity | Disagreement; active surveillance may be appropriate; ADT can be considered |
| Modality | Severe GU | Severe GI |
|---|---|---|
| Salvage RP (reference) | 20% | 1.8% |
| SBRT | 5.6% | not reported in source |
| HDR brachytherapy | 9.6% | 0.0%, p < 0.01 vs RP |
| LDR brachytherapy | 9.1% | not reported in source |
| Scenario | Target volume |
|---|---|
| mpMRI and systematic biopsy agree on lesion location | Focal favored |
| History of grade ≥3 toxicity from initial RT course | Focal favored |
| Lesion occult on mpMRI, localised by PET plus systematic biopsy | Focal or whole-gland both appropriate |
| mpMRI and systematic biopsy disagree on lesion location | Whole-gland preferred |
| Recurrent lesion in a different location to the index lesion | Whole-gland preferred, focal appropriate in selected cases |
Appropriate use criteria from a 12-member Delphi panel; the output is a recommendation grid, not an efficacy result. No trial endpoint, so efficacy verdicts do not apply.
- Salvage outcomes after primary hypofractionated RT or prior brachytherapy n=60 · primary completion 2024-11 · RO-PIP: salvage ultra-hypofx EBRT vs HDR, pt-reported toxrecruiting Stereotactic Re-irradiation of Local Recurrences of Prostate Cancer After Radiotherapy Phase 2n=55 · primary completion 2029-12 · focal SBRT reRT, G2/G3 GU-GI tox 1° EPn=30 · primary completion 2032-01 · salvage HDR after prior EBRT or LDR brachytherapy
- Whether short ADT adds oncologic benefit to salvage reirradiation
- Optimal modality for castrate-resistant or second local salvage n=50 · primary completion 2025-03 · focal salvage HDR, biopsy/MRI-guided local recurrence
📚 Sources · 📄 1 paper
SUPREMO
ForPost-mastectomy pT1-2N1, pT3N0, or pT2N0 grade 3/LVI+ breast cancer
81.4% vs 81.9%
HR 1.04, 95% CI 0.82-1.30, P=0.80; primary endpoint not met
TL;DR10yr OS 81.4% vs 81.9% (HR 1.04, 0.82-1.30, p=0.80): PMRT omission safe in intermediate-risk pN0-pN1 post-mastectomy.
The RT read is the local-control trade: 1.1% vs 2.5% chest-wall recurrence, 29 events total, bought with 40-50 Gy to the chest wall in a population where OS was flat at 10 years. Nodal volumes were not routinely treated (SCF 97/808), so this speaks to chest wall alone, not to regional nodal irradiation.
In a pT2N1 or pT3N0 mastectomy patient who has completed modern adjuvant systemic therapy, this supports discussing PMRT omission with an absolute chest-wall recurrence trade under 2 points; it does not address regional nodal irradiation or pN2-N3 disease. The longer read
The trade is 1.1% vs 2.5% chest-wall recurrence from 40-50 Gy, with 10yr OS flat (HR 1.04). Nodal volumes were not routinely treated (SCF 97/808, IMC 12/808), so this licenses chest-wall omission specifically, not regional nodal omission, and moves PMRT here into a morbidity-versus-local-control discussion.
The systemic backbone (85% chemo, 79% endocrine, 19% trastuzumab) is what makes the null interpretable: with modern adjuvant therapy the residual chest-wall event rate is 2.5% untreated, leaving no room for RT to alter survival. Referral for PMRT in this band becomes optional rather than expected.
After mastectomy plus an axillary procedure in pT1-2N1, pT3N0, or pT2N0 grade 3/LVI disease, expected PMRT no longer carries a survival argument (HR 1.04), which changes the reconstruction conversation at the time of surgery since a planned reconstruction need not be sequenced around anticipated chest-wall irradiation.
Also covered Jul 9
9 details
International phase 3 randomized trial (BIG 2-04 MRC/EORTC SUPREMO), 125 UK sites plus 27 European and 21 international sites. N=1607 ITT (808 CWI, 799 no CWI), randomized August 2006 to April 2013, database lock June 2024. Median follow-up 9.6 years.
"Intermediate-risk" post-mastectomy disease: pT1N1, pT2N1, pT3N0, or pT2N0 with grade 3 and/or LVI. All had mastectomy, an axillary procedure, and systemic therapy. Baseline systemic exposure: 85% chemotherapy, 79% endocrine, 19% trastuzumab.
Chest wall 40 to 50 Gy in the irradiation arm. Nodal volumes were not part of the randomized question: supraclavicular fossa treated in only 97/808 irradiated patients, internal mammary chain in 12/808. Twelve patients in the no-irradiation arm received SCF treatment.
Primary: overall survival at 10 years. Secondary: chest-wall recurrence, regional recurrence, disease-free survival, distant metastasis-free survival, cause of death, radiation-related adverse events.
The historic case for postmastectomy RT in node-positive disease rests on the EBCTCG overview, where the locoregional-control gain translated into a mortality benefit. SUPREMO tests that inheritance in the 1-3 node and high-risk node-negative band under contemporary systemic therapy and finds the recurrence signal preserved (HR 0.45) but the survival signal absent (HR 1.04).
The chest-wall recurrence benefit rests on 29 events total with a CI upper bound of 0.99, so the point estimate is unstable. Accrual ran 2006-2013, predating routine dual HER2 blockade, extended adjuvant CDK4/6 inhibition, and current genomic risk stratification, all of which lower the baseline recurrence rate this trial was powered against.
A flat OS with a halved chest-wall recurrence is the signature of a locoregional intervention operating below the threshold where local control converts into survival. At 1.1% vs 2.5%, the absolute chest-wall event rate in both arms is low enough that no plausible salvage-to-mortality pathway could move a 10-year OS curve. The result reframes PMRT in this band as a local-control decision to be weighed against RT morbidity, not as a survival decision.
| Endpoint | CWI | No CWI | HR (95% CI) |
|---|---|---|---|
| Overall survival (1°) | 81.4% | 81.9% | 1.04 (0.82-1.30), p=0.80 |
| Disease-free survival | 76.2% | 75.5% | 0.97 (0.79-1.18) |
| Distant MFS | 78.2% | 79.2% | 1.06 (0.86-1.31) |
| Chest-wall recurrence | 9 (1.1%) | 20 (2.5%) | 0.45 (0.20-0.99) |
CONSORT flow
Adequately powered phase 3, prespecified OS primary, 9.6yr median follow-up, modern systemic backbone. Supports omitting PMRT in a population where guidelines still often recommend it.
- Does regional nodal irradiation carry the same null in pN1 disease
- Which biomarker or genomic subgroup still benefits from chest-wall RT
- Late cardiac and second-malignancy burden of the irradiated arm
📚 Sources · 📄 1 paper
Abstract
EORTC 22033-26033/NCIC-CTG/TROG/MRC-CTU
ForClinical high-risk WHO grade 2 glioma, first-line, molecularly classified
No significant difference
PFS and OS both ns between RT and TMZ arms; effect size not reported in source
TL;DRMature phase III: RT (50.4Gy/28fx) vs dose-dense TMZ in high-risk WHO grade 2 LGG, no PFS or OS difference in any molecular subtype.
The RT-relevant read is what this does NOT license: single-modality TMZ never beat RT, so deferring 50.4Gy/28fx to spare late toxicity buys nothing on PFS or OS. IDH wild-type was the one split (OS 2.5 vs 4.7 yrs, HR 0.47 [0.27-0.82], P=.0068), post hoc and n=64, and those tumors now grade as GBM.
In molecularly classified high-risk WHO grade 2 glioma being planned for first-line therapy, this supports neither leading modality over the other and does not address the combined-modality RT plus alkylator approach that is standard for IDH-mutant astrocytoma. The longer read
50.4Gy in 28fx as sole therapy was not beaten by TMZ, so deferring RT to postpone late neurocognitive cost does not buy an outcome advantage. The trial says nothing about RT dose, target volume or the combined-modality regimen a high-risk grade 2 astrocytoma now receives, so it does not move the modern RT decision, only closes the omission argument.
Dose-dense TMZ 75 mg/m² 21/28d for up to 12 cycles as sole first-line therapy is equivalent, not superior, to RT, and the schedule was never tested against the combined-modality standard. The IDH wild-type OS advantage (2.5 vs 4.7 yrs, HR 0.47 [0.27-0.82]) is post hoc in n=64 tumors that now classify as GBM.
8 details 2 trials watching
Randomised phase III, four-group intergroup trial (EORTC/NCIC-CTG/TROG/MRC-CTU), N=478, comparing two single-modality first-line strategies. This is the mature analysis; a post hoc reclassification to 2021 WHO criteria was possible in 73% (351/478) with analyzable tissue.
Clinical high-risk WHO grade 2 low-grade glioma, treatment-naive. Post hoc molecular strata: IDHmt/1p19q non-codeleted astrocytoma n=178, IDHmt/1p19q codeleted oligodendroglioma n=109, IDH wild-type n=64.
Standard fractionation, 28 × 1.8 Gy (50.4 Gy), delivered as the entire assigned treatment. No concurrent or adjuvant systemic therapy in the RT arm, which is the gap between this trial and how grade 2 glioma is treated now.
Dose-dense temozolomide 75 mg/m² once daily, 21 of 28 days, up to 12 cycles, given as sole first-line therapy with RT withheld.
progression-free survival. Overall survival and differential response by molecular marker were the mature-analysis questions.
No significant difference in PFS or OS between arms, and the null held across every molecular subtype except IDH wild-type, where OS favored TMZ.
| Subtype (n) | RT | TMZ | HR |
|---|---|---|---|
| IDHmt astrocytoma, non-codel (n=178) | 6.6-6.7 yrs (either arm) | 6.6-6.7 yrs (either arm) | 0.67-1.44, P=.93 |
| IDHmt oligodendroglioma, 1p/19q codel (n=109) | 12.9 yrs (9.4-NR) | 14.9 yrs (10.1-NR) | 0.88 (0.52-1.49), P=.63 |
| IDH wild-type (n=64) | 2.5 yrs (1.8-3.3) | 4.7 yrs (2.2-7.2) | 0.47 (0.27-0.82), P=.0068 |
RTOG 9802 established RT followed by PCV as the high-risk grade 2 benchmark, and combined-modality therapy is now standard for IDH-mutant astrocytoma. EORTC 22033 tested neither arm of that question: it asked which single modality to lead with, and answered that it does not matter.
Molecular strata are post hoc in 73% of the enrolled population, so subtype comparisons carry both selection and multiplicity risk. The IDH wild-type finding rests on n=64, and under 2021 criteria those tumors would not be enrolled as grade 2 at all.
The durable contribution is prognostic rather than therapeutic: median OS of 12.9-14.9 years in codeleted oligodendroglioma against 6.6-6.7 years in IDH-mutant astrocytoma quantifies how far molecular class outweighs modality choice. The finding that pts ≥40 fared better than <40 undercuts the age-40 cutoff that still gates high-risk definitions.
Mature randomised phase III, endpoint negative in both arms and across molecular subtypes; the IDHwt survival difference is post hoc, n=64.
- Optimal sequencing of RT and alkylator in IDH-mutant astrocytoma
- Whether IDH inhibitors displace upfront RT in low-risk grade 2 glioma n=90 · primary completion 2027-10 · PROs: vorasidenib vs RT vs surveillance in grade 2 IDH-mutn=150 · primary completion 2031-11 · real-world vorasidenib, grade 2, no immediate RT need
- Late neurocognitive cost of combined-modality vs single-modality
📚 Sources · 📄 1 paper
Abstract
ReCOG HNSCC Reirradiation Consensus
TL;DR24 of 31 (77%) statements reached ≥85% agreement: no ENI, definitive IMRT ~66 Gy, postop ~60 Gy, SBRT ~40 Gy in five fractions.
RTOG 9610RTOG 9911GORTEC 2008–01GORTEC 98–03GORTEC-GETTEC
Subsite, not only volume, gates SBRT: in Vargo's 291-pt series severe toxicity reached up to 50% for laryngeal or hypopharyngeal recurrences vs 6-20% at other subsites, which is the basis for the 94% caution statement. Postop SBRT data are thin (n=28), which is why IMRT is preferred after salvage surgery.
For a recurrence 6-12 months after prior RT, this supports reirradiation only when disease is small, localised, and outside high-dose regions after MDT review; it does not extend to recurrence within 6 months outside urgent palliation, or to nasopharyngeal primaries. The longer read
Subsite, not only volume, gates SBRT: in Vargo's 291-pt series severe toxicity reached up to 50% for laryngeal or hypopharyngeal recurrences vs 6-20% at other subsites. Postop SBRT data are thin (n=28), so IMRT is preferred after salvage surgery.
8 details 1 trial watching
International expert consensus: a ReCOG core group drafted statements, then a 17-member radiation oncology panel voted once on 31 statements. Thresholds were high ≥85%, moderate 70-84%, low <70%, with no-opinion votes counted in the denominator. 24 (77%) reached high consensus.
Recurrent or second primary HNSCC in a previously irradiated field, covering definitive and postoperative reirradiation. Nasopharyngeal cancer and rare histologies excluded. Evidence levels adapted from Oxford CEBM, level 1 (randomised) to level 4 (expert consensus).
Definitive: CTV = GTV + 5 mm, no ENI, IMRT ~66 Gy for >25 cc, IMRT or SBRT for ≤25 cc, SBRT ~40 Gy in five fractions. Postoperative: primary-RT CTV rules, IMRT preferred, ~60 Gy. Cumulative doses in EQD2 with α/β 2-3 Gy, voxel-wise summation with DIR when available, with conservative manual point-dose addition acceptable otherwise.
Carotid: avoid cumulative EQD2 >120-125 Gy (α/β=2); encasement >180° and prior ulceration add risk. Mandible: ORN risk rises above 114-119 Gy EQD2. Cord/brainstem: D0.1 cc ≤50 and ≤55 Gy as targets, ~60 Gy at the surface case by case, recovery factors (10-25%) only with caution.
Split-course chemo-reRT in RTOG 9610 and RTOG 9911 gave 2-year OS of 15.2% and 25.9%, with grade 3-4 toxicity up to 34% and treatment-related mortality around 8%. The IMRT-era Ward cohort (n=412) reported median OS 16.5 mo with fatal toxicity in 1%. GORTEC-GETTEC (n=130), the randomised postop trial, improved locoregional control and RFS with no OS benefit.
Guidance for RPA class II and III rests largely on one retrospective RPA model, since most reirradiation outcome data come from RPA class I pts. The IMRT vs SBRT split and the dose statements come from non-randomised multi-institutional cohorts. The 10-25% recovery factor has very low evidence.
The seven moderate-consensus statements cluster on poor-prognosis subgroups, dose and fractionation, and SBRT, and the lowest agreement (70%) falls on cord and brainstem cumulative limits. The authors present dose thresholds and OAR constraints as pragmatic targets rather than validated limits. Sequencing reirradiation against first-line ICI has no randomised data.
| Statement | Consensus | Evidence level |
|---|---|---|
| Review prior RT plan: in-field vs marginal failure | High (100%) | 3 |
| Recurrence <6 mo: generally not advised, except urgent palliation | High (100%) | 2 |
| Recurrence 6-12 mo: only small, localised, outside high-dose regions, after MDT | High (88%) | 2 |
| RPA I with positive margins or ECE: consider postop reRT | High (100%) | 2 |
| R0 unlikely even without clearly positive margins: reRT can be considered | Moderate (82%) | 4 |
| RPA III: generally no curative-intent reRT | Moderate (76%) | 3 |
| Statement | Consensus | Evidence level |
|---|---|---|
| Postop: normofractionated IMRT preferred over SBRT | High (94%) | 3 |
| RPA II unresected ≤25 cc (cT1-T2): IMRT or SBRT similar | High (88%) | 3 |
| RPA II unresected >25 cc: IMRT over SBRT | High (88%) | 3 |
| SBRT with caution for unresected larynx or hypopharynx | High (94%) | 3 |
| Concomitant chemo case by case, large tumours in fit pts | High (88%) | 3 |
| Protons in selected cases to spare OARs | High (88%) | 3 |
| Brachy for <25 cc oral cavity or oropharynx, expert centres | High (88%) | 3 |
| Statement | Consensus | Evidence level |
|---|---|---|
| Definitive: CTV = GTV + 5 mm | High (94%) | 4 |
| Postop high-risk CTV: same rules as primary RT | Moderate (82%) | 4 |
| No elective nodal irradiation | High (100%) | 3 |
| Definitive IMRT: 66 Gy commonly used | Moderate (82%) | 4 |
| Hyperfractionated IMRT: an option, no clear benefit | Moderate (76%) | 3 |
| Postop: 60 Gy commonly used | High (94%) | 3 |
| SBRT: ~40 Gy in five fractions | Moderate (76%) | 3 |
| Statement | Consensus | Evidence level |
|---|---|---|
| Carotid: avoid cumulative EQD2 >120-125 Gy (α/β=2) | High (94%) | 3 |
| Carotid encasement >180° or prior ulceration raises blowout risk | High (100%) | 3 |
| Mandible: ORN risk rises above cumulative EQD2 114-119 Gy | High (100%) | 3 |
| Cord/brainstem recovery factors (10-25%): caution, document | High (88%) | 4 |
| Target cumulative EQD2 D0.1 cc ≤50 Gy cord, ≤55 Gy brainstem | Moderate (70%) | 4 |
| ~60 Gy at cord or brainstem surface, case by case | High (94%) | 4 |
| RPA class | Definition | n | 2-yr OS |
|---|---|---|---|
| I | Recurrence >2 yr after RT, salvage surgery | 91 | 61.9% |
| II | Unresected >2 yr, or <2 yr without organ dysfunction | 230 | 40.0% |
| III | <2 yr plus feeding tube or tracheostomy dependence | 81 | 16.8% |
| Dose | 2-yr OS |
|---|---|
| ≥66.0 Gy | 49.3% |
| 60.0-65.9 Gy | 34.2% |
| <60.0 Gy | 30.4% |
- Sequencing of reirradiation vs first-line immune checkpoint inhibitors recruiting Re-Radiochemotherapy and Pembrolizumab vs. Immuno(Chemo)Therapy for Locoregionally Recurrent PD-L1 Positive (CPS≥1) HNSCC Phase 3n=214 · primary completion 2032-12 · phase 3 re-RCT then pembro vs pembro ± chemo, OS
- Proton therapy vs IMRT outcomes in reirradiation
- Validated cumulative cord and brainstem constraints and recovery factors
📚 Sources · 📄 1 paper
BART
ForPost-cystectomy MIBC, pT3-4 / pN+ / R+, chemo-treated, no adjuvant IO
87.1% vs 76.0%
HR 0.43, 95% CI 0.20-0.96, p=0.04
TL;DR2yr LRFFS 87.1% vs 76.0% with adjuvant pelvic RT after cystectomy, HR 0.43 (0.20-0.96), p=0.04; OS unchanged.
Reported via UroToday →
The RT read is the per-protocol and subgroup magnitude: LRFFS HR 0.27 (0.10-0.71) among those actually irradiated, and HR 0.22 (0.06-0.75) in pN+. Target was cystectomy bed plus full pelvic nodes to 50.4Gy/28fx with stoma-sparing IMRT, a plan deliverable in standard practice, and late G3+ toxicity was 8.4% vs 10.5%. That moves the offer-RT decision for pN+ disease.
In pN+ or pT3-4 urothelial MIBC after cystectomy and cisplatin-based chemotherapy, this supports discussing adjuvant pelvic RT for locoregional control; it does not inform pts receiving adjuvant nivolumab, who were unrepresented here. The longer read
The deliverable read is technique plus magnitude: 50.4Gy/28fx to cystectomy bed and full pelvic nodes with stoma-sparing IMRT and daily IGRT, late G3+ 8.4% vs 10.5%, LRFFS HR 0.22 (0.06-0.75) in pN+. This moves the offer-adjuvant-RT decision for pN+ or margin-positive disease.
Chemotherapy was neoadjuvant in 71% and adjuvant in 20%, and no pt received immunotherapy, so this speaks to a failure mode the chemo backbone did not cover: 26% locoregional recurrence under observation. It does not change regimen choice, but it questions whether adjuvant nivolumab alone addresses pelvic failure.
With a median 20 nodes dissected and a 4.6% positive margin rate, locoregional recurrence still reached 26% without RT, so this is not attributable to inadequate surgery. For pT3-4, pN+, or R+ specimens, it argues for referral for adjuvant RT discussion rather than surveillance alone.
12 details 2 trials watching
Phase III multicenter RCT, 1:1 adjuvant radiotherapy versus observation, N=153 accrued 2016-2024 (RT 77, observation 76). Stratified by nodal stage (N0 vs N+) and chemotherapy timing. Median follow-up 47 months; per-protocol comparison by log rank, with Fine-Gray competing-risk subdistribution HRs for LRFFS (competing risks distant metastases, non-cancer death) and DFS.
High-risk non-metastatic urothelial MIBC post radical cystectomy: T3-4, N1-3, or R+. 62% pT3-T4, 41% pN+, variant histology component in 28%. Median age 57, median nodes dissected 20, positive margin rate 4.6%, neobladder in 2.6%.
Chemotherapy was neoadjuvant in 71% and adjuvant in 20%; 9.2% received none. No patient received immunotherapy in either arm.
50.4Gy in 28 fractions to the cystectomy bed and pelvic nodes. CTV covered common iliac, internal and external iliac, presacral and obturator nodes plus the cystectomy bed. Stoma and bowel sparing IMRT with daily onboard image guidance. 63 of 77 allocated received planned RT.
Primary: 2-year locoregional failure-free survival. Secondary: bladder cancer-specific survival, disease-free survival, overall survival.
Primary endpoint met. Overall 37% recurred, 18% locoregionally (8% RT vs 26% observation, p=0.006), and there were no isolated locoregional recurrences in the RT arm. Survival endpoints all favored RT numerically without reaching significance.
| Endpoint | Adjuvant RT | Observation | Effect size |
|---|---|---|---|
| LRFFS (primary) | 87.1% | 76.0% | HR 0.43 (0.20-0.96), p=0.04 |
| LRFFS per protocol | 93.2% | 75.0% | HR 0.27 (0.10-0.71), p=0.008 |
| DFS | 71.6% | 58.7% | HR 0.62 (0.36-1.05), p=0.07 |
| Bladder cancer-specific survival | 79.6% | 65.0% | HR 0.59 (0.33-1.10), p=0.09 |
| Overall survival | 70.4% | 57.4% | HR 0.78 (0.49-1.26), p=0.31 |
Grade 3 GI events were low and no higher with RT (1.6% vs 4.1%); the cost was grade 2 GI (17.5% vs 1.4%) with no toxicity-related discontinuation. Late grade 3+ toxicity was similar (8.4% vs 10.5%, p=0.60).
The comparator that defines current adjuvant practice is CheckMate 274 (adjuvant nivolumab), which no BART patient received, so this addresses a locoregional failure mode nivolumab was never shown to control. Prior adjuvant RT evidence in this space is the smaller Egyptian NCI randomised experience; BART is described as the largest RCT here.
Accrual over eight years fell short of target, so the survival endpoints are underpowered rather than negative: the OS CI (0.49-1.26) is compatible with both a substantial benefit and modest harm. 14 of 77 allocated to RT never received it and were analyzed with observation (n=90), which is the per-protocol comparison the headline HR 0.27 comes from.
This establishes that pelvic RT after cystectomy does what RT does elsewhere: it controls the field it treats, at an acceptable late-toxicity cost. What it does not establish is whether preventing a locoregional recurrence in a disease this systemically aggressive translates into survival, which the planned MERCY IPD meta-analysis is meant to answer.
CONSORT flow
Randomised, primary endpoint met, prespecified stratification. Adjuvant RT is not standard post-cystectomy; this is the first positive phase III. Underpowered for OS, no IO backbone.
- Does locoregional control translate into an overall survival benefit active Adjuvant Radiotherapy in Patients With Pathological High-risk Bladder Cancer (GETUG-AFU 30) Phase NAn=81 · primary completion 2027-12 · randomised adjuvant pelvic RT post-RC + PLND
- Adjuvant radiotherapy combined with adjuvant immunotherapy recruiting Adjuvant Concurrent Immunotherapy and Radiotherapy for the Treatment of Bladder Cancer Phase 1n=10 · primary completion 2027-04 · phase 1 concurrent adjuvant IO + RT safety
- Generalizability to older pts with limited lymphadenectomy
📚 Sources · 📄 1 paper
Abstract
ENZARAD (ANZUP 1303)
ForHigh-risk localized/locally-advanced prostate, EBRT candidates, 2yr ADT
HR 0.88
95% CI 0.67-1.15, p=0.34; 8yr 74% vs 72%, did not meet 1° EP
TL;DR8yr MFS 74% vs 72%, HR 0.88 (0.67-1.15), p=0.34: enzalutamide added to 2yr ADT + RT missed its primary endpoint.
Reported via UroToday →
The signal tracks the pelvic field, not the drug: MFS HR 0.47 (0.29-0.76) with pelvic RT planned and 0.43 (0.20-0.92) in cN1, both declared before randomization. RT was 78Gy or 46Gy plus brachy boost with 46Gy elective nodes for cN1, so this transfers directly. It moves the intensification decision toward pts you were already covering nodally.
In cN1 or node-covered high-risk localized prostate going to 2yr ADT plus definitive EBRT, this supports adding enzalutamide; in cN0 prostate-only fields, including 'very high-risk' by Gleason and PSA, it does not. The longer read
The benefit tracks the field, not the risk label: MFS HR 0.47 (0.29-0.76) where pelvic RT was planned, versus 0.85 (0.64-1.13) in 'very high-risk' disease. RT was 78Gy or 46Gy plus brachy boost, with 46Gy elective nodes plus gross nodal boost for cN1, so it maps onto standard practice. It ties the intensification call to your nodal coverage decision.
Enzalutamide x24mo was tested against an active NSAA x6mo, not ADT alone, so the flat all-comer MFS HR 0.88 argues against routine ARSI substitution rather than against intensification in general. The cN1 MFS HR 0.43 (0.20-0.92) is where the drug earns its place. Sequencing and biomarker selection remain open.
11 details
International investigator-initiated phase 3, N=802 from 8 countries, accrued March 2014 to June 2018, median follow-up 8 years. Powered at 80% for an HR 0.67. Primary was changed from OS to MFS during the trial because deaths ran below projection.
High-risk clinically localized or locally-advanced disease suitable for EBRT: 90% Gleason 8-10, 36% PSA >20 ng/ml, 12% cN1 by conventional imaging. 40% planned for pelvic RT and 8% for a brachytherapy boost.
Experimental: enzalutamide 160 mg daily x 24 months plus LHRH agonist x24 months. Control: conventional NSAA x6 months plus LHRH agonist x24 months. The control is an active antiandrogen, not ADT alone.
Prostate to 78Gy, or 46Gy plus brachytherapy boost, starting 16 weeks after hormonal therapy. Pelvic nodal RT required for cN1 (46Gy elective nodes plus boost to gross nodes) and optional for cN0 but declared before randomization. QA was unusually tight: credentialing, benchmarking, real-time review of the first 5 plans per site, then 20% random sampling.
Primary: MFS. Secondary: OS, CSS, PSA PFS, clinical PFS, castration resistance, HRQoL, adverse events, cost-effectiveness. Main effects by unstratified log-rank at alpha=0.05, Cox HRs, all p-values nominal without multiplicity adjustment, five prespecified subgroups tested by interaction.
Primary MFS not met. PFS favored enzalutamide at a nominal p=0.044 and OS was flat; the subgroup detail sits in the table above.
| Subgroup | MFS HR (95% CI) | OS HR (95% CI) |
|---|---|---|
| cN1 (regional nodes) | 0.43 (0.20-0.92) | 0.46 (0.17-1.26) |
| Pelvic field RT planned | 0.47 (0.29-0.76) | 0.53 (0.30-0.95) |
| 'Very high-risk' | 0.85 (0.64-1.13) | 0.81 (0.57-1.13) |
STAMPEDE's abiraterone-based intensification in non-metastatic high-risk disease produced an MFS HR 0.53 against ENZARAD's 0.88, and the ENZARAD cN1 subgroup HR mirrors the STAMPEDE result. The gap plausibly reflects population, not drug: cN1 11% vs 39%, median PSA 14 vs 35 ng/ml, cT3-4 47% vs 92%.
The pelvic-RT subgroup is not a clean randomized comparison of pelvic coverage: it carried 28% N1 and 62% Gleason 9/10 against 0% N1 and 49% Gleason 9/10 in the no-pelvic-RT group, so risk enrichment and biological interaction are entangled. The presenter named both explanations and could separate neither.
Two prespecified subgroups moving together on MFS and OS, with OS HRs tracking MFS HRs as ICECaP surrogacy predicts, is more internally consistent than a lone subgroup blip. It still does not establish that enzalutamide works only when the pelvis is treated.
Adequately powered phase 3 missed its primary MFS endpoint against an active NSAA control; benefit rests on two prespecified subgroups with overlapping risk composition.
- Which pelvic-RT subgroups drive the enzalutamide benefit
- Biomarkers identifying who needs ARSI intensification
- Whether pooled ARPI trial data confirms the nodal signal
📚 Sources · 📄 1 paper
Abstract
ARS Appropriate Use Criteria: Locoregionally Recurrent Rectal Cancer
TL;DRUpdated ARS appropriate use criteria for LRRC, built on 116 references (10 randomized phase 2/3), reaffirming combined-modality therapy toward R0 resection.
The RT-relevant content sits in PICO question 4 (role of RT/reirradiation), but the excerpt stops before the appropriateness ratings, so dose, fractionation and reirradiation technique recommendations are not reported in source text. What is stated: preoperative RT, systemic therapy, or both are positioned as tools to raise the odds of an R0 resection, which frames RT as resectability-directed rather than definitive.
In a previously irradiated patient with pelvic sidewall or presacral recurrence being staged for salvage, this frames preoperative RT or chemoRT as a means to margin-negative resection; it does not settle reirradiation dose or the nonoperative alternative. The longer read
RT is framed as resectability-directed: preoperative RT, systemic therapy, or both to raise the odds of R0. The reirradiation question (PICO 4) is posed but its appropriateness ratings, dose and technique are not in the source excerpt, so the decision a previously irradiated pelvis actually turns on is not reportable here.
Preoperative systemic therapy sits alongside RT as a downsizing tool rather than a competing pathway, and immunotherapy is named within the PICO question on systemic therapy. Specific regimen and sequencing ratings are not in the source excerpt.
The document is explicitly resection-centered: margin-negative resection is called the ultimate determinant of survival and local control. Resectability assessment by compartment, sidewall, sacral and visceral involvement on MRI drives the operative approach, with everything preoperative judged by whether it makes R0 more likely.
10 details 5 trials watching
Literature-based systematic review plus RAND/UCLA modified Delphi appropriateness rating, run under the standing ARS AUC methodology with PICOTS framing and PRISMA 2020 assessment. Two rounds of voting; ratings collapse to usually not appropriate, may be appropriate, usually appropriate.
Locoregionally recurrent rectal cancer. Eligible evidence was prospective observational, phase 2/3, and retrospective series of at least 25 patients, published January 1, 2013 to July 16, 2025, English language, animal studies excluded.
There is no efficacy endpoint. The output is an appropriateness rating per treatment option across five PICO questions: surgery, preoperative/perioperative therapy, nonoperative management, RT/reirradiation, and systemic therapy.
116 references carried the evidence: 10 well-designed randomized phase 2/3, 29 moderately well designed, 76 retrospective, 1 meta-analysis. The committee's stated conclusion is that margin-negative resection is the ultimate determinant of survival and local control, with preoperative systemic therapy, RT, or both used to facilitate it.
| Study design | n |
|---|---|
| Well-designed (randomized phase 2 and phase 3) | 10 |
| Moderately well designed (matched cohort, phase 2) | 29 |
| Design limitations (retrospective) | 76 |
| Meta-analysis | 1 |
Two thirds of the evidence base (76 of 116) is retrospective, so a modified Delphi vote is doing work the trials cannot. The document is an executive summary: the per-scenario appropriateness grid, which is the part a reader would carry to tumor board, is not in the source excerpt available here.
The committee explicitly declines to move practice, framing the update as reassurance about combined-modality therapy rather than a new position. For a radiation oncologist the operative question is where RT sits relative to surgical resectability, and the summary answers it in one direction only: RT is a means to R0, not an alternative to it.
- Role of nonoperative management in LRRC recruiting Radiotherapy Dose Escalation for Non-operative Management of Unresectable Locally Recurrent Rectal Cancer (STEP-UP) Phase NAn=30 · primary completion 2029-12 · RT dose escalation for unresectable LRRC, no surgery
- Optimal reirradiation dose and technique in previously irradiated pelvis recruiting Pencil Beam Proton Therapy for Pelvic Recurrences in Rectal Cancer Patients Previously Treated With Radiotherapy Phase 2n=65 · primary completion 2025-10 · dose-escalated proton reRT, prior pelvic RT >30Gy EQD2n=31 · primary completion 2025-12 · carbon ion reRT 74Gy/20Fx, unresectable LRRCrecruiting Hypofractionated Radiotherapy Plus Immunotherapy Versus Conventional Radiotherapy in Locally Recurrent Rectal Cancer Phase 2n=221 · primary completion 2030-03 · randomised 15-30Gy/5Fx reRT vs conventional RT
- Preoperative chemoRT vs systemic therapy alone before salvage resection n=44 · primary completion 2028-12 · preop chemoRT + PD-1 then radical salvage surgery
📚 Sources · 📄 1 paper
Abstract
INDIBLADE
ForStage II/III cT2-4aN0-2 MIBC, bladder-preservation candidates
78% at 2yr
0.67-0.9
TL;DR2yr bladder-intact EFS 78% (0.67-0.9) after induction ipi/nivo then chemoRT in cT2-4aN0-2 MIBC; 2yr OS 96% (0.91-1).
The RT-relevant gap is technique: the source gives no dose, fractionation, radiosensitizer, or whether the pelvic nodes were covered, and the cohort explicitly includes N1-2 and cT4a, so elective nodal coverage is exactly the parameter a reader needs and does not get. Bladder-intact EFS 78% at 2yr is the endpoint that gates preservation counselling.
In cT2-4aN0-2 MIBC where bladder preservation is already on the table, this supports discussing induction ipi/nivo before chemoradiation as investigational sequencing; it does not extend to cystectomy-eligible pts choosing surgery, nor to cT4b or M1 disease.
Technique is the missing variable: no dose, fractionation, or target volume, and with cT4a and N1-2 admitted, whether the pelvic nodes were treated is the parameter that decides whether 78% bladder-intact EFS transfers. Until that is published, this changes counselling tone, not planning.
Dual checkpoint blockade as induction, not concurrent or adjuvant, is the sequencing question here, and pts still completed chemoradiation afterwards. Cycles and dosing are not in source, so the regimen is not yet reproducible; 2yr OS 96% argues the sequence is at least deliverable.
Bladder-intact EFS 78% at 2yr bears on which cT2-4aN0-2 pts get offered preservation instead of upfront radical cystectomy. Salvage cystectomy rate is not reported in source, so the number that matters most for surgical planning, how many came to the OR anyway, is missing.
9 details
Single-arm bladder-preservation study of induction ipilimumab plus nivolumab followed by chemoradiation. Phase, N, number of sites and median follow-up are not reported in the source tweet; results are read out at 2 years.
Stage II/III muscle-invasive bladder cancer, cT2-4aN0-2. That range admits both node-positive and cT4a disease, a broader population than many bladder-preservation series. No further eligibility, performance status or baseline detail in source.
Induction ipilimumab + nivolumab, then chemoradiation. Dosing, number of induction cycles, and the concurrent radiosensitizer are not reported in source.
The chemoradiation component is named but not specified: no total dose, fractionation, technique, or target volume. Whether the cT4a and N1-2 pts received elective pelvic nodal coverage is unstated, which is the parameter that most gates transfer to another practice.
Primary read: 2yr bladder-intact event-free survival, 78% (0.67-0.9). 2yr OS 96% (0.91-1). Whether the trial prespecified bladder-intact EFS as its primary endpoint is not stated in source.
The 96% 2yr OS sits well above what an unselected cT2-4aN0-2 population would predict, which points at selection; the source reports no eligibility filter to judge that against. With no cystectomy or pathologic-response denominator reported, bladder-intact EFS cannot be separated into pts who never needed salvage vs pts who declined it.
The claim on offer is that adding induction ipi/nivo raises the ceiling of trimodality therapy, but a single arm cannot isolate the immunotherapy's contribution from the chemoradiation backbone. What it does establish is feasibility: pts got through induction dual checkpoint blockade and still completed CRT, with 2yr OS 96%.
Single-arm induction immunotherapy plus CRT with 2yr follow-up and wide CI; no randomised comparator against standard chemoradiation or cystectomy.
- Salvage cystectomy rate and pathologic response not reported
- Immunotherapy contribution over chemoradiation alone unproven
- Nodal coverage and RT dose for cT4a/N1-2 pts unstated
📚 Sources · 🐦 1 tweet
‼️ INDIBLADE: stage II/III (cT2-4aN0-2) MIBC -> induction ipilimumab plus nivolumab -> CRT
— NonsparseOncologist (@5_utr) June 17, 2026
2-year bladder-intact event-free survival is 78% (0.67−0.9) 🤩
2-year overall survival was 96% (0.91−1)
Lots of bladders can be potentially spared!https://t.co/LzTe72GYHD
DOREMY NCT02106312
ForLocalized translocation-confirmed myxoid liposarcoma, trunk or extremity, resectable
TL;DR5yr LRFS 97.4% after 36Gy/18fx preop RT in myxoid liposarcoma, wound complications 21%, median f/u 66.4mo.
The number that moves the dose decision is 97.4% 5yr LRFS at 36 Gy, matched to a 21% wound complication rate, with only 3% late G3. Dose is 2 Gy daily to 36 Gy preop, standard fractionation, so it transfers directly. This is a de-escalation read confined to translocation-confirmed MLS.
In localized translocation-confirmed myxoid liposarcoma of trunk or extremity going to resection, this supports 36 Gy preop as a discussed option in place of 50 Gy; it does not extend to other soft tissue sarcoma histologies, which were not enrolled. The longer read
36 Gy in 2 Gy daily fractions preop yielded 97.4% 5yr LRFS (95% CI 93.9-100%) at median 66.4 mo, with late G3 in only 3%. Standard fractionation, no special technique required, so the de-escalation from 50 Gy transfers directly in translocation-confirmed MLS.
The surgical read is the wound complication rate: 21% overall, 16% needing intervention, after preop RT at the reduced dose. Whether that beats 50 Gy is untested here (no comparator arm), but it is the number to weigh against reconstruction planning in trunk and extremity resections.
10 details 1 trial watching
Prospective, single-group, phase 2 nonrandomized trial across 9 tertiary sarcoma centers in Europe and the US. Enrollment ran November 2010 to May 2020; data analyzed January to December 2025. Median follow-up 66.4 months (IQR 48.8-87.5).
Adults with biopsy-proven and translocation-confirmed localized myxoid liposarcoma of the trunk or extremity. N=90, mean age 47 (SD 13.1), 50 (56%) male.
Preoperative RT to a reduced dose of 36 Gy in once-daily 2-Gy fractions, followed by resection. Delivered per protocol in all patients. Three pts (3%) did not proceed to surgery because of intercurrent metastatic disease.
Long-term local recurrence-free survival, progression-free survival, disease-specific survival, overall survival, and late toxic effects. No single stated primary endpoint for this long-term analysis.
Wound complications in 18 pts (21%), with 14 (16%) requiring intervention. Late toxic effects were grade 2 in 13 pts (15%) and grade 3 in 3 pts (3%).
The authors argue the long-term data support adopting 36 Gy as an option through shared decision-making, explicitly on the grounds that a phase 3 trial is impractical in a rare cancer. That is an argument about feasibility, not about evidence level, and the reader should price it as such.
Fourteen-year accrual window spans changing surgical and imaging practice, so the wound complication rate reflects a long era rather than current technique. Late toxicity is reported only as pooled grade counts, without organ or site attribution, which limits comparison against 50 Gy series.
| Endpoint | 5yr rate | 95% CI |
|---|---|---|
| Local recurrence-free survival | 97.4% | 93.9-100% |
| Progression-free survival | 81.0% | 72.6-89.4% |
| Disease-specific survival | 89.5% | 82.6-96.4% |
| Overall survival | 88.5% | 81.2-95.8% |
Single-arm phase 2, no randomised 50 Gy comparator; authors concede phase 3 impractical in a rare histology. Long f/u strengthens but does not replace randomisation.
- Wound complication rate vs 50 Gy in a randomised comparison n=300 · primary completion 2031-01 · prospective MLS registry, 36Gy vs 50Gy preop arms
- Whether dose reduction extends to other translocation-driven sarcoma subtypes
- Local control beyond 10 years
📚 Sources · 📄 1 paper
Abstract
REVELUTION
ForNon-metastatic intermediate/high-risk prostate cancer receiving definitive RT + ADT
68.9 mm³ adjusted mean difference
Leuprolide vs relugolix; crude 56 vs 25 mm³. CI/p not reported in source
TL;DRAdjusted 12-mo total plaque volume rose 68.9 mm³ more with leuprolide vs relugolix in men getting prostate RT.
Reported via UroToday →
Every man here got prostate ± pelvic nodal RT, so this is an RT-clinic decision, not a med-onc one: for the 6-month ADT course you prescribe alongside definitive RT, the agonist added 68.9 mm³ of adjusted total plaque volume at 12 months, driven by non-calcified plaque. A radiation-alone control cohort was enrolled in parallel, though its comparison was not reported in source.
For the intermediate/high-risk man starting definitive prostate RT with 6+ months of concurrent ADT, particularly with elevated ASCVD 10-year risk, this supports weighing agent choice on cardiovascular grounds; it says nothing about ADT duration or about men on ADT without RT. The longer read
The entire cohort received prostate ± pelvic nodal RT, so this is your ADT prescription, not someone else's: the agonist added 68.9 mm³ of adjusted total plaque volume at 12 months, driven by non-calcified plaque. It moves agent selection for the 6-month course accompanying definitive RT, particularly in men with elevated baseline ASCVD risk.
This supplies the missing mechanism under HERO's MACE difference: comparable testosterone suppression, divergent coronary plaque trajectory, with the signal in non-calcified rather than calcified plaque. It argues the agonist-antagonist cardiovascular gap is pharmacologic rather than an artifact, though the population here is non-metastatic and radiotherapy-treated.
Also covered Sep 30
11 details 4 trials watching
Single-institution, parallel-cohort, open-label randomized trial across four Emory-affiliated centers, enrolling June 2020 to 2024. ADT-eligible pts randomized 1:1 relugolix vs leuprolide, stratified by ASCVD 10-year risk score; a parallel prospective RT-alone cohort was enrolled as control.
94 men with non-metastatic prostate cancer, intermediate and high risk, all treated with pelvic radiotherapy to the prostate with or without pelvic nodes. Lower-risk men eligible for definitive RT alone without planned ADT formed the parallel arm.
Relugolix 360 mg day 1, then 120 mg daily; leuprolide in 3-month depots. ADT given for at least six months, longer by cancer risk tier.
All pts received pelvic radiotherapy to the prostate with or without the pelvic lymph nodes. Dose, fractionation and technique are not reported in source.
Primary: change in total plaque volume. Secondary: changes in plaque subtypes (non-calcified, calcified, low-attenuation). Serial CCTA at baseline (within 7 days of treatment start) and 12 months, blinded to arm, quantified by the automated HeartFlow tool; 12-month mean difference by ANCOVA adjusted for age, statin use and baseline plaque volume.
The adjusted total-plaque-volume difference of 68.9 mm³ favouring relugolix was driven mainly by non-calcified plaque; calcified and low-attenuation plaque showed no significant difference with low absolute change. Per-arm CIs and p-values are not reported in source.
| Measure | Leuprolide | Relugolix |
|---|---|---|
| Total plaque volume, crude difference | 56 mm³ | 25 mm³ |
HERO (2020) showed a lower MACE rate with relugolix vs leuprolide and drove the FDA approval, but offered no mechanism, since both agents suppress testosterone comparably and share the hypogonadal metabolic profile. REVELUTION supplies the candidate mechanism, accelerated coronary atherosclerosis under GnRH agonism, consistent with the 2010s observational signal that agonists carry higher cardiovascular risk than orchiectomy.
The imaging endpoint is validated as a predictor of MACE, not a substitute for it, and 12 months is short for plaque trajectories. The parallel RT-alone cohort was not randomized against either ADT arm, so the no-hormone comparison is observational and cannot isolate radiotherapy's own contribution to plaque change.
If the agonist-antagonist difference is real and mechanistic, the decision it moves is which ADT agent accompanies definitive RT in a man with baseline cardiovascular risk, not whether to give ADT at all. It does not establish that changing agent prevents events; that inference still rests on HERO.
Small single-institution randomized trial with an imaging surrogate (plaque volume), not clinical MACE. Supplies a mechanism for HERO rather than independent outcome evidence.
- Does the plaque difference translate to fewer clinical cardiovascular events recruiting Effects of Relugolix vs Leuprolide on Cardiac Function in Patients With Prostate Cancer Phase 2n=70 · primary completion 2027-12 · relugolix vs leuprolide, cardiac MRI + performancerecruiting REVELUTION-2: Relugolix+Abiraterone Acetate (AA) Versus Leuprolide+AA Cardiac Trial Phase 3n=72 · primary completion 2029-07 · relugolix vs leuprolide + AA, cardiac CTA, pelvic RT
- Plaque trajectory beyond 12 months and after ADT completion n=100 · primary completion 2026-12 · randomised CCTA vs usual care, ADT >12mo planned
- Does pelvic radiotherapy itself contribute to coronary plaque change n=200 · primary completion 2029-11 · ADT cardiotox cohort enrolls with and without RT
📚 Sources · 📄 1 paper
Abstract
KEYNOTE-689 vs NIVOPOSTOP
TL;DREducational round-up contrasting perioperative pembro vs postoperative nivo in resectable LA-HNSCC; 3yr DFS ~63% vs 53% cited for NIVOPOSTOP.
KEYNOTE-689NIVOPOSTOP
RT is the constant in both frameworks, not the variable: cisplatin CRT stays the postoperative backbone and the question is only where IO is inserted around it. The source gives no dose, fractionation or target volume, and no in-field vs out-of-field failure data, so nothing here changes an RT plan.
Postoperative cisplatin CRT is unchanged in both designs; only the IO timing moves. With no dose, fractionation, target volume or locoregional failure data in the source, the radiation decision is untouched, though a neoadjuvant pembro window shifts the timing of adjuvant CRT initiation.
The two designs answer different sequencing questions: pembro started before surgery and continued through adjuvant CRT and maintenance, versus nivo added to postoperative CRT only in high-risk pathology. Only NIVOPOSTOP carries a number here, 3-year DFS approximately 63% vs 53%.
The perioperative design puts two cycles of pembrolizumab before resection, so the operation is delayed by a neoadjuvant window. The source reports no compromise in surgery completion but gives no numbers on delay, resectability, or margin status.

10 details 2 trials watching
- 🔍 Curator-shared teaching infographic (single-author X post), not a primary trial report or peer-reviewed review
- 🔍 Trial framing as presented in the graphic
Feature KEYNOTE-689 NIVOPOSTOP (GORTEC 2018-01) Drug Pembrolizumab Nivolumab Setting Perioperative (before + after surgery) Purely postoperative Population Resectable Stage III-IVA HNSCC High-risk resected HNSCC Control arm Surgery → RT/CRT Post-op CRT Primary endpoint Event-Free Survival (EFS) Disease-Free Survival (DFS) - 🔍 RT is fixed background in both: adjuvant cisplatin CRT in the KEYNOTE-689 experimental arm, postoperative cisplatin CRT in both NIVOPOSTOP arms
- 🔍 NIVOPOSTOP high-risk features listed
- Positive margins
- Extranodal extension (ENE)
- ≥4 involved nodes
- Extensive perineural invasion and other adverse pathological features
- 📊 NIVOPOSTOP: 3-year DFS approximately 63% vs 53% with standard CRT alone
- 📊 KEYNOTE-689: no effect size reported in source; graphic states only "significant improvement in EFS"
- ⚠️ No HR, CI, or p-value given for either trial in the source
- ⚠️ "3-year DFS approximately 63% vs 53%" is an approximation in the source, not a reported trial value
- ⚠️ No RT dose, fractionation, or target volume reported for either trial in source
- ⚠️ Graphic asserts higher PD-L1 CPS derives greater benefit with no supporting numbers
- Head-to-head of perioperative vs postoperative IO timing n=80 · primary completion 2029-02 · perioperative IO vs pembro + surgery + adjuvant RT
- Whether PD-L1 CPS should gate IO in resected HNSCC
- Locoregional failure patterns with IO added to postoperative CRT n=173 · primary completion 2025-11 · anti-PD-1 added to adjuvant CCRT, DFS primary
📚 Sources · 🐦 1 tweet
🧠 High-yield: KEYNOTE-689 vs NIVOPOSTOP
— Dr Rupam Manna MD (@DrRupamOncology) June 15, 2026
These two trials are redefining standards for resectable LA-HNSCC.
1/ KEYNOTE-689 (NEJM 2025)
Perioperative pembro → significant EFS benefit
First positive perioperative IO trial in >2 decades
2/ NIVOPOSTOP (ASCO 2025)
Post-op nivo +… pic.twitter.com/1mRQr9jmVX
GEC-ESTRO Breast Cancer Working Group APBI patient selection recommendations
TL;DRUpdated APBI selection criteria collapse to two groups (low-risk eligible, high-risk contraindicated), widening eligibility to pT1-2 ≤30mm, pN1mi, any histology.
The eligibility boundary moved, not the technique: pN1mi and multifocal disease within 2 cm are now inside the low-risk group, and the ceiling is 30 mm across all histologies. The 2010 intermediate tier is gone, so the contralateral question at consent is binary. BRCA 1-2 carriers are contraindicated regardless of age.
In a woman over 40 post-lumpectomy with a 25 mm pT2 pN1mi tumor and clear margins, this supports offering APBI where the 2010 criteria would not have; it does not extend to triple negative, BRCA carriers, or an unstaged axilla. The longer read
The eligibility boundary moved, not the technique: pN1mi and multifocal disease within 2 cm are now inside the low-risk group, with a 30 mm ceiling across all histologies. The intermediate tier is gone, so the APBI-vs-whole-breast conversation is binary. No dose, fractionation or target volume is specified in source.
Margin status is the surgical lever: a negative invasive margin qualifies, but DCIS requires ≥ 2 mm, so a close DCIS margin decides re-excision vs losing APBI eligibility. Unknown axillary status (pNx) is a contraindication, so skipping staging forecloses the option; pN1mi does not.
9 details
Evidence-based recommendation update from the GEC-ESTRO Breast Cancer Working Group. Systematic search 2010 to 2024 across PubMed, Medline, Scopus and Cochrane returned 618 articles, supplemented by reference lists, conference abstracts and book chapters. Ten prospective randomized trials and seven retrospective comparative studies with ≥ 5 yr median follow-up formed the evidence base.
Applies to pts after breast-conserving surgery being considered for partial breast irradiation. The low-risk group is age > 40 yr, unifocal or multifocal within 2 cm, pTis or T1-2 (≤ 30 mm), pN0 or pN1mi, all histology types, no EIC, no extensive LVI, negative invasive margins (≥ 2 mm for DCIS).
The document addresses who gets APBI, not how. No dose, fractionation, technique (brachytherapy vs external beam) or target-volume recommendation is given in the source text.
Two categories replace the prior scheme: low-risk good candidates and high-risk contraindicated. Contraindications are BRCA 1-2 mutation, age < 40 yr, positive invasive margins (< 2 mm for DCIS), multicentric or > 30 mm disease, triple negative, EIC positive, extensive LVI, and ≥ pN1a or pNx.
| Criterion | Low risk (APBI suitable) | High risk (APBI contraindicated) |
|---|---|---|
| Age | > 40 years | < 40 years |
| Germline | not specified | BRCA 1-2 mutation |
| T stage / size | pTis, T1-2 (≤ 30 mm) | > 30 mm |
| Focality | unifocal or multifocal within 2 cm | multicentric |
| Nodal status | pN0 or pN1mi | ≥ pN1a, or unknown axilla (pNx) |
| Histology | all histology types | triple negative |
| EIC | absent | EIC positive |
| LVI | no extensive LVI | extensive LVI |
| Margins | negative for invasive (≥ 2 mm for DCIS) | positive for invasive (< 2 mm for DCIS) |
Recommendation strength per criterion is not reported in the source text, so a reader cannot tell which thresholds rest on randomized data and which on panel opinion. The evidence base mixes ten randomized trials with seven retrospective comparative series without stated weighting.
The direction of travel is eligibility expansion: the authors state the 2010 criteria can be significantly expanded so more pts may receive APBI in routine practice. What the document does not settle is whether the widened boundary holds at the margins it moved most, node-micrometastatic and multifocal disease, where the randomized APBI trials enrolled few pts.
- IBTR outcomes for APBI in pN1mi disease
- Whether multifocal disease within 2 cm carries equivalent in-field control
- Whether triple negative warrants blanket APBI exclusion
📚 Sources · 📄 1 paper
Abstract
RTOG 0848 NCT01013649
ForResected pancreatic head adenocarcinoma, post 6 cycles adjuvant gemcitabine-based chemo
HR 0.96
90% CI 0.79-1.18, 1-sided P=.38; did not meet OS
TL;DRAdjuvant CXRT after 6 cycles gemcitabine-based chemo missed OS (HR 0.96), but node-negative pts gained: 5yr OS 48.1% vs 28.6%.
The whole RT read sits in 91 node-negative pts: 5yr OS 48.1% vs 28.6%, median OS 3.9 vs 3.0 yr, with interaction P=.022. Delivery was standard and QA'd (50.4 Gy/28 fx, tumor bed plus pancreatojejunostomy plus regional nodes, 81% IMRT), so the technique transfers directly. G4-5 toxicity was unchanged (6% v 5%).
In a resected pancreatic head adenocarcinoma pt who is node-negative and progression-free after adjuvant chemotherapy, this supports discussing CXRT; it does not extend to node-positive disease, where no treatment effect was seen, or to margin-positive pts (only 10 node-negative/margin-positive across both arms). The longer read
The RT signal is confined to 91 node-negative pts: 5yr OS 48.1% vs 28.6%, median OS 3.9 vs 3.0 yr, interaction P=.022. Technique transfers unchanged (50.4 Gy/28 fx, tumor bed plus pancreatojejunostomy plus regional nodes, 81% IMRT, real-time central review), and G4-5 toxicity was flat at 6% v 5%.
The systemic backbone dates the result: 67% got single-agent gemcitabine, 28% gemcitabine plus erlotinib, and no pt received FOLFIRINOX. Unselected CXRT after six cycles adds nothing (OS HR 0.96), so referral for adjuvant RT stays off the default path, though the grade 3 excess (38% v 19%) is GI and lymphopenic, not prohibitive.
10 details 2 trials watching
Prospective randomized phase IIR/III, two-step, multicenter (RTOG then NRG). Step 2 opened November 2009, closed October 2018, analyzed December 2023. Randomization 1:1, unmasked, stratified by nodal status, CA19-9, margins and adjuvant systemic treatment.
Curative-intent gross total resection of pancreatic head adenocarcinoma with documented microscopic margin status; body/tail excluded. Only pts without recurrence after five cycles of chemotherapy entered step 2: 546 entered step 1, 354 randomized (174 chemo, 180 chemo+CXRT). 74% node-positive, 17% margin-positive, 81% T3.
Step 1 was gemcitabine (67%), gemcitabine plus erlotinib (28%) or non-oxaliplatin gemcitabine combinations (5%); no pt received FOLFIRINOX. Both arms then took a sixth cycle; the experimental arm followed with CXRT within 21 days, sensitized by capecitabine (83%) or infusional 5-FU (15%).
50.4 Gy in 28 fractions to the postoperative tumor bed, pancreatojejunostomy and regional nodes; median delivered dose 50.4 Gy over 28 fractions and 38 days. 81% IMRT, 19% 3D conformal, 79% with no interruptions, 88% received ≥50 Gy. Centers were IROC-credentialed and every plan underwent real-time central review before start.
Primary: overall survival from second-step randomization. Secondary: DFS and adverse events (CTCAE v4.0). Final analysis triggered at the earlier of 316 OS events or 5 years of potential follow-up for all pts; it fired on the latter with 270 events, cutting power to 72%.
Grade 4 or 5 AEs were not increased (6% v 5%, P=.68), with one grade 5 in each arm (hepatic failure, sepsis). Grade 3 rose to 38% v 19% (P<.001), driven by GI events and decreased lymphocyte count; grade 3 nonhematologic 22% v 11% (P=.004).
ESPAC-1 reported adjuvant CXRT as detrimental, but accrued 1994-2000 with split-course lower-dose 2D planning, no postoperative imaging to exclude incomplete resection or early metastases, and no QA. RTOG 9704's post hoc analysis linked RT protocol deviations to worse survival, the specific failure mode 0848 designed its real-time review to prevent.
Accrual took almost 9 years and the OS event rate ran below projection, so the trial read out on a follow-up trigger at 270 of 316 planned events (power 72% for the hypothesized HR 0.76). The node-negative arms hold 42 and 49 pts, and the subgroup rests on an interaction P=.022 across nine tested subgroups.
The negative primary settles that unselected adjuvant CXRT adds nothing after gemcitabine-based chemotherapy, while the safety profile removes the ESPAC-1-era objection that RT here is harmful. What stays open is whether the node-negative signal reflects a real locoregional benefit in pts with lower competing distant risk, and whether it survives a modern FOLFIRINOX backbone.
| Endpoint | Chemo (n=42) | Chemo+CXRT (n=49) |
|---|---|---|
| 5yr OS (95% CI) | 28.6 (14.9-42.2) | 48.1 (33.3-62.9) |
| Median OS, yr (95% CI) | 3.0 (2.2-4.0) | 3.9 (2.5-NR) |
| Median DFS, yr (95% CI) | 1.5 (0.8-2.7) | 2.3 (1.4-NR) |
CONSORT flow
Prespecified stratified phase III, primary OS endpoint negative overall. Node-negative benefit rests on a subgroup interaction (P=.022) in 91 pts, hypothesis-generating not definitive.
- Does the node-negative CXRT benefit hold on a FOLFIRINOX backbone?
- Can SBRT substitute for conventional CXRT in this setting? active mFOLFIRINOX With or Without Stereotactic Body Radiotherapy in Locally Advanced Pancreatic Adenocarcinoma Phase 2n=92 · primary completion 2025-01 · candidate match
- How to select for RT benefit when nodal status follows neoadjuvant therapy? active Carboplatin, Nab-Paclitaxel, Durvalumab Before Surgery and Adjuvant Therapy in Head and Neck Squamous Cell Carcinoma Phase 2n=39 · primary completion 2022-02 · candidate match
📚 Sources · 📄 1 paper
NRG Oncology RTOG 0539 NCT00895622
ForWHO grade 1-3 meningioma, newly diagnosed or recurrent, any resection extent
TL;DR10-yr PFS 85.2% observed low-risk, 72.2% intermediate-risk at 54 Gy, 42.5% high-risk at 60 Gy.
The transferable RT read is the target: 54 Gy/30 fx for intermediate-risk and 60 Gy/30 fx for high-risk, with grade 3+ RT-attributed toxicity 9.6% and 15.1%. Recurrent grade 1 salvaged with RT reached only 67.0% 10-yr OS, worse than upfront grade 2 post-GTR at 91.0%, which argues against deferring RT in a grade 1 you expect to recur.
In newly diagnosed WHO grade 2 meningioma after GTR, this supports upfront 54 Gy while NRG BN003 and ROAM read out; it does not speak to observation in that group, since no untreated grade 2 arm was enrolled. The longer read
The transferable parameters are 54 Gy/30 fx intermediate-risk and 60 Gy/30 fx high-risk, with grade 3+ RT-attributed toxicity of 9.6% and 15.1%. Recurrent grade 1 salvaged with RT reached only 67.0% 10-yr OS vs 91.0% for upfront grade 2 post-GTR, which argues against deferring RT in a grade 1 likely to recur.
Extent of resection carried more weight than histology: STR vs GTR gave PFS HR 2.58 (1.09-6.11) and OS HR 3.38 (1.28-8.91) on multivariable analysis. Even in observed low-risk grade 1 disease, 10-yr PFS was 88.0% after GTR vs 72.7% after STR, so a Simpson-grade decision at the first operation still shows at 10 years.
10 details 4 trials watching
Multi-arm prospective phase 2 trial (NCT00895622) of risk-adapted management, not randomised: each risk group followed its own assigned strategy. 244 consented, 165 eligible and treated per protocol. Original endpoint was 3-yr PFS, previously reported; this is the mature analysis with data cutoff 8/15/2023 and median follow-up 12.1, 12.0 and 11.1 years across the three cohorts.
Adults ≥18 with Zubrod 0-1 and histologically confirmed unifocal WHO grade 1-3 meningioma, newly diagnosed or recurrent, any resection extent, with centrally confirmed pathology. Median age 56, 62 in the high-risk group; 65.5% female overall. Recurrent disease made up 30.8% of the intermediate and 47.2% of the high-risk cohorts.
Group 1 (grade 1 post-GTR/STR) was observed only. Group 2 (recurrent grade 1, or newly diagnosed grade 2 post-GTR) received 54 Gy in 30 fractions. Group 3 (newly diagnosed grade 2 post-STR, newly diagnosed grade 3, or recurrent grade 2/3) received 60 Gy in 30 fractions.
The gradient tracks risk assignment cleanly at 10 years, and the two Cox covariates that survive adjustment are recurrent disease and subtotal resection, both for PFS and OS. See the cohort and covariate tables above.
| Cohort | Management | 10-yr PFS | 10-yr OS | 10-yr cum. incidence progression |
|---|---|---|---|---|
| Low (grp 1, n=60) | Observation | 85.2% (75.7-94.8) | 94.1% (87.6-100) | 8.9% (3.2-18.2) |
| Intermediate (grp 2, n=52) | RT 54 Gy | 72.2% (59.2-85.1) | 84.7% (74.2-95.2) | 21.2% (10.8-33.9) |
| High (grp 3, n=53) | RT 60 Gy | 42.5% (28.7-56.3) | 51.1% (37.0-65.2) | 39.3% (25.8-52.5) |
| Covariate | PFS HR (95% CI), p | OS HR (95% CI), p |
|---|---|---|
| Recurrent vs initial | 2.5 (1.01-6.18), p=0.047 | 2.86 (1.06-7.70), p=0.038 |
| STR vs GTR | 2.58 (1.09-6.11), p=0.031 | 3.38 (1.28-8.91), p=0.014 |
Grade 3+ AEs attributed to radiotherapy occurred in 5 pts (9.6%) of the intermediate-risk and 8 pts (15.1%) of the high-risk cohorts. Newly reported late events in the intermediate group were auditory and neurologic grade 3 plus one grade 4 hemorrhage. Zubrod, MMSE and neurologic function score were stable over time.
This is the mature counterpart to the trial's own 3-yr landmark reports and now sits as the benchmark alongside the ongoing de-escalation questions in NRG BN003 (NCT03180268) and ROAM/EORTC 1308, both of which test whether grade 2 post-GTR needs RT at all. Until those read out, the 10-yr PFS 72.2% and OS 84.7% here are the reference numbers for treating that group.
Pathology was graded under the WHO criteria of the enrolment era, so some group 1 tumors would likely be reclassified today, which is the trial's own proposed explanation for the poor recurrent grade 1 outcomes. Subgroup estimates rest on very small denominators, with intervals such as 15.0% (0-42.0%) for recurrent grade 2 PFS that cannot support a practice decision on their own.
The trial settles the low-risk question (observe after GTR, 10-yr PFS 88.0%) and confirms that high-risk disease is not controlled by 60 Gy, with 10-yr PFS 42.5%. What it cannot settle is whether the intermediate-risk result reflects RT or favorable biology, since no group 2 patient went untreated.
Non-randomised risk-adapted phase 2 with mature 10+ yr follow-up; supports existing consensus (observe post-GTR grade 1, RT otherwise) rather than testing it against a control.
- Does grade 2 meningioma post-GTR need adjuvant RT at all recruiting Observation or Radiation Therapy in Treating Patients With Newly Diagnosed Grade II Meningioma That Has Been Completely Removed by Surgery Phase 3n=163 · primary completion 2027-06 · randomised RT vs observation, GTR grade II
- Whether molecular classification reassigns recurrent grade 1 tumors n=210 · primary completion 2026-03 · methylation + histone PTM signature for recurrence
- How to improve first-line treatment for high-risk meningioma recruiting Vismodegib, FAK Inhibitor GSK2256098, Capivasertib, and Abemaciclib in Treating Patients With Progressive Meningiomas Phase 2n=124 · primary completion 2027-01 · mutation-matched targeted arms, progressive tumorsactive A Trial of Increased Dose Intensity Modulated Proton Therapy (IMPT) for High-Grade Meningiomas Phase NAn=21 · primary completion 2027-08 · dose-escalated IMPT, STR grade II / grade III
📚 Sources · 📄 1 paper
Abstract
FIRESTORM
ForHigh-risk meningioma (WHO gr 2 post-STR, recurrent gr 2, any gr 3), postop RT
HR 0.40
95% CI 0.24-0.69, P = .001 (MVA); IPTW HR 0.45 (0.24-0.83)
TL;DR5-yr PFS 65.8% vs 38.8% with dose-escalated postop RT (BED ≥79.2 Gy) in high-risk meningioma; MVA HR 0.40.
The benefit survives the obvious confounders: excluding the 35 single-fraction SRS cases from SD-RT, DE-RT still gave 5-yr PFS 65.8% vs 41.7% (HR 0.56, 0.36-0.86), and photon-alone escalation matched carbon on PFS (68.3% vs 61.1%) with 0% grade ≥3 radionecrosis. That makes 66-70 Gy conventionally fractionated photons the practical escalation route, not particle referral.
In a subtotally resected WHO grade 2 or any grade 3 meningioma being planned for postoperative RT, this supports considering escalation beyond 60 Gy/30 fx rather than defaulting to it; it does not speak to gross-totally resected grade 1 disease. The longer read
Photon-alone escalation to 70 Gy/35 fx or 66 Gy/33 fx matched carbon on 5-yr PFS (68.3% vs 61.1%) with zero grade ≥3 radionecrosis, versus 9.1% in the carbon subgroup. Boost PTV margins were 0.5 to 2 mm off cavity and residual tumor. That makes escalation a standard photon department decision, not a particle referral.
14 details
Individual patient-level meta-analysis pooling 248 patients from 7 international institutions, all retrospective except one prospective trial. Median follow-up 67.1 months (range 2.13-178). PFS was the primary outcome, analyzed by Kaplan-Meier, Cox MVA, and IPTW propensity weighting.
High-risk meningioma per RTOG 0539: newly diagnosed WHO grade 2 after STR/biopsy, any recurrent grade 2, or any grade 3. 188 (75.8%) were grade 2, 103 (41.5%) recurrent, and 182 (75.2%) had Simpson grade 4/STR. Median age 60; 55 (22.2%) had prior RT.
DE-RT was defined by biologically effective dose ≥79.2 Gy (equivalent to 66 Gy in 33 fractions) or receipt of a carbon-ion boost; anything below that threshold counted as SD-RT. Photon DE-RT used a sequential or simultaneous integrated boost with a 0.5 to 2 mm PTV margin, versus 1-2 cm CTV margins in the SD-RT arm. Carbon DE-RT boosted 16 Gy/8 fx after 50 Gy/25 fx photons with a 6 mm CTV margin.
Whole-cohort 3- and 5-yr PFS were 62.8% and 45.0%. DE-RT improved 3-yr (86.4% vs 55.6%) and 5-yr PFS (65.8% vs 38.8%), P = .0022, holding on stratified Cox by grade (HR 0.40, 0.22-0.73) and after IPTW (3-yr 84.7% vs 55.8%). OS was not improved on MVA or IPTW.
| Subgroup | 3-yr PFS DE-RT vs SD-RT | 5-yr PFS DE-RT vs SD-RT | MVA HR (95% CI) | P |
|---|---|---|---|---|
| Simpson 1-3 | 87.5% vs 55.9% | 70.0% vs 40.0% | 0.31 (0.08-1.14) | .08 |
| Simpson 4-5 | 86.3% vs 55.4% | 63.3% vs 38.4% | 0.55 (0.36-0.84) | .006 |
| Cohort | Any-grade RN | Grade ≥3 RN |
|---|---|---|
| DE-RT overall | 20 of 59 (33.9%) | 3 of 59 (5.1%) |
| DE-RT mixed carbon/photon | 15 of 33 (45%) | 3 of 33 (9.1%) |
| DE-RT photon-alone | 5 of 26 (19.2%) | 0% |
| SD-RT | 25 of 189 (13.2%) | 6 of 189 (3.2%) |
Any-grade radionecrosis was 33.9% with DE-RT vs 13.2% with SD-RT (P = .001), but grade ≥3 RN did not differ (5.1% vs 3.2%, P = .47). All 3 grade ≥3 events in the DE-RT arm occurred in the mixed carbon-photon cohort; the photon-alone DE-RT cohort had none, and its any-grade RN rate was not significantly higher than SD-RT (P = .41). One grade 5 event occurred in each arm.
Published series anchored on RTOG 0539 report 5-yr PFS of roughly 40% to 60% with 60 Gy/30 fx, which is what the SD-RT arm reproduces (45.0% overall). The escalation signal draws on MARCIE (carbon boost) and the Zeng et al. photon series, both contributors to this pool, so the comparison is partly internal rather than independent.
DE-RT was delivered at only 2 of 7 institutions, one carbon-only and one photon-only, so treatment arm is nearly collinear with center, and unmeasured practice differences (DOTATATE PET planning, response assessment, supportive care) travel with it. Molecular classification was unavailable, and P values were not adjusted for multiple testing across the subgroup analyses.
The Simpson 1-3 subgroup showed absolute separation as large as Simpson 4-5 (5-yr PFS 70.0% vs 40.0%) without reaching significance (P = .08 on MVA), which the authors attribute to a smaller GTR subset and fewer events rather than an absent effect. Whether escalation belongs in fully resected disease is the open question, and the PFS-only benefit means the case rests on avoiding local progression and its neurologic morbidity, not on survival.
Retrospective IPD pooling, DE-RT confined to 2 centers, no randomization; IPTW cannot remove selection. Direction consistent across every sensitivity analysis, but prospective randomization still needed.
- Benefit of dose escalation after gross total resection
- Whether molecular subgroups predict DE-RT benefit
- Prospective randomized confirmation of the PFS signal
📚 Sources · 📄 1 paper
Abstract
RAPCHEM (BOOG 2010-03) NCT01872975
ForcT1-2 (<5cm) cN1 breast cancer, post-neoadjuvant chemo and surgery
2.9% (24/838)
Low 2.4%, intermediate 3.2%, high 2.8%
TL;DR10yr locoregional recurrence 2.9% (24/838) with response-adapted RT after neoadjuvant chemo; 2.4% in the RT-omission-eligible low-risk group.
Reported via The ASCO Post →
The allocation rule, not the recurrence rate, is the transferable part: ypN0 after mastectomy received no RT at all and still ran 2.4% at 10yr, and ypN1 pts had regional nodes omitted entirely. Dose, fractionation and target-volume detail are not reported in source, which limits direct transfer.
In cT1-2 cN1 pts who convert to ypN0 after neoadjuvant chemotherapy, this supports the safety of a de-escalated RT volume over 10 years; it does not extend to cN2-3 disease, and the randomised comparison remains open. The longer read
The transferable content is the allocation rule: ypN0 after mastectomy got no RT and ran 2.4% at 10yr, ypN1 had regional nodes omitted at 3.2%. Dose, fractionation and target volumes are not reported in source, so the volume decision transfers but the technique does not.
The de-escalation is entirely downstream of chemotherapy response: nodal clearance after neoadjuvant treatment is what unlocks the smaller RT volume, which raises the stakes on regimen choice and on documenting response. It does not change drug selection or sequencing itself.
8 details 3 trials watching
Prospective multicentre cohort, N=848 across 17 Dutch centres, accrued 2011-2015, presented at EBCC15 with 10-year follow-up; 838 completed follow-up. Not randomised: every patient received the RT volume their risk group assigned.
Breast tumour under 5 cm with 1 to 3 involved lymph nodes at presentation, treated with neoadjuvant chemotherapy then surgery (BCS or mastectomy). Most underwent axillary lymph node dissection.
Volume was set by post-chemotherapy nodal status. ypN0: breast RT after BCS, none after mastectomy. ypN1: breast or chest wall only, regional nodes omitted. ypN2+: breast or chest wall plus regional nodal irradiation. Dose and fractionation are not reported in source.
24 of 838 (2.9%) had a locoregional recurrence without distant spread at 10 years. Per-group counts appear in the detail table; the rates do not separate across strata.
The randomised test of this exact question is NSABP B-51/RTOG 1304 (NCT01872975), which the investigators expect in about 3 years; until then no trial has randomised ypN0 pts to nodal RT versus omission. Prior nodal-RT evidence (MA.20, EORTC 22922) was built in upfront-surgery populations, so it cannot arbitrate a post-chemotherapy response-adapted rule.
The 2.9% rate is uninterpretable without a comparator: a low event count in a de-escalated cohort is equally consistent with the omitted RT having been unnecessary and with the cohort being low-risk to begin with. ALND staging also means the ypN0 label carries more information than a modern sentinel-node ypN0 does.
The finding that recurrence is flat at 2.4% / 3.2% / 2.8% across escalating risk is the intended signal: the added RT in the higher strata may be doing the work that keeps them level with the low-risk group. It does not settle whether the low-risk group needed any RT, only that the allocation rule did not produce a visible failure.
Single-arm prospective cohort with no randomised comparator; allocation used ALND-era nodal staging. Confirmatory randomised answer (NSABP B-51) still pending.
- Does response-adapted RT omission hold under sentinel-node-only staging?
- Late toxicity avoided by omitting regional nodal irradiation n=827 · primary completion 2029-12 · randomised WBI alone vs WB+RNI in pN1 post-BCSnot yet A Study of Postoperative Regional Nodal Radiotherapy in Intermediate-risk Breast Cancer Phase 3n=3142 · primary completion 2032-12 · phase 3 RNI vs no RNI, toxicity evaluated
- Distant recurrence and survival in the de-escalated groups not yet A Study of Postoperative Regional Nodal Radiotherapy in Intermediate-risk Breast Cancer Phase 3n=3142 · primary completion 2032-12 · tumor-free survival non-inferiority without RNI
📚 Sources · 📄 1 paper
Abstract
MROQC ADT Practice Patterns
ForIntact high-risk M0, N0-1 prostate cancer, definitive RT
TL;DRGuideline-concordant ≥18mo ADT intended in 67.0% of high-risk M0/N0-1 pts receiving definitive RT; ARPI recommended in 23.2% of STAMPEDE-eligible pts post-publication.
Facility-level variability in ≥18mo ADT recommendations persisted after adjusting for cN1, grade group and PSA (P<.0001), so treating site, not only tumor features, shapes duration. Among STAMPEDE M0-eligible pts, ARPI recommendations reached only 23.2% after publication, a gap a department can audit directly in its own high-risk RT cohort. The longer read
Grade group drove concordant ADT recommendations most (GG5 OR 9.45, GG4 OR 6.23), and site-level variability survived adjustment (P<.0001). For an RT department the benchmark is concrete: 67.0% intended ≥18mo ADT and 23.2% ARPI uptake in STAMPEDE M0-eligible pts after publication.
9 details
Prospective statewide quality-consortium data (MROQC), N=553 across 26 centers, June 2020 to November 2024. Multivariable analysis of predictors, a mixed-effects model with treatment site as random intercept, and ARPI adoption compared before vs after STAMPEDE M0 publication.
Intact high-risk M0, N0-1 prostate cancer treated with definitive RT: cT3/4 13.3%, cN1 19.9%, GG 4-5 75.0%, PSA ≥20 ng/mL 40.0%. 27.9% met STAMPEDE M0 criteria (≥2 of cT3/T4, GG 4-5, PSA ≥40 ng/mL, or cN1).
Primary: intended guideline-concordant ADT (GC-ADT, ≥18 months) per 2022 AUA/ASTRO. Also assessed: ARPI recommendation in STAMPEDE-eligible pts and facility-level variability.
91.3% recommended any ADT, 67.0% guideline-concordant. ARPI recommendations in STAMPEDE-eligible pts rose from 0% to 23.2% after publication; facility variability persisted on MVA (P<.0001).
| Factor | OR (95% CI) |
|---|---|
| cN1 | 2.94 (1.44-5.99) |
| GG4 | 6.23 (2.85-13.62) |
| GG5 | 9.45 (4.46-20.06) |
| PSA ≥40 ng/mL | 3.64 (1.22-10.87) |
Benchmarks practice against the 2022 AUA/ASTRO 18-36 month recommendation and STAMPEDE M0 ARPI intensification criteria. Single-state data, and the source offers no comparison with other practice settings.
The abstract gives no reasons for sub-18mo recommendations (comorbidity, pt preference, toxicity), so non-concordance is not necessarily poor care. The ARPI comparison is an uncontrolled before-after design, and no OR is reported for cT3/4.
The strongest predictors of a concordant recommendation were grade group (GG5 OR 9.45) and cN1, consistent with shorter courses being offered when high-risk status rests on other features. Residual site variability points to local norms beyond the modelled case mix, though unmeasured covariates could contribute.
Practice-patterns study of intended ADT recommendations; no efficacy or outcome endpoint, so nothing here confirms or challenges SOC.
- Delivered vs intended ADT duration in routine definitive RT practice
- Drivers of facility-level variation in ADT duration recommendations
- Barriers to ARPI intensification in STAMPEDE M0-eligible pts
📚 Sources · 📄 1 paper
Abstract
AREST
ForResected pT1-2N0 OSCC, margins ≥5mm, ≥1 intermediate-risk feature
HR 0.52
95% CI 0.30-0.91, p=0.02 · 3-yr 89.2% vs 80.9% (ITT)
TL;DR3-yr LRFS 89.2% vs 80.9% (HR 0.52, p=0.02) with adjuvant RT vs observation in resected intermediate-risk pT1-2N0 OSCC; no significant DFS/OS difference.
Competing-risk LRF incidence was 10.6% vs 18.9% (HR 0.52) with 60Gy/30fx to tumor bed and at-risk neck. Controls had ≥5mm margins and a level I-III dissection with ≥16 nodes, so this is RT's increment over high-quality surgery alone. It moves adjuvant RT vs observation most for oral tongue, an exploratory subgroup.
In pT1-2N0 OSCC resected with ≥5mm margins and an adequate level I-III neck dissection but carrying PNI, LVE, poor differentiation or DOI ≥5 to ≤10mm, this supports discussing adjuvant RT for loco-regional control; it does not extend to close-margin, limited-neck or node-positive disease. The longer read
Competing-risk LRF incidence 10.6% vs 18.9% (HR 0.52) with 60Gy/30fx to tumor bed and at-risk neck, after surgery that already met ≥5mm margins and ≥16 nodes. It moves adjuvant RT vs observation in pT1-2N0 OSCC, strongest for oral tongue in an exploratory subgroup; smaller target volumes untested.
Benefit was measured against surgery with clear margins ≥5mm and an ipsilateral level I-III dissection yielding ≥16 nodes, so RT added loco-regional control even after high-quality resection. Pathology reporting of PNI, LVE, differentiation and DOI now gates the adjuvant referral; the data do not cover close margins or a limited neck.
9 details
Multicenter, open-label, phase III RCT from India, 1:1, stratified by oral cavity subsite, PNI/LVE and differentiation. N=392 (191 RT, 201 observation); median follow-up 47.2 mo (IQR 30-59.4). Powered at 80% to detect HR 0.6256, assuming 3-yr LRFS 70% with observation.
pT1-T2, pN0 OSCC after adequate surgery: clear margins ≥5mm and at least ipsilateral level I-III neck dissection with ≥16 nodes. Required ≥1 intermediate risk factor: DOI ≥5 to ≤10mm, PNI, LVE, or poor differentiation.
60Gy in 30 fractions over 6 weeks to the resected tumor bed and at-risk neck nodal region. Technique and nodal volume definitions not stated in source; no concurrent systemic therapy described.
Primary: loco-regional recurrence-free survival, from randomization to first local and/or regional recurrence. Also reported: cumulative incidence of loco-regional failure with death as competing event, DFS, OS.
LRFS benefit held on PP and competing-risk analyses; DFS and OS not significantly different, with no survival HRs in source.
| Endpoint | Adjuvant RT | Observation | HR (95% CI), p |
|---|---|---|---|
| 3-yr LRFS, ITT | 89.2% (84.3-93.3) | 80.9% (74.6-86.1) | 0.52 (0.30-0.91), p=0.02 |
| 3-yr LRFS, PP | 91.1% | 80.9% | 0.43 (0.23-0.80), p=0.01 |
| LRF cumulative incidence (death competing), ITT | 10.6% (6.1-15.1) | 18.9% (13.3-24.6) | 0.52 (0.30-0.91), p=0.021 |
| LRF cumulative incidence (death competing), PP | 8.7% (4.3-13.1) | 18.9% (13.3-24.6) | 0.43 (0.23-0.79), p=0.007 |
The abstract describes the evidence for adjuvant RT in this setting as largely retrospective; AREST is the randomised test of that practice. The RTOG and EORTC postoperative trials tested adding concurrent chemo to RT in high-risk resected disease and did not randomise RT itself against observation.
Control arm beat its design assumption (3-yr LRFS 80.9% vs 70% assumed), so the absolute gain sits against a lower-risk baseline than planned. Oral tongue vs buccal mucosa is an exploratory subgroup with no HR in source, and no result is given per risk factor. Salvage treatment at recurrence is not described, which bears on the OS read.
Loco-regional control improved without DFS or OS separation; one explanation is effective salvage of isolated recurrences in observed pts, which the abstract cannot confirm. The decision it moves is adjuvant RT vs observation after adequate resection, weighed against RT morbidity the abstract does not report.
CONSORT flow
Randomised phase III hit LRFS primary at 47.2 mo median f/u; DFS/OS not significantly different and no toxicity data in abstract, so supports rather than mandates adjuvant RT.
- Which intermediate-risk feature (PNI, LVE, DOI, grade) drives the benefit?
- Does the oral tongue benefit hold as a prespecified subgroup?
- Late RT toxicity and salvage outcomes in the observation arm
📚 Sources · 🐦 1 tweet · 📄 1 paper
#ASCO26
— Dr Rishabh Jain (@DrRishabhOnco) May 27, 2026
🗣️ The AREST trial tackles one of the biggest gray zones in oral cavity cancer.
After adequate surgery in pT1-2N0 OSCC with intermediate-risk features:
✅ Adjuvant RT improved loco-regional control
❌ No OS benefit observed
3-year LRFS:
🔹 89.2% vs 80.9%
🔹 HR 0.52… https://t.co/qsALPFX032 pic.twitter.com/F4XzTMETih
Abstract
mRCAT-III NCT06507371
ForpMMR/MSS cT3-4N0/+M0 rectal adenoCa, ≤10cm from anal verge, no lateral node
61.0% vs 28.6%
P<0.0001, blinded independent central review
TL;DRpCR 61.0% vs 28.6% (P<0.0001) when elective nodal RT was omitted and tislelizumab added in pMMR/MSS LARC.
The RT variable here is target volume, not dose: both arms got 5Gy x 5d, and the experimental target was tumor bed alone with tumor-draining nodes deliberately spared. That inverts the usual de-escalation logic (smaller field proposed to IMPROVE efficacy by preserving nodal immunity), but tislelizumab moves with it, so the pCR gain cannot be assigned to the field change.
In pMMR/MSS cT3-4 rectal cancer ≤10cm from the verge with no positive lateral node, this raises the question of elective nodal omission with PD-1 blockade but does not yet support dropping nodal coverage outside a trial, and says nothing about dMMR/MSI-H disease. The longer read
The only RT variable is target volume: 5Gy x 5d in both arms, tumor bed alone versus conventional fields including the tumor-draining nodes. Elective nodal omission is being proposed to improve efficacy rather than reduce toxicity, but with no recurrence data reported, the coverage decision stays unchanged outside a trial.
Tislelizumab was added to an unchanged CAPOX backbone in a pMMR/MSS population, where checkpoint blockade has generally underperformed. The 61.0% vs 28.6% pCR is the sequencing signal, though the concurrent field reduction means the drug's independent contribution is not isolated.
All patients proceeded to TME, so the higher pCR (61.0% vs 28.6%) and MPR (77.9% vs 50.6%) bear on the depth of response at resection and, via the unreported organ-preservation secondary, on which patients might avoid it. Nodal yield and recurrence after unirradiated draining nodes are not reported.

| Endpoint (ITT) | Experimental (N=77) | Control (N=77) | P |
|---|---|---|---|
| pCR rate | 61.0 (47/77) | 28.6 (22/77) | <0.001 |
| MPR rate | 77.9 (60/77) | 50.6 (39/77) | <0.001 |
+1 more figure

10 details 5 trials watching
Multicenter, open-label, randomized phase 3 across 17 hospitals in China (NCT06507371). 1:1 allocation, n=77 per arm, stratified by clinical N stage (cN0 vs cN+). Pathologic response read by blinded independent central review.
Rectal adenocarcinoma with lower edge ≤10 cm from the anal verge, cT3-4 N0/+ M0, MSS/pMMR, age 18-75, ECOG PS 0-1. No positive lateral lymph node permitted, which excludes the population where lateral nodal management is itself contested.
Both arms received 5Gy x 5 days. The experimental arm's modification was target volume only: radiation to the tumor bed without tumor-draining lymph nodes, against conventional short-course fields in the control. Dose and fractionation were held constant, so the field is the only RT variable.
Experimental: tislelizumab 200 mg IV d1 plus oxaliplatin 130 mg/m² IV d1 and capecitabine 1000 mg/m² PO d1-14. Control: the same CAPOX backbone without tislelizumab. Both followed by TME, then adjuvant therapy and follow-up.
Primary: pCR rate in the ITT population. Secondary: MPR rate, TRG, organ preservation rate, EFS, OS and AEs. Only pCR and MPR are reported in the source; the time-to-event secondaries are not.
The presentation states the experimental approach reduced the incidence of severe gastrointestinal adverse events, consistent with a smaller irradiated volume, but no grade-specific rates are reported in source.
The control arm's 28.6% pCR sits above what short-course RT with consolidation chemotherapy has historically produced in pMMR disease, so the comparator is not obviously weak. The experimental result approaches the response depth usually reserved for dMMR/MSI-H disease, where checkpoint blockade already produces high complete-response rates; extending that to MSS is the claim being made.
Nodal recurrence is the outcome that decides whether sparing the tumor-draining nodes is safe, and no recurrence, EFS or OS data appear in the source. A pCR advantage at TME cannot answer it, and the cN+ stratum is where a nodal-omission failure would show first.
The trial's mechanistic premise, that irradiating draining nodes depletes the lymphocyte reservoir a PD-1 agent needs, is testable but not tested here: the field change and the checkpoint inhibitor were introduced together. A three-arm design (node-sparing RT + CAPOX, conventional RT + CAPOX + tislelizumab) would be needed to separate them.
CONSORT flow
Randomised phase 3, 1° EP met by central review, but confounds nodal-target omission with PD-1 addition and reports no recurrence or survival data.
- Nodal recurrence risk after sparing tumor-draining lymph nodes recruiting Nodal-Region Sparing Short-Course RT With Chemo-PD-1/Bevacizumab vs. Short-Course RT With Chemotherapy as TNT in pMMR/MSS Locally Advanced Rectal Cancer Phase 2n=76 · primary completion 2029-06 · nodal-sparing vs standard SCRT TNT in pMMR/MSSrecruiting Node-Sparing Short-Course Radiotherapy Sequential Chemotherapy and PD-1 Inhibitor for Mid/Low pMMR/MSS Rectal Cancer (MODIFI-RC-II) Phase 2/3n=430 · primary completion 2030-12 · randomised node-sparing vs conventional field, n=430
- Whether tislelizumab or field reduction drives the pCR gain recruiting Neoadjuvant Long-course Chemoradiation Plus PD-1 Blockade for Mid-low Locally Advanced Rectal Cancer Phase 2n=186 · primary completion 2024-03 · CRT ± tislelizumab, fixed field: isolates the PD-1 armnot yet Neoadjuvant Chemoradiotherapy Followed by Chemotherapy With or Without Tislelizumab for Resectable Ultra-low Rectal Cancer: The RELIEVE-02 Study Phase 3n=154 · primary completion 2027-12 · phase 3 CRT+chemo ± tislelizumab, ultra-low pMMR/MSS
- Organ preservation and EFS with node-sparing short-course RT recruiting Nodes-sparing Short-course Radiation Combined With CAPOX and Tislelizumab for MSS Middle and Low Rectal Cancer Phase 2n=32 · primary completion 2024-08 · node-sparing SCRT + CAPOX/tisle, organ preservation 2° EP
📚 Sources · 🐦 1 tweet
One of most interesting rectal ca studies at #ASCO26
— Dr. Nina Niu Sanford (@NiuSanford) June 2, 2026
P3 RCT in pMMR LARC: Node-sparing short-course RT + CAPOX + tislelizumab doubled pCR v conventional SCRT + CAPOX (61 v 29%)
Hypothesis = sparing elective node RT preserves antitumor immunity & improves PD1 response @OncoAlert pic.twitter.com/6xvA6ne0mg
RT + Systemic Therapy: What to Continue vs Hold (Speers)
TL;DRASCO 2026 education session slides triaging concurrent systemic agents with breast/CW + RNI into continue, caution, and hold/sequence.
HERANCCTG N9831APHINITYKATHERINEATEMPTDESTINY-Breast05COMBARTKEYNOTE-522
The operational content is the PK column: talazoparib 5t½ 19 days and pembrolizumab 5t½ ~110 days mean a brief hold buys nothing, so the mitigation is field size, lung dose and monitoring rather than a washout. Field size, not agent class, gates the CDK4/6i and olaparib calls.
In a pt starting breast/CW + RNI while on T-DXd, this supports concurrent treatment with lung-dose scrutiny rather than a hold; it does not extend to baseline ILD or active pulmonary disease, where sequencing is advised. The longer read
Plan geometry, not the drug name, does the deciding: large lung volumes, IMN coverage, bolus and reconstruction move T-DM1 into caution, high lung-dose plans move T-DXd, and field size gates CDK4/6i and olaparib. Where 5t½ is long (pembrolizumab ~110 days, T-DXd 30 days) a hold is unavailable, so the lever is dose constraints and surveillance.
The washout column tells you what a hold actually costs: capecitabine 4 hrs and veliparib 1 day are free to interrupt, talazoparib 19 days and T-DXd 30 days are not. Olaparib is asked to start 2-12 wks after RT completes on the OlympiA paradigm, which is a sequencing constraint on adjuvant planning, not a toxicity call.

+3 more figures


14 details 4 trials watching
ASCO 2026 education session slide set from Corey W. Speers, adapted from Wong, Speers, Schaverien, ASCO Educational Book 2026, Table 5. It is an allocation framework, not a trial: agents are sorted into continue, caution, and hold/sequence for concurrent use with breast/chest wall + RNI.
The RT context throughout is breast/CW + regional nodal irradiation. The modifiers that move an agent between buckets are plan-level, not drug-level: large lung volumes, IMN coverage, bolus, reconstruction, CNS SRS for T-DM1, high lung-dose plans and thoracic/lung RT for T-DXd, and field size for CDK4/6 inhibitors and olaparib.
Each agent is anchored to its half-life and five-half-life washout: olaparib 15 hr / 3 days, veliparib 5.5 hr / 1 day, talazoparib 90 hr / 19 days, capecitabine ~45 min / 4 hrs, palbociclib 28.8 hr / 6 days, abemaciclib-ribociclib 24-55 hr / 5-11 days, T-DM1 4 days / 20 days, T-DXd 6 days / 30 days, pembrolizumab 22 days / ~110 days. The stated default outside protocol is PK-based washout → RT → resume.
T-DXd's dominant toxicity is ILD: ~12% at 5.4 mg/kg with ~0.9% fatal, and 9.6% vs 1.6% for T-DM1 in DESTINY-Breast05; RT timing within the T-DXd arm showed 10.7% sequential vs 9.6% concurrent. Veliparib carries dose-limiting moist desquamation and fibrosis with concurrent RT (TBCRC 024). T-DM1 signals are dermatitis (possibly underreported), a small pneumonitis signal, and CNS radionecrosis with SRS.
The HER2 mAb call rests on trial precedent rather than new data: HERA started trastuzumab after chemotherapy and XRT, NCCTG N9831 gave XRT concurrently with trastuzumab, and APHINITY gave trastuzumab plus pertuzumab concurrently with RT. The immunotherapy call rests on KEYNOTE-522, whose V1 protocol required restarting pembrolizumab ≥2 wks post-RT and whose V2 amendment permitted concurrency; the post-hoc of 1,174 pts (715 irradiated) found numerically fewer G3-5 and immune AEs in the concurrent group.
The evidence tiers behind the buckets are uneven and the slide says so: the KEYNOTE-522 concurrency read is post-hoc with no adjustment for why pts were irradiated concurrently versus sequentially, and the CDK4/6i call rests on limited prospective data, most evidence retrospective, with a single trial cited (NCT05996107). P-RAD's endpoint is a biomarker (T-cell infiltration, tertiary lymphoid structures), not a clinical outcome.
The organizing logic is that PK sets whether a hold is even available, and plan geometry sets whether it is needed. Where 5t½ is short (capecitabine 4 hrs, veliparib 1 day, olaparib 3 days) the framework holds because it costs almost nothing; where 5t½ is long (talazoparib 19 days, T-DXd 30 days, pembrolizumab ~110 days) it concedes that a hold is theatre and shifts to lung dose, field size and surveillance. The unresolved item it flags rather than settles is T-DM1 vs T-DXd, where the mAbs are described as settled and the ADCs are not.
| Agent | Call | Basis given |
|---|---|---|
| Endocrine therapy | Continue | Minimal radiosensitization |
| Trastuzumab ± pertuzumab | Continue | Generally safe; modern heart-sparing |
| T-DM1 | Continue | Dermatitis + pneumonitis vigilance; caution with CNS SRS |
| Pembrolizumab | Continue | Pneumonitis vigilance + immune-toxicity workflows |
| T-DXd | Caution | Sequence/hold for high lung-dose or active pulmonary disease |
| CDK4/6 inhibitors | Caution | Usually hold for large fields; concurrent only in protocol |
| Olaparib | Caution | Reasonable with limited fields; protocol settings only |
| Cytotoxic chemo (anthracycline/taxane/platinum) | Hold / sequence | Sequence, do not give concurrently |
| Capecitabine | Hold / sequence | Adjuvant paradigm non-concurrent |
| Veliparib / talazoparib | Hold / sequence | Veliparib + RT severe acute/late tox |
| mTOR / PI3K agents | Hold / sequence | Mucosal, skin, metabolic, inflammatory risk; ESMO-ESTRO advises caution |
- T-DM1 vs T-DXd concurrency with locoregional RT
- Prospective CDK4/6i concurrent RT safety data recruiting Safety Assessment of Concurrent Radiotherapy and Novel Systemic Therapy for Breast Cancer Phase NAn=148 · primary completion 2026-01 · CDK4/6i during breast/CW ± nodal RT, n=148 safetyn=15 · primary completion 2026-09 · phase 1b abemaciclib + letrozole concurrent preop RT
- Whether short-course preop RT priming translates to outcomes n=120 · primary completion 2025-12 · randomised no/low/high dose preop RT boost + pembrorecruiting Preoperative Immunotherapy Combined With Stereotactic Radiation Therapy Boost in the Treatment of HER2-negative Breast Cancer Phase 2n=78 · primary completion 2028-02 · preop RT boost + randomised pembro vs placebo, HER2-neg
📚 Sources · 🐦 1 tweet
#ASCO26
— Yakup Ergün (@dr_yakupergun) June 1, 2026
Which treatments should continue with RT, and which should be held?
From the Great presentation by Dr. Corey W. Speers pic.twitter.com/9B7e0HePDZ
ctDNA and Local Regrowth/Distant Mets in Nonoperative Rectal Cancer
ForMSS stage I-III rectal ca, cCR/nCR after NAT, on nonoperative management
TL;DRctDNA sensitivity for local regrowth only 41% (12/29), specificity 94%; distant mets sensitivity 74%, specificity 97%.
The number that gates watch-and-wait practice is 41% sensitivity for local regrowth (12/29 samples): a negative ctDNA cannot license lengthening MRI or endoscopy intervals in an organ-preservation protocol. Specificity 94% means a positive result is worth acting on, and ctDNA+ at regrowth tracked ypT3-4 in 6/8 vs 3/14 (p=0.01).
In a stage I-III MSS rectal pt in watch-and-wait after TNT or CRT, a positive ctDNA supports intensified assessment for regrowth or distant disease; a negative result does not support relaxing endoscopic or MRI surveillance intervals. The longer read
Watch-and-wait after TNT or chemoRT is an RT-owned pathway, and this says the surveillance burden that sustains it cannot be shifted to blood. Sensitivity for local regrowth was 41% (12/29); a negative ctDNA does not support lengthening MRI or proctoscopy intervals in a pt whose rectum you preserved.
The distant-metastasis read is where ctDNA earns its place: sensitivity 74%, specificity 97% (31/42 and 611/627), versus 41% locally. That supports using serial ctDNA to trigger systemic restaging and escalation decisions, not to arbitrate local status.
ctDNA positivity at the time of regrowth tracked more advanced salvage pathology: ypT3-4 in 6/8 (75%) vs 3/14 (21%), p=0.01. A regrowth found in a ctDNA-positive pt is more likely to be a deeper-invading tumor, which informs how the salvage TME is planned rather than whether it is offered.

| Outcome | Sensitivity | Specificity | Accuracy |
|---|---|---|---|
| For local regrowth | 12 / 29 (41%) | 480 / 509 (94%) | 492 / 538 (91%) |
| For distant metastasis | 31 / 42 (74%) | 611 / 627 (97%) | 642 / 669 (96%) |
11 details
Single-institution cohort from MD Anderson's INTERCEPT program, 2020-2024, N=110, with serial tumor-informed ctDNA during nonoperative management. Median follow-up 25 months (IQR 18-37).
Microsatellite stable stage I-III rectal adenocarcinoma achieving cCR or near-cCR after neoadjuvant therapy and managed nonoperatively. Median age 56; baseline cT3 in 72 and cT4 in 16; 69 received TNT, 41 CRT or chemotherapy alone.
Local regrowth and distant metastasis by longitudinal ctDNA status, by first post-NAT ctDNA (within 180 days), and per-sample accuracy for an event within ±90 days of each draw. Salvage-surgery pathology by ctDNA status at regrowth.
Twenty-three pts (21%) had local regrowth and 12 (11%) distant metastasis. Ever-positive ctDNA separated both curves (log rank p=0.0002 for regrowth, p<.0001 for metastasis). The per-sample table carries the operating characteristics.
Per-sample analysis pools 669 draws from 110 pts without accounting for repeated measures, so the confidence around 41% is softer than the denominator suggests. The first-post-NAT comparison rests on n=12 evaluable pts as reported in the source. No comparison against MRI or endoscopy, the tests ctDNA would have to beat.
The asymmetry between local (41%) and distant (74%) sensitivity is the informative result: intraluminal regrowth from a small residual burden sheds too little DNA to be caught reliably, while metastatic disease does. That biology argues for ctDNA as a distant-recurrence tool layered onto, not substituted for, luminal surveillance.
Retrospective single-center cohort; per-sample analysis treats 669 draws from 110 pts as independent. No head-to-head against MRI/endoscopy surveillance.
- Does ctDNA add anything over MRI plus endoscopy in NOM surveillance?
- Can draw timing or a lower assay threshold raise local regrowth sensitivity?
- Does ctDNA-triggered restaging improve salvage outcomes?
📚 Sources · 🐦 1 tweet
Important study re: ctDNA for non-op surveillance in rectal ca.
— Dr. Nina Niu Sanford (@NiuSanford) June 1, 2026
Pos ctDNA associated w regrowth (60%) & distant mets (60%), but neg ctDNA doesn't exclude local regrowth (sensitivity only 41%)
ctDNA good for risk stratification but not surveillance replacement #ASCO26 @OncoAlert pic.twitter.com/UQQub5QfNB
COMPPARE
ForDe novo non-metastatic prostate cancer, excluding very high risk
TL;DRBowel urgency 5.7% vs 6% (p=0.28), proton vs IMRT; no significant difference in G2+ GI toxicity or 3-yr biochemical control, localized prostate.
The RT variable that tracked with GI toxicity was the rectal spacer, not the particle: 2-yr cumulative G2+ GI was 4.4% IMRT and 4.7% proton with spacer vs 7.2% and 8.7% without (Gray's test p=0.009). Observed IMRT rates sat well below the hypothesized control rates, leaving little absolute room for a proton advantage.
In de novo non-metastatic prostate cancer short of very high risk, this questions choosing protons over IMRT to reduce bowel urgency, bowel frequency, or G2+ GI toxicity; it does not address late toxicity or long-term disease control.
Rectal spacer, not modality, tracked with 2-yr G2+ GI toxicity: 4.4% IMRT and 4.7% proton with spacer vs 7.2% and 8.7% without (Gray's test p=0.009). With observed IMRT GI rates far below hypothesized, the rectal-sparing decision carries more weight than the proton referral.

+1 more figure

| Group | 2-yr cumulative CTCAE GI G2+ |
|---|---|
| IMRT, no spacer | 7.2% (5.0%, 9.9%) |
| Proton, no spacer | 8.7% (5.0%, 14%) |
| IMRT, spacer | 4.4% (2.8%, 6.4%) |
| Proton, spacer | 4.7% (3.6%, 6.0%) |
| Gray's test p-value | 0.009 |
10 details 1 trial watching
Prospective comparison of proton and photon cohorts, PCORI-funded, 51 PT and IMRT centers. 2524 accrued July 2018 to October 2022; schema lists a proton cohort of 1500 and a photon cohort of 1000. Source does not describe randomisation.
All de novo prostate cancer except very high risk and metastatic. Baseline characteristics and risk-group mix by cohort not reported in source.
Proton therapy vs photon IMRT, with rectal spacer use analysed as a stratum. Dose, fractionation, target volume and ADT use not reported in source.
Powered hypotheses (90% power): EPIC bowel urgency, EPIC bowel frequency, CTCAE v5 ≥G2 GI toxicity. Exploratory: freedom from PSA progression at 3 years.
No significant difference on any powered GI endpoint or on 3-yr biochemical control (see table).
| Endpoint | PT | IMRT | Hypothesized PT vs IMRT | p |
|---|---|---|---|---|
| Bowel urgency (EPIC) | 5.7% | 6% | 7% vs 15% | 0.28 |
| Bowel frequency (EPIC) | 3.5% | 4% | 4% vs 10% | 0.43 |
| GI toxicity (CTCAE ≥G2) | 5.2% | 5.6% | 20% vs 29% | 0.60 |
| 3-yr freedom from progression (PSA) | 98.0% | 97.9% | 91% vs 89% (exploratory) | 0.90 |
GI G2+ toxicity point estimates were lower with a rectal spacer in both cohorts (Gray's test p=0.009). GU toxicity not reported in source.
PARTIQoL randomised the same proton vs IMRT question in localized prostate cancer and also found no bowel-function advantage for protons. COMPPARE adds a larger multicentre cohort read in the same direction.
Control event rates came in far below the powering assumptions, so the hypothesized absolute differences were never plausible at observed rates. Spacer use by cohort is not reported, so the modality comparison may be confounded by rectal sparing strategy.
The null holds across patient-reported and physician-graded GI endpoints, and the spacer stratum suggests GI toxicity tracks rectal sparing more than particle type. It does not settle late toxicity or long-term outcomes.
Source calls these early results; late toxicity and long-term control immature. No randomisation described, so the null GI comparison carries cohort selection bias.
- Proton vs IMRT late GI toxicity beyond early follow-up n=102 · primary completion 2028-12 · late GI tox, protons vs photons, high-risk pelvic RT
- Long-term disease control with protons vs IMRT
- Does a rectal spacer erase any residual proton GI advantage?
📚 Sources · 🐦 1 tweet
#COMPPARE early results: in localized #ProstateCancer, #proton therapy vs #IMRT showed no sig difference in pt-reported bowel urgency/frequency, ≥G2 GI toxicity, or 3-year biochemical control. Longer follow-up needed for late toxicity/long term outcomes #ASCO2026 pic.twitter.com/yli4l8nEOY
— QianJanieQin (@QianJanieQin) May 31, 2026
CAN-2409 NCT01436968
ForIntermediate or high-risk localised prostate cancer, EBRT candidates, ECOG 0-2
HR 0.70
95% CI 0.52-0.94, p=0.016; median NR vs 86.1 mo
TL;DRDFS HR 0.70 (0.52-0.94), 2y biopsy persistence/recurrence 19.6% vs 36.4%, adding intraprostatic aglatimagene to EBRT in intermediate/high-risk localised prostate cancer.
The effect is local: 2y post-treatment biopsy persistence/recurrence 19.6% vs 36.4% (p=0.0015), while OS and PCSM were not different (1 PCSM event per arm). That places it beside ADT, SIB and brachy boost as a local-intensification option; the discussant's RTOG 9408 benchmark, 4mo ADT added to 66.6 Gy, showed 2y positive biopsy 40% vs 20%.
In intermediate or high-risk localised prostate cancer planned for 78 Gy in 2 Gy, 60 Gy in 3 Gy or 70 Gy in 2.5 Gy fractions, this supports intraprostatic aglatimagene as a DFS-improving addition; it does not extend to pts whose EBRT includes a brachytherapy or SIB boost. The longer read
Local control is the RT read: 2y biopsy persistence/recurrence 19.6% vs 36.4% (p=0.0015) on 78 Gy or hypofractionated EBRT, with OS and PCSM not different. It sits beside ADT, SIB and brachy boost as local intensification, none of which was tested with it here.

| Trial | Arms | Local endpoint | Control vs intensified |
|---|---|---|---|
| RTOG 9408 | RT 66.6Gy vs + 4m ADT | 2yr post-Rx biopsy positive | 40% vs 20% |
| ASCENDE-RT | 46Gy + DE-EBRT 23Gy vs 46Gy + LDR-BT | 10y local failure | 7.1% vs 1.5% |
| FLAME | RT 77Gy vs + SIB 95Gy | Crude local failure | 7.7% vs 2.7% |
| CAN-2409 | RT 78Gy + placebo vs + CAN-2409 | 2yr post-Rx biopsy positive | 36.4% vs 19.6% |
8 details
Phase 3, randomised 2:1, double-blind, placebo-controlled at 51 US and Puerto Rico centres (26 community, 25 institutional or military). Accrual Feb 2012 to Sept 2021; median follow-up 50.3 mo (IQR 35.2-63.3).
Intermediate or high-risk localised prostate cancer planned for EBRT, age ≥18, ECOG 0-2. N=745 (496 vs 249); 591 (79%) White, 121 (16%) Black.
Three courses of intraprostatic aglatimagene (5 × 10^11 viral particles) plus valacyclovir vs placebo plus valacyclovir. Stratified by risk category and ADT use; ADT optional.
78 Gy in 2 Gy fractions, or hypofractionated 60 Gy in 3 Gy or 70 Gy in 2.5 Gy fractions. No boost regimen described in source.
Primary: DFS, time from randomisation to prostate cancer recurrence or death, ITT. Safety in all pts receiving ≥1 injection.
Per the discussant, the DFS gain was driven mainly by 2y post-treatment biopsy pCR; OS and PCSM not significantly different.
| Endpoint | Aglatimagene + valacyclovir | Placebo + valacyclovir | Effect |
|---|---|---|---|
| Median DFS | NR (95% CI 121.78-NR) | 86.1 mo | HR 0.70 (0.52-0.94), p=0.016 |
| 2y post-Rx biopsy pCR | 80.4% | 63.6% | not stated |
| 2y biopsy persistence/recurrence | 19.6% | 36.4% | p=0.0015 |
G3+ TEAEs 8% vs 7%; most common G3+ event AKI (2% each). SAEs 6% vs 7%, treatment-related SAEs 2% each. No treatment-related deaths.
The discussant set it against established local-intensification strategies: ADT in RTOG 9408, LDR brachy boost in ASCENDE-RT and focal SIB in FLAME. None was tested head-to-head or in combination with aglatimagene.
Long accrual (Feb 2012 to Sept 2021). Safety population (479 and 232) smaller than randomised arms (496 and 249). MFS and biochemical recurrence not presented; funded by Candel Therapeutics and NIH.
A positive blinded phase 3 of an oncolytic-viral agent with RT and no toxicity penalty, but the benefit currently rests on biopsy-defined local persistence. Whether that converts to MFS or PCSM, and whether it holds against boost-level dose intensification, is unsettled.
CONSORT flow
Blinded phase 3 met DFS at 50.3mo, but gain driven by 2y biopsy persistence; OS/PCSM not different, and no boost-level dose intensification in control.
- Does the biopsy-driven DFS gain translate into MFS or PCSM benefit?
- Added value over brachytherapy boost or focal SIB dose intensification
- Interaction with ADT use and duration
📚 Sources · 🐦 1 tweet · 📄 1 paper
🗣️Prostate Oral Abstract #ASCO25
— Michael Serzan, MD (@MikeSerzanMD) June 3, 2025
👉Dr @angela_jia_ discusses "Better Treatments, Better Selection: Improving Patient Outcomes in Localized Prostate Cancer"
🔑 KEY TAKE AWAYS
- #CAN2409 improves DFS and 2yr PathCR however PCSM and OS remain immature.
❓How to integrate with… pic.twitter.com/WamsneYBI1
Abstract
RAD-IO
ForMIBC cT2-T3 (13% N+), bladder-preservation intent, 75% prior neoadjuvant chemo
TL;DR12-mo DFS 40/50 (80%, 95% CI 0.67-0.89) with durvalumab added to 5FU/MMC chemoRT, clearing the pre-set GO bar (≥75%).
The RT is unchanged from standard UK practice (55Gy/20fr bladder, 46Gy/20fr nodes when N+), so nothing here alters target volume or dose. What is new is that durvalumab was delivered neoadjuvant, synchronous AND adjuvant around that backbone, and only 61% completed it, which is the number gating any future randomised trial design.
In cT2-T3 MIBC pts choosing bladder preservation with 5FU/MMC chemoRT, this supports enrolling on a checkpoint-inhibitor chemoRT trial rather than adding durvalumab off protocol; it does not extend to cisplatin-ineligible pts having RT alone or to those with extensive nodal disease. The longer read
The RT is unchanged: 55Gy/20fr bladder, 46Gy/20fr to nodes in the N+ expansion, standard UK practice, so no target-volume or dose decision moves. The trial's value for an RT reader is that a 12-month adjuvant IO tail can be run around that backbone at all, though only 61% completed it.
Durvalumab was given in all three positions (neoadjuvant, synchronous, adjuvant 12 months) on a 5FU/MMC backbone, and 39% discontinued early. That delivery figure, not the 80% DFS, is what constrains which durvalumab schedule is worth randomising in bladder preservation.

+3 more figures


| Treatment status | N = 54 | % |
|---|---|---|
| Completed planned treatment | 33 | 61 |
| Discontinued early | 21 | 39 |

| Baseline | Number | % |
|---|---|---|
| Age, median (IQR) | 69 | 62-76 |
| Female | 10 | 18 |
| Male | 45 | 82 |
| Prior neoadjuvant chemo, yes | 41 | 75 |
| cT2 | 44 | 80 |
| cT3 | 11 | 20 |
| N+ | 7 | 13 |
10 details
Single-arm multi-stage feasibility and safety trial of durvalumab added to 5-fluorouracil/mitomycin C chemoradiotherapy in muscle-invasive bladder cancer. N=55 enrolled, 54 treated. A stage 1 expansion opened to node-positive pts, the first 6 with N+ disease.
Median age 69 (IQR 62-76), 45 (82%) male. cT2 in 44 (80%), cT3 in 11 (20%), N+ in 7 (13%) (N1 4, N2 3). 41 (75%) had prior neoadjuvant chemotherapy, so this is largely a post-NAC bladder-preservation population.
Durvalumab before, during and for 12 months after chemoRT, with 5-fluorouracil and mitomycin C as the radiosensitising backbone. 33/54 (61%) completed planned treatment; 21/54 (39%) discontinued early.
55Gy in 20 fractions to bladder; node-positive pts received 46Gy in 20 fractions to nodes alongside the bladder dose. This is the standard UK hypofractionated schedule, not an escalated or de-escalated variant.
Primary: disease-free survival rate at 12 months post chemoRT, read against a prespecified GO/NO-GO framework (GO ≥75%, contextual 60-75%, NO-GO <60%).
40/50 (80%) disease free at 12 months, 95% CI 0.67 to 0.89, clearing the GO threshold. 2 pts pending and 3 not evaluable. Investigators report very high bladder preservation and survival versus their previous trial data; those comparator figures are not given in the source.
The benchmark is the team's own BC2001 trial (James, JCO 2016), whose chemotherapy randomisation gave DFS HR 0.78 (0.60-1.02), stratified logrank p=0.07 on the slide shown. Comparison is to that historic control experience, not to a contemporaneous arm.
A 12-month DFS read is short for a preservation strategy where salvage cystectomy and late nodal relapse both fall outside the window. The evaluable denominator dropped from 55 to 50, and with 2 still pending the point estimate can move relative to a 75% threshold it clears by 5 points.
This clears a feasibility gate, not an efficacy one: the design question it answers is whether a randomised trial of durvalumab plus chemoRT is worth running, and the answer is yes. The 39% early discontinuation is the finding that should shape that trial, since a 12-month adjuvant tail that four in ten pts do not finish may not be the schedule worth randomising.
Single-arm feasibility/safety trial, N=55, 12-mo endpoint benchmarked against historic in-house CRT data. No randomised comparator; hard maturity gate applies.
- Which durvalumab component (neoadjuvant, synchronous, adjuvant) drives benefit
- Whether 80% 12-mo DFS survives a randomised comparator
- Drivers of the 39% early discontinuation
📚 Sources · 🐦 3 tweets
RAD-IO at #ASCO26: durvalumab added to chemoradiation in muscle-invasive bladder cancer cleared its efficacy bar in a bladder-preservation approach. Single-arm, benchmarked against prior CRT data.
— Katy Beckermann (@katy_beckermann) May 30, 2026
Durvalumab given before, during, and 12 months after chemoRT (55Gy/20Fr +… pic.twitter.com/UXxwoZzaMC
#ASCO26 🔬 Abstract 4504 | RAD-IO
— Dra. María Natalia Gandur Quiroga (@nataliagandur) May 30, 2026
Durvalumab + chemoradiotherapy in muscle-invasive bladder cancer
Presented by Nicholas D. James, PhD, MBBS, FRCP@OncoAlert@ASCO
Bladder preservation in MIBC remains one of the most important curative-intent questions in GU oncology.
The key… pic.twitter.com/W6JqzTVsJ3
RAD-IO: chemoradiation (5FU+MMC) + Durva in MIBC. #ASCO26 pic.twitter.com/yTyhkdjCox
— Álvaro Pinto (@dralvaropinto) May 30, 2026
Management After pCR in MIBC (Panel)
TL;DRPanel review: sandwich immunotherapy regimens continue planned adjuvant therapy regardless of pCR, with de-escalation still unanswered.
SWOG 8710ABACUSCHECKMATE-274KEYNOTE-905VOLGANIAGARAVESPERKEYNOTE-B15
In MIBC pts who reach pT0N0 at cystectomy on a sandwich regimen, this supports completing planned adjuvant therapy rather than stopping on pathologic response; after cisplatin-based chemo alone, surveillance remains the presented standard.

+2 more figures

| Setting | Trial | Reported outcome |
|---|---|---|
| Cisplatin-ineligible | KEYNOTE-905 | Periop EVP now standard |
| Cisplatin-ineligible | VOLGA | EV + durva/treme improved EFS (press release) |
| Cisplatin-eligible | NIAGARA | 24-mo OS 82.2% vs 75.2% |
| Cisplatin-eligible | VESPER | 5-yr OS 66% vs 57%, ddMVAC > gem/cis |
| Cisplatin-eligible | KEYNOTE-B15 | OS improved vs gem/cis, under FDA review |

11 details
ASCO 2026 GU education session, not a trial. Synthesizes SWOG 8710, NIAGARA, VESPER, KEYNOTE-905, KEYNOTE-B15 and VOLGA into a position on what to do after pCR.
The practice answer presented is continue: resume durvalumab for 8 months post-cystectomy on the NIAGARA regimen, resume EVP post-cystectomy on perioperative EVP. Surveillance after pCR is standard only for cisplatin-based chemo alone.
The continue-vs-stop question has never been randomized. Not all pts in the source trials completed adjuvant therapy, often for toxicity, so the observed benefit reflects a mixed delivered dose rather than the full planned course.
The session names the two open questions itself: the relative contribution of the pre- versus postoperative components, and whether adjuvant therapy can be de-escalated on pCR or another biomarker. Neither is answerable from an intention-to-treat perioperative design.
- Relative contribution of pre- vs postoperative components
- Can adjuvant therapy be de-escalated based on pCR or biomarkers
📚 Sources · 🐦 1 tweet
#ASCO26 GU Oncology Spotlight 🚨
— Dra. María Natalia Gandur Quiroga (@nataliagandur) May 30, 2026
🔬 Management in Bladder Cancer After Pathologic Complete Disease Response
Presented by Brendan J. Guercio, MD@OncoAlert@ASCO
In muscle-invasive bladder cancer, pCR after neoadjuvant therapy is one of the most powerful prognostic signals we… pic.twitter.com/sMd2In7X3p
Living Longer, Living Better (GU Discussant)
TL;DRASCO 2026 GU discussant on curing more while preserving organ, bladder, and kidney function across MIBC, RCC, and ctDNA selection.
EV209EV309RAMPART
For an RT reader the delivery slide is the actionable part: full 55 Gy in 20 fractions was given in 54 (100) with no extension or delay in 47 (87) alongside durvalumab, so the immunotherapy did not cost RT intensity. EV-309 then places chemoradiation as the randomised comparator, meaning the bladder-preservation standard is now the control arm.
In cT2-4a N0 MIBC being counselled for bladder preservation, this supports discussing chemoradiation plus checkpoint blockade as deliverable and trials of EV-based sparing as open questions; it does not extend to node-positive or metastatic disease. The longer read
The delivery slide is the actionable part: full 55 Gy in 20 fractions in 54 (100) with no extension or delay in 47 (87) while durvalumab ran concurrently, so RT intensity survived the combination. EV-309 then makes chemoradiotherapy the randomised control arm for a drug-only bladder-sparing strategy.
Systemic components absorbed the attrition: chemotherapy discontinued early in 12 (22) and durvalumab in 21 (39). In adjuvant RCC the discussant's position is that adjuvant IO has no proven benefit in non-clear cell disease, while ctDNA separates 24-mo DFS far better than pathology (79.9% vs 38.8% on pembrolizumab).
EV-209 keeps cystectomy as the fallback for non-clinical-CR pts in cystectomy-eligible cT2-4a N0 MIBC (N=240), and EV-309 (N=390) enrols only pts ineligible for or refusing cystectomy. Bladder-intact event-free survival counts cystectomy as an event, so the trials are structured around deferring surgery, not replacing it outright.

+2 more figures

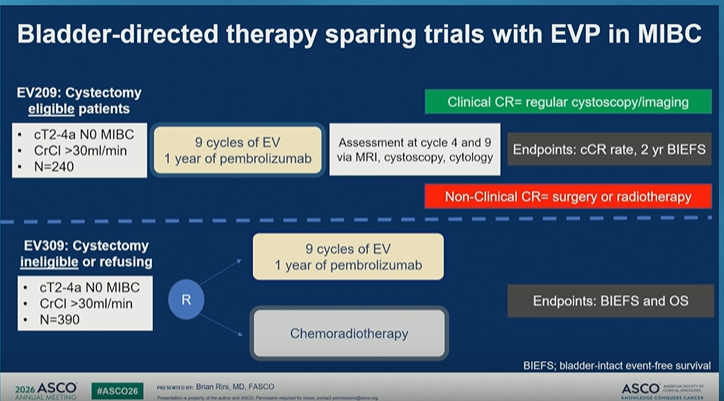
9 details 4 trials watching
Discussant presentation, not an original trial. Brian Rini, MD, FASCO discusses ASCO 2026 GU data spanning MIBC bladder preservation, adjuvant RCC, and ctDNA-based selection.
The chemoradiation regimen under discussion is 55 Gy in 20 fractions with mitomycin C and 5-FU. All 54 (100) received the full dose and 47 (87) had no extension or delay, so adding durvalumab did not erode RT delivery.
Concurrent mitomycin C plus 5-FU with durvalumab. Mitomycin C dose reduced in 4 (7), 5-FU Week 1 dose reduced in 9 (17), chemotherapy discontinued early in 12 (22). Durvalumab completed in 33 (61), discontinued early in 21 (39) for toxicity and progression.
The EV platform reframes the comparison: EV-309 randomises cystectomy-ineligible or refusing cT2-4a N0 pts (N=390) against chemoradiotherapy for BIEFS and OS, while EV-209 (N=240) tests EV plus pembrolizumab in cystectomy-eligible pts with cCR and 2yr BIEFS. In adjuvant RCC the discussant's read is that adjuvant IO has no proven benefit in non-clear cell disease, with RAMPART non-clear cell subgroups too small to resolve it.
Selection, not intensification, is the through-line. Pathologic features are called a crude selection tool, and the ctDNA-stratified adjuvant RCC curves separate far more than pathology does (ctDNA-negative 24-mo DFS 79.9% on pembrolizumab and 72.9% on placebo, versus 38.8% and 18.3% in ctDNA-positive pts). The same logic sits under bladder preservation, where the unanswered question is which pt keeps their bladder, not whether the regimen can be delivered.
Everything here is second-hand from a discussant slide deck, so denominators, CIs and per-arm attributions are partial. The RAMPART non-clear cell forest plot arrived with row association uncertain in OCR, and its point estimates are not attributed to specific histologies. Central pathology review is still ongoing.
| Component | Outcome | Number (%) |
|---|---|---|
| Radiotherapy | Received full 55 Gy in 20 fractions | 54 (100) |
| Radiotherapy | No extension or delay | 47 (87) |
| Chemotherapy | Mitomycin C dose reduced | 4 (7) |
| Chemotherapy | 5-FU Week 1 dose reduced | 9 (17) |
| Chemotherapy | Chemotherapy discontinued early | 12 (22) |
| Durvalumab | Completed | 33 (61) |
| Durvalumab | Discontinued early | 21 (39) |
- Long-term bladder preservation, function and QoL after chemoradiation plus durvalumab n=11 · primary completion 2026-02 · chemoRT +/- durvalumab, node-positive bladder
- Whether EV-based bladder sparing beats chemoradiotherapy on BIEFS and OS recruiting A Study to Find Out if Enfortumab Vedotin Given With Pembrolizumab Helps People With Muscle-invasive Bladder Cancer Keep Their Bladder Phase 2n=240 · primary completion 2027-11 · phase 2 EV+pembro bladder-sparing, n=240recruiting Enfortumab Vedotin in Combination With Pembrolizumab vs. Concurrent Chemoradiotherapy (cCRT) in People With Muscle Invasive Bladder Cancer (EV-309) Phase 3n=390 · primary completion 2030-03 · phase 3 EV+pembro vs cCRT, bladder preservationn=56 · primary completion 2031-04 · response-adapted EVP induction, cCRT or RC on failure
- Whether ctDNA-guided selection changes adjuvant RCC outcomes
📚 Sources · 🐦 1 tweet
#ASCO26 GU Oncology Spotlight 🚨
— Dra. María Natalia Gandur Quiroga (@nataliagandur) May 30, 2026
🔬 Living Longer, Living Better: Can We Have It All?
Discussant: Brian I. Rini, MD, FASCO@OncoAlert@ASCO
This GU session captured one of the central tensions in curative-intent oncology:
Can we improve cure rates while preserving quality of… pic.twitter.com/AMwrRZZM2Q
Clinico-transcriptomic Risk Stratification (Abstract 5000)
ForNCCN high-risk / very-high-risk localized prostate, definitive RT + ADT
TL;DR~¼ of NCCN ≥HR pts carry discordant clinical vs biomarker risk; 22-gene GC independently prognostic for MFS, DM, OS.
The de-escalation cell is where the risk sits: 9% of NCCN ≥HR pts read clinically high but biomarker low, and the framework withholds AAP from them. The 15% running the other way is the easier sell. What moves is whether GC gets ordered at consult, not any planning parameter.
In NCCN high-risk or very-high-risk localized prostate headed for definitive RT + ADT, this supports ordering a 22-gene GC before the abiraterone decision; it does not speak to post-prostatectomy salvage, node-positive, or metastatic disease. The longer read
RT + ADT is fixed in both branches, so nothing here touches dose, target volume, or fractionation; the framework is a consult-time test-order decision. Reclassification runs both ways, 15% clinically lower but biomarker higher and 9% the reverse, on GC bands of 0.6 and 0.85.
Intensification with AAP in localized disease gets a biomarker gate instead of an NCCN label: NCCN class and GC each contribute up to 2 points, and a sum ≥ 3 triggers AAP. GC was tested as prognostic across MFS, DM, and OS; no treatment-by-GC interaction is reported, so predictive value is unestablished.

+3 more figures
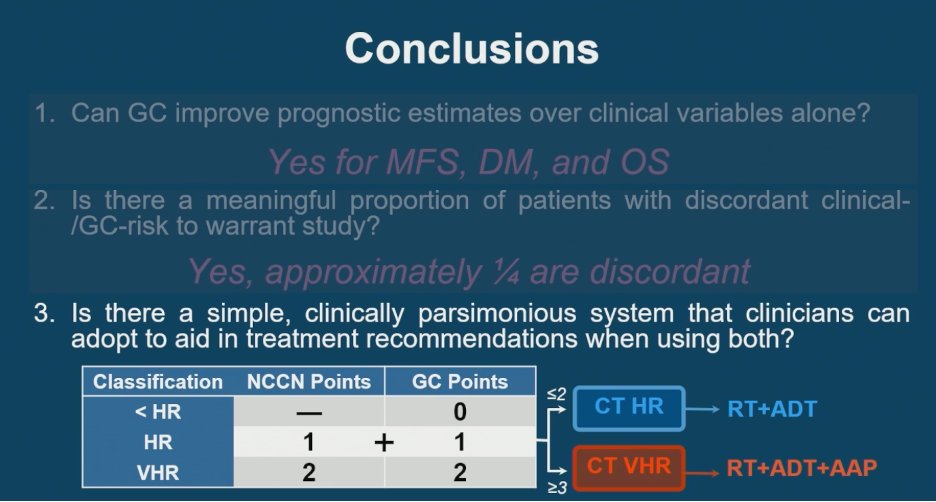

| Clinical risk | ↓ Biomarker | ↑ Biomarker |
|---|---|---|
| ↓ Clinical | 49% | 15% |
| ↑ Clinical | 9% | 27% |

8 details
Clinico-transcriptomic analysis of NRG cohorts modeling the 22-gene GC as a continuous variable (per 0.1 unit) alongside clinical covariates, with treatment carried as a covariate. Contributing trials, N, and follow-up duration are not reported in the source.
NCCN ≥ high-risk localized prostate, spanning NCCN HR and VHR. Baseline age, PSA, and grade distributions are not reported in the source.
Every branch of the framework keeps RT + ADT. No dose, fractionation, target volume, or ADT duration is reported, so RT enters as a fixed backbone rather than a variable under test.
Prognostic performance assessed on MFS, distant metastasis, and OS. No single primary endpoint is stated, and the framework itself is not compared against a randomized alternative.
GC was independently prognostic for all three endpoints (p<0.001); the row-level hazard ratios are not legible in the source slide. Approximately ¼ of the ≥HR population carries discordant clinical vs biomarker risk.
| Score (NCCN + GC) | CT risk | Recommendation |
|---|---|---|
| ≤ 2 points | CT HR | RT + ADT |
| ≥ 3 points | CT VHR | RT + ADT + AAP |
STAMPEDE M0 (Attard, Lancet 2022) is the external yardstick: the CT HR and CT VHR curves are overlaid on that trial's RT + ADT arm rather than on a randomized internal control. Eligibility, staging era, and ADT duration differ between cohorts, so the vertical gap carries trial effects alongside risk-group effects.
The GC term's hazard ratios and confidence intervals are not legible in the source, so the size of the increment over clinical variables cannot be checked. The 9% clinically-high / biomarker-low cell is where the framework withholds intensification, and its outcomes are the ones a reader most needs before acting.
The contribution is a parsimonious integer score computable at the consult desk, extending Spratt et al. (JCO 2018) to the modern VHR population. What it does not settle is whether the signal separating these curves also identifies who benefits from AAP: a prognostic split widens absolute benefit for a uniformly effective drug without any interaction, and none is reported here.
Retrospective pooled analysis; GC shown prognostic, not predictive. Intensification threshold benchmarked against STAMPEDE across trials, not randomized within cohort; no treatment-by-GC interaction in source.
- Does GC predict abiraterone benefit or only prognosis?
- Prospective validation of the ≥3-point intensification threshold
- Whether NCCN VHR pts with GC < 0.6 can omit AAP
📚 Sources · 🐦 2 tweets
#ASCO26 GU Oncology Spotlight 🚨
— Dra. María Natalia Gandur Quiroga (@nataliagandur) May 30, 2026
🔬 Abstract 5000 | High-risk prostate cancer
Clinico-transcriptomic risk stratification to guide abiraterone intensification
Presented by Krishnan R. Patel, MD, MHS@Krishnan_Patel@OncoAlert@ASCO
In high-risk localized prostate cancer,… pic.twitter.com/pZSCiTyGB8
#ASCO26 Dr. Patel presented a clinically practical framework integrating NCCN clinical risk + a 22-gene genomic classifier to guide treatment intensification in high-risk localized prostate cancer.
— Julian Chavarriaga (@chavarriagaj) May 30, 2026
Key findings:
🔹 The genomic classifier independently improved prognostic… pic.twitter.com/fRcdTmfBec
PREPEC
ForSkin- or nipple-sparing mastectomy, therapeutic or risk-reducing, implant reconstruction
79.2 vs 74.3
Difference 4.8 (95% CI 1.0-8.7), p=0.01
TL;DRPre-pectoral implant improved 24-mo BREAST-Q physical well-being (chest) by 4.8 points, but implant loss 21.1% vs 14.5%.
The 4.8-point BREAST-Q gain (1.0 to 8.7) sits against a 5.7-point higher implant loss rate (-2.4 to 13.8), so this is a trade-off, not a win. Source reports no post-mastectomy RT stratification or irradiated subgroup, so whether pre-pectoral holds up under PMRT is untested here.
In women planned for skin- or nipple-sparing mastectomy with implant reconstruction, this supports pre-pectoral placement for patient-reported chest well-being while flagging higher device loss; it does not address women who will need post-mastectomy radiotherapy. The longer read
Nothing in the source stratifies by post-mastectomy RT or reports capsular contracture, so the irradiated implant patient is not addressed. A 21.1% unplanned device loss rate at 24 months without radiation is the baseline to hold in mind when timing chest wall RT around a pre-pectoral reconstruction.
The primary endpoint is met (4.8 points, 1.0 to 8.7, p=0.01) but the prespecified non-inferiority safety hypothesis is not: unplanned device loss or replacement was 21.1% versus 14.5%. This makes plane selection a documented consent conversation about reoperation risk, not a default technique choice.

| IBBR assignment | N | 24-mo LS mean (95% CI) |
|---|---|---|
| Pre-pectoral IBBR | 191 | 79.2 (75.5 - 82.8) |
| Sub-pectoral IBBR | 189 | 74.3 (70.7 - 78.0) |
| Difference | 4.8 (1.0 - 8.7), p=0.01 |
+2 more figures

| Actual IBBR positioning | Unplanned loss/replacement at 24 mo, crude % (n/N) |
|---|---|
| Pre-pectoral IBBR | 21.1% (41 / 194) |
| Sub-pectoral IBBR | 14.5% (27 / 186) |
| Adjusted difference (95% CI) | 5.7 (-2.4 to 13.8) |

9 details
International randomized trial (PREPEC / OPBC-02) of pre-pectoral versus sub-pectoral implant-based breast reconstruction after skin-sparing or nipple-sparing mastectomy. Follow-up to 24 months, with 6 post-randomization patient-reported timepoints.
Women undergoing nipple-sparing or skin-sparing mastectomy in either the therapeutic or risk-reduction setting. Primary analysis included 191 pre-pectoral and 189 sub-pectoral; safety was analysed by actual positioning (194 versus 186).
Primary: long-term patient-reported physical well-being (chest) on BREAST-Q, scored 0 to 100 with higher better. Main secondary safety endpoint: unplanned loss or replacement of expander or implant.
Primary endpoint met; the safety endpoint moved against pre-pectoral placement. See the endpoint tables above.
Unplanned implant or expander loss or replacement at 24 months was 21.1% (41/194) pre-pectoral versus 14.5% (27/186) sub-pectoral, adjusted difference 5.7% (-2.4 to 13.8), which the investigators call inconsistent with the non-inferiority hypothesis.
Longitudinal completion ranged 83-95% and the primary estimate rests on multiple imputation with imputed baseline values, so the 4.8-point difference carries missing-data assumptions on top of its confidence interval. Surgeon and patient blinding is not feasible for a positioning trial, which cuts directly at a patient-reported primary endpoint.
The trial answers the PRO question it asked and simultaneously undercuts the assumption that pre-pectoral placement is device-safe. Whether a 4.8-point BREAST-Q gain is worth a 5.7-point absolute rise in unplanned reoperation is a preference-sensitive decision, not one the trial resolves.
Randomised, prespecified PRO primary endpoint met, but the safety co-read failed its non-inferiority hypothesis, so the trade-off, not the win, is the finding.
- Does pre-pectoral placement hold up under post-mastectomy radiotherapy
- Capsular contracture rates by implant plane
- Durability of the well-being advantage beyond 24 months
📚 Sources · 🐦 1 tweet
📌 Surgical de-escalation of implant-based breast reconstruction after mastectomy for breast cancer treatment or prevention: The international randomized phase I|I
— Elisabetta Bonzano MD, PhD (@to_be_elizabeth) May 30, 2026
PREPEC trial (ОРBC-02).
Presented by Walter Weber ✨#ASCO26 @OncoAlert #OncoAlertAF #BreastCancer pic.twitter.com/WE20JcBQG0
Neo-CRAG
ForcT3N2-3M0 / cT4 gastric or Siewert II-III EGJ adenocarcinoma, D2-resectable
HR 0.750
95% CI 0.607-0.928, P=0.008; 3yr DFS 55.6% vs 42.4%
TL;DRAdding preop 45Gy/25fx to periop XELOX raised 3yr DFS 55.6% vs 42.4%, HR 0.750; mOS 67.5 vs 37.6mo.
The RT case here rests on locoregional control: LRR after R0 fell to 9.4% from 18.3%, tracking the ypN0 (56.1% vs 36.4%) and pCR gains, which is the mechanistic chain CRITICS and TOPGEAR never produced. Dose was conventional 45Gy/25fx preoperatively, and G3+ postop complications stayed flat (9.0% vs 7.6%), so the deliverability objection to preop RT before D2 loses force.
In node-heavy cT3N2+ or cT4 gastric/Siewert II-III disease heading to D2 resection, this supports revisiting preoperative chemoRT rather than chemo alone; it does not speak to cT2N0-N1 disease or to pts already committed to a FLOT backbone. The longer read
Conventional 45Gy/25fx delivered preoperatively, after cycle 1 of chemo, halved locoregional recurrence after R0 resection (9.4% vs 18.3%) with no excess G3+ postoperative complications (9.0% vs 7.6%). That combination, a local-control gain without a surgical-morbidity cost, is what the omission decision in node-heavy cT3N2+ disease has been waiting for.
The systemic backbone was XELOX in both arms, so the DFS gain is attributable to radiotherapy rather than to the regimen, but the control arm's 37.6 mo median OS is the caveat: this does not tell you whether radiotherapy still adds on top of FLOT, whose own advantage is partly locoregional. Sequencing of RT after cycle 1 with attenuated dosing was deliverable.
Every pt was intended for standardized D2 resection, and preoperative chemoRT did not degrade it: G3+ postoperative complications were 9.0% vs 7.6%, and 448 of 620 randomised pts reached gastrectomy. ypN0 rose to 56.1% from 36.4%, which changes what the surgeon can expect to find in the nodal basin rather than the extent of dissection required.

| Endpoint | CRT | CT | Effect size |
|---|---|---|---|
| 3yr DFS | 55.6% (50.1-61.1) | 42.4% (36.9-47.9) | HR 0.750 (0.607-0.928), P=0.008 |
| Median DFS | 52.7 mo | 24.4 mo | n/a |
| 5yr OS | 50.1% | 44.2% | HR 0.781 (0.628-0.970), P=0.025 |
| Median OS | 67.5 mo | 37.6 mo | n/a |
9 details
Randomised, multicenter, phase 3 trial, N=620 (310 per group), 13 referral hospitals in China, accrual 2013-2022. Follow-up on the DFS curve extends past 120 months.
High-risk locally advanced gastric or EGJ adenocarcinoma: cT3N2-3M0, cT4aN+M0, or cT4bNanyM0, Siewert II/III permitted. 225 (36.3%) had an EGJ primary, and every pt was intended for standardized D2 resection.
Both arms: 3 cycles preoperative XELOX (oxaliplatin 130 mg/m² D1, capecitabine 1000 mg/m² BID D1-14, Q3W) then D2 gastrectomy then 3 adjuvant XELOX cycles.
CRT arm added concurrent 45 Gy / 25 fractions after cycle 1 of preoperative chemo, with attenuated concurrent dosing (oxaliplatin 100 mg/m², capecitabine 825 mg/m²). Target volume not specified in source.
Primary: disease-free survival, from randomization to progression, relapse, or death. Secondary: overall survival, pCR, R0 resection, safety.
Primary endpoint met. The locoregional read is the one an RT reader needs: LRR 9.4% vs 18.3% among R0-resected pts.
G3+ haematologic toxicity 14.6% vs 10.3%, the expected cost of concurrent chemoRT. G3+ postoperative complications were comparable, 9.0% vs 7.6%, so preoperative RT did not measurably worsen D2 surgical morbidity.
CRITICS (postoperative chemoRT after D1+ surgery) and TOPGEAR (preoperative chemoRT with ECF/FLOT) both failed to show a survival gain for radiotherapy in this disease. Neo-CRAG differs on three axes at once: RT given preoperatively, D2 resection mandated, and enrolment restricted to node-heavy cT3N2+ or cT4 disease.
The 2013-2022 accrual window means the control arm reflects a doublet era; a 37.6 mo median OS in the control group is short against contemporary FLOT-treated series. Single-country enrolment with uniformly high-quality D2 surgery also caps generalisability to centres with variable nodal dissection.
The pCR, downstaging, ypN0 and LRR gradient forms a coherent mechanistic chain from RT to the DFS separation, which is what earlier negative trials lacked. What it does not settle is whether that chain survives a stronger systemic backbone, since much of FLOT's advantage over a doublet is itself locoregional.
CONSORT flow
Randomised ph3, prespecified DFS met with OS support, but the chemo backbone is XELOX not FLOT, so it contests RT omission without settling it.
- Does preoperative chemoRT still add benefit on a FLOT backbone?
- Generalizability outside high-volume D2 centers
- Optimal target volume and elective nodal coverage not reported in source
📚 Sources · 🐦 1 tweet
Neo-CRAG: Ph3 RCT (n=620, gastric/GEJ) - adding neoadj chemoRT to peri-op XELOX improved OS (68 v 38 mo).
— Dr. Nina Niu Sanford (@NiuSanford) May 30, 2026
Limitation=non-FLOT, BUT still relevant IMO b/c:
1) DFS/OS benefit substantial.
2) Improvements in pCR, downstg, LRR supports plausible RT effect on OS. #ASCO26 @OncoAlert pic.twitter.com/eeM0Z8p20M
SENOMAC NCT02240472
ForcN0 T1-T3 breast, 1-2 sentinel-node macromets, planned nodal RT
HR 0.89
95% CI 0.66-1.19, P<0.001 for noninferiority (margin 1.44)
TL;DR5yr RFS 89.7% vs 88.7% omitting completion ALND, HR 0.89 (0.66-1.19), noninferior in 1-2 SLN macromets.
The axilla here was irradiated, not left alone: 89.9% vs 88.4% received nodal target volumes, so this validates SLNB plus regional nodal RT, not surgical de-escalation without RT. Untreated non-SLN disease was present in 34.5%, meaning the RT field is carrying real burden. Nodal level doses and volumes are not yet reported.
In cN0 T1-T3 disease with one or two sentinel macrometastases, including mastectomy, T3 and extracapsular extension, this supports omitting completion dissection when regional nodal irradiation is planned; it does not speak to pts in whom nodal RT is being omitted. The longer read
Nodal target volumes were treated in 89.9% vs 88.4%, so the axilla was managed, not observed, and the RT field is covering the 34.5% non-sentinel-node burden the surgery would have removed. Doses and nodal levels are not yet reported, so the trial supports covering the regional nodes without specifying how.
Systemic therapy shares the load: approximately 65% received chemotherapy and 93% endocrine therapy, and 9.9% of dissected pts were upstaged to pN2 with 3.0% pN3, meaning omission removes nodal counts that currently inform adjuvant intensity. Decisions will rest on tumour biology and genomic tools rather than final node count.
Completion dissection can be omitted in the subgroups the earlier trials could not answer: mastectomy (36.7%), T3 (5.5%) and extracapsular extension, with 5yr RFS 89.7% vs 88.7%. The trade is accepting known residual disease, since 34.5% of dissected pts had additional non-sentinel-node metastases and 9.9% were pN2.
13 details 5 trials watching
Prospective randomized phase 3 noninferiority trial, 1:1, 67 hospitals in Sweden, Denmark, Germany, Greece and Italy. 2766 enrolled Jan 2015 to Dec 2021; per-protocol population 2540 (1335 sentinel-node biopsy only, 1205 completion dissection). Median follow-up 46.8 months (range 1.5 to 94.5).
cN0, T1 to T3 breast cancer with one or two sentinel-node macrometastases (>2mm). Preoperative axillary ultrasound was mandatory; suspicious nonpalpable nodes were still eligible even with FNA-confirmed metastasis. Additional micrometastases and extracapsular extension were allowed, and both breast-conserving surgery (63.3% / 64.3%) and mastectomy (36.7% / 35.7%) were eligible. Mean age 61.
RT including nodal target volumes was given to 89.9% (1192/1326) of the sentinel-node-only group and 88.4% (1058/1197) of the dissection group. Whole-breast RT was mandatory after breast-conserving surgery, but the protocol stipulated no specific target volumes or doses, deferring to national guidelines. QA on 1154 plans showed eCRF-to-plan concordance of 99.3% for breast or chest wall and 96.6% for nodal volumes.
Primary: overall survival (switched from breast cancer-specific survival in 2020 on DSMB advice). Prespecified secondary endpoints were recurrence-free survival, breast cancer-specific survival and patient-reported outcomes. Noninferiority required the upper CI bound for recurrence or death below 1.44.
No clinical lymphedema measurements were performed; arm morbidity relies on the LYMPH-ICF, QLQ-C30, QLQ-BR23 and EQ-5D questionnaires at 1, 3, 5 and 10 years. Only 1-year data from a Swedish-Danish subpopulation are published; 3-year data for the whole trial are not yet available.
Consistent with ACOSOG Z0011 and AMAROS, but the authors place SENOMAC alongside AMAROS and OTOASOR rather than Z0011, SINODAR-ONE or POSNOC, because nodal irradiation was routine here. Where the earlier trials enrolled nearly 40% micrometastasis-only pts, one T3 patient between them, and only 248 mastectomies (17.4%) in AMAROS, SENOMAC filled each of those gaps.
Detailed nodal level doses and volumes are not yet reported, so the RT dose actually treating the residual axilla is unquantified. Withdrawal was higher in the dissection arm, reflecting pts' wish to avoid the operation. The ER+/HER2+ subgroup HR of 0.26 (0.07-0.96) rests on 3 versus 10 events among 13 subgroups and should not be read as a real interaction.
The completion dissection arm shows what is being left behind: 34.5% (403/1167) had additional non-sentinel-node metastases, rising to 51.3% with two macrometastases, and 9.9% were upstaged to pN2 with 3.0% pN3. Noninferior recurrence-free survival despite that residual burden is a statement about what systemic therapy plus nodal RT can control, not about the axilla being clean.
| Event | SLNB only (N=1335) | cALND (N=1205) |
|---|---|---|
| Local recurrence | 12 (0.9) | 10 (0.8) |
| Regional recurrence | 6 (0.4) | 6 (0.5) |
| Distant recurrence | 44 (3.3) | 53 (4.4) |
| Death | 62 (4.6) | 69 (5.7) |
| Recurrence or death as first event | 95 (7.1) | 96 (8.0) |
CONSORT flow
Prespecified noninferiority met with wide margin to boundary; enrolls the mastectomy, T3 and ECE subgroups Z0011 and AMAROS excluded, resolving the residual uncertainty.
- Nodal RT target volumes and doses needed for this result n=1900 · primary completion 2026-07 · axillary treatment vs none, 1-2 SLN macrometsrecruiting The T-REX Trial: Tailored Regional External Beam Radiotherapy in Clinically Node-negative Breast Cancer Patients With 1-2 Sentinel Node Macrometastases. Phase NAn=1350 · primary completion 2028-12 · omits regional RT in ER+ 1-2 SLN macrometsrecruiting Level I-II Axillary Irradiation in Breast Cancer With Sentinel-Node Macro-metastases Phase NAn=1608 · primary completion 2032-12 · level I-II axilla vs whole regional RT, SLN macromets
- Late recurrence in luminal disease beyond 5 years
- Arm morbidity: 3yr and 5yr lymphedema outcomes recruiting Axillary Management in Breast Cancer Patients With Needle Biopsy Proven Nodal Metastases After Neoadjuvant Chemotherapy Phase NAn=1900 · primary completion 2030-02 · 5y lymphedema endpoint after omitting ALND + ARTnot yet Omission of Axillary Lymph Node Dissection in Case of Tumor Spread to Lymph Nodes in the Armpit in Breast Cancer Phase NAn=1380 · primary completion 2030-12 · TAD vs ALND, arm lymphedema + shoulder function
📚 Sources · 📄 1 paper
SWOG/NRG S1914 NCT04214262
ForT1-3N0M0 NSCLC ≤7cm, medically inoperable or declined surgery, ≥1 risk factor
HR 1.15
95% CI 0.65-2.01, p=0.63; primary endpoint not met
TL;DROS HR 1.15 (0.65-2.01), p=0.63: atezolizumab added to SBRT failed, with more local failures (13% vs 7%) and G≥3 AEs (12% vs 2%).
The RT read is that adding IO did not just fail to help, it tracked with MORE local failure (13% vs 7%), inside a BED ≥100 Gy 3-8 fraction regimen that is already delivering >90% in-field control. Central review of those events is pending, so treat the local signal as unconfirmed. This closes the question of routinely sequencing atezolizumab around definitive SBRT off-protocol.
In medically inoperable T1-3N0M0 NSCLC with high-risk features (size ≥2 cm, SUV ≥6.2, or poorly differentiated histology), this supports SBRT alone at BED ≥100 Gy without added checkpoint blockade; it does not address IO for node-positive or operable early-stage disease. The longer read
SBRT alone at BED ≥100 Gy in 3-8 fractions remains the standard, and adding atezolizumab tracked with MORE local failure (13% vs 7%) rather than better in-field durability. Central review of those events is pending. Regional (2% vs 3%) and distant (4% vs 5%) failure were unchanged, so the out-of-field rationale also went unrewarded.
Neoadjuvant/concurrent/adjuvant atezolizumab 1200 mg Q3W × 8 cycles bought no OS or PFS benefit and cost a six-fold rise in G≥3 AEs (12% vs 2%) including a G5 respiratory failure. This argues against porting PACIFIC-style consolidation logic into node-negative early-stage disease pending the PD-L1 analysis.
11 details
Randomized phase III SWOG/NRG cooperative-group trial, accrual 8/13/20 to 9/6/24, 417 randomized / 403 eligible (201 SBRT alone, 202 atezolizumab + SBRT) against an accrual goal of 432. Closed at the first interim analysis for futility on both OS and PFS. Median follow-up in living pts was 12 months (range 0.03-49).
T1-3N0M0 NSCLC ≤7 cm, medically inoperable or declined surgery, with ≥1 recurrence risk factor: tumor diameter ≥2 cm, ≥6.2 (SUV), or moderately/poorly/undifferentiated histology. Median age 73 (41-91), 89% ECOG 0-1, median tumor diameter 2.3 cm. Stratified by location (central vs peripheral), size (<4 vs ≥4 cm) and PS.
SBRT in 3-8 fractions to a BED ≥100 Gy in both arms, i.e. standard definitive dosing rather than a de-escalated backbone. In the experimental arm SBRT began with cycle 3, so radiation was delivered after two neoadjuvant atezolizumab cycles and concurrently with the third.
Atezolizumab 1200 mg IV Q3W for 8 cycles, given neoadjuvantly, concurrently and adjuvantly around SBRT. No protocol treatment was received by 6 pts on S and 8 on AS.
Primary: overall survival, compared by 1-sided stratified log-rank at the 2.5% level. Secondary: PFS, failure patterns, toxicity, QoL.
Neither OS nor PFS favored the IO arm, and local failure ran higher with atezolizumab. See the failure-pattern table and primary endpoint above.
| Failure site | SBRT alone | Atezo + SBRT |
|---|---|---|
| Local | 7% | 13% |
| Regional | 2% | 3% |
| Distant | 4% | 5% |
G≥3 AEs 12% on AS vs 2% on S (21 G3, 1 G4, and 1 G5 respiratory failure with atezolizumab; 3 G3 and 1 G4 with SBRT alone). A six-fold excess of high-grade toxicity with no efficacy return is the safety read.
The prior randomized phase II (PMID 37478883) suggested benefit from adding immunotherapy to SBRT; this larger phase III does not reproduce it. It also sits against PACIFIC-era logic, where consolidation IO helps after chemoRT for stage III, and shows that result does not port down to node-negative disease treated with ablative SBRT.
Follow-up is short (median 12 mo alive) and central review of local recurrence events is not complete, so the local-failure imbalance is provisional. The smoker subgroup harm signal was not multiplicity-controlled, and PD-L1 status, QoL and correlative blood/tissue analyses are all still pending.
A negative primary endpoint with a directionally worse PFS, worse local control and six-fold more high-grade toxicity is stronger than a null result: it argues against the abscopal/radiosensitization rationale in this setting. It does not exclude benefit in a biomarker-selected subset, which the pending PD-L1 analysis will test.
CONSORT flow
Phase III, primary OS endpoint not met, closed at interim for futility. Reaffirms SBRT alone as SoC and refutes the earlier phase II IO signal.
- Does a PD-L1-defined subset benefit from IO added to SBRT?
- Will central review confirm the excess local failures with atezolizumab?
- Is the worse outcome in former/never smokers real or chance?
📚 Sources · 📄 1 paper
Abstract
DBCG IMN2 NCT06549920
ForNode-positive early breast, upfront surgery + ALND, no neoadjuvant therapy
HR 0.85
95% CI 0.76-0.94, p=0.0016; 15y OS 65.0% vs 60.8%
TL;DRAdjusted OS HR 0.85 (0.76-0.94) with IMNI in node-positive breast cancer; 15y OS 65.0% vs 60.8% despite taxanes, trastuzumab, AIs and 3D RT.
The benefit held in the 1-3 node group, HR 0.85 (0.73-0.97), the population where guidelines still hedge on IMNI. It was delivered with free-breathing 3D wide tangents at 50 Gy/25 Fx, and dilution (20.4% incidental coverage left-sided) biases toward the null, so modern gated or VMAT coverage likely does no worse.
In node-positive breast cancer after upfront surgery and ALND, including 1-3 positive nodes, this supports covering the IMN in the regional field; it does not extend to pts treated after neoadjuvant therapy. The longer read
The 1-3 node HR 0.85 (0.73-0.97) addresses the group where IMN coverage is most contested, using 50 Gy/25 Fx free-breathing 3D tangents to ICS 1-4. Because incidental left-sided coverage (V90% 20.4%) dilutes the contrast, the benefit is likely understated with gated or VMAT coverage.
11 details 3 trials watching
Prospective nationwide population-based cohort across 6 Danish RT centres, N=4541, 2007-2014. Not randomized: IMNI allocated by tumour laterality per national guideline; ITT right vs left. Median follow-up 13.7y.
Macrometastatic node-positive breast cancer, all with ALND, mastectomy or BCS. Excluded neoadjuvant systemic therapy, bilateral BC, prior malignancy, recurrence before RT. Median age 59; 68.3% had 1-3 positive nodes.
EC x3 then docetaxel x3 when chemo indicated; AI postmenopausal, tamoxifen premenopausal; trastuzumab concurrent for HER2+. 96.2% of chemo pts received taxanes.
48 Gy/24 Fx before Jan 2009, 50 Gy/25 Fx after. IMN target ICS 1-4 with 3D conformal wide tangents, free breathing, plus level II-III, interpectoral and level IV in all pts.
Primary: OS. Secondary: breast cancer mortality and distant metastasis, with non-breast-cancer death as competing event.
15y death from ischemic or valvular heart disease 0.2% right vs 0.7% left. 15y secondary lung cancer death 1.8% vs 2.2%. No smoking or baseline cardiac data.
OS HR 0.85 sits with the EBCTCG regional RT RR 0.90 (0.84-0.96) and underpowered KROG 08-06 HR 0.87 (0.57-1.31). Magnitude matches DBCG IMN1, which treated pts before taxanes and 3D planning.
Left-sided controls got incidental IMN dose (median CTV V90% 20.4%) and 10.1% received IMNI, compressing separation. 1-3 node analysis was post hoc; no correction for multiple testing across subgroups.
Newer systemic therapy did not erase the IMNI gain. The medial/central ≥4 node HR 0.98 and ER-/HER2+ HR 1.49 are exploratory signals, not omission criteria; authors found no subgroup for safe omission.
| Endpoint | IMNI (n=2194) | No IMNI (n=2347) | Adjusted HR (95% CI), p |
|---|---|---|---|
| OS at 15y | 65.0% | 60.8% | 0.85 (0.76-0.94), p=0.0016 |
| Breast cancer mortality, 15y CI | 21.4% | 23.6% | 0.84 (0.74-0.95), p=0.0077 |
| Distant metastasis, 15y CI | 25.1% | 26.9% | 0.87 (0.78-0.98), p=0.026 |
| Subgroup | HR (95% CI) | 15y OS IMNI vs no IMNI |
|---|---|---|
| 1-3 LN (n=3100, post hoc) | 0.85 (0.73-0.97) | 72.3% vs 68.0% |
| 4-9 LN | 0.92 (0.75-1.12) | 55.3% vs 51.6% |
| ≥10 LN | 0.75 (0.59-0.96) | 39.2% vs 31.1% |
| Lateral ≥4 LN | 0.77 (0.64-0.93) | 53.8% vs 41.7% |
| Medial/central ≥4 LN | 0.98 (0.79-1.21) | 43.6% vs 50.4% |
| ER-/HER2+ | 1.49 (0.98-2.25) | 57.7% vs 68.2% |
Large prospective multicentre cohort, primary endpoint met with 13.7y f/u, but laterality allocation is not randomization. Aligns with EBCTCG and DBCG IMN1.
- Does IMNI benefit persist with adjuvant immunotherapy or ADCs?
- Is regional RT omission safe after neoadjuvant therapy with pCR? active Standard or Comprehensive Radiation Therapy in Treating Patients With Early-Stage Breast Cancer Previously Treated With Chemotherapy and Surgery Phase NAn=1636 · primary completion 2023-09 · regional nodal XRT vs breast/chestwall only post chemon=100 · primary completion 2028-06 · RNI de-escalation in cN1 → ypN0 after neoadjuvant therapyrecruiting Axillary Management in Breast Cancer Patients With Needle Biopsy Proven Nodal Metastases After Neoadjuvant Chemotherapy Phase NAn=1900 · primary completion 2030-02 · omits axillary RT if SLNB node-neg after NACT; DFS
- Is ER-/HER2+ subtype a true predictor of IMNI harm?
📚 Sources · 📄 1 paper
SWOG S1007
ForHR+/ERBB2- breast, 1-3 positive nodes, Oncotype RS ≤25
TL;DR5yr LRR 0.85% with RNI vs 0.55% without after BCS+RT in RS≤25 N1 disease; IDFS unchanged by RNI.
The number that moves the RNI decision is 0.55% 5yr LRR after BCS+RT without RNI, and equally low LRR in the endocrine-alone arm. Chemotherapy omission on a low RS does not by itself justify adding supraclavicular coverage. Target-volume detail beyond supraclavicular is not reported in source.
In HR+/ERBB2- N1 disease with RS ≤25 treated with BCS and whole-breast RT, this argues low RS alone does not compel nodal irradiation; it does not speak to RS >25, higher nodal burden, or ERBB2+ disease. The longer read
The actionable number is 0.55% 5yr LRR after BCS+RT without RNI in RS ≤25 N1 disease, against 0.85% with RNI. That floor leaves little absolute room for regional coverage, and IDFS did not move (premenopausal HR 1.03, postmenopausal HR 0.85). This informs the elective supraclavicular decision.
LRR stayed similarly low in the endocrine-therapy-alone group, so omitting chemotherapy on a low Recurrence Score did not raise locoregional risk. The conclusion is explicit: chemo omission is not an independent indication for RNI, which removes a reason to hedge a de-escalation decision.
9 details
Secondary analysis of the randomized SWOG S1007 trial (endocrine therapy alone vs chemotherapy then endocrine therapy). Radiotherapy data were prospectively collected across diverse practice settings, but RNI receipt itself was not randomized. Data analyzed June 2022 to April 2023.
Hormone receptor-positive, ERBB2-negative breast cancer with 1 to 3 involved nodes and Oncotype DX 21-gene Recurrence Score ≤25. 4871 female patients had radiotherapy forms; median age 57 (range 18-87).
RNI defined as targeting at least the supraclavicular region. 3947 (81.0%) reported radiotherapy receipt; of 3852 with complete target information, 2274 (59.0%) received RNI. Dose, fractionation, and internal mammary coverage are not reported in source.
Cumulative incidence of locoregional recurrence by locoregional treatment received, plus association between invasive disease-free survival and locoregional therapy, adjusted for menopausal status, treatment group, recurrence score, tumor size, nodes involved, and axillary surgery.
Median follow-up 6.1 years. See the LRR and IDFS tables above; IDFS did not differ by RNI receipt in either menopausal stratum.
| Locoregional treatment | 5yr LRR |
|---|---|
| BCS + RT with RNI | 0.85% |
| BCS + RT without RNI | 0.55% |
| Mastectomy + PMRT | 0.11% |
| Mastectomy, no RT | 1.7% |
| Group | HR (95% CI) | P |
|---|---|---|
| Premenopausal | 1.03 (0.74-1.43) | .87 |
| Postmenopausal | 0.85 (0.68-1.07) | .16 |
MA.20 and EORTC 22922 established the regional irradiation question in node-positive disease, both without an overall survival gain, in cohorts assembled before genomic risk stratification. This analysis reads that question in the population those trials could not define, biologically favorable N1, and finds an LRR floor low enough that a relative benefit has little absolute room to operate.
Radiotherapy information was recorded only in the first year after randomization, forcing a 1-year landmark that excludes the earliest events. Target detail stops at supraclavicular coverage, so internal mammary treatment cannot be separated, and the low absolute event count leaves the IDFS confidence intervals wide enough to accommodate a small effect in either direction.
The finding that matters is the floor, not the comparison: with 5yr LRR at or below 1.7% in every locoregional strategy examined, the population has too few events for regional irradiation to demonstrate meaningful absolute benefit. The explicit conclusion is that omission of chemotherapy is not an independent indication for RNI, which addresses a specific compensatory reflex rather than the general RNI question.
Prospectively collected RT data in a large trial cohort, but RNI receipt was not randomized; observational comparison, so an unmeasured-confounding read is unavoidable.
- Does any favorable N1 subgroup (3 nodes, RS near 25) still warrant RNI?
- Internal mammary coverage contribution, unseparable in this dataset
- Longer follow-up for late locoregional events in HR+ disease
📚 Sources · 📄 1 paper
Abstract
EORTC 22922/10925
ForStage I-III breast, central/medial tumor or involved axilla, post-ALND
61.0% vs 61.8% at 20yr
HR 1.00, p=.967; primary endpoint not met
TL;DR20yr OS 61.0% vs 61.8% (HR 1.00, p=.967): IM-MS nodal RT cut breast cancer mortality but added non-cancer deaths.
The breast cancer mortality gain (22.4% vs 18.6%, HR 0.82) is real and was fully offset by non-breast-cancer deaths (15.8% vs 20.4%, HR 1.26) that only emerged after 15 years. Cardiac disease ran 15.2% vs 11.7%. In a 1996-2004 planning era, that trade gates IM-MS coverage on achievable heart dose, not on nodal risk alone.
In a woman with a medial or central stage I-III tumor being considered for IM chain coverage, this supports treating the cardiac dose constraint as co-equal with nodal risk; it does not speak to modern DIBH or proton delivery, where the competing-mortality arm may not hold. The longer read
Breast cancer mortality fell (HR 0.82) and non-cancer death rose (HR 1.26), netting OS HR 1.00, with cardiac disease 15.2% vs 11.7% and lung fibrosis 6.3% vs 3.2%. Planning ran in the 2D era, so the decision this moves is achievable heart dose, not whether to cover the IM chain.
Systemic therapy was per institutional preference across 1996-2004 accrual, so the disease-specific gain (HR 0.82) sits on a backbone that predates current regimens. For a med onc the read is competing mortality: the excess non-cancer deaths after 15 years reframes how long-term cardiac surveillance should run in irradiated survivors.
9 details
Prospective multicenter randomized phase 3 trial, accrual 1996-2004, 4004 pts, with an RT quality-assurance program built in. The last analysis was planned at 20 years on the assumption that any survival effect of IM-MS-RT would be delayed. Median follow-up 22.2 years.
Women ≤75 yrs, unilateral histologically confirmed breast adenocarcinoma, stage I-III. Gate was tumor location or nodal status: centrally or medially located primary irrespective of axillary involvement, or any quadrant with axillary involvement. Median age 54.
Randomization was to internal mammary and medial supraclavicular (levels 3-4) nodal irradiation or not, layered on standard breast or chest wall treatment. Dose and fractionation are not given in the source excerpt. Planning ran in the two-dimensional and early-conformal era, when IM coverage at least doubled heart dose.
Primary: overall survival. Secondary: disease-free survival, distant metastases-free survival, breast cancer mortality, any breast recurrence.
Lung fibrosis 6.3% vs 3.2%, cardiac fibrosis 2.7% vs 1.7%, cardiac disease 15.2% vs 11.7% with IM-MS-RT. Severe (grade 3-4) events were uncommon and near-equal: cardiac 1.9% vs 1.7%, lung 0.3% vs 0.0%, so the excess sits in lower-grade, chronic morbidity rather than catastrophic events.
MA.20 and DBCG-IMN both read regional nodal RT positively at roughly ten-year horizons, and DBCG-IMN reported an OS gain. This trial covers the same anatomic question at twice that follow-up and shows the disease-specific gain surviving while the survival gain does not, which is the read those trials were too short to produce.
Systemic therapy was left to physician and institutional preference across an eight-year accrual, so the systemic backbone is heterogeneous and predates current regimens. The competing-mortality signal is a cause-of-death attribution over two decades in a population whose baseline cardiovascular risk rises independently, and the source does not report a cardiac-specific mortality breakdown separating RT-attributable from age-attributable death.
The two effects are both real and point opposite ways: HR 0.82 on breast cancer mortality, HR 1.26 on other deaths, netting HR 1.00 on OS. That arithmetic is the finding, and it argues the relevant question is not whether IM-MS coverage works but whether its cost can be engineered down.
| Endpoint | Control | IM-MS-RT | Effect size |
|---|---|---|---|
| Overall survival | 61.8% | 61.0% | HR 1.00, p=.967 |
| Disease-free survival | 49.0% | 48.2% | HR 0.97 (0.89-1.06), p=.5148 |
| Distant metastasis-free survival | 59.8% | 58.9% | HR 0.97 (0.88-1.08), p=.578 |
| Breast cancer mortality | 22.4% | 18.6% | HR 0.82 (0.72-0.95), p=.006 |
| Death not from breast cancer/unknown | 15.8% | 20.4% | HR 1.26, p=.002 |
Randomised, prespecified 20yr primary analysis, adequate power, endpoint reported honestly. Divergence from the 10yr-era read of nodal RT is internally valid, not a design artifact.
- Does modern heart-sparing delivery erase the excess non-cancer mortality?
- Which subgroups have enough breast cancer risk to justify the trade?
- Cardiac surveillance interval for irradiated long-term survivors
📚 Sources · 📄 1 paper
Abstract
Bladder Adjuvant Radiotherapy
ForPost-cystectomy MIBC, pT3-4 / pN+ / margin+ / ≤10 nodes dissected
87.1% v 76.0%
HR 0.43 (95% CI, 0.20 to 0.96), P = .04
TL;DR2yr LRFS 87.1% vs 76.0% with adjuvant pelvic IMRT after RC, HR 0.43 (0.20-0.96), P=.04; DFS/BCSS/OS not significant.
The RT read is the target volume and the technique: stoma-sparing IG-IMRT, 50.4Gy/28fx to cystectomy bed plus pelvic nodes, with no additional severe toxicity reported. That combination is deliverable in a standard department today, so this moves the offer-vs-observe decision for a pT3-4 or pN+ postcystectomy patient rather than leaving adjuvant pelvic RT as a historical toxicity concern.
In a postcystectomy MIBC patient with pT3-4, pN+, positive margin, or ≤10 nodes dissected who has completed perioperative chemotherapy, this supports discussing adjuvant pelvic RT for locoregional control; it does not address patients who received adjuvant immunotherapy. The longer read
The transferable detail is the technique: stoma-sparing IG-IMRT, 50.4Gy/28fx to cystectomy bed plus pelvic nodes, with no additional severe toxicity reported. Elective nodal coverage was standard in the treated volume. This moves the offer-versus-observe decision for pT3-4 or pN+ postcystectomy patients.
Over 90% of patients received perioperative chemotherapy (71% neoadjuvant), so the RT benefit sits on top of a modern systemic backbone rather than substituting for it. No patient received immunotherapy, so how adjuvant RT interacts with adjuvant checkpoint blockade in this same high-risk group is untested here.
Surgical adequacy is embedded in eligibility: ≤10 nodes dissected and positive margin were qualifying high-risk features alongside T3-4 and N1-3. That reframes a limited lymphadenectomy or a close margin as a trigger for adjuvant RT referral rather than observation.
10 details
Multicenter phase III RCT, 1:1 adjuvant RT versus observation after radical cystectomy. 153 patients randomly assigned June 2016 to May 2024 (Obs 76, RT 77), stratified by nodal involvement and chemotherapy timing. Median follow-up 47 months.
Nonmetastatic urothelial MIBC, high risk after RC by any one of T3-4, N1-3, positive margin, or ≤10 nodes dissected. Baseline load was heavy: 62% pT3-T4 and 41% pN+.
Over 90% received systemic chemotherapy (71% neoadjuvant, 20% adjuvant). None received immunotherapy in either arm.
Stoma-sparing IG-IMRT, 50.4Gy in 28 fractions, prescribed to the cystectomy bed and pelvic nodes. Elective nodal coverage was part of the treated volume, not an optional add-on.
Primary: 2-year locoregional recurrence-free survival. Secondary: disease-free survival, bladder cancer-specific survival, overall survival.
The primary endpoint was met; secondary endpoints all favored RT numerically without reaching significance. See the endpoint table for arm-level rates and hazard ratios.
| Endpoint | RT | Obs | HR (95% CI) |
|---|---|---|---|
| LRFS (1°) | 87.1% | 76.0% | 0.43 (0.20-0.96), P=.04 |
| DFS | 71.6% | 58.7% | 0.62 (0.36-1.05) |
| BCSS | 79.6% | 65.0% | 0.59 (0.33-1.10) |
| OS | 70.4% | 57.4% | 0.78 (0.49-1.26) |
The authors report no additional severe toxicity with adjuvant pelvic IMRT. Grade-level AE breakdown is not reported in the source abstract.
The primary endpoint is a 2-year locoregional readout under a 47-month median follow-up, so the headline reports early control rather than durability. Accrual spanned eight years, during which adjuvant immunotherapy entered practice in this exact population, and the control arm reflects none of it.
Adjuvant pelvic RT after cystectomy has been an open question since the older Egyptian NCI randomized experience, which used larger fields and conventional technique. This is the modern IMRT-era answer, and it lands positive on local control only, not survival.
A HR of 0.43 on locoregional control with an upper CI bound of 0.96 is a real but fragile signal in 153 patients. The consistent numeric direction across DFS (HR 0.62), BCSS (HR 0.59), and OS (HR 0.78) is reassuring but underpowered, and none of it settles whether locoregional control converts to survival.
CONSORT flow
Randomised, prespecified 2yr LRFS primary endpoint met in a setting where adjuvant RT is not standard. Small N and borderline CI limit confidence, not internal validity.
- Does locoregional benefit persist alongside adjuvant immunotherapy
- Does 2yr LRFS gain translate to survival with longer follow-up
- Which high-risk feature drives the benefit: pN+, margin, or nodal yield
📚 Sources · 📄 1 paper
Abstract
Pencil beam scanning proton vs IMRT photon PMRT: capsular contracture risk
ForSubpectoral implant reconstruction (TE/I or DTI) receiving PMRT
TL;DRProton vs photon PMRT CC HR 1.76 (0.93-3.32, P=.083) on MVA; 2-yr CC 50% with protons plus DTI.
The proton excess persists within both reconstruction types (2-yr CC 23% vs 12% after TE/I, 50% vs 35% after DTI) even though the adjusted HR crossed 1. Dose, fractionation and superficial constraints are not reported in source, so the PBS planning lever behind it is unknown. It bears on proton selection for implant pts.
In a pt planned for subpectoral DTI reconstruction who is being considered for PBS proton PMRT, this questions that pairing (2-yr CC 50%); it does not address autologous or prepectoral reconstruction. The longer read
The proton excess lost significance on MVA (HR 1.76, 0.93-3.32), but 2-yr CC stayed higher with protons after both TE/I (23% vs 12%) and DTI (50% vs 35%). Dose, fractionation and superficial constraints are not reported, so the planning lever is unknown. It bears on proton selection for implant pts.
Reconstruction type carried the strongest association: DTI vs TE/I HR 3.0 (1.7-5.5), P<.001, with the TE irradiated in all TE/I pts. For a pt expected to need PMRT, this bears on DTI vs 2-stage planning, especially when proton PMRT is anticipated.
12 details
Retrospective, IRB-approved cohort from 2 centers within a single institution, Jan 2017 to Dec 2023. Hypothesis stated a priori: proton cohort would have higher CC. Median follow-up 42 mo proton, 47 mo photon.
Subpectoral 2-stage TE/I or DTI reconstruction with PMRT; N=175 (89 proton, 86 photon). Median age 49 (range 24-78), 63% Hispanic. Groups balanced except laterality and reconstruction type (both P<.001).
Pencil beam scanning proton vs IMRT photon PMRT; the TE was irradiated in all TE/I pts. Dose, fractionation, bolus and superficial dose constraints are not reported in source.
Capsular contracture by Kaplan-Meier; associated factors by Cox proportional hazards, verified with binary logistic regression.
Reconstruction type was the only factor that stayed associated on multivariable analysis; the proton effect did not reach significance after adjustment (see tables).
| Comparison | Model | HR (95% CI) | P |
|---|---|---|---|
| Proton vs photon | Univariate | 2.3 (1.26-4.30) | .007 |
| Proton vs photon | Multivariable | 1.76 (0.93-3.32) | .083 |
| DTI vs TE/I | Multivariable | 3.0 (1.7-5.5) | <.001 |
| Reconstruction | Proton | Photon |
|---|---|---|
| DTI | 50% (n=36) | 35% (n=15) |
| TE/I | 23% (n=53) | 12% (n=71) |
The source frames proton vs photon CC data as scarce and reports this as the largest PBS PMRT reconstruction cohort to date. RADCOMP compares proton vs photon breast RT on cardiac outcomes, not reconstruction complications, so it will not settle this question.
Photon DTI stratum is only n=15, so the within-DTI modality contrast is underpowered. CC grading scale and RT planning parameters are absent from the abstract, which blocks translation to a specific planning change.
Adjusted proton HR 1.76 with an interval of 0.93-3.32 excludes neither no effect nor a large one; P=.083 is not reassurance. The consistent direction within both reconstruction types is the stronger signal, and PBS plus DTI is where the risk concentrates.
Retrospective cohort with reconstruction type imbalanced between modalities (P<.001); proton effect lost significance on multivariable analysis, so the modality signal stays confounded.
- Does proton CC excess persist after matching on reconstruction type?
- Which PBS superficial dose parameters drive capsular contracture?
- Does prepectoral or autologous reconstruction change proton vs photon risk?
📚 Sources · 📄 2 papers
Abstract
NRG/RTOG 9804 + E5194 combined analysis (tamoxifen after lumpectomy, DCIS)
ForGood-risk DCIS, lumpectomy without RT, low/int grade, ≤2.5 cm, margins ≥3 mm
TL;DR15-yr IBR 11.4% vs 19.0% with vs without tamoxifen in good-risk DCIS treated by lumpectomy without RT; invasive IBR HR 0.43.
The association was confined to invasive events (DCIS-IBR p=0.089), which made up 65 of 117 IBRs. For the RT-omission discussion, the 11.4% 15-yr IBR on tamoxifen has no RT arm in this analysis to benchmark against, and which good-risk subgroups drive it sits in Fig 3, with subgroup HRs not in source text.
In low/intermediate-grade DCIS ≤2.5 cm with margins ≥3 mm managed without RT after lumpectomy, this supports tamoxifen as an invasive-IBR risk-reduction option in the omission discussion; it does not extend to high-grade DCIS or pts receiving RT. The longer read
For RT omission in good-risk DCIS, tamoxifen alone still left 15-yr IBR at 11.4%, and this analysis has no RT arm to benchmark it against. The reduction tracked invasive IBR (HR 0.43), while DCIS-IBR did not separate (p=0.089).
In good-risk DCIS managed without RT, tamoxifen associated with lower invasive IBR (HR 0.43, 0.24-0.77) but not DCIS-IBR (p=0.089). Dose, duration and adherence are not reported, and contralateral breast event results, the other half of the endocrine rationale, are not in source text.
9 details 1 trial watching
Ancillary exploratory analysis combining the non-RT arm of NRG/RTOG 9804, which randomized good-risk DCIS to RT or no RT, with the good-risk E5194 cohort observed without RT. Tamoxifen was optional and not randomized in either trial. Univariate and multivariable Fine-Gray models; median follow-up 14.85 yr.
N=878 (317 RTOG 9804, 561 E5194); median age 59 (28-88). Good-risk: low- or intermediate-grade, ≤2.5 cm, excision margins ≥3 mm, lumpectomy without RT.
Tamoxifen, optional per trial; used by 43.1% overall (65.6% RTOG 9804 vs 30.3% E5194). Dose, duration and adherence not reported in source.
No RT in the analyzed population. The RTOG 9804 RT arm is not part of this analysis, so tamoxifen alone is not compared against RT here.
IBR (any), invasive IBR, DCIS-IBR, contralateral breast event and overall survival. CBE and OS results are not reported in the source text.
117 IBRs (65 invasive, 52 DCIS). The reduction tracked invasive IBR, not DCIS-IBR.
| Endpoint | Tamoxifen | No tamoxifen | Effect |
|---|---|---|---|
| Any IBR, 15-yr estimate | 11.4% (7.9-15.5) | 19.0% (15.3-22.9) | p=0.001 |
| Any IBR, multivariable | n/a | n/a | HR 0.54 (0.35-0.83), p=0.0045 |
| Invasive IBR | not reported | not reported | p=0.0048; MVA HR 0.43 (0.24-0.77), p=0.0042 |
| DCIS-IBR | not reported | not reported | p=0.089 |
| Characteristic | Tamoxifen | No tamoxifen | p |
|---|---|---|---|
| Enrolled on NRG/RTOG 9804 | 55.0% | 21.8% | <0.0001 |
| Non-white | 13.8% | 9.2% | 0.034 |
| Negative re-excision | 27.2% | 10.6% | <0.0001 |
| Pathologic size ≤5 mm | 57.0% | 41.3% | <0.0001 |
NSABP B-24 randomized tamoxifen after lumpectomy plus RT, and the UK/ANZ DCIS trial randomized tamoxifen and RT in a factorial design. Here tamoxifen is examined only in good-risk pts managed without RT, and without randomization.
Multivariable covariates are not listed in source, and trial membership also differs in follow-up (13.87 vs 16.15 yr). The DCIS-IBR result (p=0.089) rests on 52 events and does not exclude an effect.
Tamoxifen use tracked lower invasive recurrence in good-risk DCIS managed without RT, consistent in direction with randomized tamoxifen data. It does not settle whether tamoxifen alone approaches RT, or how much of the gap reflects the lower-risk profile of users.
Exploratory ancillary analysis; tamoxifen optional, not randomized, and imbalanced by trial, re-excision and size. Parent RCT tested RT, not tamoxifen, so residual confounding limits causal read.
- Does tamoxifen alone approximate RT for IBR control in good-risk DCIS? recruiting Omission of Adjuvant Radiotherapy in Low- and Intermediate-Risk Ductal Carcinoma In Situ After Breast-Conserving Surgery Phase 3n=636 · primary completion 2031-06 · ph3 NI RT omission in ER+ low/int-grade DCIS, tamoxifen
- Which good-risk DCIS subgroups gain enough to justify tamoxifen?
- Is the lack of DCIS-IBR reduction real or underpowered?
📚 Sources · 📄 1 paper
Abstract
High-dose hyperfractionated SIB RT vs standard-dose RT for limited-stage SCLC NCT03214003
ForLS-SCLC (VALSG), age 18–70, ECOG 0–1, PET-CT and brain MRI staged
HR 0.55
95% CI 0.37–0.72, p=0.003 · mOS 60.7 vs 39.5 mo
TL;DRmOS 60.7 vs 39.5 mo, HR 0.55 (0.37–0.72), p=0.003 with 54 Gy/30 fx BID SIB vs 45 Gy/30 fx BID in LS-SCLC; toxicity similar.
Escalation is a GTV/IGTV-only SIB (PTV held at 45 Gy) within the same 30 fx, 3-week BID course on PET-defined involved fields. Local PFS separated (HR 0.51) while MFS did not (HR 0.81), fitting an in-field effect. The decision it moves is BID dose, 45 vs 54 Gy, not BID vs once daily.
In PET-CT and brain-MRI staged LS-SCLC, age 18–70 and ECOG 0–1, planned for concurrent platinum-etoposide with BID thoracic RT, this supports 54 Gy SIB as an alternative to 45 Gy; it does not extend to pts over 70, ECOG 2, or once-daily schedules. The longer read
A GTV/IGTV-only boost to 54 Gy with PTV at 45 Gy keeps 30 fx BID over 3 weeks on involved PET-defined fields, with G3–4 acute oesophagitis 13% vs 12%. The actionable choice is BID dose, 45 vs 54 Gy, for fit PET-staged pts; once-daily escalation is not addressed.
8 details 1 trial watching
Open-label randomised phase 3, 1:1, 16 public hospitals in China, N=224 (108 vs 116) enrolled June 2017 to April 2021. Stratified by ECOG, stage, prior chemo courses and platinum choice. Stopped early by the DSMB at the interim after 88 deaths; median follow-up 46 mo.
Age 18–70, ECOG 0–1, LS-SCLC by VALSG staging, with mandatory whole-body PET-CT and brain MRI. Untreated or after 1–2 courses of platinum-etoposide. Median age 64; 86% stage III; 79% current or former smokers.
Cisplatin 75 mg/m² or carboplatin AUC 5 plus etoposide 100 mg/m² days 1–3, 4 courses every 3 weeks; almost 99% received all 4. PCI 25 Gy/10 fx for responders (82% vs 81%).
54 Gy/30 fx SIB to GTV/IGTV with PTV at 45 Gy vs 45 Gy/30 fx, both VMAT, BID at least 6 h apart, 5 days/wk for 3 weeks, starting 0–42 days after chemo cycle 1. Involved field: PET-positive primary and nodes, CTV = GTV + 5 mm, no elective nodal irradiation. Constraints included MLD ≤15 Gy, lung V20 <30%, cord max ≤40 Gy.
Primary: OS in ITT, measured from chemo start. Secondary: PFS, local PFS, MFS, DCR, acute and late toxicity (CTCAE v5.0), HRQOL (to be reported separately). Powered on HR 0.65 at 81% power, target 326 pts.
Primary endpoint crossed the interim boundary and held at the January 2023 cutoff, with 40 (37%) vs 66 (57%) deaths. Arm-level estimates are in the efficacy table.
| Endpoint | 54 Gy SIB | 45 Gy | HR (95% CI), p |
|---|---|---|---|
| Median OS (primary) | 60.7 mo (49.2–62.0) | 39.5 mo (27.5–51.4) | 0.55 (0.37–0.72), p=0.003 |
| 2-yr OS | 76% | 54% | p=0.001 |
| Median PFS | 30.5 mo (14.5–46.5) | 16.7 mo (10.7–22.7) | 0.70 (0.49–0.99), p=0.044 |
| Median local PFS | Not reached | 40.6 mo (22.8–58.4) | 0.51 (0.33–0.78), p=0.002 |
| Median MFS | 40.2 mo (26.6–53.8) | 23.8 mo (10.1–37.5) | 0.81 (0.57–1.16), p=0.248 |
| DCR | 97% | 93% | p=0.218 |
| Event | 54 Gy | 45 Gy | p |
|---|---|---|---|
| Oesophagitis | 14 (13%) | 14 (12%) | 0.84 |
| Pneumonitis | 5 (5%) | 7 (6%) | 0.663 |
| Neutropenia | 48 (44%) | 48 (41%) | 0.64 |
| Thrombocytopenia | 14 (13%) | 17 (14%) | 0.71 |
| Trial | Escalated schedule | Endpoint | Escalated arm | 45 Gy BID arm |
|---|---|---|---|---|
| This trial (phase 3) | 54 Gy/30 fx BID SIB | mOS · 2-yr OS | 60.7 mo · 76% | 39.5 mo · 54% |
| CONVERT (phase 3) | 66 Gy/33 fx QD | mOS · 2-yr OS | 25 mo · 51% | 30 mo · 56% |
| CALGB 30610/RTOG 0538 (phase 3) | 70 Gy QD | Median survival · 5-yr OS | 28.5 mo · 29% | 30.1 mo · 32% |
| Northern European randomised phase 2 | 60 Gy/40 fx BID | 2-yr OS | 74.2% | 48.1% |
Acute G3–4 RT toxicity similar between arms. No late G3 oesophagitis or stricture in either arm; late G3 pneumonitis in 2 vs 3 pts, no G3 pulmonary fibrosis. One treatment-related death (myocardial infarction) in the 54 Gy arm.
INT-0096 set 45 Gy/30 fx BID as the reference. CONVERT (66 Gy/33 fx QD) and CALGB 30610/RTOG 0538 (70 Gy QD) escalated dose without acceleration or hyperfractionation and did not beat it; the Northern European randomised phase 2 of 60 Gy/40 fx BID was the only prior BID escalation signal. The authors describe this as the first phase 3 to escalate while keeping BID delivery.
Control mOS of 39.5 mo beat the 24 mo design assumption and prior 45 Gy BID arms (20.8–30 mo), marking a selected cohort. Tumour and RT volumes were not controlled, and the interim analysis is listed as the only protocol amendment despite being described as preplanned. Reporting inconsistencies: median age given as both 64 and 62, and the OS CI upper bound (62.0) sits just above the 60.7 mo median.
The authors credit local control for the OS gain, but first-relapse rates were near identical (59 [55%] vs 65 [56%]) and chest-first failure did not differ significantly, so patterns of failure do not yet show where the benefit arises. Subgroup and HRQOL results are unreported.
CONSORT flow
Stopped at interim for benefit with 224 of 326 planned accrued; truncated RCTs tend to overstate effect. Single-country, open-label, no central RT QA, age ≤70.
- Does the 54 Gy SIB benefit hold in pts older than 70 or ECOG 2?
- 54 Gy/30 fx SIB BID vs 60 Gy/40 fx BID or high-dose once-daily? recruiting Dose-Escalation Radiotherapy in Limited-Stage Small Cell Lung Cancer: A Phase III Randomized Trial Phase 3n=300 · primary completion 2028-09 · phase 3: SIB 45-54 Gy vs 60 Gy vs 45 Gy BID, LS-SCLC
- Does higher thoracic dose add benefit alongside consolidation immunotherapy?
📚 Sources · 📄 1 paper
ePLND vs PSMA-PET staging (AUA2026 round-up)
TL;DRAUA2026 round-up: PSMA-PET NPV ~96% may allow PLND omission in intermediate risk; 47.7% of nodal mets sit outside ePLND template.
The RT-relevant number is toxicity sequencing: 19-29% lower limb lymphedema after PLND plus salvage pelvic nodal RT versus 0-9% after pelvic nodal RT alone, with 2-22% genital lymphedema in the combined group. If PSMA-PET is negative and PLND is omitted, later elective or salvage pelvic nodal coverage carries far less lymphedema cost.
In intermediate-risk pts with a PSMA-PET negative for nodal involvement, this supports omitting PLND before planned or possible pelvic nodal RT; it does not settle the high-risk case, where the round-up calls the decision individual. The longer read
Sequencing drives the toxicity: 19-29% lower limb lymphedema after PLND plus salvage pelvic nodal RT versus 0-9% after pelvic nodal RT alone, plus 2-22% genital lymphedema in the combined group. A pt who skips PLND arrives at elective or salvage nodal coverage with a much lower lymphedema burden.
The template itself is the weak point: 47.7% of nodal metastases in a 1253-man PSMA-PET series lay outside ePLND boundaries, and LND carried a 6-10x DVT/PE risk increase in Tyritzis. With a PSMA-PET negative for LNI in intermediate-risk disease, the yield no longer justifies routine dissection.

+3 more figures

| Treatment | Lower limb lymphedema | Genital lymphedema |
|---|---|---|
| RP with PLND | 0-14% | n/a |
| Pelvic node RT | 0-9% | n/a |
| PLND + salvage pelvic node RT | 19-29% | 2-22% |


10 details 5 trials watching
AUA 2026 podium round-up of the ePLND question in the PSMA-PET era. Draws on a 1253-man primary staging series (Yaxley, BJUI 2019), a systematic review of lymphedema (Clinckaert, Cancers 2022), a cohort of 3544 pts (Tyritzis, J Urol 2015) and a SWOT perspective (Roberts, PCAN 2024). No new dataset.
Staging yield argues against template adequacy: 47.7% of nodal metastases fell outside ePLND boundaries. PSMA-PET NPV is given as ~96% in the source text without its parent series named.
Lymphedema tracks the combination, not either modality alone: 0-14% after RP with PLND, 0-9% after pelvic nodal RT, 19-29% after PLND plus salvage pelvic nodal RT with 2-22% genital lymphedema. LND also carried a 6-10x DVT/PE risk increase in Tyritzis.
The argument is that a template operation cannot stage what sits outside the template, so its role narrows to pts in whom imaging is likely wrong. The slide's own conclusion keeps high-risk disease individualized rather than resolved, and explicitly asks that the possibility of adjuvant or salvage pelvic RT enter that conversation.
Slide-level source: NPV ~96% has no denominator, cohort or PSMA tracer attached here, and no BCR effect size is reported for the RCTs the round-up invokes. The lymphedema review's authors note the absent uniform definition, so 19-29% is a range across heterogeneous ascertainment, not a pooled estimate.
- Does ePLND improve BCR-free survival in any risk group? recruiting Dutch National Randomized Study: PSMA-PET/CT As a Triage Tool for Pelvic Lymph Node Dissection in Prostatectomy Patients Phase NAn=706 · primary completion 2025-07 · PSMA-PET triage to ePLND, n=706, prognosis endpointrecruiting Extended vs. No Pelvic Lymph Node Dissection During Radical Prostatectomy. DISSECTION 2.0. Phase NAn=400 · primary completion 2027-02 · randomises ePLND vs none in PSMA-negative high riskn=270 · primary completion 2028-02 · RP+ePLND vs RP±SRT, Briganti >=7%
- PSMA-PET NPV by risk group and tracer recruiting Preoperative PSMA PET/CT As Triage for EPLND in Patients Scheduled for RALP (PrePSMA) Phase NAn=600 · primary completion 2029-12 · tests whether PSMA-PET can replace ePLND staging
- Nodal RT after PSMA-PET staging without prior PLND n=250 · primary completion 2031-05 · PSMA-N0M0 randomised to prostate-only vs WPRT
📚 Sources · 🐦 1 tweet
At #AUA2026, the message was clear:⁰📌 ePLND provides staging information, but its therapeutic benefit remains uncertain.⁰📌 RCTs have not shown consistent improvements in BCR outcomes.⁰📌 PSMA PET/CT has a high NPV (~96%) and may safely avoid unnecessary PLND in… pic.twitter.com/7vJFe2hG77
— DR CARVAJAL (@RomanCarvajal) May 17, 2026
Bladder-preserving TMT multicenter analysis (URONCOR)
ForcT2-T4aN0M0 MIBC treated with definitive TMT, median age 76
TL;DRCLR 63.7% in a 369-pt Spanish TMT cohort; salvage cystectomy 9.7%, image-guidance quality and 5-FU-based CRT predicted local response.
The modifiable RT variable here is verification protocol: weekly portal imaging carried OR 0.35 (0.20-0.60) for complete local response, with VMAT trending favorable, across a 2010 to 2022 accrual. Dose, fractionation and target volume are not reported in source, so what transfers is the case for daily volumetric IGRT in a filling, moving organ.
In cT2-T4aN0M0 MIBC pts in their seventies weighing bladder preservation against cystectomy, this real-world series supports TMT delivered with modern image guidance and a 5-FU-based backbone; it does not inform node-positive or metastatic disease and carries no head-to-head against radical cystectomy. The longer read
Verification protocol is the modifiable variable: weekly portal imaging carried OR 0.35 (0.20-0.60) for complete local response, with VMAT trending favorable. Dose, fractionation and target volume are not reported in source, so what transfers is the case for daily volumetric IGRT and adaptive planning rather than a specific prescription.
The concurrent backbone mattered: 5-FU-based CRT carried OR 4.9 (1.1-22.1) for complete local response, though the CI leaves the magnitude open and comparator regimens are unnamed in source. Systemic failure at 10.7% ran at or above local-only failure at 10.1%, keeping perioperative systemic therapy questions live.
Salvage cystectomy was performed in 9.7% against 28.8% who progressed, so in a median-age-76 cohort most failures were not surgically rescued. With no in-cohort cystectomy comparator, this informs counseling on bladder preservation for cT2-T4aN0M0 disease without establishing equivalence to upfront radical cystectomy.

10 details
Multicenter retrospective cohort, Spain, 2010 to 2022, N=369 treated with definitive trimodality therapy (maximal TURBT then concurrent chemoradiotherapy). Predictors of response identified by multivariable logistic regression. Follow-up duration not reported in source.
cT2-T4aN0M0 MIBC selected for bladder preservation. Median age 76, 85.1% male. Fitness for cystectomy and completeness of TURBT are not reported in source.
Concurrent chemoradiotherapy, regimen at each center's discretion. 5-FU-based CRT predicted higher complete local response (OR 4.9, 95% CI 1.1-22.1, p=0.038). The comparator regimens are not named in source.
Dose, fractionation and target volume are not reported in source. The only technique signals reported are verification frequency (weekly portal imaging, OR 0.35 for CLR) and a non-significant trend favoring VMAT.
complete local response (CLR). Secondary: OS, CSS, recurrence patterns, salvage cystectomy. No OS or CSS estimate appears in the source, so the survival half of the conclusion cannot be checked.
CLR 63.7%, salvage cystectomy 9.7%. Progression 28.8%, with systemic failure (10.7%) running at or above local-only failure (10.1%).
BC2001 established the locoregional-control gain from adding chemotherapy to bladder radiotherapy, and the pooled RTOG bladder-preservation experience set the complete-response benchmark; both were protocol populations. This adds European real-world multicenter data at a median age of 76, with no internal cystectomy comparator.
No follow-up duration, OS or CSS estimate is reported, so the durability behind the preservation claim cannot be judged. The 5-FU odds ratio spans 1.1 to 22.1, compatible with a marginal or a large effect, and in a retrospective series regimen choice tracks renal function and performance status.
Systemic failure at 10.7% running at or above local-only failure at 10.1% argues the ceiling in this population is micrometastatic disease rather than the bladder, which caps what further local intensification can buy. Read conservatively, the predictors favor modern image guidance and an active concurrent backbone, not any specific verification schedule.
Retrospective multicenter cohort with no cystectomy comparator; imaging and chemo predictors come from multivariable regression across a 2010-2022 era shift, so a causal reading is unsupported.
- Does daily volumetric IGRT improve complete local response vs weekly portal imaging?
- Which concurrent chemotherapy backbone maximizes complete local response in TMT?
- Long-term bladder-intact survival vs radical cystectomy in matched populations
📚 Sources · 🐦 1 tweet
📢 Presentamos en #ESTRO26 nuestro análisis multicéntrico sobre preservación vesical en cáncer vesical músculo-invasivo tratado con TMT.
— URONCOR (@URONCOR) May 19, 2026
🔎 En 369 pacientes, la respuesta completa clínica se asoció a menor recurrencia local y mejor supervivencia!@fcounago #NicoFeltes pic.twitter.com/aQjjkcHGP4
Single-fraction SABR pooled analysis, 1687 pts
ForPrimary NSCLC or pulmonary oligomets selected for single-fraction SABR
TL;DRLocal control 90-93% at 2yr and G3+ AEs 2.9% across 1687 single-fraction SABR pts at 3 centres.
The oligomet read is the gap between local control and PFS: 90-93% LC at 2yr against median PFS 11 mo, so distant failure, not the treated lesion, drives the course. For primary NSCLC the same LC sits with median PFS 30 mo, which is the split that should decide whether one-visit ablation is offered as definitive treatment or as a break from systemic therapy.
In early-stage primary NSCLC where visit burden drives the fractionation choice, this supports single fraction as a durable local option (LC 90-93% at 2yr, G3+ 2.9%); tumour location and operability are not reported, so who it represents stays open. The longer read
Local control holds at 90-93% at 2yr for a primary and for a metastasis alike, so the single fraction is not the variable separating outcomes; median PFS is (30 vs 11 mo). Tumour size and location go unreported, so the target selection behind that number is unmeasured.
For a pt with pulmonary oligometastases, one-visit ablation gave 90-93% local control at 2yr but median PFS of 11 mo, so it clears the treated lesion without changing the systemic course. That frames referral as a local step between systemic lines, not a substitute for one.
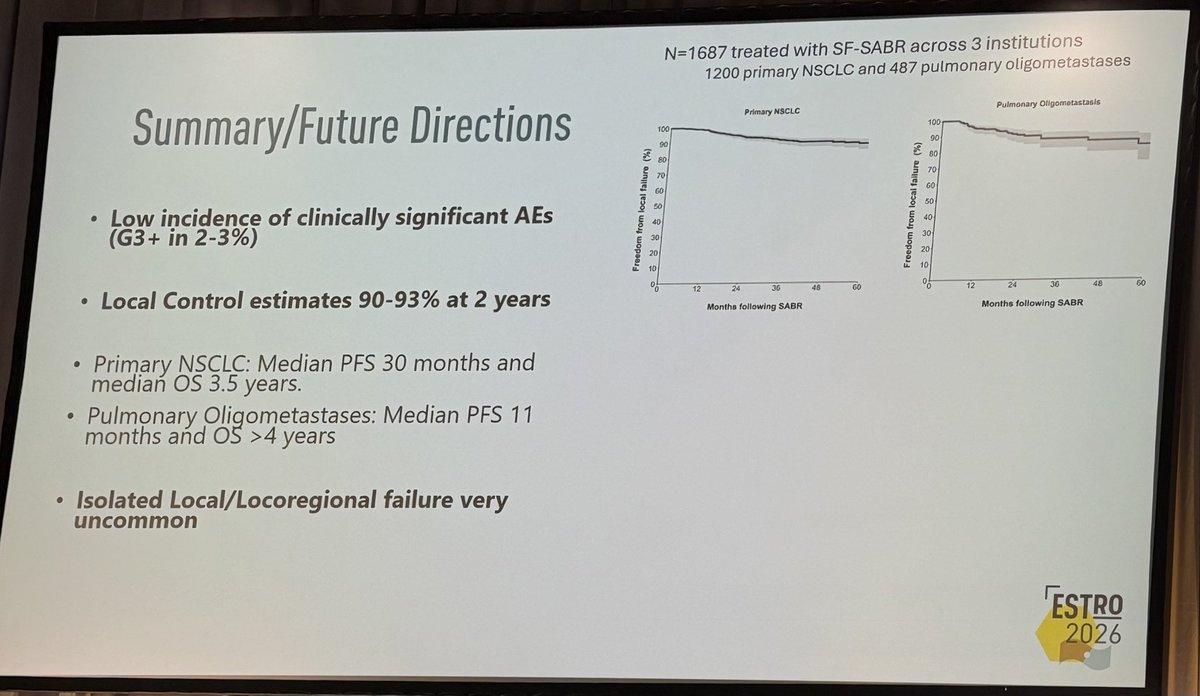
| Cohort | n | Median PFS | Median OS |
|---|---|---|---|
| Primary NSCLC | 1200 | 30 mo | 3.5 yrs |
| Pulmonary oligometastases | 487 | 11 mo | >4 yrs |
+2 more figures
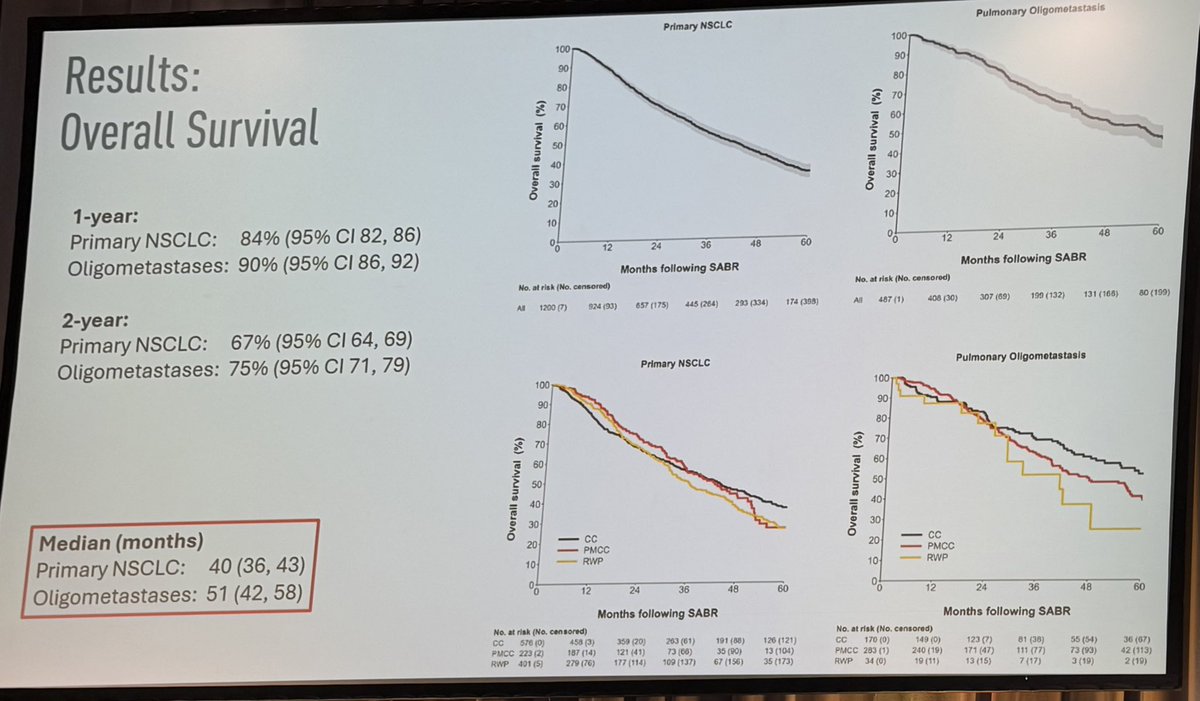
| Endpoint | Primary NSCLC | Oligometastases |
|---|---|---|
| 1yr OS | 84% (95% CI 82, 86) | 90% (95% CI 86, 92) |
| 2yr OS | 67% (95% CI 64, 69) | 75% (95% CI 71, 79) |
| Median OS | 40 mo (36, 43) | 51 mo (42, 58) |
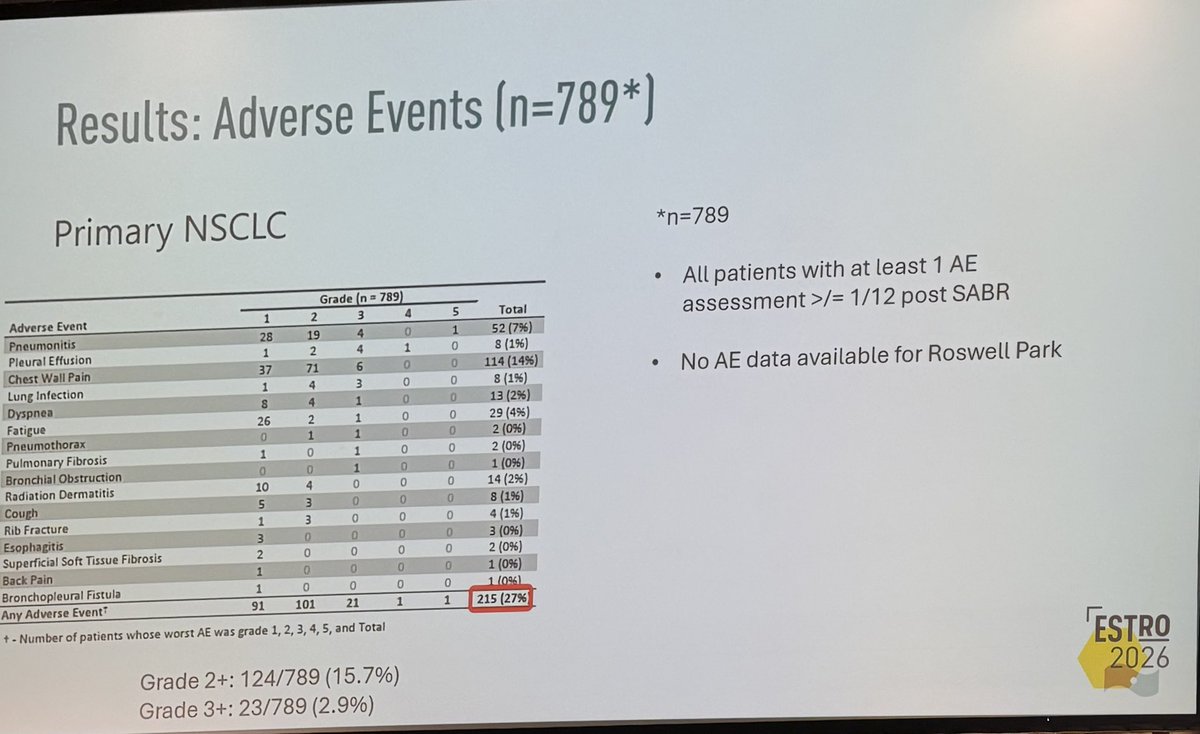
| Adverse event (n=789) | n (%) |
|---|---|
| Any AE | 215 (27%) |
| Grade 2+ | 124 (15.7%) |
| Grade 3+ | 23 (2.9%) |
| Chest wall pain | 114 (14%) |
| Pneumonitis | 52 (7%) |
| Fatigue | 29 (4%) |
| Dyspnea | 13 (2%) |
6 details
Pooled analysis of 1687 pts treated with single-fraction SABR at three centres (Peter MacCallum, Cleveland Clinic, Roswell Park): 1200 primary NSCLC and 487 pulmonary oligometastases. Whether the contributing cohorts were prospective or retrospective is not stated in source.
Eligibility, operability, tumour size and central vs peripheral location are not reported in source. Cohort mix differs sharply by centre: Roswell Park supplied 401 of the NSCLC pts but only 34 oligomet pts, while Peter Mac supplied 283 of 487 oligomet pts.
Single fraction throughout, but the prescribed dose is not reported in source. Without it the outcome cannot be mapped onto a schedule a reader could write, which is the one parameter that would carry this into planning.
No primary endpoint is stated in the source. Reported outcomes are local control, freedom from local failure, PFS, OS and adverse events, each descriptive rather than tested against a comparator.
Local control 90-93% at 2 years across both cohorts, with isolated local or locoregional failure described as very uncommon. Survival separates by cohort while local outcome does not.
| Centre | Primary NSCLC | Pulmonary oligomets |
|---|---|---|
| Cleveland Clinic | 576 | 170 |
| Peter MacCallum | 223 | 283 |
| Roswell Park | 401 | 34 |
AE reporting covers 789 primary NSCLC pts only, with no Roswell Park data and no oligometastasis toxicity in source. Within that subset chest wall pain and pneumonitis dominate and G3+ events stay at 2.9%.
Single-fraction SABR already carries randomised support: RTOG 0915 in peripheral early-stage NSCLC and SAFRON II in pulmonary oligometastases, both randomised single against multi-fraction schedules. This series adds scale and follow-up at three high-volume centres, which is what a non-randomised dataset can contribute, and no comparator.
Toxicity rests on 789 of 1687 pts, with one centre absent from the AE table and the oligometastatic cohort not represented in it at all. Centre mix is uneven, so pooled rates carry each centre's own selection rather than a common one.
The question the thread raises, whether one-stop SABR should be used more often, is not the question this dataset answers. What it does show is that local control near 90-93% and G3+ toxicity near 3% hold at scale outside a protocol, which is the usual worry about a schedule with no second chance. The unreported dose sits between that reassurance and a prescription.
Pooled uncontrolled series across three centres, no multi-fraction comparator and no stated design; dose unreported, so outcomes cannot be tied to a prescription.
- Whether single-fraction outcomes hold for central tumours
- Durability of single-fraction ablation for pulmonary oligometastases beyond first progression
- Toxicity of single-fraction SABR in the oligometastatic cohort
📚 Sources · 🐦 1 tweet
👏🏽👏🏽👏🏽@neildwallaceie at #ESTRO26 - 1687 patients receiving single fraction SABR for #lungcancer and pulmonary oligomets, @PeterMacRadOnc / @ClevelandClinic / @RoswellPark. Fantastic local control, and low adverse rates. Should we be using “one stop” SABR more often #radonc ? pic.twitter.com/w2IlGKRU5o
— Shankar Siva (@_ShankarSiva) May 18, 2026
OPERA
ForRectal cancer on watch-and-wait pathway after neoadjuvant therapy
TL;DRW14 clinical response (DRE+rectoscopy) identified 76% good responders; 5yr organ preservation 75% A vs 83% B, p=0.24.
The transferable read is timing: response can be called at W14, one month after NAT ends, on DRE plus rectoscopy, with MRI TRG1-2 concordance of 98% (80/82). nCR at W14 preserved organs as well as cCR (77% vs 81%), so a near-complete response reflecting radiation effect does not by itself send a patient to TME.
In rectal pts on a watch-and-wait pathway, this supports assessing response at W14 rather than deferring to W24 and reassessing nCR rather than treating it as failure; it does not address pts never eligible for organ preservation. The longer read
Response can be called at W14, one month after NAT ends, on DRE plus rectoscopy, with MRI TRG1-2 concordance of 98% (80/82). nCR at that point preserved organs as well as cCR (77% vs 81%), so a near-complete response reflecting radiation effect does not itself justify TME.
The surgical decision this moves is when to abandon watch-and-wait. A W14 nCR reached 5yr organ preservation of 77% versus 81% for cCR, so early near-complete response is not evidence for proceeding to TME. Regrowth and salvage counts are not reported in source.
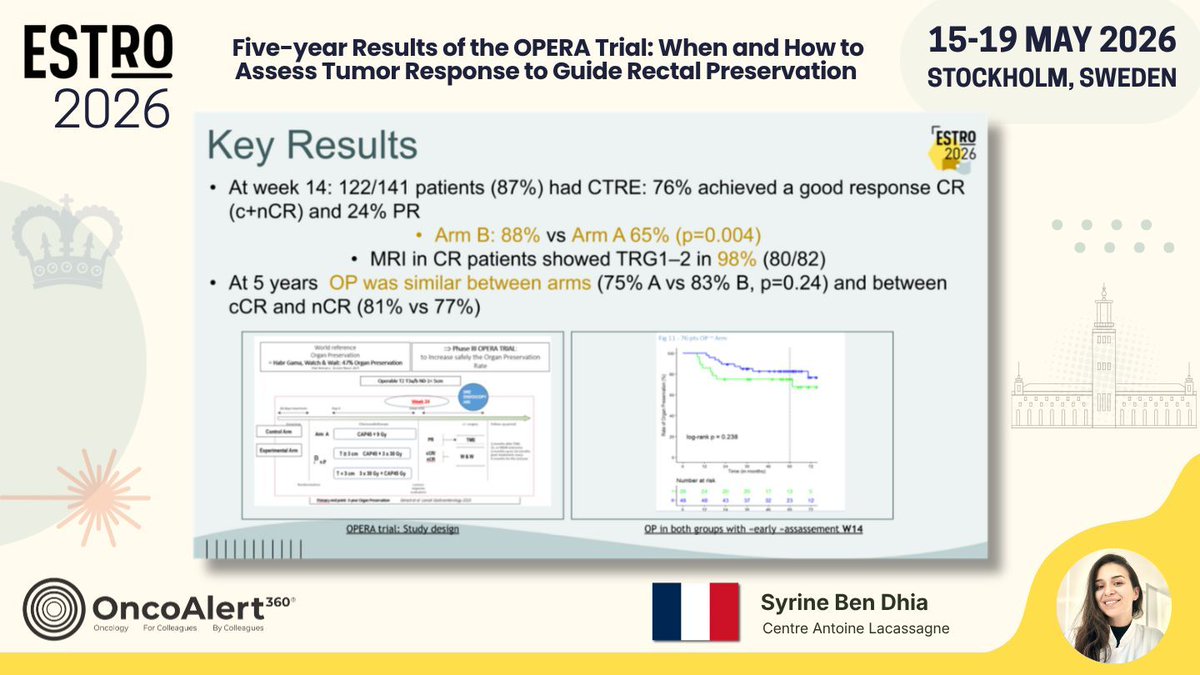
| Endpoint | Arm A | Arm B | Overall |
|---|---|---|---|
| W14 good response (cCR+nCR) | 65% | 88% | 76% |
| W14 partial response | n/a | n/a | 24% |
| 5yr organ preservation | 75% | 83% | p=0.24 |
| CTRE performed at W14 | n/a | n/a | 122/141 (87%) |
+2 more figures


10 details
Post-hoc analysis of the randomised OPERA trial (two arms, A and B), reporting 5-year organ-preservation outcomes. The parent trial assessed response at week 24 with a three-modality triad (DRE, rectoscopy, MRI); this analysis asks whether the week 14 read is good enough.
Week-14 clinical tumor response evaluation (CTRE) by DRE and rectoscopy, categorised CR / nCR / PR, with cCR + nCR counted as a "good" clinical response. MRI graded by TRG. CTRE was correlated with relapse and 5-year organ-preservation rates.
Both arms received neoadjuvant therapy with organ preservation as the goal, and good responders at W14 either proceeded to organ preservation or were reassessed at W24. Dose, fractionation, and the content distinguishing Arm A from Arm B are not reported in source, which limits how far the arm difference transfers.
CTRE was obtainable in 122/141 (87%) at W14. MRI confirmed TRG1-2 in 98% (80/82) of clinical CR pts, and 5-year organ preservation did not differ by arm (p=0.24) or by response depth (cCR 81% vs nCR 77%).
Watch-and-wait practice has largely settled on later response assessment, with the OPRA framing of consolidation timing and the registry experience both anchoring the decision point well beyond three months. This analysis argues the clinical exam carries most of that information a month after NAT ends, which is earlier than the field currently commits.
The 19 pts without CTRE at W14 (141 minus 122) are unaccounted for in source, and selective assessability would bias the 76% good-response figure upward. The arm difference (88% vs 65%, p=0.004) is uninterpretable here because the randomised contrast is not described.
The clinically useful claim is that nCR is a radiation effect, not residual tumor, and the 5-year organ-preservation parity between cCR and nCR (81% vs 77%) is the evidence for it. What the source does not settle is regrowth: organ preservation at 5 years is a net figure that can absorb salvage, so equal preservation does not establish equal local control.
Post-hoc timepoint analysis of 141 pts; W14 vs W24 assessment was never randomised, and no relapse or regrowth data reported in source.
- Regrowth and salvage rates behind the 5yr organ preservation figures
- What distinguished Arm A from Arm B
- Outcomes of the 19 pts without W14 CTRE
📚 Sources · 🐦 1 tweet
Day FOUR of #ESTRO26 Coverage by OncoAlert 🚨
— OncoAlert (@OncoAlert) May 18, 2026
Five-year Results of the OPERA Trial: When and How to Assess Tumor Response to Guide Rectal Preservation Presented by Syrine Ben Dhia 🇫🇷 #RadOnc ☢️
This post-hoc analysis of the OPERA trial evaluated early tumor response… pic.twitter.com/KUanFTxeFh
HEAT NCT01794403
ForLocalized low- to intermediate-risk prostate, IPSS <12, gland <80 cc
7% vs 7.4%
p-non-inferiority = 0.007 at 4.25y, margin 12%
TL;DRInterim: BF 7% vs 7.4% at 4.25y, p-non-inferiority 0.007, 5-fx SBRT non-inferior to 26-fx IMRT with ADT allowed.
The design detail that transfers is the SIB: 36.25 Gy/5 fx with GTV boost to 40 Gy, against a 70.2 Gy/26 fx IMRT comparator rather than conventional fractionation, with ≤6 months ADT permitted in both arms. That combination is closer to what most departments now offer than HYPO-RT-PC or PACE-B, so it addresses whether 5 fractions holds up when the control arm is already moderately hypofractionated.
In localized low- to intermediate-risk disease with IPSS <12 and gland under 80 cc, including men receiving short-course ADT, this supports 5-fraction SBRT as an option against moderate hypofractionation; it does not speak to high-risk disease or nodal coverage. The longer read
The transferable parameters are 36.25 Gy/5 fx with GTV SIB to 40 Gy against a 70.2 Gy/26 fx IMRT comparator, with ≤6 months ADT permitted in both arms. Acute G2+ GI favored 5 fractions and late G2+ GI and GU were comparable at median 59.7 months, so this moves the fractionation choice in low- to intermediate-risk disease.
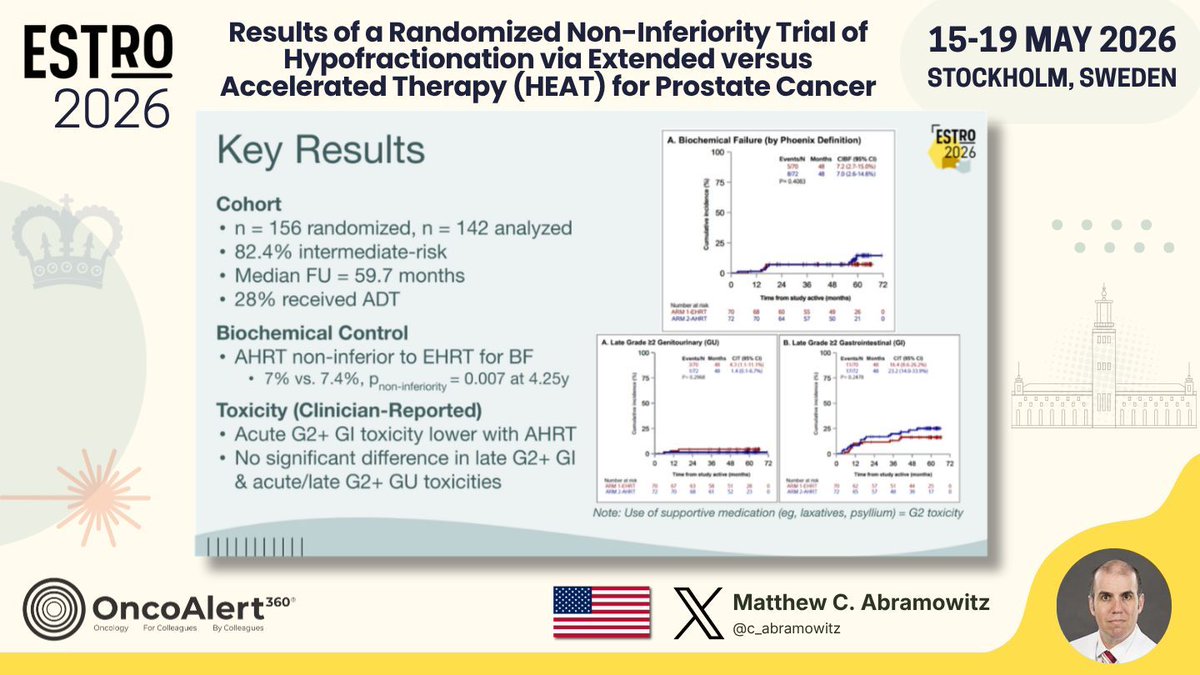
+2 more figures
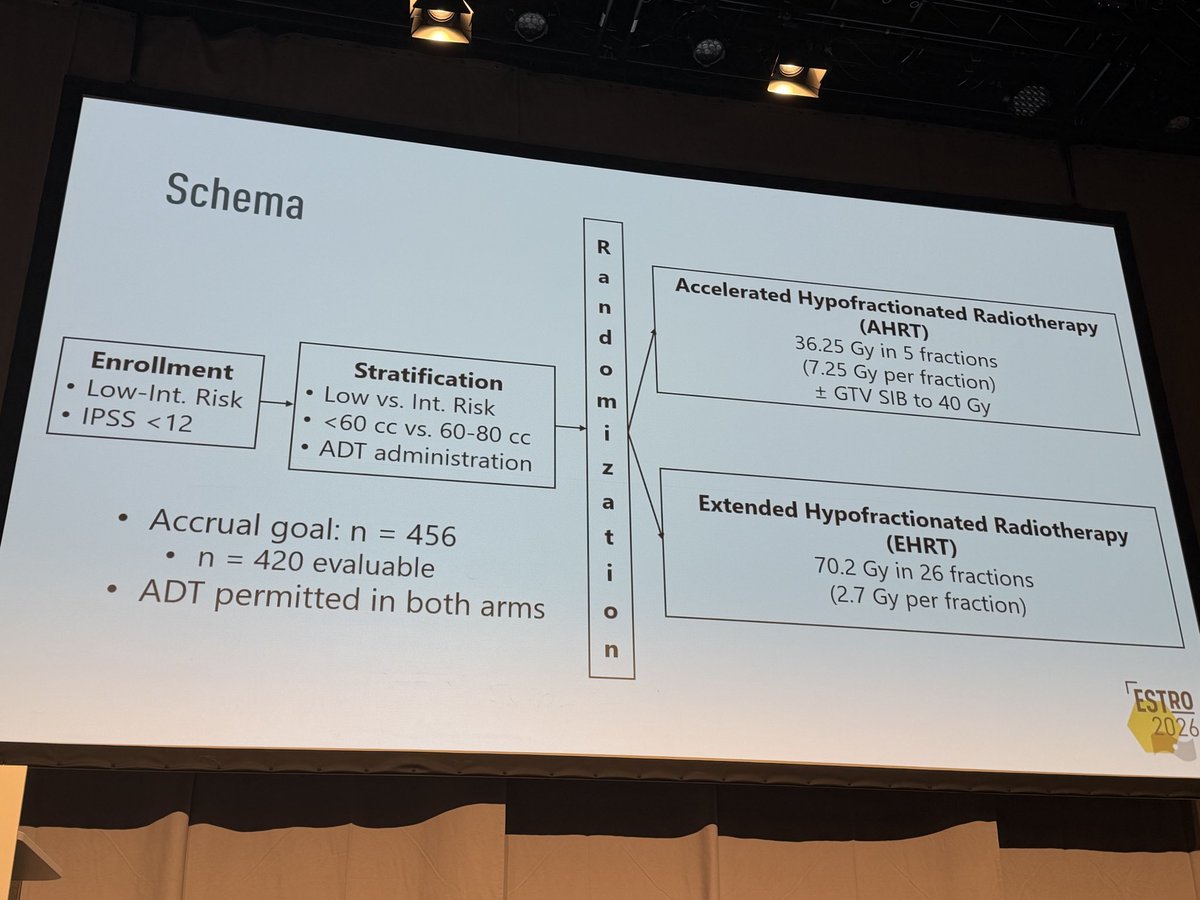
| Arm | Dose | Fractions | Dose per fraction |
|---|---|---|---|
| AHRT | 36.25 Gy (+ GTV SIB to 40 Gy) | 5 | 7.25 Gy |
| EHRT | 70.2 Gy | 26 | 2.7 Gy |
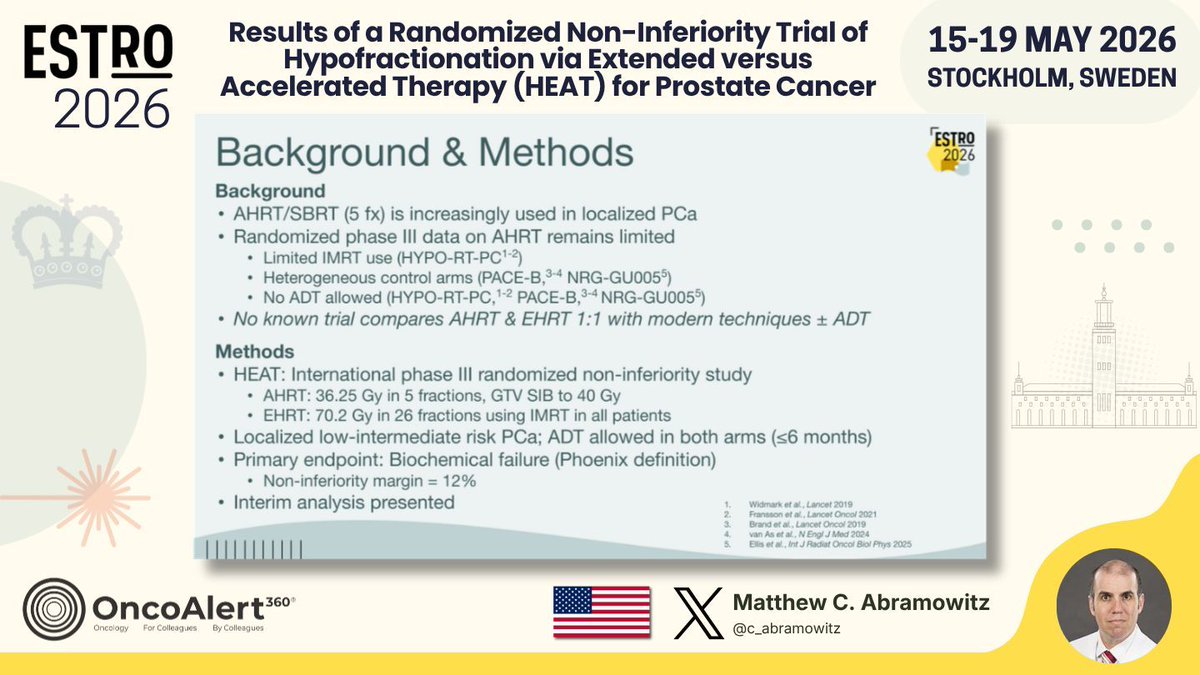
9 details 5 trials watching
International phase III randomized non-inferiority trial, 1:1, comparing accelerated (AHRT) vs extended (EHRT) hypofractionation. Interim analysis presented; accrual goal n = 456 with 420 evaluable, and 142 analyzed so far. Median follow-up 59.7 months.
Localized low- to intermediate-risk prostate cancer with IPSS <12. Stratified by risk group, prostate volume (<60 cc vs 60-80 cc) and ADT administration. 82.4% intermediate-risk; 28% received ADT.
AHRT: 36.25 Gy in 5 fractions (7.25 Gy per fraction) with GTV SIB to 40 Gy. EHRT: 70.2 Gy in 26 fractions (2.7 Gy per fraction), IMRT in all patients. ADT permitted in both arms, ≤6 months.
Primary: biochemical failure, Phoenix definition, with a non-inferiority margin of 12%. Clinician-reported acute and late GI and GU toxicity reported alongside.
BF 7% vs 7.4%, p-non-inferiority = 0.007 at 4.25y, meeting the non-inferiority criterion.
Acute G2+ GI toxicity lower with AHRT. No significant difference in late G2+ GI or in acute or late G2+ GU. Note that use of supportive medication (laxatives, psyllium) was scored as G2.
The presenters position HEAT against HYPO-RT-PC (limited IMRT use), PACE-B and NRG-GU005 (heterogeneous control arms), all of which allowed no ADT. HEAT is framed as the first trial comparing AHRT and EHRT 1:1 with modern technique plus ADT.
Event counts are low (7% vs 7.4%) against a 12% margin, so the interval around the difference is wide relative to the difference being excluded. The comparator is itself hypofractionated, so this does not test 5 fractions against conventional fractionation.
The question HEAT answers is narrower than 'does SBRT work': it asks whether 5 fractions holds when the control arm is already 26 fractions of IMRT and short ADT is on the table. A positive interim read supports 5 fractions as a default offer in this risk band, but the final prespecified analysis is what settles it.
Interim analysis at 142 of a planned 420 evaluable; prespecified final primary analysis is the gate. Wide 12% margin relative to observed event rates.
- Does non-inferiority hold at the final prespecified analysis
- Effect of concurrent ADT on the fractionation comparison n=60 · primary completion 2028-02 · randomises SBRT +/- relugolix in cFIR/cgUIRn=130 · primary completion 2028-11 · adds ultra-short ADT to single-fraction SBRT
- Late GU outcomes beyond 5 years with 7.25 Gy fractions n=100 · primary completion 2027-10 · 36.25 Gy/5 fx, 1-2mm PTV, late urethra toxicityn=175 · primary completion 2028-12 · 3 fx vs 5 fx benchmark, late GU grade 2+ 1° EPrecruiting Erectile Dysfunction in Good Prognosis Prostate Cancer : Comparison Between Brachytherapy and Stereotactic Body Radiotherapy Phase NAn=240 · primary completion 2030-04 · 7.25 Gy x5 vs I-125 brachy, f/u to 2030
📚 Sources · 🐦 2 tweets
Day FOUR of #ESTRO26 Coverage by OncoAlert 🚨
— OncoAlert (@OncoAlert) May 18, 2026
Results of a Randomized Non-Inferiority Trial of Hypofractionation via Extended versus Accelerated Therapy (HEAT) for Prostate Cancer Presented by Matthew C. Abramowitz🇺🇸 #RadOnc ☢️ #ProstateCancer
HEAT is an international phase… pic.twitter.com/IkSTgQHwXK
The HEAT trial is another randomized demonstration of the safety & efficacy of SBRT compared to hypofractionted RT in #prostatecancer at #ESTRO26 pic.twitter.com/c9sNb3KOqo
— Pierre Blanchard, MD (@PBlanchardMD) May 18, 2026
INRT-AIR & DARTBOARD pooled analysis
ForHNSCC oropharynx/larynx/hypopharynx, stage I-IVB, excluding T1-2N0 larynx
TL;DR5yr solitary elective nodal recurrence 0% with ENI omission in HNSCC; 5yr OS 87%, PFS 74%, n=117.
The number that matters is 0% solitary elective nodal recurrence at 5 yrs: elective volumes are where the parotid, constrictor and pharyngeal dose lives, and this is the first pooled long-term read that omitting them does not trade nodal control. MDADI 84.9 at 12 mo with no significant decline is the swallowing correlate. No dose or CTV detail in source, so the contouring approach cannot be replicated from this abstract.
In stage I-IVB oropharynx, larynx or hypopharynx SCC being planned for definitive chemoRT, this supports enrolling on an INRT protocol rather than adopting nodal omission off-trial; it does not extend to T1-2N0 larynx, which was excluded. The longer read
This is the elective-volume decision, the one de-escalation lever definitive chemoRT has never randomised. 0% solitary elective nodal recurrence at 5 yrs with MDADI 84.9 at 12 mo says the trade is not nodal control, but the nodal selection ran through an AI model on staging PET/CT, so the transferable piece may be the selection step, not the omission.

+1 more figure

11 details 2 trials watching
Patient-level pooled analysis of 2 prospective trials, INRT-AIR and DARTBOARD, both testing involved nodal radiotherapy. N=117, median follow-up 3.4 years. No randomised comparator arm receiving standard elective nodal irradiation.
HNSCC of oropharynx, larynx, and hypopharynx, stage I-IVB, explicitly excluding T1-2N0 larynx. Completed PET/CT and neck CT were required for eligibility, which is also the imaging substrate the nodal-selection step depends on.
Definitive chemoradiotherapy with omission of elective nodal irradiation (ENI), treating involved nodes only (INRT). Suspicious node identification was assisted by an artificial-intelligence model reading the staging PET/CT and neck CT. Dose, fractionation and margin expansions are not reported in the source.
5-yr solitary elective nodal recurrence 0%. 3-yr cumulative incidence: local 9.5%, regional 4.3%, distant 11%. 5-yr OS 87%, PFS 74%. Mean composite MDADI 84.9 at 12 months with no significant decline after treatment.
Pooling two protocols with different designs into one patient-level cohort assumes their INRT definitions were interchangeable, which the source does not establish. Median follow-up of 3.4 years supports a 5-year estimate on a shrinking risk set, and HPV status, which drives OS in an oropharynx-weighted cohort, is not reported.
The zero solitary elective nodal failures make the mechanistic case that undissected, PET-negative elective levels rarely harbour disease that only ENI would sterilise. What the pooled cohort cannot settle is whether the result survives outside two experienced centres using an AI-assisted nodal-selection step, which is precisely the component a general department would have to reproduce.
Pooled single-arm prospective cohorts, n=117, no randomised comparator against standard elective nodal RT. Presenters state randomised evidence needed before non-trial use.
- Randomised INRT vs elective nodal irradiation in definitive chemoRT recruiting Dose De-escalation and Sentinel LN Mapping Driven Radiotherapy of Contralateral Neck in Ipsilateral Node Positive HNSCC Phase NAn=147 · primary completion 2027-01 · sentinel node mapping tailors contralateral neck volumerecruiting Invert-Prospective Phase II Randomized Trial of Involved Nodal Versus Elective Neck RadioTherapy Phase 2n=80 · primary completion 2028-07 · randomised INRT vs ENI, solitary elective recurrence
- Does AI-assisted nodal selection outperform physician contouring
- Whether INRT toxicity benefit is measurable against standard elective volumes
📚 Sources · 🐦 1 tweet
Day FOUR of #ESTRO26 Coverage by OncoAlert 🚨
— OncoAlert (@OncoAlert) May 18, 2026
Omission of elective nodal irradiation in HNSCC: long-term results and patient-level pooled analysis from 2 prospective trials (INRT-AIR & DARTBOARD)
Presenter Sympascho Young 🇺🇸
A patient-level pooled analysis of 117 patients… pic.twitter.com/KaaT70nSNH
NRG/RTOG 1005 NCT01349322
ForHigh-risk early breast cancer post-lumpectomy + axillary surgery, boost indicated
HR 1.31
90% CI 0.84-2.04, P=.037 (noninferiority met)
TL;DR7yr IBR 2.6% concurrent vs 2.2% sequential, HR 1.31 (90% CI 0.84-2.04), noninferior, one shorter course.
The concurrent arm is 15 fractions total, 40 Gy/15F whole breast with an 8 Gy SIB at 0.53 Gy/day, versus 21-32 fractions sequentially. Cosmesis was noninferior on patient BCTOS, physician rating, and blinded photo review, so the usual objection to a simultaneous integrated boost in a high-risk, 16.7% close-margin population does not hold at 3 years.
In a post-lumpectomy patient with grade 3, ER-negative, close-margin, or node-positive disease where you would add a boost, this supports a 15-fraction SIB course instead of sequential; it does not address partial-breast, regional nodal irradiation, or ultrahypofractionated 5-fraction boost. The longer read
The concurrent arm is 15 fractions total, 40 Gy/15F whole breast with an 8 Gy SIB at 0.53 Gy/day, against 21-32 fractions sequentially. Cosmesis was noninferior on patient BCTOS, physician rating, and blinded photo review, so the usual SIB objection does not hold at 3 years in a cohort with 16.7% close margins.
10 details 5 trials watching
Randomized, unblinded phase 3 noninferiority trial run by NRG Oncology, 278 sites across North America and 6 other countries, accrual May 2011 to June 2014. 2,354 randomly assigned, 2,255 eligible (sequential 1,118, concurrent 1,137). Median follow-up 7.3 years.
Post-lumpectomy and axillary surgery, selected for higher risk of ipsilateral breast recurrence. Median age 55 (IQR 47-64), 35.6% under 50; 96.8% invasive, 52.7% grade 3, 29.6% ER-negative, 16.7% LVI, 16.7% close (<2 mm) or focally positive margins, 16.3% node-positive, 61.8% received chemotherapy.
Sequential arm: WBI 50 Gy/25F or 42.7 Gy/16F, then boost 12 Gy/6F (84.9%) or 14 Gy/7F. Concurrent arm: WBI 40 Gy/15F with an 8 Gy/15F integrated boost at 0.53 Gy per day. 3DCRT in 1,290 (59%), photons in 1,614 (73.8%). QART scored contours and plans per protocol or acceptable variation in 92.8% and 91.9%.
Primary: IBR as first recurrence, noninferiority margin an HR upper 90% CI limit of 2.12, powered at 80% off an assumed 1.59% 5-year sequential-arm IBR. Secondary: DFS, OS, adverse events, and cosmesis (patient BCTOS, physician global cosmetic score, blinded central digital photo review).
56 IBR events, 24 sequential and 32 concurrent. Cause-specific hazards and Fine-Gray gave the same HR 1.31, and noninferiority held against each sequential WBI fractionation separately. The protocol-specified superiority test was not significant, and post-hoc analyses by stratification variable showed no treatment interactions.
| Arm | WBI | Boost |
|---|---|---|
| Sequential | 50 Gy/25F (575, 52.4%) or 42.7 Gy/16F (523, 47.6%) | 12 Gy/6F (932, 84.9%) or 14 Gy/7F, after WBI |
| Concurrent | 40 Gy/15F | 8 Gy/15F at 0.53 Gy/day, during WBI |
Grade >2 treatment-related toxicity was uncommon with no difference in grade 3-4 events (p=0.81); radiation dermatitis, fatigue, and breast pain were the most prevalent events. Physician-rated excellent/good cosmesis at 3 years was 85.9% sequential vs 82.4% concurrent (p=0.34), photo review 64.2% vs 72.0% (p=0.11).
The boost itself was established by EORTC 22881-10882, where 16 Gy sequential cut IBR but added treatment time and worsened fibrosis. IMPORT HIGH tested integrated boosts on a 40 Gy/15F backbone and found 48 Gy acceptable while its 53 Gy arm carried more induration. NRG 1005 answers the delivery question at scale rather than the dose question.
Cosmetic assessment thinned badly over time: blinded photo review response fell from 79.7% at baseline to 47.1% at 3 years, and physician rating from 90.3% to 50.5%, so the cosmesis conclusions rest on roughly half the cohort with unblinded delivery. The QoL substudy also had imbalances, more stage II sequentially (39.7% vs 32.5%) and more IMRT concurrently (27.1% vs 18.5%).
The point estimate favors sequential (HR 1.31) even as the confidence bound clears the margin, so this is a noninferiority conclusion in the honest sense, not equivalence. With 7-year IBR at 2.2% and 2.6%, the absolute difference is under a percentage point in a deliberately high-risk cohort, which is the frame in which trading 6 to 7 fractions is reasonable.
CONSORT flow
Adequately powered phase III, prespecified noninferiority margin met at 7.3yr median f/u, with cosmesis and toxicity co-endpoints also noninferior. Removes 6-7 fractions.
- Late cosmesis and fibrosis beyond 3 years with an integrated boost n=132 · primary completion 2026-03 · 1° EP RT fibrosis at 4y with hypofx tumor bed boostn=50 · primary completion 2028-09 · cosmesis + PROMs to 60mo after ultra-short WBI/SIB
- Does noninferiority hold at 10-year IBR follow-up
- Integrated boost on ultrahypofractionated 5-fraction whole-breast RT recruiting Ultra Hypo-fractionated Adjuvant Whole Breast Radiation Therapy With Simultaneous Integrated Boost for Early-Stage Breast Cancer (H-ASSIST) Phase 2n=90 · primary completion 2028-02 · 5fx WBI + SIB, toxicity and QoL endpointsrecruiting 5 fr Ultrahypofractionated WBI and SIB for Breast Cancer With Unfavorable Characteristics Phase NAn=458 · primary completion 2029-06 · randomised 26Gy/5fx + SIB 30Gy vs 40.05Gy/15fx + SIBn=400 · primary completion 2030-12 · phase 3 FAST-Forward 1wk vs 2wk concomitant boost
📚 Sources · 📄 1 paper
Abstract
Multinational HCC EBRT IPD Cohort
ForVery early / early-stage HCC (BCLC-0 or A), incl. treatment-naive
TL;DRMedian OS 6.8y BCLC-0 and 4.6y BCLC-A across 4,913 EBRT-treated HCC pts, comparable to resection and ablation.
The modifiable RT variable in the Cox model is ablative dose, which was associated with reduced mortality, so the transferable read is that dose, not simply delivering EBRT, tracks with the outcome. Fractionation and dose thresholds are not given in the abstract. This is the citation for putting EBRT on the BCLC-0/A allocation discussion.
In BCLC-0 or A HCC where resection, transplant, or ablation is not feasible or is declined, this supports discussing ablative-dose EBRT as a locoregional option; it does not establish EBRT over resection or ablation in a pt eligible for either. The longer read
Ablative dose was the modifiable variable associated with reduced mortality, so the transferable read is dose, not simply offering EBRT. Dose thresholds, fractionation, and modality mix are not given in the source abstract. This is the citation for putting EBRT into the BCLC-0/A allocation discussion at tumor board.
Child-Pugh B or C, performance status, and tumor burden drove mortality in the multivariable model, which is the gating frame for who gets locoregional therapy at all. For the med onc coordinating a BCLC-0/A pt, EBRT enters the locoregional menu alongside ablation rather than as a last resort.
Median OS of 6.8 y (BCLC-0) and 4.6 y (BCLC-A) in EBRT-treated pts is a cross-literature benchmark against resection and ablation, not a head-to-head. It bears on referral for the medically inoperable or anatomically difficult pt, and does not establish EBRT over resection in a fully resectable candidate.
9 details 2 trials watching
Systematic review of EBRT publications meeting prespecified HCC technical standards (search date December 15, 2022), with corresponding authors invited to contribute individual patient data. Kaplan-Meier OS and RMST stratified by BCLC stage and treatment status; random-effects Cox for covariates. No comparator arm.
4,913 pts treated with EBRT, median follow-up 5.0 years, multinational. Analyses split by BCLC stage and by treatment-naive vs treatment-experienced; the headline read sits in BCLC-0 and BCLC-A.
EBRT delivered per each contributing series, gated by the prespecified technical standards rather than one protocol. Ablative dose was associated with a reduced risk of death; specific dose levels, fractionation, and modality mix are not given in the source abstract.
Overall survival by Kaplan-Meier and restricted mean survival time, stratified by BCLC stage and treatment status. Covariate associations from multivariable random-effects Cox modeling.
Median OS 6.8 y (95% CI 5.7-8.7) for BCLC-0 and 4.6 y (95% CI 4.1-5.1) for BCLC-A. Treatment-naive: not reached (95% CI 8.6-NR) for BCLC-0, 5.4 y (95% CI 4.5-6.7) for BCLC-A.
| Cohort | BCLC-0 | BCLC-A |
|---|---|---|
| All pts | 6.8 y (95% CI 5.7-8.7) | 4.6 y (95% CI 4.1-5.1) |
| Treatment-naive | NR (95% CI 8.6-NR) | 5.4 y (95% CI 4.5-6.7) |
The authors frame these medians as comparable with resection, thermal ablation, and other ablative locoregional therapies, a cross-study benchmark rather than a randomised comparison. EBRT's exclusion from BCLC has rested on the absence of OS evidence, which is the gap this cohort is built to fill.
IPD came only from authors who published and agreed to share, so contributing centers are self-selected and unmeasured selection at the patient level (who was routed to EBRT rather than resection) is unrecoverable. More recent year of treatment predicting survival mixes technique gains with stage migration and modern systemic salvage over a multi-decade accrual window.
The claim is an allocation claim, not an efficacy claim: EBRT belongs in the BCLC decision tree as an option to be weighed. It does not settle sequencing against ablation in a pt eligible for both, and the ablative-dose signal makes the quality of the RT, not its mere availability, the operative variable.
Largest EBRT IPD cohort argues for a BCLC allocation change, but it is pooled non-randomised data with no head-to-head comparator against resection or ablation.
- Ablative dose threshold and fractionation driving the survival association
- EBRT vs thermal ablation head-to-head in early HCC recruiting Stereotactic Radiosurgery Versus Radiofrequency Ablation for Primary Liver Cancer Phase 2n=130 · primary completion 2025-01 · phase 2 SBRT vs RFA, inoperable primary liver caactive Stereotactic Body Radiotherapy Versus Radiofrequency Ablation for Unresectable, Small (≤ 3 cm) HCC Phase NAn=178 · primary completion 2026-12 · randomised SBRT vs RFA, unresectable HCC <=3cm
- Selection differences between EBRT-treated and resected early-stage pts
📚 Sources · 📄 1 paper
Abstract
FASTRACK II NCT02613819
ForPrimary RCC ≤10cm, T1b-dominant, medically inoperable or declined surgery
100% at 36, 60, 84 mo
ITT population, RECIST-assessed, median f/u 62 mo
TL;DR100% freedom from local progression at 36, 60, and 84mo after single-fraction 26Gy or 42Gy/3fx SABR in inoperable primary RCC.
The transferable detail is the size-adapted prescription: 26Gy in one fraction under 4cm, 42Gy/3fx above it, with median tumour 46mm and 65% T1b or higher. That is a larger-tumour cohort than most ablation series, and zero local failures out to 84mo supports offering SABR when a 77-year-old is turned down for nephrectomy.
In a medically inoperable or surgery-declining patient with a primary RCC up to 10cm, including T1b and larger where thermal ablation is a poor fit, this supports SABR as a durable local option; it does not speak to the operable patient, where nephrectomy remains untested against it. The longer read
The transferable detail is the size-adapted prescription: 26Gy single fraction under 4cm, 42Gy/3fx above it, in a cohort with median tumour 46mm and 65% at least T1b. Zero local failures to 84mo supports offering SABR when the patient is turned down for nephrectomy; bowel toxicity (two colonic obstructions) sets the technical ceiling.
This is the non-surgical arm of the small-renal-mass conversation getting real prospective follow-up, at a median tumour of 46mm where thermal ablation performs worst. It changes what you can tell a high-risk or surgery-declining patient at referral; it does not test SABR against partial nephrectomy in an operable patient, which remains unstudied.
10 details
Non-randomised phase 2, eight hospitals in Australia and the Netherlands, run by TROG and ANZUP. Enrolment July 28 2016 to Feb 27 2020; 71 enrolled, one withdrew consent before treatment. This report is the pre-planned final follow-up at a median of 62 months (IQR 60-72).
Histologically confirmed primary RCC, medically inoperable, high risk, or declined surgery, ECOG ≤2, tumours ≤10 cm, N0-N1. Median age 77 years (70-82), 49 (70%) male. Median tumour size 46 mm (37-55), with 39 (56%) T1b, six (9%) T2a and one (1%) T3a.
Size-adapted prescription: 26 Gy in a single fraction for tumours ≤4 cm, 42 Gy in three fractions 48 h apart for tumours >4 cm. Histological confirmation was required before treatment, so this is a biopsy-proven cohort rather than a radiographic-diagnosis one.
Primary: freedom from local progression by RECIST, assessed in the intention-to-treat population, as was safety.
100% local control at 36, 60 and 84 months, with no local recurrences and no cancer-related deaths reported in the cohort.
Seven (10%) patients had at least one treatment-related grade 3 event within 9 months: pain in four (6%), nausea and vomiting in three (4%), colonic obstruction in two (3%), diarrhoea in one (1%). No grade 4 events and no treatment-related deaths; no new long-term safety signals emerged with extended follow-up.
A 100% point estimate in 70 pts carries a wide confidence bound that the headline hides, and RECIST is an imperfect local-control instrument after ablative RT, where a treated mass commonly persists without viable tumour. Renal function trajectory, the endpoint that actually competes with nephrectomy, is not reported in this source.
Prior SABR evidence in primary RCC was retrospective and pooled, so a prospective multicentre dataset at 84 months is the new contribution rather than the effect size itself. Comparison to partial nephrectomy and thermal ablation remains indirect: no randomised trial has run, and this cohort was selected against surgery by definition.
The finding that transfers is durability at a tumour size where thermal ablation performs worst, with a median of 46 mm and 65% at least T1b. What it does not settle is whether SABR is a choice rather than a fallback, which needs a randomised or matched comparison in operable pts, with renal function as a co-primary.
Single-arm phase 2, N=70, inoperable or surgery-declining pts only. No randomised comparator vs partial nephrectomy or thermal ablation. Maturity gate holds despite 62mo f/u.
- SABR vs partial nephrectomy in operable pts
- Renal function trajectory after SABR vs nephrectomy
- SABR vs thermal ablation in T1b tumours
📚 Sources · 📄 1 paper
Abstract
POP-RT vs PEACE-2
TL;DRWPRT bFFS HR 0.50 (POP-RT) vs bPFS HR 0.97 (PEACE-2); pelvic RT benefit vanishes with 3yr ADT, PSMA staging.
POP-RTPEACE-2
The reversal tracks four coupled changes, and the one an RT reader controls is target volume: with 36 months ADT, 78 Gy EQD2 and PSMA staging, WPRT bought nothing biochemically (HR 0.97, p=0.73) where it halved biochemical failure at 24 months ADT and 74-76 Gy (HR 0.50). This moves elective nodal coverage toward optional in PSMA-staged very-high-risk N0M0 on 3 years of ADT, not in conventionally staged pts.
In very-high-risk N0M0 prostate staged by PSMA PET and planned for 36 months ADT with dose-escalated RT, this questions routine whole-pelvis coverage; it does not extend to conventionally staged pts or shorter ADT, where POP-RT still supports it. The longer read
Target volume is the variable you own here. WPRT halved biochemical failure at 24 months ADT and 74-76 Gy EQD2 (HR 0.50) but returned HR 0.97 (p=0.73) at 36 months ADT, 78 Gy and PSMA staging, with no toxicity penalty either way. Elective nodal coverage becomes conditional on staging and ADT length, not automatic.
ADT duration is the confounder doing the heavy lifting: 24 vs 36 months separates the two trials as much as the RT volume does. If 3 years of ADT is what erases the nodal-RT signal, then shortening ADT for tolerability reopens the case for pelvic coverage, so the systemic and RT decisions cannot be made independently in very-high-risk N0M0.

| Endpoint | POP-RT HR (95% CI), p | PEACE-2 HR (95% CI), p |
|---|---|---|
| bFFS / bPFS | 0.50 (0.42-0.61), p<0.001 | 0.97 (0.81-1.16), p=0.73 |
| cFFS / cPFS | 0.74 (0.61-0.90), p=0.002 | 0.81 (0.63-1.03), p=0.09 |
| MFS | 0.72 (0.58-0.89), p=0.002 | 0.93 (0.74-1.17), p=0.54 |
8 details 4 trials watching
Two independent phase III, open-label, randomized trials of whole-pelvis RT vs prostate-only RT, set side by side in a curator comparison graphic. POP-RT accrued 2011-2016 (median f/u 6.3-7.2 yr, updated); PEACE-2 accrued 2018-2023 and reads out at ~5.5 yr median f/u as an interim analysis (ESTRO 2026).
POP-RT enrolled high / very-high-risk localized N0M0 disease staged by conventional CT and bone scan. PEACE-2 restricted to very-high-risk N0M0 with PSMA PET/CT widely used, so its N0 is a cleaner, node-negative-by-molecular-imaging population.
Both delivered IMRT to whole pelvis plus prostate boost against prostate-only IMRT. Prostate dose was 74-76 Gy EQD2 in POP-RT and 78 Gy EQD2 in PEACE-2, so the control arm in the newer trial is the better-treated prostate.
ADT was a GnRH analog plus antiandrogen in both, but 24 months in POP-RT vs 36 months in PEACE-2. The extra year of systemic control is the single most plausible eraser of a nodal-RT effect.
Primary: bFFS in POP-RT, biochemical PFS in PEACE-2. Secondaries overlap (clinical failure/progression, MFS, OS, toxicity), with PEACE-2 adding CSS. The endpoints are close analogues but not identically defined, which limits how tightly the HRs can be compared.
Both trials reported comparable Grade ≥2 late GU toxicity between arms, with no significant increase in toxicity from WPRT in either. Toxicity is therefore not the lever in this decision; efficacy is.
POP-RT remains the only randomized trial to show a clear elective pelvic RT benefit (bFFS HR 0.50, MFS HR 0.72). PEACE-2's null biochemical result (HR 0.97) at interim is the first randomized read to contradict it, and it does so with a systemic and staging backbone POP-RT never had.
The two trials differ simultaneously in ADT duration, prostate dose, staging modality, risk band and accrual era, so no single factor can be assigned the loss of effect. PEACE-2's read is also interim with shorter follow-up than POP-RT's, and biochemical endpoints mature earliest, so the later endpoints are the least settled.
The graphic's own reading is that longer ADT, modern staging and intensified local therapy may reduce the incremental benefit of elective pelvic RT in very-high-risk disease. That is a hypothesis this comparison cannot test: it settles nothing about which of the four changes did the work, and a reader who shortens ADT while omitting pelvic RT is borrowing from both trials at once.
| Endpoint | POP-RT | PEACE-2 |
|---|---|---|
| Biochemical (bFFS / bPFS) | HR 0.50 (0.42-0.61), p<0.001 | HR 0.97 (0.81-1.16), p=0.73 |
| Clinical (cFFS / cPFS) | HR 0.74 (0.61-0.90), p=0.002 | HR 0.81 (0.63-1.03), p=0.09 |
| MFS | HR 0.72 (0.58-0.89), p=0.002 | HR 0.93 (0.74-1.17), p=0.54 |
- Does PEACE-2's cPFS signal mature into benefit at final analysis?
- Is longer ADT or PSMA staging the reason pelvic RT stopped working? n=250 · primary completion 2031-05 · PSMA-N0M0 randomised to PORT vs prostate+WPRTrecruiting Abi/Pred + ADT vs ADT in PSMA-Positive, Conventionally Node-Negative Prostate Cancer Phase 2n=140 · primary completion 2033-04 · PSMA+ cN0 nodes: ADT vs abi/pred intensification
- Does elective pelvic RT still help pts on shorter ADT? recruiting Phase II Trial of PSA Response-based Androgen Deprivation Therapy and Nodal Coverage for Prostate Cancer Early Salvage Radiotherapy (RANGER) Phase 2n=68 · primary completion 2030-11 · adds pelvic nodal RT + 4mo ADT in PSA nonrespondersn=250 · primary completion 2031-05 · prostate-only vs whole-pelvis RT, high-risk N0
📚 Sources · 🐦 1 tweet
POP RT Vs PEACE II
— Rohit Malde (@roxboxfix) May 18, 2026
2 years ADT + WPRT
Vs 3 years ADT + Prostate Only RT
Tough to choose or you already have a choice ?? pic.twitter.com/42kdSKQYKW
PRIME NCT03561961
ForHigh-risk, very high-risk or node-positive non-metastatic prostate; ECOG 0-2
TL;DRInterim: acute grade ≥2 GU ~5.4% vs ~4.0% (p=0.59) for 5-fx SBRT vs 25-fx, both with whole-pelvis RT; BFFS immature.
The transferable parameter is the nodal dose: 25 Gy in 5 fractions to elective pelvis in both arms, with SIB to involved nodes permitted only in the SBRT arm. Late grade ≥2 GU ran ~10-12% vs ~9-11% at 1-2 yr, so the 5-fraction schedule carried no toxicity penalty over 25 fractions in a node-covered field.
In high-risk or node-positive non-metastatic prostate cancer where whole-pelvis RT and ~2 years of ADT are already planned, this supports 5-fraction delivery on toxicity grounds; it does not yet inform biochemical control, and does not extend to pts treated to prostate alone. The longer read
The gate is the elective nodal dose: 25 Gy in 5 fractions to whole pelvis in both arms, SIB to involved nodes only in the SBRT arm. Grade 3+ GU/GI stayed <1% either way, so the decision this moves is whether pelvic coverage can be compressed to 5 fractions, not whether it controls nodes.

+1 more figure

| Feature | HYPO-RT-PC | PRIME |
|---|---|---|
| Fractionation | 42.7 Gy/7 fx vs 78 Gy/39 fx | 36.25 Gy/5 fx vs 68 Gy/25 fx |
| Pelvic RT | None (prostate + SV) | Whole pelvis, 25 Gy/5 fx, both arms |
| ADT | Not permitted | Long course (~2 years), both arms |
| Nodal status | Node-negative only | Includes node-positive |
| Primary result | 10-yr FFS 72% vs 65%, adj HR 0.84 (95% CI 0.69-1.03) | BFFS not yet mature |
9 details 3 trials watching
Phase III, open-label, randomized non-inferiority trial from Tata Memorial Centre and collaborating Indian centres. Accrual 2018 to 2023, completed at ~434 pts, 1:1, stratified by risk group and nodal status. Interim analysis with follow-up of 1 to 2 years.
High-risk, very high-risk and/or node-positive non-metastatic prostate cancer, ECOG 0-2, life expectancy 10 years. PSMA PET/CT staging was permitted, so nodal staging is not uniform across the cohort.
Arm A 36.25 Gy in 5 fractions (7.25 Gy/fx), every other day. Arm B ~68 Gy in 25 fractions (2.7 Gy/fx) over ~5 weeks. Both arms received whole-pelvis elective nodal RT at 25 Gy in 5 fractions or equivalent, with SIB to positive nodes allowed in the SBRT arm; delivery was modern IMRT/VMAT with daily IGRT.
Long-course ADT (~2 years) in both arms, so the randomised variable is fractionation alone, not systemic intensity.
Primary: biochemical failure-free survival (Phoenix, nadir + 2 ng/mL). Secondary: acute and late toxicity (RTOG/CTCAE v4.0/5.0), OS, MFS, cFFS, QoL (EORTC QLQ-C30, QLQ-PR25, IPSS) and cost-effectiveness.
No BFFS, MFS or OS estimate is reported in the source. The interim efficacy statement is only no signal of inferiority for the SBRT arm, with mature 4 to 5 year data awaited.
| Toxicity | SBRT 5 fx | Mod hypo 25 fx | p |
|---|---|---|---|
| Acute GU (≤90 days) | ~5.4% | ~4.0% | 0.59 |
| Acute GI (≤90 days) | ~2.2% | ~3.7% | 0.20 |
| Late GU (1-2 yr) | ~10-12% | ~9-11% | NS |
| Late GI (1-2 yr) | ~5-7% | ~4-6% | NS |
| Grade 3+ GU/GI | <1% | <1% | not reported |
QoL by EORTC QLQ-C30, QLQ-PR25 and IPSS showed urinary and bowel domains stable and comparable between arms, with transient declines during and soon after treatment then recovery. ADT-related sexual and hormonal effects were similar, as expected with a fixed 2-year backbone in both arms.
HYPO-RT-PC gave level-1 support for ultra-hypofractionation (10-yr FFS 72% vs 65%, adjusted HR 0.84, 95% CI 0.69-1.03), but in node-negative pts with no pelvic RT and no ADT, mostly on 3D-CRT. PRIME asks the fractionation question where the target includes the pelvis and the backbone is 2 years of ADT, so its toxicity read is not inherited from that trial.
Toxicity reaches the reader as approximate values on a third-party summary graphic rather than a published table, and late follow-up of 1 to 2 years is short for the GU and GI events that separate fractionation schedules. Open-label design also leaves the QoL and IPSS readouts unblinded.
If BFFS holds at 4 to 5 years, the practical claim is that elective pelvic coverage can be delivered in 5 fractions instead of 25, compressing a 5-week course to 1 to 2 weeks where linac time rations access. Toxicity is the necessary first gate and it clears; non-inferiority is an efficacy claim and nothing here tests it yet.
Interim toxicity and QoL readout at 1-2 yr; primary BFFS not reported and 4-5 yr efficacy pending. Safety comparability cannot establish non-inferiority of 5-fraction SBRT.
- Adequacy of 25 Gy/5 fx elective nodal dose for microscopic disease recruiting A Trial of 5 Fraction Prostate SBRT Versus 5 Fraction Prostate and Pelvic Nodal SBRT Phase 3n=1128 · primary completion 2028-06 · phase 3, 5-fx prostate vs prostate+pelvic nodal SBRTrecruiting PRO-BOOST-N: Prostate-First Versus Combined Prostate and Nodal Dose Escalation in PSMA PET-Staged Node-Positive Prostate Cancer Phase 2/3n=600 · primary completion 2033-12 · randomises nodal dose escalation over UHF whole-pelvis
- Late GU/GI toxicity beyond 2 years with 5-fraction whole-pelvis RT
- Mature BFFS non-inferiority at 4-5 years recruiting Comparing Moderately Ultra Hypofractionated Radiation Treatments for Prostate Cancer Phase 2n=204 · primary completion 2030-11 · non-inferiority: 25 Gy/5 fx vs 44 Gy/20 fx pelvic nodes
📚 Sources · 🐦 1 tweet
PRIME trial
— Rohit Malde (@roxboxfix) May 18, 2026
Can we safely deliver ultra-short SBRT including pelvic nodal irradiation in biologically aggressive disease treated with ADT?
With Pelvic RT
Moderate hypofractionation:
~68 Gy/25#/5w
Vs
Extreme hypofractionation/SBRT:
36.25 Gy / 5 # /1-2w
Compare HYPO RT PC pic.twitter.com/7NABknLsD5
PIVOTALboost
ForHigh-risk localised prostate, 20-fraction IMRT candidates
TL;DRAdding pelvic nodal IMRT to a focal prostate boost in 20fx raised early bowel toxicity only; 2yr G2+ rates similar across arms.
The 2-year cumulative G2+ rates run in the wrong direction for a toxicity argument against nodal RT: bowel 6.5% (4.5-9.5) and bladder 16.5% (13.1-20.6) in the nodes+boost arm, below both prostate-only arms. Whatever excess bowel toxicity nodal RT causes lives inside 18 weeks. That removes late toxicity as the reason to omit pelvic nodes in 20fx, and leaves the decision resting entirely on the unreported efficacy endpoint.
In high-risk localised prostate planned for 20-fraction IMRT, this supports that adding a focal boost with or without pelvic nodal coverage does not raise 2-year G2+ bowel or bladder toxicity; it says nothing about whether either improves biochemical control. The longer read
At 2 years, the nodes-plus-boost arm sat at 6.5% G2+ bowel (4.5-9.5) and 16.5% bladder (13.1-20.6), below both prostate-only arms, so the excess bowel toxicity from pelvic coverage is confined to the first 18 weeks. In a 20-fraction schedule, late morbidity is no longer the argument for omitting elective nodal RT or a focal boost.

| Arm | Bowel G2+ (95% CI) | Bladder G2+ (95% CI) |
|---|---|---|
| Prostate (n=281) | 8.2% (5.7-11.7) | 19.5% (15.5-24.4) |
| Prostate+Boost (n=345) | 8.7% (6.3-12.1) | 24.1% (20.2-28.7) |
| Prostate+Nodes+Boost (n=347) | 6.5% (4.5-9.5) | 16.5% (13.1-20.6) |
+1 more figure
8 details 5 trials watching
Phase 3 RCT, N=1465 randomised at 39 UK centres. Primary endpoint is biochemical/clinical failure; the side-effect endpoints presented here are secondary. Early toxicity assessed to 18 weeks, late toxicity at 2 years.
Localised prostate cancer, with the slides naming the high-risk localised group as most likely to benefit from the interventions under test. Full eligibility criteria not stated in the source.
20-fraction moderately hypofractionated IMRT in all arms. Randomisation is to prostate alone (388), prostate + focal boost (464), or prostate + pelvic nodes + focal boost (462), so the trial separates the boost question from the nodal question. Prescription dose and boost dose level not stated in the source slides.
Primary: biochemical/clinical failure, not reported at this presentation. Secondary (reported here): early bowel and bladder side effects to 18 weeks and late G2+ events at 2 years.
Nodal RT increased early bowel side effects, resolving by 18 weeks. Late cumulative rates were reported for the 973 (74%) patients with at least 2 years' follow-up.
The nodal question in prostate RT is currently split: POP-RT favoured whole-pelvis RT on biochemical failure-free survival while PEACE-2 was null on its nodal comparison, and both used conventional or near-conventional fractionation. PIVOTALboost is the first randomised test of pelvic nodal coverage in a 20-fraction schedule, so its eventual efficacy readout is the one that transfers to how most UK and increasingly non-UK practice actually delivers prostate RT.
The late analysis rests on the 74% with 2 years of follow-up, so a differential drop-out by arm would bias the comparison, and cumulative-incidence estimates at 2 years cannot address the fibrotic and stricture toxicity that appears at 5 to 10 years. The source does not state the grading instrument, and a clinician-graded versus patient-reported difference materially changes the size of a G2+ bowel signal.
A safety readout without its efficacy partner cannot move the nodal decision on its own, but it does close off one of the two arguments against nodal coverage in the hypofractionated era. The remaining argument is whether pelvic nodal RT does anything for disease control, which this trial is powered to answer and has not yet reported.
CONSORT flow
Randomised phase 3, but this is the secondary toxicity readout only; the biochemical/clinical failure primary endpoint is unreported, so it settles safety, not benefit.
- Does pelvic nodal RT improve biochemical/clinical failure at 20 fractions? n=18 · primary completion 2026-08 · 20fx pelvic nodal RT with prostate SIBrecruiting Phase III Adaptive Adaptive Stereostactic Body Radiotherapy (SBRT) With Dose Escalation for High-Risk Prostate Cancer Phase NAn=390 · primary completion 2033-04 · WPRT + DIL boost vs standard RT, high risk
- Does the focal intraprostatic boost add control over prostate IMRT alone? recruiting Image-guided Focal Dose Escalation- Primary pc Treated With Primary External Beam Hypofract.Stereotactic rt Phase NAn=374 · primary completion 2025-08 · arm A focal dose escalation vs arm B IMRTactive Standard Moderately Hypofractionated RT vs. Ultra-hypofractionated Focal Lesion Ablative Microboost in Prostate Cancer Phase NAn=484 · primary completion 2032-01 · Hypo-FLAME microboost vs standard 20fx RTrecruiting Addition of Focal Boost to Primary Radiotherapy for Prostate Cancer in 12 or 20 Fractions Phase NAn=1016 · primary completion 2040-10 · randomises focal boost vs none at 20fx
- Do G2+ rates diverge beyond 2 years as late fibrotic toxicity matures?
📚 Sources · 🐦 1 tweet
Day THREE of #ESTRO26 Coverage by OncoAlert 🚨
— OncoAlert (@OncoAlert) May 17, 2026
Moderately fractionated prostate radiotherapy with a focal boost: acute and preliminary late side effects from the phase 3 PIVOTALboost trial Presented by Isabel Syndikus 🇬🇧 #RadOnc ☢️
In the PIVOTALboost trial, we treated 1314… pic.twitter.com/cGuR1j2Qos
PACE-NODES
ForHigh-risk localised prostate (T3a-T4, Gleason 8-10, or PSA>20), on 12-36mo ADT
28% vs 21%
PPN-SBRT vs P-SBRT; no effect size or p-value reported in source
TL;DRCTCAE G2+ GI toxicity 28% vs 21% with added pelvic nodal SBRT; no GU difference, symptoms resolved by 12wk.
Nodal SBRT at 25Gy/5f costs 7 points of acute G2+ GI (28% vs 21%) and nothing in GU, with the EPIC-26 bowel signal at 4 weeks resolving by 12. That makes acute tolerability a weak argument against 5f elective nodal coverage; the decision now waits on late effects and the immature failure endpoint.
In high-risk localised prostate already planned for 5f prostate SBRT plus 12-36mo ADT, this supports the feasibility of extending to pelvic nodes without a GU penalty; it says nothing yet about whether nodal coverage improves control. The longer read
The cost of adding 25Gy/5f to the pelvis is 7 points of acute G2+ GI (28% vs 21%), transient by 12 weeks, with no GU penalty. The gating practical fact is deliverability: 11% of PPN-SBRT patients never received allocation on unmet constraints.

| Endpoint | PPN-SBRT | P-SBRT |
|---|---|---|
| CTCAE G2+ GI, 12wk | 28% | 21% |
| Did not receive allocation | 11% | 4% |
+1 more figure
10 details 3 trials watching
Phase 3 randomised 1:1 multicentre trial, target n=1128, 1166 randomised. This presentation reports the acute toxicity analysis only; the efficacy primary is time to biochemical or clinical failure and is not yet mature.
High-risk localised prostate cancer: T3a-T4 and/or Gleason 8-10 and/or PSA>20ng/ml, all planned for 12-36 months ADT.
Both arms 36.25Gy in 5 fractions to the prostate on alternate days. PPN-SBRT adds 25Gy in 5 fractions to the pelvic nodes; P-SBRT is prostate-only.
Primary for this analysis: CTCAE grade ≥2 GI and grade ≥2 GU toxicity up to 12 weeks. Patient-reported EPIC-26 domain scores collected at 4 weeks.
GI was the only separating domain; GU did not differ by clinician or patient report, and the GI gap had closed by 12 weeks.
11% of PPN-SBRT and 4% of P-SBRT patients did not receive their allocated treatment, mostly because planning constraints were not met, which is itself a deliverability signal for 5f nodal treatment.
Patient-reported outcomes were captured at 4 weeks only, so the 12-week convergence rests on clinician CTCAE grading. No effect size, confidence interval or p-value for the GI difference appears in the source, and late GI toxicity is the endpoint that historically decides elective nodal coverage.
The trial's answer so far is about deliverability rather than benefit: 5f nodal SBRT can be given across multiple centres at an acute cost confined to transient bowel symptoms. Whether that cost is worth paying depends entirely on the failure endpoint still to read out.
Acute-toxicity readout only; the efficacy primary (time to biochemical or clinical failure) is immature, so the nodal-coverage question stays open.
- Late GI toxicity beyond the 12-week acute window n=100 · primary completion 2027-10 · 1-2mm PTV margins to cut late rectal toxicityn=500 · primary completion 2027-12 · late GI toxicity as primary endpoint after prostate SBRT
- Whether 5f nodal SBRT improves biochemical or clinical failure recruiting PRO-BOOST-N: Prostate-First Versus Combined Prostate and Nodal Dose Escalation in PSMA PET-Staged Node-Positive Prostate Cancer Phase 2/3n=600 · primary completion 2033-12 · randomises nodal dose in cN1 ultrahypofx pelvic RT
- Which anatomy or constraints drove the 11% non-delivery rate
📚 Sources · 🐦 1 tweet
Day THREE of #ESTRO26 Coverage by OncoAlert 🚨
— OncoAlert (@OncoAlert) May 17, 2026
Acute toxicity in PACE-NODES: A randomised trial of 5 fraction (f) prostate stereotactic body radiotherapy (SBRT) vs 5f prostate and pelvic nodal SBRT
Presented by Angela Pathmanathan 🇬🇧 #RadOnc ☢️ #ProstateCancer
PACE-NODES is a… pic.twitter.com/z9bAOiKSIy
PEACE-2
ForVery-high-risk localized prostate, N0M0, ≥2 of Gleason ≥8 / T3-T4 / PSA ≥20
HR 0.81
95% CI 0.63-1.03, p=0.088, primary endpoint not met
TL;DRcPFS HR 0.81 (0.63-1.03), p=0.088: pelvic RT over prostate-only missed its primary endpoint in very-high-risk N0M0.
The target-volume decision is the whole trial: ADT × 3 years and the systemic backbone were fixed, so the 4.2-point 7yr cPFS gap (67.1% vs 62.9%, p=0.088) is what elective pelvic coverage buys in conventionally-staged N0M0 disease. No dose or fractionation appears in the source slides, and staging used conventional imaging or choline PET, not PSMA.
In very-high-risk localized prostate cancer staged N0M0 on conventional imaging or choline PET, this questions routine elective pelvic nodal coverage added to 3 years of ADT; it does not address PSMA-staged or node-positive disease. The longer read
Target volume is the randomized variable with the systemic backbone fixed, so the 7yr cPFS gap of 67.1% vs 62.9% (HR 0.81, p=0.088) is the entire return on elective pelvic coverage in conventionally-staged N0M0. Dose and fractionation are absent from source, blocking a technique-level transfer.
ADT × 3 years ran in every arm and cabazitaxel × 4 cycles was the second randomization, so nothing here moves systemic choice. The relevant read is prognostic: fewer than 1 in 10 men died of prostate cancer in a decade, which questions intensification in this clinicopathologically-defined very-high-risk group.

| Arm | 7yr cPFS | HR (95% CI) | p |
|---|---|---|---|
| Pelvic RT | 67.1% [61.6; 72.2] | 0.81 [0.63; 1.03] | 0.088 |
| Prostate only RT | 62.9% [57.4; 68.1] | n/a | n/a |
+2 more figures


9 details 5 trials watching
International multicenter randomized trial with four arms crossing two questions: RT target volume (prostate only vs pelvis) and cabazitaxel × 4 cycles vs none. Primary: cPFS. The target-volume comparison reads out at 7 years.
Very-high-risk localized prostate cancer defined as ≥2 risk factors among Gleason ≥8, T3-T4, and PSA ≥20 ng/mL. N0M0 by conventional imaging or choline PET/CT.
Androgen deprivation therapy × 3 years in every arm, with cabazitaxel × 4 cycles as the second randomization. The systemic backbone is held constant across the target-volume comparison.
The randomized variable is target volume alone: prostate-only RT versus pelvic RT. Dose, fractionation, and nodal CTV definition are not reported in the source slides.
Primary: cPFS. Secondary: PSA response at 3 months, bPFS, metastasis-free survival, prostate-cancer-specific survival, OS, acute and long-term tolerance, QoL, and biopsy biomarkers.
cPFS HR 0.81 (0.63-1.03), p=0.088 on multivariable analysis, so the primary endpoint was not met. 7yr cPFS 67.1% pelvic versus 62.9% prostate-only. Toxicity and secondary endpoints are not reported in these slides.
POP-RT, a single-center randomized trial of roughly 224 men, reported a whole-pelvis benefit that made elective nodal coverage common practice in high-risk disease. PEACE-2 is larger and multicenter and does not reproduce a comparable signal on its own primary endpoint.
Staging predates routine PSMA PET, so occult nodal disease sits in both arms and dilutes a target-volume comparison. The RT dose, fractionation, and pelvic CTV definition are absent from the source, which blocks a transfer judgment to any specific technique.
The plenary's own conclusion turned on prognosis rather than the RT question: with fewer than 1 in 10 men dying of prostate cancer in the first decade, the "very high-risk" definition itself is what the investigators challenged. A cohort with that little cancer-specific mortality has little room for a target-volume difference to show up in cPFS.
CONSORT flow
Randomized, prespecified cPFS primary, adequate accrual (380 vs 381) and 7yr readout. Negative result contests routine elective pelvic coverage in N0M0 very-high-risk disease.
- Does PSMA PET staging identify a subgroup where pelvic RT helps n=250 · primary completion 2031-05 · PSMA-N0M0 high-risk randomised to PORT vs whole-pelvis RTrecruiting PRO-BOOST-N: Prostate-First Versus Combined Prostate and Nodal Dose Escalation in PSMA PET-Staged Node-Positive Prostate Cancer Phase 2/3n=600 · primary completion 2033-12 · PSMA PET-staged cN1M0: nodal dose escalation vs…
- Biomarkers to guide intensification vs de-intensification in very-high-risk disease
- Pelvic RT toxicity and QoL tradeoff not reported in source n=700 · primary completion 2021-12 · longitudinal GI/heme/GU toxicity + HRQoL after WPRTactive Hypofractionated Whole-Pelvis Radiotherapy (WPRT) vs Conventionally-Fractionated WPRT in Prostate Cancer Phase 2n=58 · primary completion 2026-09 · QoL of 5-fraction vs 25-fraction WPRTn=400 · primary completion 2027-03 · late GI toxicity, protons vs photons, whole-pelvis RT
📚 Sources · 🐦 1 tweet
📣@PBlanchardMD shows #ESTRO26 that pelvic #radiotherapy in high risk #prostatecancer does not have a large improve in outcomes.
— Shankar Siva (@_ShankarSiva) May 17, 2026
- With only 1 in 10 dying of prostate cancer in 10 years, are these patients truly “high risk”? #pcsm #radonc pic.twitter.com/D0XrGD6iNX
APBI-IMRT Florence NCT02104895
ForEarly breast cancer post-BCS, pT <25 mm, margins ≥5 mm, age >40
7.7% vs 4.2%
HR 1.57 (95% CI 0.82-3.04), p=0.17
TL;DR15-yr IBTR 7.7% APBI vs 4.2% WBI, HR 1.57 (0.82-3.04) p=0.17; excess driven by new ipsilateral primaries, not true local relapse.
The 5-fraction 30Gy IMRT schedule is what transfers: this is the longest follow-up for that specific PBI regimen, and the 15-yr excess sits in new ipsilateral primaries (5.9% vs 2.7%, p=0.09) rather than local relapse (2.1% vs 1.6%, p=0.75). That distinction is the whole case for keeping PBI in Florence-eligible pts, and it rests on adjudication, not on a powered endpoint.
In a woman over 40 after breast-conserving surgery with a tumour under 25 mm and margins of at least 5 mm, this supports offering 5-fraction PBI as a durable option; it does not extend to node-positive disease, close margins, or younger patients. The longer read
The transferable parameter is 30Gy in 5 fractions by IMRT, now with 15-yr follow-up. The excess ipsilateral events are new primaries (5.9% vs 2.7%, p=0.09), not local relapse (2.1% vs 1.6%, p=0.75), which is the distinction that justifies continuing PBI in Florence-eligible pts.
Nothing here moves systemic therapy: distant metastasis 2.7% vs 4.6% and breast-cancer deaths 2.3% vs 3.1% are indistinguishable at 15 years. What matters downstream is the new-primary rate of 5.9% with PBI, which shapes how much ipsilateral surveillance a de-escalated local approach earns.

+2 more figures


10 details
Phase III equivalence trial, 1:1 randomisation, n=520, accrued 2005-2013, median follow-up 15 years. Powered at 80% against a 5-year estimated IBTR of 3% with a 5% equivalence margin. Survival outcomes analysed ITT; toxicity and cosmesis per protocol after 14 withdrawals.
Post-breast-conserving-surgery early breast cancer: pT <25 mm, final surgical margins ≥5 mm, age >40 years. A selected, low-risk population by design.
PBI arm: 30Gy in 5 fractions delivered by IMRT (n=260). WBI arm: 50Gy in 25 fractions plus a 10Gy in 5-fraction tumour-bed boost (n=260).
No endpoint separated the arms at 15 years. The IBTR point estimate favours WBI (HR 1.57, 95% CI 0.82-3.04, p=0.17) but the confidence interval spans unity.
Florence remains the only randomised test of a 5-fraction IMRT PBI schedule with follow-up this long; other external-beam PBI randomisations used different dose and fractionation, so their recurrence rates are not directly interchangeable with this one. The direction here, a numerically higher IBTR concentrated in new primaries, is the pattern PBI trials have consistently reported when they separate the two.
The trial was sized for 5-year equivalence, so the 15-year IBTR comparison is a long-term description rather than a powered test, and the upper CI bound of 3.04 leaves room for a real excess. The relapse-versus-new-primary split is an adjudicated distinction, not a molecularly confirmed one, and it carries the entire reassurance.
The result supports continuing PBI in Florence-eligible pts rather than expanding the indication. It does not settle whether the new-primary excess is a genuine consequence of leaving untreated breast tissue unirradiated, which is biologically the expected cost of the approach and would not be captured by any local-control endpoint.
CONSORT flow
Randomised phase III with mature 15-yr follow-up; no significant difference on any oncological endpoint. Supports an already guideline-listed de-escalation rather than establishing a new one.
- Whether the new-primary excess reflects untreated ipsilateral breast tissue
- Ipsilateral surveillance intensity after partial-breast irradiation
- Applicability of 5-fraction PBI below age 40
📚 Sources · 🐦 1 tweet
📌 Fifteen-year outcomes of the randomised APBI-IMRT Florence phase Ill trial of partial versus whole-breast irradiation in early breast cancer ✨
— Elisabetta Bonzano MD, PhD (@to_be_elizabeth) May 17, 2026
Excellent presentation led by @CarlottaB 👏🏻#ESTRO26 @Icro_Meattini @ESTRO_RT @OncoAlert #OncoAlertAF pic.twitter.com/1j4bIA2nyC
EORTC IM-MS (22922/10925)
ForStage I-III breast cancer considering internal mammary / medial supraclavicular nodal RT
61.0% vs 61.8%
HR=1.00, 95% CI 0.90-1.10, P=0.967 (1° EP not met)
TL;DR20yr OS 61.0% vs 61.8%, HR 1.00 (0.90-1.10), P=0.967: the 15yr breast-cancer mortality benefit is erased by non-BCM.
The 20yr null OS is a competing-risk cancellation, not absent efficacy: BCM 18.6% vs 22.4% (HR 0.82) offset by non-BCM 20.4% vs 15.8% (HR 1.26), with cardiac disease 15.2% vs 11.7% and lung fibrosis 6.3% vs 3.2%. Whether IM coverage survives depends entirely on your heart dose, and DBCG IMN2 ran 4-9x lower.
In stage I-III breast cancer where IM-MS coverage is on the table, this supports the anti-cancer effect of IM irradiation while showing the 20yr survival gain is forfeited at 1990s-era heart doses; it does not describe outcomes at modern DIBH/IMRT cardiac exposures. The longer read
This is a planning-constraint result, not a target-volume result. IM coverage delivered BCM 18.6% vs 22.4% (HR 0.82) and gave it all back as non-BCM (HR 1.26), with cardiac disease 15.2% vs 11.7%. The benefit survives only if your mean heart dose looks like DBCG IMN2's 1.2-2.3 Gy, not this trial's.
The 20yr OS null (61.0% vs 61.8%) should not be read as breast-cancer control being unimproved: BCM fell to 18.6% from 22.4%. The excess deaths are cardiopulmonary, which is a comorbidity and cardiac-surveillance consideration in long survivors treated in older RT eras rather than a systemic-therapy signal.

| Endpoint | IM-MS RT | No IM-MS RT | HR | P |
|---|---|---|---|---|
| BCM rate | 18.6% | 22.4% | 0.82 (0.72-0.95) | 0.006 |
| non-BCM rate | 20.4% | 15.8% | 1.26 (1.09-1.46) | 0.002 |
+3 more figures

| Endpoint | IM-MS RT | No IM-MS RT | HR (95% CI) | P |
|---|---|---|---|---|
| Overall survival (ITT), 20yr | 61.0% | 61.8% | 1.00 (0.90-1.10) | 0.967 |

| RT-related side effect | IM-MS RT | No IM-MS RT |
|---|---|---|
| Lung fibrosis | 6.3% | 3.2% |
| Cardiac fibrosis | 2.7% | 1.7% |
| Cardiac diseases | 15.2% | 11.7% |

| Endpoint (pN0) | IM-MS RT | No IM-MS RT | HR | P |
|---|---|---|---|---|
| DFS rate | 53.9% | 53.6% | 0.93 (0.81-1.07) | 0.318 |
| DMFS rate | 67.2% | 67.4% | 0.93 (0.78-1.10) | 0.397 |
9 details
Randomised EORTC trial 22922/10925, stage I-III breast cancer, internal mammary + medial supraclavicular irradiation versus no IM-MS irradiation. This is the 20-year readout, presented as a plenary at ESTRO 2026, including a dedicated pN0 analysis.
The intervention is the IM-MS target volume itself, added to otherwise standard locoregional treatment. Per-arm dose and fractionation are not reported in source; what the presenters did quantify is the dosimetric era gap, with DBCG IMN2 mean heart doses 4-9 times lower (MHD 1.2 Gy right-sided, 2.3 Gy left-sided, treated 2007-2014).
Primary: overall survival (ITT). Secondary readouts presented at 20 years include DFS and DMFS under DATECAN definitions (DFS counts all deaths and all breast events including DCIS and contralateral; DMFS counts all deaths and distant metastases), breast-cancer mortality, non-breast-cancer mortality, second cancers, and RT-related late effects.
OS 61.0% vs 61.8%, HR=1.00 (0.90-1.10), P=0.967. DFS and DMFS are likewise flat (HR 0.97 each), and the pN0 subgroup shows no separation. The signal lives entirely in the cause-specific split.
No statistical difference in secondary cancers or second breast cancers between arms. Absolute RT-related late effects favour the control arm: cardiac disease 15.2% vs 11.7%, lung fibrosis 6.3% vs 3.2%, cardiac fibrosis 2.7% vs 1.7%.
The Danish DBCG IMN2 cohort (Nielsen, Lancet Reg Health Eur 2024) reported that IM-MS irradiation reduced distant metastasis and BCM and improved OS in node-positive pts at 15 years. The presenters attribute the divergence to technique, since IMN2 heart doses were 4-9x lower.
The pN0 result is a subgroup read on endpoints that were flat overall, so it cannot exclude a small benefit in that group. The competing-risk interpretation also rests on comparing this trial's toxicity against a non-randomised cohort treated a decade later, which is a dosimetric argument, not a trial result.
This is the cleanest available demonstration that an oncologically real nodal-RT benefit can be spent entirely on late cardiopulmonary mortality. It settles that IM-MS irradiation reduces breast cancer death; it does not settle whether the survival benefit is recoverable, which is now a planning question rather than a target-volume question.
Randomised, prespecified 1° OS, 20yr follow-up, null. Divergence from DBCG IMN2 is confounded by an old-technique heart dose (4-9x higher), not by design flaw.
- Does IM-MS survival benefit re-emerge at modern cardiac-sparing doses?
- Which nodal subgroups justify IM coverage given competing cardiac mortality?
📚 Sources · 🐦 2 tweets
📌 Internal Mammary and Medial Supraclavicular irradiation in stage I-III breast cancer: 20 years results of the randomised EORTC trial 22922/10925, including in pNo patients
— Elisabetta Bonzano MD, PhD (@to_be_elizabeth) May 17, 2026
Special Joint Presentation Led by Prof. Philip Poortmans and Orit Kaidar-Person ✨ at #ESTRO26 @ESTRO_RT… pic.twitter.com/KIoJtdhEzp
20-year outcomes of @EORTC internal mammary #radiotherapy trial.
— Shankar Siva (@_ShankarSiva) May 17, 2026
➡️internal mammary improved control
➡️ survival counterbalanced by late adverse events #radiotherapy #bcsm
Great to see the long term data at #ESTRO26, and discussing Charlotte Cole suggests with modern RT, long… pic.twitter.com/yPtlfrLcri
DBCG RT Natural
For≥60y, pT1N0, grade 1-2, ER≥10%, HER2 normal, margin ≥2mm, post-BCS
1.5% vs 9.8%
+RT 2/236, 1.5% (0.3-5.1); -RT 19/272, 9.8% (5.9-14.9)
TL;DR5yr invasive LR 1.5% with PBI vs 9.8% randomised no-PBI vs 8.2% self-selected no-PBI at 4yr median f/u.
The 2x2 by treatment received is the actionable read, not the arm comparison: -RT +ET reached 3.7% (7/213) while -RT -ET hit 12.2% (32/352), so ET adherence is what holds the omission strategy together, and it was suboptimal. PBI was 40Gy/15fr, not a 5-fraction schedule.
In a woman ≥60 with pT1N0 grade 1-2 ER-positive HER2-normal disease post-lumpectomy, this argues against dropping both PBI and endocrine therapy, and it does not address node-positive, lobular, grade 3, or ER-low disease, which were excluded. The longer read
PBI 40Gy/15fr drove LR to 1.5% (2/236) vs 9.8% randomised omission, and the -RT arm crossed the prespecified 4% ceiling. The +RT -ET cell at 3.0% (2/132) means RT alone holds local control without endocrine therapy, which moves the omission conversation for a patient who will not take or tolerate ET.
The -RT +ET cell reached 3.7% (7/213) versus 12.2% (32/352) with neither, so endocrine therapy alone is close to RT alone for local control here. But the ET grouping is by treatment received (≥4.5y vs <4.5y or low-risk), so that 3.7% describes completers and adherence is the load-bearing assumption in an ET-only strategy.

+3 more figures

| Study arm | Events/Total | CIF % (95% CI) |
|---|---|---|
| +RT | 2/236 | 1.5 (0.3-5.1%) |
| -RT | 19/272 | 9.8 (5.9-14.9%) |
| S-RT | 18/278 | 8.2 (4.5-13.3%) |


9 details 3 trials watching
Phase III randomized trial, PBI 40Gy/15fr vs no PBI, stratified by institution and endocrine therapy yes/no, with a third non-randomised self-selecting no-PBI cohort. Planned accrual 926 randomised with an interim analysis at 200 patients with 2 year follow-up. Median follow-up 4 years at this reading.
≥60 years, breast cancer treated with breast conservation, pT1N0, unilateral, unifocal, non-lobular, ER ≥10%, HER2 normal, grade 1-2, limited DCIS, margin ≥2mm. Endocrine therapy given per DBCG guideline, which recommends ET for pT1c and/or grade 2.
Partial breast irradiation, 40Gy in 15 fractions. This is a moderately hypofractionated PBI schedule, not the 5-fraction regimens now in wide use, which matters for how the toxicity and convenience side of the omission trade transfers.
Primary: 5 year invasive local recurrence, with a design assumption of 2% and a prespecified maximum acceptable 4%. Secondary: loco-regional side effects and quality of life. Follow-up yearly mammography plus loco-regional side effect assessment to 10 years.
All 41 recurrences were invasive and 39 of 41 arose in patients who received no PBI. Distant failure was rare across the whole trial at 4 events, 2 in each of the +RT and no-PBI groups.
Loco-regional side effects and QoL were prespecified secondary endpoints but no toxicity or QoL figures were reported in the source. The omission-versus-PBI toxicity trade that drives this decision is therefore unquantified here.
PRIME II and CALGB 9343 established that RT omission in older low-risk women is tolerable because absolute local recurrence stays low. Here the randomised no-RT arm reached 9.8% and crossed the trial's own 4% ceiling, which is the opposite result, and the discussant framed surgery alone as carrying high local recurrence even in low risk.
Median follow-up is 4 years against a 5 year primary endpoint, so the reported cumulative incidences are read before the timepoint the trial was designed around. The third arm is self-selected, not randomised, so its 8.2% carries confounding by whatever drove refusal, and the endocrine therapy split is by treatment received rather than assignment.
The trial's contribution is that it isolates the floor: a group with no adjuvant treatment at all, which the modern omission trials do not have because endocrine therapy is universal in their omission arms. 12.2% at that floor reframes the published omission literature as measuring RT omission on an endocrine backbone, not omission of local therapy. It does not settle whether PBI or ET is the better single agent, since 3.0% and 3.7% overlap widely.
CONSORT flow
Randomised, prespecified LR endpoint, stopped early by independent monitoring for exceeding the 4% threshold. Cuts against the de-escalation direction PRIME II and CALGB 9343 set.
- Does 5-fraction PBI match 40Gy/15fr local control in this population n=910 · primary completion 2029-11 · phase 3 PBI vs WBI, 1 week each, LR endpoint
- Toxicity and QoL trade between PBI and endocrine monotherapy n=30 · primary completion 2023-11 · SBRT added to endocrine tx, unoperated pts 75+n=168 · primary completion 2030-07 · randomised 30Gy vs 26Gy/5fr PBI, PRO endpoint
- Whether 4yr separation holds at the 5yr primary timepoint
📚 Sources · 🐦 2 tweets
Another trial showing even for lR optimal local control with RT and ET and suboptimal adherence to ET. In era of 5 fraction decision making is easier # Estro2026 pic.twitter.com/nkvYl3iuTn
— Sushil (@Sushilberiwal) May 17, 2026
Danish #breastcancer partial breast #radiotherapy “natural” trial.
— Shankar Siva (@_ShankarSiva) May 17, 2026
➡️ No postoperative treatment had highest risk of recurrence
➡️either tamoxifen or #radonc reduced recurrence
➡️combined tamoxifen + RT had no recurrences
In context of EUROPA trial, RT has best QoL vs endocrine… pic.twitter.com/bDVmbDKRNb
IMPORT HIGH
ForInvasive early breast, pT1-3 pN0-pN3a M0, post-BCS, requiring tumour bed boost
3.7% vs 3.5% 10yr IBTR (48Gy SIB vs 40+16Gy)
95% CI 2.6-5.3 vs 2.4-5.0; 53Gy/15F 5.5% (4.1, 7.3)
TL;DR10yr IBTR 3.7% with 48Gy/15F SIB vs 3.5% with 40Gy/15F + 16Gy/8F sequential; 53Gy/15F higher at 5.5%.
The decision this hardens is delivery, not dose: 48Gy/15F SIB holds at 3.7% (2.6, 5.3) IBTR at 10 years against 3.5% (2.4, 5.0) for a sequential 16Gy/8F phase, in a higher risk group. 53Gy/15F sits at 5.5% (4.1, 7.3), so escalation buys nothing.
For a woman after breast conserving surgery for pT1-3 pN0-pN3a invasive disease who needs a tumour bed boost, the 10-year data support the integrated 48Gy/15F arm over a separate sequential boost; they do not speak to boost omission or to 5-fraction whole-breast schedules. The longer read
Three weeks, one plan: the boost is integrated into 15 fractions with a modest dose reduction to whole breast distant from tumour, and IBTR at 10 years matches the sequential 16Gy/8F phase. Escalating the integrated boost to 53Gy/15F does not improve local control.

| Dose group | 10yr IBTR (95% CI) | 10yr OS abs. diff vs 40Gy/15F |
|---|---|---|
| 40Gy/15F + 16Gy/8F | 3.5% (2.4, 5.0) | reference |
| 48Gy/15F (3.2Gy/F) | 3.7% (2.6, 5.3) | -0.5 (-3.0, 2.8) |
| 53Gy/15F (3.5Gy/F) | 5.5% (4.1, 7.3) | 1.5 (-1.4, 5.1) |
+1 more figure

8 details 4 trials watching
Three-arm randomised multicentre trial, 1:1:1, N=2617 across 76 UK hospitals, recruited 2009-2015. Annual clinical follow-up to 10 years; PRO and photographic assessment collected only to 5 years.
Women ≥18 after breast conserving surgery for invasive early breast cancer, pT1-3, pN0-pN3a, M0, all requiring a tumour bed boost. Described as a higher-than-average risk group.
40Gy/15F + 16Gy/8F sequential boost (N=871), 48Gy/15F SIB at 3.2Gy/F (N=874), 53Gy/15F SIB at 3.5Gy/F (N=872). The SIB arms escalate to the regions at highest risk with a modest dose reduction to whole breast distant from tumour, all delivered in 3 weeks.
Endpoint reported here: ipsilateral breast tumour relapse at 10 years. The original sample size calculation assumed a 5% control rate at 5 years. Absolute OS difference and clinician-assessed normal tissue effects also reported.
The 5-year ordering holds at 10 years: the two lower-dose groups sit close together and 53Gy/15F stays highest. Both absolute OS differences vs 40Gy/15F have intervals containing zero.
Moderate/marked effects at 10 years were given as bounds across all randomised groups: <18% breast distortion or shrinkage, <10% induration, <2% telangiectasia, <2% breast oedema. No per-arm split reported in source.
EORTC 22881-10882 established the tumour bed boost itself; IMPORT HIGH asks how to deliver it and whether more dose helps. At 10 years, integration works and escalation does not, the same ranking the 5-year publication (Coles et al. Lancet 2023;401:2124-37) reported.
PRO and photographic assessment stopped at 5 years, so the 10-year toxicity comparison rests on clinician scoring reported as all-group bounds, not per-arm rates. Observed IBTR also ran below the 5% control rate the sample size calculation assumed.
The practical read is fraction count, not dose: a boost folded into 15 fractions removes the separate 16Gy/8F phase with no 10-year IBTR cost, while 53Gy/15F returns nothing. What the trial does not settle is whether the same integration transfers to 5-fraction whole-breast schedules.
CONSORT flow
Mature 10yr follow-up of a 2617-pt randomised trial; extends the 5-year Lancet 2023 read rather than changing it. No formal 10yr non-inferiority margin stated in source.
- Simultaneous integrated boost within 5-fraction whole-breast schedules recruiting Ultra-hypofractioNated Adjuvant Radiotherapy ± sImultaneous Integrated Boost for Low-risk Breast Cancer Patients Phase 2n=65 · primary completion 2025-10 · ultra-hypofx WBI +/- SIB, low-risk, phase 2recruiting Ultra Hypo-fractionated Adjuvant Whole Breast Radiation Therapy With Simultaneous Integrated Boost for Early-Stage Breast Cancer (H-ASSIST) Phase 2n=90 · primary completion 2028-02 · 5-fraction WBI with SIB tumor bed boost, phase 2
- Patient-reported cosmesis beyond 5 years, unmeasured after photographic follow-up ended n=139 · primary completion 2025-12 · 10y registry with cosmesis + QoL assessmentsn=50 · primary completion 2028-09 · cosmesis + PROMs to 60mo after ultra-short WBI/SIB
📚 Sources · 🐦 1 tweet
Day THREE of #ESTRO26 Coverage by OncoAlert 🚨
— OncoAlert (@OncoAlert) May 17, 2026
Ten-year results of the IMPORT HIGH trial (ISRCTN47437448): Dose escalated simultaneous integrated boost radiotherapy in early breast cancer Presented by Charlotte Coles 🇬🇧 #RadOnc ☢️
Ten-year IMPORT HIGH trial data show that a… pic.twitter.com/7RqVy2SrQm
DBCG HYPO
ForNode-negative early breast cancer or DCIS, post-BCS whole-breast RT
24.7% vs 19.5% at 10 yr
HR 0.76 (95% CI 0.62-0.92), p=0.005, favouring 40 Gy/15 fr
TL;DR10yr grade 2-3 breast induration 24.7% (50Gy) vs 19.5% (40Gy), HR 0.76 (0.62-0.92), p=0.005, no recurrence penalty.
The fibrosis separation persists at a decade, 24.7% vs 19.5%, HR 0.76 (0.62-0.92): 40 Gy/15 fr is not merely non-inferior on late morbidity, it is better, with OS numerically higher (93.0% vs 92.1%, p=0.10). For a node-negative or DCIS patient, the residual argument for 25 fractions is gone.
For node-negative invasive breast cancer or DCIS after breast conservation, this supports 40 Gy/15 fr over 50 Gy/25 fr on late induration with no recurrence cost; node-positive and regional nodal irradiation populations were not enrolled and are not addressed. The longer read
The fibrosis separation persists at a decade, 24.7% vs 19.5%, HR 0.76 (0.62-0.92), so 40 Gy/15 fr is superior on late induration rather than merely non-inferior. In node-negative disease or DCIS, whole-breast only, the late-tissue argument for 25 fractions has no support here.

| Endpoint (10-yr) | 50 Gy/25 fr | 40 Gy/15 fr | HR (95% CI), p |
|---|---|---|---|
| Grade 2-3 breast induration | 24.7% | 19.5% | 0.76 (0.62-0.92), p=0.005 |
| Overall survival | 92.1% | 93.0% | 0.81 (0.63-1.04), p=0.10 |
+1 more figure

8 details 5 trials watching
Phase III randomised non-inferiority trial, 1:1, run across Denmark, Norway and Germany from 2009-2014. These are the prespecified 10-year analyses of toxicity, recurrence and survival, at a median follow-up of 12.8 years.
1,882 women with node-negative breast cancer or DCIS. After exclusions (13 and 16), 933 and 936 women were analysed in the two arms, with 917 carried into the morbidity analysis of one arm.
Whole-breast irradiation only: 50 Gy in 25 fractions versus 40 Gy in 15 fractions. No regional nodal irradiation question is posed, and boost details are not reported in the source slides.
Primary: grade ≥2 breast induration at 3 years, requiring two consecutive visits or the final follow-up. Morbidity was scored at years 0, 1, 2, 3, 4, 5 and 10; recurrence and survival are the co-reported 10-year outcomes.
The toxicity endpoint is the positive result here: 10-year grade 2-3 induration 24.7% with 50 Gy vs 19.5% with 40 Gy, HR 0.76 (0.62-0.92), p=0.005. The fibrosis advantage of hypofractionation is durable, not an early-follow-up artefact.
START-B and the UK 10-year hypofractionation data established 40 Gy/15 fr as at least equivalent for control with less normal-tissue effect; DBCG HYPO reproduces that direction in a contemporary node-negative and DCIS population treated 2009-2014, in an era of CT planning and modern systemic therapy rather than the 1990s cohorts.
Breast induration is a clinician-scored endpoint and the source does not state whether assessment was blinded, which matters when the two arms are trivially distinguishable by treatment duration. Locoregional recurrence, distant failure and breast cancer mortality are reported only as 'no significant difference' with no event counts or confidence intervals in the source, so the precision of the non-inferiority claim cannot be judged from these slides.
A 5.2-percentage-point absolute reduction in decade-level grade 2-3 induration is a real cosmetic and symptomatic difference in a population most of whom will never recur. The OS HR of 0.81 (0.63-1.04) is directionally in favour of the shorter schedule but is not significant and should not be read as a survival benefit of hypofractionation.
Randomised phase III, prespecified 10-yr analysis, 12.8-yr median follow-up, primary toxicity endpoint favours 40 Gy/15 fr. Reinforces already-standard moderate hypofractionation rather than changing it.
- How does 40 Gy/15 fr compare with five-fraction schedules on 10-yr fibrosis? n=2100 · primary completion 2029-03 · randomised 1 wk vs 3 wk adjuvant WBI, non-inferiorityrecruiting 5 fr Ultrahypofractionated WBI and SIB for Breast Cancer With Unfavorable Characteristics Phase NAn=458 · primary completion 2029-06 · 26 Gy/5 fr + SIB vs 40.05 Gy/15 fr + SIB, randomisedrecruiting Ultra-Hypofractionated vs Moderate Hypofractionated Radiotherapy for Regional Lymph Nodes in High Risk Breast Cancer Phase NAn=1950 · primary completion 2034-03 · 26 Gy/5 fr vs 40-42.5 Gy/15-16 fr nodal RT
- Does the induration benefit hold with regional nodal irradiation? recruiting Hypofractionated Irradiation At Regional Nodal Area for Breast Cancer Vs Existed Standard Treatment Phase 3n=801 · primary completion 2022-12 · phase 3 hypofx vs conventional RNI, safety endpointactive Hypofractionated vs. Conventional Regional Nodal Radiation Therapy for Patients With Invasive Breast Cancer Phase 2n=805 · primary completion 2030-02 · 3 wk vs 5 wk nodal RT, arm edema and recurrence
- Locoregional recurrence event counts and confidence intervals
📚 Sources · 🐦 1 tweet
Day TWO of #ESTRO26 Coverage by OncoAlert 🚨
— OncoAlert (@OncoAlert) May 17, 2026
10-year Follow-Up of the DBCG HYPO Trial: Breast Induration, Recurrence and Survival After Hypofractionated Whole Breast Irradiation Presented by Hanna Forsberg 🇩🇰 @BOffersen #RadOnc ☢️ #BreastCancer
The DBCG HYPO trial reports… pic.twitter.com/4qf9R3HZwT
HypoG-01
ForBreast cancer receiving adjuvant RT incl. nodal volumes, ESTRO-contoured
118 events / 1260 pts
Median f/u 4.8 yrs; LRR 20/118, iLRR sites in-volume 20/30 (67%)
TL;DR118 first events over 4.8yr median f/u; 67% of LRR sites in-volume, patterns comparable across 40Gy/15fx and 50Gy/25fx.
The actionable number is 20/30 iLRR sites in-volume, with 19/30 nodal and concentrated in levels 1 and 2: failures are happening inside correctly contoured CTVs, not at their edges, so this argues against widening nodal volumes and supports ESTRO contouring as drawn. Per-arm event counts not reported in source.
In node-involved breast cancer planned for adjuvant regional nodal RT, this supports keeping ESTRO-guideline CTVs rather than expanding level 1 to 2 coverage for geographic-miss concern; it does not address volume choice in pts contoured outside those guidelines. The longer read
20/30 iLRR sites were in-volume and 19/30 nodal, mainly levels 1 and 2. Recurrences are inside correctly drawn CTVs, so the fix is not a wider nodal volume, and ESTRO contouring holds under 40 Gy/15 fx. Per-arm counts not reported in source.
19/30 recurrence sites were nodal, concentrated in levels 1 and 2, the levels most affected when axillary dissection is replaced by sentinel-node-only management. Relevant to how much residual nodal risk surgical de-escalation leaves for RT to absorb; the analysis does not stratify by axillary surgery type.

| Event / site | n |
|---|---|
| Isolated distant recurrence | 61 |
| Second malignancy | 37 |
| Isolated locoregional recurrence | 19 |
| Concomitant locoregional recurrence | 1 |
| LRR as first event | 20 / 118 |
| iLRR sites in-volume | 20 / 30 (67%) |
| iLRR sites nodal | 19 / 30 |
+1 more figure

9 details 5 trials watching
Pre-planned secondary analysis of the HypoG-01 phase III trial, analysed ITT. N=1,260, median follow-up 4.8 years. Reported as a patterns-of-failure and dosimetric mapping study, not a re-test of the parent efficacy endpoint.
Randomisation was 40 Gy/15 fractions over 3 weeks vs 50 Gy/25 fractions over 5 weeks, each with a tumour-bed boost. Contouring followed ESTRO guidelines, which is what makes the in-volume/marginal classification interpretable rather than institution-specific.
Primary event was the first oncological event: locoregional recurrence, distant recurrence, or second malignancy. LRR was classified against the CTV as in-volume (within CTV), marginal (outside CTV but ≥50% prescribed dose), or out-of-volume (<50%). Planned dose at each recurrence site was re-estimated on the original planning CT.
118 first events. Distant recurrence and second malignancy dominated (61 and 37); LRR was the least common first event at 20/118. Among 30 iLRR sites, 20 (67%) were in-volume and 19/30 were nodal, mainly levels 1 and 2.
The dosimetric read is retrospective by construction: dose at the recurrence site is estimated on the initial plan CT, so anatomic change and registration error over a median 4.8 years both push sites toward an in-volume label. The event count also caps what can be concluded, since 30 sites split across two arms leaves the "not obviously different" claim underpowered rather than negative.
START-B and FAST-Forward established that moderate and ultra-hypofractionation do not cost local control, but neither mapped recurrence sites against the CTV. The contribution here is geographic rather than actuarial: it tests whether the *volume*, not the *dose per fraction*, is where hypofractionated regional treatment could fail.
A 67% in-volume rate reframes residual LRR as a biology problem, not a coverage problem: pts recurred where dose was delivered. The nodal concentration in levels 1 and 2 is the one signal worth watching, since those are the levels most variably treated when surgical axillary management is de-escalated.
Pre-planned secondary analysis, descriptive only. No per-arm effect size or statistical comparison in source; 30 iLRR sites cannot exclude an arm difference.
- Per-arm LRR site distribution, 40 Gy/15 fx vs 50 Gy/25 fx recruiting Hypofractionated Irradiation At Regional Nodal Area for Breast Cancer Vs Existed Standard Treatment Phase 3n=801 · primary completion 2022-12 · phase 3 hypofx vs conventional RNI, node-positiverecruiting Conventionally Fractionated vs. Hypofractionated Comprehensive Nodal Irradiation for Breast Cancer Using Pencil Beam Scanning Proton Therapy Phase 3n=276 · primary completion 2038-02 · phase 3 3wk vs 5wk comprehensive nodal RT, protons
- Does ultra-hypofractionation shift nodal failure geography? n=768 · primary completion 2029-01 · randomised ultrahypo vs moderate hypo RNI, 4 cohortsrecruiting Ultra-Hypofractionated vs Moderate Hypofractionated Radiotherapy for Regional Lymph Nodes in High Risk Breast Cancer Phase NAn=1950 · primary completion 2034-03 · 26Gy/5fx vs 40Gy/15fx RNI, n=1950, recurrence f/u
- Level 1-2 coverage after sentinel-node-only axillary management n=205 · primary completion 2027-12 · RNI volume tailored to SLND-alone vs SLND+ALND
📚 Sources · 🐦 1 tweet
Day TWO of #ESTRO26 Coverage by OncoAlert 🚨
— OncoAlert (@OncoAlert) May 16, 2026
Patterns of locoregional and distant recurrence and dosimetric analysis in the HypoG-01 phase III trial Presented by Louis Munschi 🇫🇷 #RadOnc ☢️
In the HypoG-01 phase III trial (1260 patients, median follow-up 4.8 years), 118… pic.twitter.com/ogARInu0fB
Tumour bed boost after BCS+WBRT (Dutch cohort)
ForPost-BCS invasive breast cancer receiving WBRT, boost decision pending
TL;DR10yr IBTR 1.2% with 0-2 risk factors regardless of boost, supporting boost omission in the modern systemic era.
The decision this moves is boost omission, and the number that moves it is 10yr IBTR 1.2% in the 0-2 risk-factor group whether or not a boost was given, on 15,085 vs 13,845 pts. Note the ≥3 group ran higher WITH boost (3.3% vs 2.7%), which is allocation bias, not boost harm. Boost dose and fractionation are not in the source.
In a post-BCS patient over 40 with grade 1-2, hormone-receptor-positive disease receiving guideline-concordant systemic therapy, this supports omitting the tumour bed boost; it does not resolve the boost question for pts carrying three or more risk factors. The longer read
The omission decision rests on 10yr IBTR of 1.2% in the 0-2 risk-factor group with and without boost (15,085 vs 13,845 pts). The ≥3 stratum ran higher WITH boost (3.3% vs 2.7%), a signature of risk-based allocation rather than boost harm. Boost dose and fractionation are absent from the source.

| Risk factors | N no boost | N boost | 5yr no boost | 5yr boost | 10yr no boost | 10yr boost |
|---|---|---|---|---|---|---|
| 0-2 | 15,085 | 13,845 | 0.6% | 0.7% | 1.2% | 1.2% |
| ≥ 3 | 149 | 733 | 1.3% | 2.9% | 2.7% | 3.3% |
| Uncertain | 592 | 944 | 0.8% | 3.3% | 1.4% | 3.6% |
+2 more figures


9 details
Population-based Dutch cohort from the Netherlands Cancer Registry linked to pathology, on behalf of the DBRT group. Treatment years 2012-2016, follow-up to 10 years. Observational, no randomisation and no adjusted comparison reported in source.
Breast-conserving treatment with or without an RT boost, N=31,348 across the three risk strata. Stratification is by a count of five risk factors: age ≤40, grade 3, triple-negative, guideline-indicated systemic therapy not adequately given, and no pCR after neoadjuvant chemo in TNBC or HER2+.
Whole-breast RT with or without a tumour bed boost. Boost dose, fractionation, technique (photon vs electron vs SIB) and the WBRT schedule are not reported in the source slides, which limits transfer to a specific departmental protocol.
Primary: ipsilateral breast tumour recurrence (IBTR), histologically confirmed, identified by an algorithm over pathology report codes and free text. Reported as cumulative incidence at 5 and 10 years by risk-factor count. Benchmarked against the Assisi thresholds: omission acceptable at <3% 10yr IBTR with boost, <6% without.
IBTR was low in every stratum. The only cell crossing an Assisi threshold was ≥3 risk factors treated with a boost at 10 years, and even there the no-boost value in the same stratum was lower.
EORTC 22881-10882 established that a boost roughly halves IBTR, and that trial's control-arm event rates were an order of magnitude above these. IMPORT HIGH and the 2024 Assisi think tank both moved the field toward de-escalating or restricting the boost; this cohort supplies the contemporary absolute rates those recommendations assumed but could not show.
Boost was allocated by guideline-based risk, so the boost groups are adversely selected and the raw contrast understates any boost effect; the higher rate in the ≥3 boost group is the visible signature of that confounding. The ≥3 no-boost cell holds only 149 pts, and the 'uncertain' stratum (592 / 944) shows a boost-no-boost gap wide enough to suggest unmeasured risk is driving allocation there too.
The finding is about absolute rather than relative benefit: a preserved 50% relative reduction applied to a 1.2% 10-year event rate is not worth five extra fractions and a fibrosis penalty. What the cohort cannot say is whether the boost is the reason those low-risk rates are low, since roughly half the low-risk group received one.
Registry cohort, no randomisation and no adjusted effect estimate; boost allocation confounded by risk. Supports the direction already set by IMPORT HIGH and Assisi thresholds.
- Which ≥3 risk-factor subgroups actually benefit from a boost
- Whether boost omission holds under randomised testing in low-risk pts
- Boost dose and technique used across this cohort
📚 Sources · 🐦 1 tweet
Day TWO of #ESTRO26 Coverage by OncoAlert 🚨
— OncoAlert (@OncoAlert) May 16, 2026
Is a boost to the tumour bed still indicated after breast-conserving surgery and whole-breast radiotherapy in the era of modern systemic therapy? Presented by Femke Froklage 🇳🇱 #RadOnc ☢️
We aimed to identify a subgroup of breast… pic.twitter.com/RqK5r9XPqW
DIREKHT
ForResected HNSCC referred for post-operative RT
TL;DRDe-escalated post-op HNSCC RT: contralateral neck sparing and primary CTV to 56 Gy in selected pts; no outcome numbers in source tweet.
The two levers named are the ones that gate post-op HNSCC RT morbidity: contralateral neck omission and a 56 Gy primary CTV rather than standard higher-dose coverage. Which pts qualified is the whole question, and the source text does not give the selection criteria or any control or toxicity numbers.
Both levers are RT-side decisions: whether to cover the contralateral neck electively, and whether 56 Gy suffices for the primary CTV in selected post-op pts. The source names the approach but gives no selection rule and no control or toxicity numbers, so it flags a trial to read rather than a volume or dose change to adopt.
6 details
Two de-escalation levers reported in source: contralateral neck sparing in a specified subgroup, and reduction of the primary CTV dose to 56 Gy. Fractionation, technique, and the dose to involved or high-risk volumes are not stated in the source text.
Described as a trial, but phase, randomisation, N, sites, and follow-up are not stated in the source tweet.
No primary endpoint, effect size, or toxicity result reported in source. The tweet is commentary on the trial's approach, not its results.
Everything that would let a reader act on this is missing from the source: the selection rule for contralateral neck omission, the comparator, and any locoregional control or late-toxicity figures. A de-escalation result is only interpretable against its non-inferiority margin, which is not given.
Source is a single commentary tweet with no design, N, endpoint, or effect size. Nothing to classify beyond the de-escalation concept.
- Which pts qualify for contralateral neck sparing post-operatively
- Whether 56 Gy primary CTV holds locoregional control vs standard dose
📚 Sources · 🐦 1 tweet
There are tremendous opportunities to improve post-operative radiotherapy in HNSCC. The DIREKHT trial is an excellent example of such work, in which they spared the contralateral neck in a specified group of patients and/or reduced the primary CTV dose to 56 Gy.
— David Sher (@DavidSherMD) May 16, 2026
The details… https://t.co/7W84LYIofR