Practice-changing
DeLLphi-305 NCT06211036
ForES-SCLC, no progression after 1L platinum-etoposide + durvalumab, ECOG 0-1
HR 0.42
95% CI 0.32-0.54, P<0.001; mOS 21.1 vs 12.7 mo
TL;DRmOS 21.1 vs 12.7 mo, HR 0.42 (0.32-0.54), adding tarlatamab to durvalumab 1L maintenance in ES-SCLC after chemo-IO induction.
Asymptomatic untreated brain mets were eligible and brain/liver mets were a stratification factor, so a cranial-disease subgroup read should exist; it is not in the source. The source also does not state whether consolidative thoracic RT or PCI was permitted, which gates how this maintenance backbone integrates with RT consolidation in ES-SCLC.
In ES-SCLC with no progression after 4 cycles of platinum-etoposide + durvalumab and ECOG 0-1, including asymptomatic brain mets, this supports adding tarlatamab to durvalumab maintenance; it does not inform pts who progressed on induction or ECOG ≥2. The longer read
Adds a BiTE to durvalumab maintenance with an OS HR of 0.42 and mOS 21.1 vs 12.7 mo, moving tarlatamab from later-line into 1L maintenance for induction nonprogressors. The post-dose monitoring requirement (1-2h, 6-8h in some regions) is an operational cost to plan for; AE rates are not in the source.

| Metric | Tarlatamab + Durvalumab (n = 282) | Durvalumab (n = 281) |
|---|---|---|
| Median OS, mo (95% CI) | 21.1 (20.8-NE) | 12.7 (11.2-14.8) |
| Median FU, mo | 15.9 | 16.1 |
| HR (95% CI); P | 0.42 (0.32-0.54); P < 0.001 | ref |
+2 more figures

10 details 1 trial watching
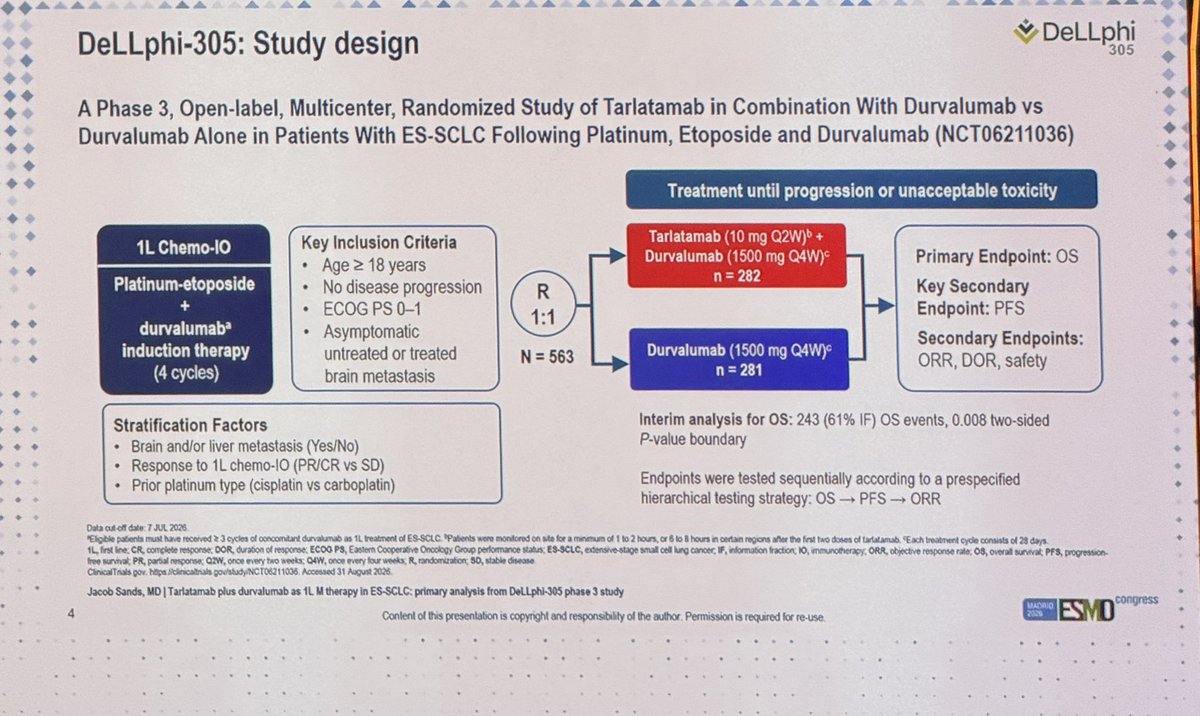
Phase 3, open-label, multicenter, randomized 1:1, N=563. OS interim analysis at 243 events (61% IF), two-sided boundary 0.008. Data cutoff 7 Jul 2026.
ES-SCLC after 4 cycles platinum-etoposide + durvalumab induction with no disease progression, ECOG PS 0-1, age ≥18. Asymptomatic untreated or treated brain mets allowed.
Tarlatamab 10 mg Q2W + durvalumab 1500 mg Q4W vs durvalumab 1500 mg Q4W alone, 28-day cycles, until progression or toxicity. On-site monitoring 1-2h (6-8h in some regions) after early tarlatamab doses.
Primary: OS. Key secondary: PFS. Secondary: ORR, DOR, safety. Tested hierarchically OS → PFS → ORR.
mOS 21.1 vs 12.7 mo, HR 0.42 (0.32-0.54), P<0.001; PFS 7.4 vs 1.9 mo, HR 0.34 (0.28-0.42); ORR 26% vs 4%.
| Endpoint | Tarlatamab + durvalumab | Durvalumab | Effect |
|---|---|---|---|
| Median PFS | 7.4 mo | 1.9 mo | HR 0.34 (0.28-0.42), P<0.001 |
| ORR | 26% | 4% | n/a |
Control arm is the current chemo-IO maintenance standard established by CASPIAN-era durvalumab, so the comparator is contemporary. Tarlatamab previously moved into later lines (DeLLphi-304); this trial tests it earlier, in the maintenance window.
Efficacy stop at 61% IF risks an inflated HR; median FU ~16 mo leaves the OS tail unknown. No safety data in source, and thoracic RT/PCI permissibility not stated.
A BiTE added at the point of maximal disease control nearly halves the death hazard over durvalumab alone. Unsettled: toxicity cost, durability beyond the interim, and integration with consolidative RT.
CONSORT flow
Randomized phase 3, OS primary met at prespecified interim boundary, labeled primary analysis; source calls it a game-changer. Safety data absent from source.
- Role of consolidative thoracic RT alongside tarlatamab maintenance
- OS durability with follow-up beyond the interim analysis
- Benefit and safety in pts with brain metastases n=35 · primary completion 2029-02 · ph2 tarlatamab intracranial efficacy, active SCLC brain mets
📚 Sources · 🐦 1 tweet
💥Game-changer in small cell #lungcancer! #ESMO26 LBA3 DeLLphi-305: Tarlatamab + durvalumab vs durvalumab 1L maintenance in ES-SCLC (n=563) after chemo-IO. Median OS ⬆️ 21.1 vs 12.7 mo (HR 0.42), PFS ⬆️7.4 vs 1.9 mo (HR 0.34), ORR 26% vs 4%. ☢️44% of pts still on T+D due to… pic.twitter.com/zwBot7Pt3N
— Shankar Siva (@_ShankarSiva) October 24, 2026
30 Gy vs 40 Gy consolidative RT, limited-stage DLBCL
ForStage I-II DLBCL, CR/CRu after anthracycline-based chemo ± rituximab
90.5% vs 87.2%
HR 0.87, 95% CI 0.59-1.28; one-sided P = 0.0013 for non-inferiority
TL;DR5-yr PFS 90.5% (30 Gy) vs 87.2% (40 Gy), HR 0.87 (0.59-1.28), non-inferiority met in stage I-II DLBCL in CR after chemo.
The local-regional read backs the PFS headline: locoregional recurrence did not differ between 30 Gy and 40 Gy involved-site/field RT, though no rates are given in the source text. Toxicity, including second malignancies, was also comparable at 7.2 years median f/u, so the late-effect gain from de-escalation is inferred, not shown.
In stage I-II DLBCL in CR/CRu after anthracycline-based chemo with or without rituximab, this supports 30 Gy over 40 Gy as the consolidative dose; it does not extend to pts short of CR, and it does not test omitting RT. The longer read
The local-regional read backs the PFS headline: locoregional recurrence did not differ between 30 Gy and 40 Gy involved-site/field RT, though no rates are given in the source text. Toxicity, including second malignancies, was also comparable at 7.2 years median f/u, so the late-effect gain from de-escalation is inferred, not shown.
12 details 1 trial watching
Multicenter, open-label, non-inferiority phase 3, randomized 1:1. 432 pts enrolled April 14, 2010 to July 1, 2019; median follow-up 7.2 years. Non-inferiority margin not reported in source.
Newly diagnosed stage I-II DLBCL achieving CR/CRu after anthracycline-based chemo with/without rituximab. Age criterion printed as '=15 years' in the portal text. Bulk, IPI and PET status at response not reported in source.
30 Gy vs 40 Gy consolidative involved-site/field RT. Fraction size, technique and the split between involved-site and involved-field volumes are not reported in source.
Primary: 5-year PFS, tested for non-inferiority of 30 Gy. Also reported: OS, locoregional recurrence, acute and late toxicity including second malignancies.
Primary endpoint met (table). OS and locoregional recurrence showed no difference between arms; the source gives no rates or HRs for either.
| Endpoint | 30 Gy | 40 Gy | Effect |
|---|---|---|---|
| Randomized | n=216 | n=216 | 1:1 |
| ITT analysis | 212 | 213 | n/a |
| 5-yr PFS (95% CI) | 90.5% (86.5-94.7) | 87.2% (82.7-91.9) | HR 0.87 (0.59-1.28), one-sided P = 0.0013 for non-inferiority |
Acute and late toxicities, including second malignancies, were comparable between arms. No rates or grades reported in source, so no measured toxicity advantage for 30 Gy.
The source states no prior randomized trial compared these two doses in DLBCL specifically. The UK NHL dose-reduction RCT (Lowry et al.) asked a similar de-escalation question in aggressive NHL more broadly, and ILROG guidance already favors the lower consolidative dose after CR, so this result is concordant with that direction.
Enrollment spans 2010 to 2019 with rituximab optional and response graded as CR/CRu, so systemic therapy and response assessment may not match current PET-adapted practice. Mixed involved-site/field volumes are not broken out. Abstract only: no event counts, no margin.
With PFS near 90% in both arms and locoregional recurrence no different, the higher dose bought no measurable disease control in pts already in CR. What the trial does not settle is whether the lower dose reduces late effects (not shown at 7.2 years) and whether any RT is needed after a PET-negative response.
CONSORT flow
Randomised phase 3, prespecified non-inferiority primary met at 7.2-year median f/u; source calls 30 Gy the new standard. Caveats: margin and fractionation unreported, rituximab optional.
- Can consolidative RT be omitted after PET-negative CR in limited-stage DLBCL?
- Does 30 Gy reduce late toxicity or second malignancies with longer follow-up?
- Is a dose below 30 Gy adequate after CR to rituximab-containing chemo? active Dose-Reduced Consolidation Radiation Therapy in Patients With Diffuse Large B-cell Lymphoma Phase NAn=243 · primary completion 2025-07 · 30 Gy to 20 Gy consolidation RT after PET-neg R-chemo
📚 Sources · 📄 1 paper
Abstract
BIG 3-07/TROG 07.01 NCT00470236
ForNon-low-risk DCIS after BCS, ≥1 mm clear radial margins
TL;DRTumour bed boost after WBI in resected non-low-risk DCIS: 5-yr freedom from LR 97.1% vs 92.7%, HR 0.47 (0.31-0.72), p<0.001.
The boost gain held on a 42.5 Gy/16 fx WBI backbone as well as 50 Gy/25 fx, so boost is not tied to conventional fractionation. The cost is G2+ induration 14% vs 6%, which is the number to weigh when deciding boost vs omission after ≥1 mm margins in non-low-risk DCIS.
In a woman with resected non-low-risk DCIS and ≥1 mm margins planned for WBI, this supports offering a 16 Gy/8 fx boost against a higher G2+ induration and pain rate; it does not address low-risk DCIS or pts with <1 mm margins. The longer read
Boost 16 Gy/8 fx cut LR hazard (HR 0.47) on both 50 Gy/25 fx and 42.5 Gy/16 fx WBI backbones, so it transfers to hypofractionated practice. The trade is G2+ induration 14% vs 6%, which frames the boost-or-omit conversation in non-low-risk DCIS with ≥1 mm margins.
7 details 4 trials watching
International randomised, unmasked, factorial phase 3, 136 centres across six trial groups in 11 countries. N=1608 accrued 2007-2014; median f/u 6.6 yr.
Women ≥18y with unilateral, histologically proven non-low-risk DCIS after breast-conserving surgery with ≥1 mm clear radial margins.
WBI either 50 Gy/25 fx (n=831) or 42.5 Gy/16 fx (n=777), randomised in a 4-arm factorial or chosen per centre. Boost 16 Gy/8 fx to tumour bed after WBI.
Primary: time to local recurrence. Toxicity reported as G2+ breast pain and induration.
Boost raised G2+ breast pain (14% vs 10%, p=0.003) and G2+ induration (14% vs 6%, p<0.001).
Older DCIS trials (NSABP B-17, EORTC 10853) established WBI after lumpectomy but did not test boost; the EORTC boost trial tested it only in invasive disease. This is the first randomised boost evidence in DCIS.
The fractionation-sensitivity result is not reported in the source abstract, so hypofractionation non-inferiority in DCIS cannot be read from it. Toxicity is assessor-unmasked, and no survival endpoint is reported.
A boost roughly halves local recurrence hazard in non-low-risk DCIS at a real cost in G2+ breast morbidity. It does not settle which non-low-risk subsets carry enough baseline risk to justify that trade.
CONSORT flow
Adequately powered phase 3 RCT, primary endpoint hit with 6.6-yr median f/u; first randomised boost data in DCIS. Qualified by unmasked design and added G2+ toxicity.
- Which non-low-risk DCIS subsets derive most boost benefit
- Local recurrence with hypofractionated vs conventional WBI in DCIS n=301 · primary completion 2020-11 · randomised hypo vs standard WBI, DCIS eligiblen=72 · primary completion 2026-12 · 1-wk vs 3.1-wk WBI, DCIS eligible, local control EP
- Boost role with ultra-hypofractionated or partial-breast RT recruiting Ultra Hypo-fractionated Adjuvant Whole Breast Radiation Therapy With Simultaneous Integrated Boost for Early-Stage Breast Cancer (H-ASSIST) Phase 2n=90 · primary completion 2028-02 · 5-fx WBI + SIB tumour bed boost, DCIS includedrecruiting 5 vs. 9-day Course of Whole Breast Radiotherapy With Boost for Early-stage Breast Cancer Phase 2n=144 · primary completion 2030-05 · randomised 5 vs 9 day WBI with boost, DCIS eligible
📚 Sources · 📄 1 paper
Abstract
DBCG Skagen Trial 1
ForHigh-risk breast cancer with an indication for locoregional (nodal) radiotherapy
8.0% vs 9.4%
OR 0.84 (95% CI 0.62-1.14), P=.27; within +5pp NI margin
TL;DR3yr lymphedema 8.0% (40Gy/15fx) vs 9.4% (50Gy/25fx), OR 0.84 (0.62-1.14), noninferior; no recurrence or mortality differences at 8yr.
The lymphedema signal that kept 50Gy/25fx alive for nodal volumes does not appear: 8.0% vs 9.4% at 3yr, OR 0.84 (0.62-1.14). Locoregional recurrence HR 0.96 (0.62-1.51) says the shorter course does not trade control for convenience, so 15 fractions becomes defensible when the nodes are in the field.
In high-risk breast cancer needing nodal irradiation, this supports 40Gy/15fx over 50Gy/25fx on both arm morbidity and locoregional control; it does not speak to pts needing a boost regimen or reconstruction subgroups the abstract does not break out. The longer read
The morbidity objection to nodal hypofractionation does not hold: lymphedema 8.0% vs 9.4% at 3yr, OR 0.84 (0.62-1.14), with locoregional recurrence HR 0.96 (0.62-1.51). 40Gy/15fx to the full locoregional volume becomes the defensible default, with SIB and reconstruction still untested here.
Lymphedema is the shared surgical and radiation morbidity after axillary management, and fraction size is now off the list of drivers: 8.0% with 40Gy/15fx vs 9.4% with 50Gy/25fx at 3yr. Counseling about arm morbidity after nodal surgery plus RT should not attribute risk to the shorter course.
8 details 5 trials watching
Phase III noninferiority RCT, 17 centers, accrual 2015-2021. ITT cohort n=2,908 (1,444 at 50Gy, 1,464 at 40Gy). Accrual continued until 3-year lymphedema estimates were reported in 1,012 patients.
High-risk breast cancer with an indication for locoregional radiotherapy, the population where nodal coverage has kept 25 fractions standard in Denmark. Median age 57 (range 23-86).
Standard arm 50Gy/25fx, experimental arm 40Gy/15fx, both delivered to the locoregional volume rather than breast or chest wall alone. That target volume is the whole point: it is where the morbidity concern lives.
Primary: arm lymphedema at 3 years, with an assumed 10% incidence under 50Gy/25fx and noninferiority predefined as maximum 5 percentage points excess. Cancer endpoints (locoregional recurrence, distant recurrence, breast cancer mortality, all-cause mortality) were assessed within 8 years.
Lymphedema 8.0% vs 9.4%, OR 0.84 (0.62-1.14), P=.27, comfortably inside the margin. Cancer-outcome HRs are tabulated above and show no difference by random assignment.
| Endpoint | HR | 95% CI |
|---|---|---|
| Locoregional recurrence | 0.96 | 0.62 to 1.51 |
| Distant recurrence | 1.10 | 0.89 to 1.37 |
| BC mortality | 1.25 | 0.93 to 1.66 |
| All-cause mortality | 1.08 | 0.85 to 1.36 |
The UK hypofractionation programme (START A/B, then FAST-Forward) established 40Gy/15fx and shorter for breast and chest wall, but node-positive patients receiving comprehensive regional coverage were a small fraction, which left the nodal question open. Skagen 1 tests exactly that gap prospectively with morbidity as the primary endpoint.
Median lymphedema follow-up of 4.1 years captures the 3-year endpoint but not the later plateau, and the abstract reports no brachial plexopathy, shoulder, cardiac, or pulmonary late toxicity. The BC mortality HR 1.25 (0.93-1.66) runs the wrong way with a CI that does not exclude harm; the trial was sized for lymphedema, not survival.
The trial removes the specific objection that blocked hypofractionated nodal RT rather than merely adding another positive fractionation result. It does not settle very-long-term arm and shoulder function, nor whether the same holds with a simultaneous integrated boost or in reconstructed chest walls.
CONSORT flow
Phase III, prespecified noninferiority margin met on the morbidity endpoint that blocked nodal hypofractionation, with 8yr recurrence and mortality HRs showing no difference.
- Does 40Gy/15fx hold with a simultaneous integrated boost? active Hypofractionation With Simultaneous Integrated Boost vs. Standard Fractionation in Early Breast Cancer Phase NAn=2324 · primary completion 2019-01 · phase 3 hypofx SIB vs standard fx, n=2324n=132 · primary completion 2026-03 · 40.05Gy/15fx + SIB, 4y fibrosis endpointrecruiting 5 fr Ultrahypofractionated WBI and SIB for Breast Cancer With Unfavorable Characteristics Phase NAn=458 · primary completion 2029-06 · randomised vs 40.05Gy/15fx + 48Gy SIB control arm
- Lymphedema and shoulder function beyond 5 years
- Safety in immediate breast reconstruction n=20 · primary completion 2025-12 · post-surgical complications after RT then immediate reconactive Hypofractionated Regional Nodal Irradiation Clinical Trial for Women With Breast Cancer Phase NAn=137 · primary completion 2026-04 · hypofx RNI cohort stratified by post-mastectomy recon
📚 Sources · 📄 1 paper
Abstract
STAMPEDE abiraterone ± enzalutamide in high-risk non-metastatic prostate cancer (meta-analysis) NCT00268476
ForHigh-risk non-metastatic prostate cancer (N+ or high-risk N0) starting ADT
HR 0.53
95% CI 0.44-0.64, p<0.0001; 6-yr MFS 82% vs 69%
TL;DRMFS HR 0.53 (0.44-0.64) and OS HR 0.60 (0.48-0.73) adding 2yr abiraterone ± enzalutamide to ADT in high-risk non-metastatic prostate cancer.
The MFS benefit held whether or not RT was planned: HR 0.54 (0.44-0.67) with RT vs 0.51 (0.34-0.76) without, interaction p=0.67. So abiraterone adds to prostate RT and does not stand in for it. The RT was 74 Gy/37 fx to prostate + SVs, and the source does not describe pelvic nodal fields for the 39% who were N+.
In N+ or high-risk N0 non-metastatic prostate cancer starting long-course ADT with prostate RT, this supports 2 yr of abiraterone + prednisolone without enzalutamide. It does not extend to men treated with prostatectomy, who were not studied. The longer read
The abiraterone benefit is independent of planned RT (MFS HR 0.54 with vs 0.51 without, interaction p=0.67), and RT was mandated for N0. It stacks on 74 Gy/37 fx to prostate + SVs with 3 yr ADT. The source does not describe pelvic nodal fields, and only 71% of N+ pts had RT planned.
Two years of abiraterone + prednisolone added to 3 yr ADT improved OS (HR 0.60). Adding enzalutamide gave no extra MFS benefit (interaction HR 1.02) and raised grade 3+ AEs to 58% vs 32%. Enzalutamide adds cost and toxicity without added efficacy.
Also covered Oct 24
11 details 4 trials watching
Prespecified IPD meta-analysis of two open-label, randomised (1:1) phase 3 trials in the STAMPEDE platform, run at 113 UK and Swiss sites. N=1974, randomised 2011-2016, with no overlapping controls. Median follow-up was 72 mo.
High-risk non-metastatic prostate cancer on conventional imaging: N+, or N0 with at least two of T3/T4, Gleason 8-10, or PSA ≥40 ng/mL. Pts relapsing with high-risk features were also eligible. Median age was 68, and 774 (39%) were node-positive. Clinically significant cardiovascular disease was excluded.
All pts received 3 yr ADT. The combination arm added abiraterone 1000 mg + prednisolone 5 mg daily for 2 yr, and the second trial also added enzalutamide 160 mg. If RT was omitted, treatment could continue until progression.
Per local guidelines: 74 Gy/37 fx to prostate + SVs or a hypofractionated equivalent. RT was mandated for N0 and encouraged for N+. RT was planned in 85% overall: 99% of N0, 71% of N+ and 7% of previously treated pts.
Primary: MFS, which was changed from OS before any efficacy inspection and approved by the steering committee on Dec 2, 2019. Secondary endpoints were OS, prostate cancer-specific survival, biochemical failure-free survival, PFS and toxicity.
Both trials showed the benefit on their own: MFS HR 0.54 in the abiraterone trial and 0.53 in the abiraterone + enzalutamide trial, with no between-trial heterogeneity (I² p=0.90).
| Endpoint | Combination | Control | HR (95% CI) |
|---|---|---|---|
| MFS (1°) | 6-yr 82% | 6-yr 69% | 0.53 (0.44-0.64), p<0.0001 |
| OS | 6-yr 86% | 6-yr 77% | 0.60 (0.48-0.73), p<0.0001 |
| Prostate cancer-specific survival | median not reached | median not reached | 0.49 (0.37-0.65), p<0.0001 |
| Biochemical failure-free survival | median not reached | median 86 mo | 0.39 (0.33-0.47), p<0.0001 |
| PFS | median not reached | median not reached | 0.44 (0.36-0.54), p<0.0001 |
| Subgroup | HR (95% CI) | p interaction |
|---|---|---|
| RT planned: yes | 0.54 (0.44-0.67) | 0.67 |
| RT planned: no | 0.51 (0.34-0.76) | 0.67 |
| N0 | 0.60 (0.46-0.78) | 0.22 |
| N+ | 0.49 (0.38-0.64) | 0.22 |
| WHO PS 0 | 0.47 (0.38-0.58) | 0.00656 |
| WHO PS 1-2 | 0.86 (0.58-1.28) | 0.00656 |
| NSAID/aspirin: no | 0.62 (0.51-0.77) | 0.0052 |
| NSAID/aspirin: yes | 0.32 (0.21-0.48) | 0.0052 |
| AE | Abi trial: combo | Abi trial: control | Abi+enza trial: combo | Abi+enza trial: control |
|---|---|---|---|---|
| Any grade 3+ | 37% | 29% | 58% | 32% |
| Hypertension | 5% | 1% | 14% | 2% |
| ALT increase | 6% | <1% | 13% | 1% |
Grade 3+ AEs in the first 24 mo were 37% vs 29% in the abiraterone trial and 58% vs 32% in the abiraterone + enzalutamide trial. The main drivers were hypertension and ALT elevation. There were 7 grade 5 events, all in the combination arms.
The backbone is long-course ADT with prostate RT, which the authors frame as standard for this population. Adding enzalutamide to abiraterone also gave no extra benefit here, consistent with the modest rPFS gains and absent OS benefit the authors cite from that combination in mCRPC.
Staging used conventional imaging only. Toxicity was reported only for the first 2 yr, and data on subsequent therapy are unreliable. Heterogeneity by PS 1-2 (HR 0.86, 0.58-1.28) makes the benefit less certain in less fit men.
Abiraterone intensification improved MFS and OS on top of ADT whether or not RT was planned. Enzalutamide added toxicity without extra efficacy. Open questions are the right duration, the benefit after prostatectomy, and the benefit in PSMA-staged disease, none of which were tested.
Pooled IPD from two randomised phase 3 trials, 72-mo f/u, with both MFS and OS improved. The OS→MFS switch was prespecified before efficacy was seen. Authors call it a new standard.
- Is 2 years the optimal abiraterone duration? recruiting Reduced Length of ADT and ARTA With XRT in High-Risk Prostate Cancer (RELAX): A Randomised Trial Phase 2n=206 · primary completion 2035-01 · 9mo ADT + 6mo ARTA vs 2y ADT with RT, high-risk N0M0
- Benefit after radical prostatectomy untested recruiting Treating Prostate Cancer That Has Come Back After Surgery With Apalutamide and Targeted Radiation Based on PET Imaging Phase 3n=804 · primary completion 2032-12 · post-RP BCR: apalutamide+abiraterone added to SRT+ADT
- Benefit in relapse after prior local therapy underrepresented active Finite Androgen Ablation With or Without Abiraterone Acetate and Prednisone in Treating Patients With Recurrent Prostate Cancer Phase 2n=310 · primary completion 2027-02 · recurrent PCa: finite ADT ± abiraterone, randomisedrecruiting Treating Prostate Cancer That Has Come Back After Surgery With Apalutamide and Targeted Radiation Based on PET Imaging Phase 3n=804 · primary completion 2032-12 · phase 3 ARSI intensification in post-RP BCR
📚 Sources · 📄 1 paper
SUPREMO
ForPost-mastectomy pT1-2N1, pT3N0, or pT2N0 grade 3/LVI+ breast cancer
81.4% vs 81.9%
HR 1.04, 95% CI 0.82-1.30, P=0.80; primary endpoint not met
TL;DR10yr OS 81.4% vs 81.9% (HR 1.04, 0.82-1.30, p=0.80): PMRT omission safe in intermediate-risk pN0-pN1 post-mastectomy.
The RT read is the local-control trade: 1.1% vs 2.5% chest-wall recurrence, 29 events total, bought with 40-50 Gy to the chest wall in a population where OS was flat at 10 years. Nodal volumes were not routinely treated (SCF 97/808), so this speaks to chest wall alone, not to regional nodal irradiation.
In a pT2N1 or pT3N0 mastectomy patient who has completed modern adjuvant systemic therapy, this supports discussing PMRT omission with an absolute chest-wall recurrence trade under 2 points; it does not address regional nodal irradiation or pN2-N3 disease. The longer read
The trade is 1.1% vs 2.5% chest-wall recurrence from 40-50 Gy, with 10yr OS flat (HR 1.04). Nodal volumes were not routinely treated (SCF 97/808, IMC 12/808), so this licenses chest-wall omission specifically, not regional nodal omission, and moves PMRT here into a morbidity-versus-local-control discussion.
The systemic backbone (85% chemo, 79% endocrine, 19% trastuzumab) is what makes the null interpretable: with modern adjuvant therapy the residual chest-wall event rate is 2.5% untreated, leaving no room for RT to alter survival. Referral for PMRT in this band becomes optional rather than expected.
After mastectomy plus an axillary procedure in pT1-2N1, pT3N0, or pT2N0 grade 3/LVI disease, expected PMRT no longer carries a survival argument (HR 1.04), which changes the reconstruction conversation at the time of surgery since a planned reconstruction need not be sequenced around anticipated chest-wall irradiation.
Also covered Jul 9
9 details
International phase 3 randomized trial (BIG 2-04 MRC/EORTC SUPREMO), 125 UK sites plus 27 European and 21 international sites. N=1607 ITT (808 CWI, 799 no CWI), randomized August 2006 to April 2013, database lock June 2024. Median follow-up 9.6 years.
"Intermediate-risk" post-mastectomy disease: pT1N1, pT2N1, pT3N0, or pT2N0 with grade 3 and/or LVI. All had mastectomy, an axillary procedure, and systemic therapy. Baseline systemic exposure: 85% chemotherapy, 79% endocrine, 19% trastuzumab.
Chest wall 40 to 50 Gy in the irradiation arm. Nodal volumes were not part of the randomized question: supraclavicular fossa treated in only 97/808 irradiated patients, internal mammary chain in 12/808. Twelve patients in the no-irradiation arm received SCF treatment.
Primary: overall survival at 10 years. Secondary: chest-wall recurrence, regional recurrence, disease-free survival, distant metastasis-free survival, cause of death, radiation-related adverse events.
The historic case for postmastectomy RT in node-positive disease rests on the EBCTCG overview, where the locoregional-control gain translated into a mortality benefit. SUPREMO tests that inheritance in the 1-3 node and high-risk node-negative band under contemporary systemic therapy and finds the recurrence signal preserved (HR 0.45) but the survival signal absent (HR 1.04).
The chest-wall recurrence benefit rests on 29 events total with a CI upper bound of 0.99, so the point estimate is unstable. Accrual ran 2006-2013, predating routine dual HER2 blockade, extended adjuvant CDK4/6 inhibition, and current genomic risk stratification, all of which lower the baseline recurrence rate this trial was powered against.
A flat OS with a halved chest-wall recurrence is the signature of a locoregional intervention operating below the threshold where local control converts into survival. At 1.1% vs 2.5%, the absolute chest-wall event rate in both arms is low enough that no plausible salvage-to-mortality pathway could move a 10-year OS curve. The result reframes PMRT in this band as a local-control decision to be weighed against RT morbidity, not as a survival decision.
| Endpoint | CWI | No CWI | HR (95% CI) |
|---|---|---|---|
| Overall survival (1°) | 81.4% | 81.9% | 1.04 (0.82-1.30), p=0.80 |
| Disease-free survival | 76.2% | 75.5% | 0.97 (0.79-1.18) |
| Distant MFS | 78.2% | 79.2% | 1.06 (0.86-1.31) |
| Chest-wall recurrence | 9 (1.1%) | 20 (2.5%) | 0.45 (0.20-0.99) |
CONSORT flow
Adequately powered phase 3, prespecified OS primary, 9.6yr median follow-up, modern systemic backbone. Supports omitting PMRT in a population where guidelines still often recommend it.
- Does regional nodal irradiation carry the same null in pN1 disease
- Which biomarker or genomic subgroup still benefits from chest-wall RT
- Late cardiac and second-malignancy burden of the irradiated arm
📚 Sources · 📄 1 paper
Abstract
RASolute 302
ForPreviously treated metastatic pancreatic cancer, RAS G12-mutant
TL;DRMedian OS 13.2 vs 6.6 mo, HR 0.40 (95% CI 0.30-0.54), P<0.001, daraxonrasib over chemo in previously treated RAS G12 metastatic pancreatic cancer.
In previously treated metastatic pancreatic cancer with a RAS G12 mutation, this supports daraxonrasib over investigator's choice chemotherapy on OS; it does not extend to treatment-naive or non-metastatic disease.

| Population | Arm | N | Events, n (%) | mOS, mo (95% CI) | HR for death (95% CI) |
|---|---|---|---|---|---|
| RAS G12 | Daraxonrasib | 228 | 72 (32) | 13.2 (10.0-NR) | 0.40 (0.30-0.54), P<0.001 |
| RAS G12 | Chemotherapy | 231 | 127 (55) | 6.6 (5.4-8.2) | ref |
| Overall | Daraxonrasib | 248 | 79 (32) | 13.2 (10.0-NR) | 0.40 (0.30-0.53), P<0.001 |
| Overall | Chemotherapy | 252 | 141 (56) | 6.7 (5.8-8.0) | ref |
8 details 2 trials watching
Phase, randomization and primary endpoint not stated in source. HRs came from a stratified Cox model and P values from a stratified log-rank test. Presented at ASCO as abstract LBA5.
Previously treated metastatic pancreatic cancer. OS reported in a RAS G12 population (228 vs 231) and an overall population that also includes G13 or Q61 mutations or no RAS mutation identified (248 vs 252).
Daraxonrasib vs investigator's choice chemotherapy. Dose, schedule and the chemo options allowed are not stated in source.
OS favored daraxonrasib in both populations with HR 0.40, P<0.001; per-arm values are in the figure table.
Second-line metastatic pancreatic cancer has been a chemotherapy space, with NAPOLI-1 establishing a nal-IRI based option. An OS benefit for a RAS-directed agent over chemo is a different class of result; no cross-trial numbers are reported in source.
Safety and follow-up duration not reported in source; the daraxonrasib median OS upper CI is not reached. Composition of the investigator's-choice control is unknown, which bears on comparator strength.
The identical HR 0.40 in both populations reflects that the overall population is almost entirely RAS G12, not a demonstrated benefit beyond G12. Events of 32% vs 55% and 56% mean the daraxonrasib median of 13.2 mo rests on fewer events and may move with maturity.
OS HR 0.40 vs investigator's-choice chemo, P<0.001, consistent in RAS G12 and overall populations; source frames it as historic. Tweet omits phase and design.
- Benefit in RAS G13, Q61, or no-RAS-mutation tumors?
- Durability of OS benefit with longer follow-up
- Role in first-line metastatic pancreatic cancer recruiting Study of Daraxonrasib and Daraxonrasib + GnP as First-line Treatment in Patients With Metastatic Pancreatic Adenocarcinoma Phase 3n=900 · primary completion 2028-06 · phase 3 daraxonrasib ± GnP vs chemo, 1L metastatic PDACn=400 · primary completion 2029-03 · phase 3 zoldonrasib + daraxonrasib vs GnP, 1L KRAS G12D
📚 Sources · 🐦 1 tweet
#ASCO26
— Nicholas Hornstein (@GIMedOnc) May 31, 2026
This one is special.
This is the hottest paper of 2026 and potentially in the history of pancreatic cancer.
Let’s dive in.
RASolute 302: Daraxonrasib vs investigator’s choice chemotherapy in previously treated metastatic pancreatic cancer
Abstract LBA5 (soon!)… pic.twitter.com/Lq7PEjOWAo
TALAPRO-3
ForHRR-deficient metastatic hormone-sensitive prostate cancer, enzalutamide/ADT candidates
HR 0.48
95% CI 0.36-0.65, P<0.001; 3yr rPFS 77% vs 56%
TL;DR3yr rPFS 77% vs 56%, stratified HR 0.48 (0.36-0.65), p<0.001, adding talazoparib to enzalutamide in HRR-deficient mCSPC.
In HRR-deficient metastatic prostate cancer starting enzalutamide plus ADT, this supports considering talazoparib upfront rather than reserving it, including for non-BRCA HRR alterations; it does not speak to HRR-proficient disease, which the trial excluded. The longer read

| Panel | Arm | Events/N | Median rPFS (95% CI), mo | HR (95% CI) |
|---|---|---|---|---|
| A ITT | Talazoparib+enzalutamide | 67/300 | NC (NC-NC) | 0.48 (0.36-0.65), P<0.001 |
| A ITT | Placebo+enzalutamide | 126/299 | 45.8 (37.7-NC) | |
| B BRCA | Talazoparib+enzalutamide | 22/104 | NC (NC-NC) | 0.37 (0.22-0.61) |
| B BRCA | Placebo+enzalutamide | 49/103 | 35.1 (18.6-NC) | |
| C Non-BRCA | Placebo+enzalutamide | 77/196 | NC (40.5-NC) | 0.57 (0.39-0.82) |
8 details 4 trials watching
Randomised, placebo-controlled phase 3 of talazoparib plus enzalutamide vs placebo plus enzalutamide, with ADT in both arms. ITT N=599 (300 vs 299), analysed as ITT with prespecified BRCA and non-BRCA subgroups.
HRR-deficient metastatic prostate cancer; the BRCA subgroup was 104 vs 103 and non-BRCA 196 vs 196, so BRCA carried roughly a third of the trial. Detailed eligibility and stratification factors are not reported in source.
Talazoparib added to an enzalutamide/ADT backbone that both arms received, so the comparison isolates the PARP inhibitor's contribution rather than the androgen-signaling backbone. Doses not reported in source.
Primary: imaging-based rPFS. Overall survival, safety and response endpoints are not reported in the source tweet or figure.
Landmark 3yr rPFS 77% vs 56%; median rPFS not reached in the talazoparib arm against 45.8 mo on placebo. Effect held in both molecular subgroups, numerically larger in BRCA (HR 0.37) than non-BRCA (HR 0.57).
| Population | Events/N talazoparib | Events/N placebo | Median placebo arm | HR (95% CI) |
|---|---|---|---|---|
| ITT | 67/300 | 126/299 | 45.8 (37.7-NC) | 0.48 (0.36-0.65) stratified |
| BRCA | 22/104 | 49/103 | 35.1 (18.6-NC) | 0.37 (0.22-0.61) unstratified |
| Non-BRCA | 45/196 | 77/196 | NC (40.5-NC) | 0.57 (0.39-0.82) unstratified |
TALAPRO-2 tested the same combination in first-line mCRPC across all comers; here the population is HRR-selected and the HR is numerically stronger. PROpel and MAGNITUDE established the PARP-plus-ARSI question in mCRPC, with MAGNITUDE's benefit confined to HRR-altered pts, which is the population this trial enrolled outright.
The talazoparib arm's median rPFS is NC (NC-NC) in both ITT and BRCA panels, so the absolute duration of benefit is unmeasured and the curves may still converge. No OS signal is available in source, and toxicity of the doublet (the practical cost of adding a PARP inhibitor to lifelong ARSI) is entirely absent from what was published in the thread.
The non-BRCA HR of 0.57 is the number that decides how wide this goes: if it holds, the case extends past BRCA to the broader HRR panel rather than collapsing to a BRCA-only result as earlier PARP trials did. What it does not settle is whether an rPFS gain of this size converts to survival, or whether the same result would follow sequential rather than upfront talazoparib.
CONSORT flow
Randomised double-blind phase 3, prespecified 1° rPFS hit with HR 0.48 in a biomarker-defined population, consistent across BRCA and non-BRCA. OS immature.
- Does the rPFS gain convert to overall survival n=1054 · primary completion 2022-10 · TALAPRO-2 mCRPC, mature OS readout of same combon=599 · primary completion 2026-02 · TALAPRO-3 itself; OS is a secondary endpoint
- Upfront combination vs sequential talazoparib after progression recruiting Talazoparib Plus Enzalutamide After Progression to Abiraterone in Metastatic Prostate Cancer: (TEAM PC) Phase 2n=78 · primary completion 2026-01 · talazoparib + enza 1L mCRPC after abiraterone PDrecruiting A Study of Talazoparib With or Without Enzalutamide in People With Prostate Cancer Who Have Previously Received Abiraterone Acetate Phase 2n=126 · primary completion 2029-03 · talazoparib +/- enza post-abiraterone, HRR-mutated
- Toxicity cost of indefinite PARP plus ARSI
📚 Sources · 🐦 1 tweet
JUST In: TALAPRO-3 published in @NEJM
— Toni Choueiri, MD (@DrChoueiri) May 30, 2026
Adding #talazoparib to enzalutamide/ADT
=>3-year rPFS: 77% vs 56% in HRR-deficient metastatic prostate cancer !
Looking forward to full presentation by @neerajaiims who keeps changing SOC, one trial at a time. @ASCO #ASCO26 @OncoAlert pic.twitter.com/nXiPk4DIXg
SENOMAC NCT02240472
ForcN0 T1-T3 breast, 1-2 sentinel-node macromets, planned nodal RT
HR 0.89
95% CI 0.66-1.19, P<0.001 for noninferiority (margin 1.44)
TL;DR5yr RFS 89.7% vs 88.7% omitting completion ALND, HR 0.89 (0.66-1.19), noninferior in 1-2 SLN macromets.
The axilla here was irradiated, not left alone: 89.9% vs 88.4% received nodal target volumes, so this validates SLNB plus regional nodal RT, not surgical de-escalation without RT. Untreated non-SLN disease was present in 34.5%, meaning the RT field is carrying real burden. Nodal level doses and volumes are not yet reported.
In cN0 T1-T3 disease with one or two sentinel macrometastases, including mastectomy, T3 and extracapsular extension, this supports omitting completion dissection when regional nodal irradiation is planned; it does not speak to pts in whom nodal RT is being omitted. The longer read
Nodal target volumes were treated in 89.9% vs 88.4%, so the axilla was managed, not observed, and the RT field is covering the 34.5% non-sentinel-node burden the surgery would have removed. Doses and nodal levels are not yet reported, so the trial supports covering the regional nodes without specifying how.
Systemic therapy shares the load: approximately 65% received chemotherapy and 93% endocrine therapy, and 9.9% of dissected pts were upstaged to pN2 with 3.0% pN3, meaning omission removes nodal counts that currently inform adjuvant intensity. Decisions will rest on tumour biology and genomic tools rather than final node count.
Completion dissection can be omitted in the subgroups the earlier trials could not answer: mastectomy (36.7%), T3 (5.5%) and extracapsular extension, with 5yr RFS 89.7% vs 88.7%. The trade is accepting known residual disease, since 34.5% of dissected pts had additional non-sentinel-node metastases and 9.9% were pN2.
13 details 5 trials watching
Prospective randomized phase 3 noninferiority trial, 1:1, 67 hospitals in Sweden, Denmark, Germany, Greece and Italy. 2766 enrolled Jan 2015 to Dec 2021; per-protocol population 2540 (1335 sentinel-node biopsy only, 1205 completion dissection). Median follow-up 46.8 months (range 1.5 to 94.5).
cN0, T1 to T3 breast cancer with one or two sentinel-node macrometastases (>2mm). Preoperative axillary ultrasound was mandatory; suspicious nonpalpable nodes were still eligible even with FNA-confirmed metastasis. Additional micrometastases and extracapsular extension were allowed, and both breast-conserving surgery (63.3% / 64.3%) and mastectomy (36.7% / 35.7%) were eligible. Mean age 61.
RT including nodal target volumes was given to 89.9% (1192/1326) of the sentinel-node-only group and 88.4% (1058/1197) of the dissection group. Whole-breast RT was mandatory after breast-conserving surgery, but the protocol stipulated no specific target volumes or doses, deferring to national guidelines. QA on 1154 plans showed eCRF-to-plan concordance of 99.3% for breast or chest wall and 96.6% for nodal volumes.
Primary: overall survival (switched from breast cancer-specific survival in 2020 on DSMB advice). Prespecified secondary endpoints were recurrence-free survival, breast cancer-specific survival and patient-reported outcomes. Noninferiority required the upper CI bound for recurrence or death below 1.44.
No clinical lymphedema measurements were performed; arm morbidity relies on the LYMPH-ICF, QLQ-C30, QLQ-BR23 and EQ-5D questionnaires at 1, 3, 5 and 10 years. Only 1-year data from a Swedish-Danish subpopulation are published; 3-year data for the whole trial are not yet available.
Consistent with ACOSOG Z0011 and AMAROS, but the authors place SENOMAC alongside AMAROS and OTOASOR rather than Z0011, SINODAR-ONE or POSNOC, because nodal irradiation was routine here. Where the earlier trials enrolled nearly 40% micrometastasis-only pts, one T3 patient between them, and only 248 mastectomies (17.4%) in AMAROS, SENOMAC filled each of those gaps.
Detailed nodal level doses and volumes are not yet reported, so the RT dose actually treating the residual axilla is unquantified. Withdrawal was higher in the dissection arm, reflecting pts' wish to avoid the operation. The ER+/HER2+ subgroup HR of 0.26 (0.07-0.96) rests on 3 versus 10 events among 13 subgroups and should not be read as a real interaction.
The completion dissection arm shows what is being left behind: 34.5% (403/1167) had additional non-sentinel-node metastases, rising to 51.3% with two macrometastases, and 9.9% were upstaged to pN2 with 3.0% pN3. Noninferior recurrence-free survival despite that residual burden is a statement about what systemic therapy plus nodal RT can control, not about the axilla being clean.
| Event | SLNB only (N=1335) | cALND (N=1205) |
|---|---|---|
| Local recurrence | 12 (0.9) | 10 (0.8) |
| Regional recurrence | 6 (0.4) | 6 (0.5) |
| Distant recurrence | 44 (3.3) | 53 (4.4) |
| Death | 62 (4.6) | 69 (5.7) |
| Recurrence or death as first event | 95 (7.1) | 96 (8.0) |
CONSORT flow
Prespecified noninferiority met with wide margin to boundary; enrolls the mastectomy, T3 and ECE subgroups Z0011 and AMAROS excluded, resolving the residual uncertainty.
- Nodal RT target volumes and doses needed for this result n=1900 · primary completion 2026-07 · axillary treatment vs none, 1-2 SLN macrometsrecruiting The T-REX Trial: Tailored Regional External Beam Radiotherapy in Clinically Node-negative Breast Cancer Patients With 1-2 Sentinel Node Macrometastases. Phase NAn=1350 · primary completion 2028-12 · omits regional RT in ER+ 1-2 SLN macrometsrecruiting Level I-II Axillary Irradiation in Breast Cancer With Sentinel-Node Macro-metastases Phase NAn=1608 · primary completion 2032-12 · level I-II axilla vs whole regional RT, SLN macromets
- Late recurrence in luminal disease beyond 5 years
- Arm morbidity: 3yr and 5yr lymphedema outcomes recruiting Axillary Management in Breast Cancer Patients With Needle Biopsy Proven Nodal Metastases After Neoadjuvant Chemotherapy Phase NAn=1900 · primary completion 2030-02 · 5y lymphedema endpoint after omitting ALND + ARTnot yet Omission of Axillary Lymph Node Dissection in Case of Tumor Spread to Lymph Nodes in the Armpit in Breast Cancer Phase NAn=1380 · primary completion 2030-12 · TAD vs ALND, arm lymphedema + shoulder function
📚 Sources · 📄 1 paper
NRG/RTOG 1005 NCT01349322
ForHigh-risk early breast cancer post-lumpectomy + axillary surgery, boost indicated
HR 1.31
90% CI 0.84-2.04, P=.037 (noninferiority met)
TL;DR7yr IBR 2.6% concurrent vs 2.2% sequential, HR 1.31 (90% CI 0.84-2.04), noninferior, one shorter course.
The concurrent arm is 15 fractions total, 40 Gy/15F whole breast with an 8 Gy SIB at 0.53 Gy/day, versus 21-32 fractions sequentially. Cosmesis was noninferior on patient BCTOS, physician rating, and blinded photo review, so the usual objection to a simultaneous integrated boost in a high-risk, 16.7% close-margin population does not hold at 3 years.
In a post-lumpectomy patient with grade 3, ER-negative, close-margin, or node-positive disease where you would add a boost, this supports a 15-fraction SIB course instead of sequential; it does not address partial-breast, regional nodal irradiation, or ultrahypofractionated 5-fraction boost. The longer read
The concurrent arm is 15 fractions total, 40 Gy/15F whole breast with an 8 Gy SIB at 0.53 Gy/day, against 21-32 fractions sequentially. Cosmesis was noninferior on patient BCTOS, physician rating, and blinded photo review, so the usual SIB objection does not hold at 3 years in a cohort with 16.7% close margins.
10 details 5 trials watching
Randomized, unblinded phase 3 noninferiority trial run by NRG Oncology, 278 sites across North America and 6 other countries, accrual May 2011 to June 2014. 2,354 randomly assigned, 2,255 eligible (sequential 1,118, concurrent 1,137). Median follow-up 7.3 years.
Post-lumpectomy and axillary surgery, selected for higher risk of ipsilateral breast recurrence. Median age 55 (IQR 47-64), 35.6% under 50; 96.8% invasive, 52.7% grade 3, 29.6% ER-negative, 16.7% LVI, 16.7% close (<2 mm) or focally positive margins, 16.3% node-positive, 61.8% received chemotherapy.
Sequential arm: WBI 50 Gy/25F or 42.7 Gy/16F, then boost 12 Gy/6F (84.9%) or 14 Gy/7F. Concurrent arm: WBI 40 Gy/15F with an 8 Gy/15F integrated boost at 0.53 Gy per day. 3DCRT in 1,290 (59%), photons in 1,614 (73.8%). QART scored contours and plans per protocol or acceptable variation in 92.8% and 91.9%.
Primary: IBR as first recurrence, noninferiority margin an HR upper 90% CI limit of 2.12, powered at 80% off an assumed 1.59% 5-year sequential-arm IBR. Secondary: DFS, OS, adverse events, and cosmesis (patient BCTOS, physician global cosmetic score, blinded central digital photo review).
56 IBR events, 24 sequential and 32 concurrent. Cause-specific hazards and Fine-Gray gave the same HR 1.31, and noninferiority held against each sequential WBI fractionation separately. The protocol-specified superiority test was not significant, and post-hoc analyses by stratification variable showed no treatment interactions.
| Arm | WBI | Boost |
|---|---|---|
| Sequential | 50 Gy/25F (575, 52.4%) or 42.7 Gy/16F (523, 47.6%) | 12 Gy/6F (932, 84.9%) or 14 Gy/7F, after WBI |
| Concurrent | 40 Gy/15F | 8 Gy/15F at 0.53 Gy/day, during WBI |
Grade >2 treatment-related toxicity was uncommon with no difference in grade 3-4 events (p=0.81); radiation dermatitis, fatigue, and breast pain were the most prevalent events. Physician-rated excellent/good cosmesis at 3 years was 85.9% sequential vs 82.4% concurrent (p=0.34), photo review 64.2% vs 72.0% (p=0.11).
The boost itself was established by EORTC 22881-10882, where 16 Gy sequential cut IBR but added treatment time and worsened fibrosis. IMPORT HIGH tested integrated boosts on a 40 Gy/15F backbone and found 48 Gy acceptable while its 53 Gy arm carried more induration. NRG 1005 answers the delivery question at scale rather than the dose question.
Cosmetic assessment thinned badly over time: blinded photo review response fell from 79.7% at baseline to 47.1% at 3 years, and physician rating from 90.3% to 50.5%, so the cosmesis conclusions rest on roughly half the cohort with unblinded delivery. The QoL substudy also had imbalances, more stage II sequentially (39.7% vs 32.5%) and more IMRT concurrently (27.1% vs 18.5%).
The point estimate favors sequential (HR 1.31) even as the confidence bound clears the margin, so this is a noninferiority conclusion in the honest sense, not equivalence. With 7-year IBR at 2.2% and 2.6%, the absolute difference is under a percentage point in a deliberately high-risk cohort, which is the frame in which trading 6 to 7 fractions is reasonable.
CONSORT flow
Adequately powered phase III, prespecified noninferiority margin met at 7.3yr median f/u, with cosmesis and toxicity co-endpoints also noninferior. Removes 6-7 fractions.
- Late cosmesis and fibrosis beyond 3 years with an integrated boost n=132 · primary completion 2026-03 · 1° EP RT fibrosis at 4y with hypofx tumor bed boostn=50 · primary completion 2028-09 · cosmesis + PROMs to 60mo after ultra-short WBI/SIB
- Does noninferiority hold at 10-year IBR follow-up
- Integrated boost on ultrahypofractionated 5-fraction whole-breast RT recruiting Ultra Hypo-fractionated Adjuvant Whole Breast Radiation Therapy With Simultaneous Integrated Boost for Early-Stage Breast Cancer (H-ASSIST) Phase 2n=90 · primary completion 2028-02 · 5fx WBI + SIB, toxicity and QoL endpointsrecruiting 5 fr Ultrahypofractionated WBI and SIB for Breast Cancer With Unfavorable Characteristics Phase NAn=458 · primary completion 2029-06 · randomised 26Gy/5fx + SIB 30Gy vs 40.05Gy/15fx + SIBn=400 · primary completion 2030-12 · phase 3 FAST-Forward 1wk vs 2wk concomitant boost