Phase 2 trial
AZUR-1 NCT05723562
FordMMR/MSI-H locally advanced rectal cancer, treatment-naive
TL;DRcCR12 68% (investigator) and cCR12+pCR 76% with dostarlimab alone in dMMR/MSI-H LARC, no recurrences to date at 26.3mo median f/u.
The RT-omission read hinges on the assessor: investigator cCR12 is 68%, central review 47% (54/116) with 38 pts still pending. Either figure exceeds the 21-41% post-TNT cCR range the source cites, which supports MMR testing before any pelvic RT is planned in LARC.
In dMMR/MSI-H LARC, this supports checkpoint-first, organ-preservation discussion before committing to chemoRT or TNT; it does not extend to pMMR/MSS rectal cancer. The longer read
Central review cCR12 is 47% (54/116) against investigator 68%, with 38 pts pending; both exceed the 21-41% post-TNT cCR range cited. In dMMR/MSI-H LARC, pelvic RT is shifting toward a salvage role, so MMR status should be known before simulation.
Nine cycles of dostarlimab 500 mg q3w delivered 68% cCR12 (INV) with 88% completing therapy and G≥3 immune-mediated AEs in 4 pts. This positions PD-1 monotherapy as the first move in dMMR/MSI-H LARC, ahead of oxaliplatin-based TNT.
Only 15 pts underwent resection after dostarlimab alone and 12 (80%) were pCR, so most surgical specimens showed no residual tumour. The surgical question becomes timing of salvage and surveillance intervals, not upfront TME, in dMMR/MSI-H LARC.
10 details 2 trials watching
Global single-arm phase II, registrational. Interim analysis, N=154 enrolled, median f/u 26.3 mo (range 2-36).
dMMR/MSI-H locally advanced rectal cancer. 144 pts had ≥12 mo f/u for investigator-assessed cCR12.
Dostarlimab 500 mg IV q3w for 9 cycles as monotherapy; chemotherapy, radiation and surgery reserved for non-responders.
Key endpoints: sustained cCR for 12 months (cCR12) after end of treatment by investigator and independent central review, and composite cCR12 (INV) + pCR.
cCR12 68% (INV) vs 47% (54/116) (ICR); composite cCR12+pCR 76%. Of 15 resected pts, 12 (80%) had pCR; no recurrences to date after cCR or pCR.
| Assessor | Evaluable | cCR12 |
|---|---|---|
| Investigator | 144 | 68% |
| Independent central review | 116 | 54/116 (47%) |
88% completed all 9 cycles. G≥3 immune-mediated AEs in 4 pts.
Post-TNT cCR is cited at 21-41% in LARC broadly; AZUR-1 exceeds that in a biomarker-selected group. It scales up the earlier small dostarlimab study that first showed durable cCR in dMMR LARC.
Investigator and central review diverge on cCR12, and ICR evaluability lagged because cCR was confirmed later. cCR12 is a surrogate for durable organ preservation; local regrowth risk beyond 3 years is unmeasured.
Durable cCR with no recurrences so far makes RT omission a realistic default question in dMMR LARC. Open: how long surveillance must run, and what salvage looks like for late regrowth.
Single-arm interim analysis without a randomised comparator; investigator vs central review cCR12 diverge, and durability beyond 26.3mo median f/u is unproven.
- Will ICR cCR12 converge with investigator rate as pending pts mature?
- Late local regrowth risk beyond 3 years without RT or surgery not yet Non-Operative Management and Following Immunotherapy for Colorectal Cancer and Other GI Cancersn=50 · primary completion 2029-06 · dMMR/MSI-H W&W registry after neoadjuvant IO
- Role of RT for dMMR pts without cCR after dostarlimab recruiting Study of Induction PD-1 Blockade in Subjects With Locally Advanced Mismatch Repair Deficient Solid Tumors Phase 2n=212 · primary completion 2026-11 · dostarlimab then capecitabine-IMRT in dMMR LARC
📚 Sources · 📄 2 papers
Abstract
Abstract
PE-PE NCT05578664
ForOligometastatic RCC, ≤3 mets within 5y of prior nephrectomy, MDT-eligible
HR 0.47
95% CI 0.24-0.92, p=0.024; mRFS 25.4 vs 11.0 mo
TL;DRmRFS 25.4 vs 11.0 mo, HR 0.47 (0.24-0.92), p=0.024, adding 1y perioperative pembrolizumab to SABR/surgery MDT in omRCC.
SABR was the MDT in 73% vs 72% of pts, so this is mostly pembrolizumab plus SABR vs SABR alone. Dose/fractionation and the local relapse secondary aren't in the abstract, so it can't yet show whether P changes in-field control or only cuts distant events. The decision it moves is whether SABR to all sites goes ahead with or without IO.
In post-nephrectomy omRCC with ≤3 mets within 5y planned for SABR or metastasectomy, this supports discussing 1y of perioperative pembrolizumab with MDT; it does not extend to >3 mets or relapse beyond 5y of nephrectomy. The longer read
SABR was the MDT in 73% vs 72%, so this tests IO on top of SABR to all sites. Dose and the local relapse secondary are unreported, so whether P improves in-field control or only distant events is unknown, and SABR technique itself is unchanged.
One year of pembrolizumab, started before MDT, gave HR 0.47 for RFS beyond the M1NED-within-1y adjuvant setting. G3 AEs were 7% and hypothyroidism 23%, and with 2 deaths there is no OS read to weigh against deferring IO until relapse.
10 details
Randomized 2:1, open-label, multicenter phase II, N=85 (56 P+MDT, 29 MDT alone). Median follow-up 17.5 mo.
omRCC after prior nephrectomy, ≤3 metastases within 5 years of Nx or prior metastasectomy, candidates for MDT to all metastatic sites. Baseline characteristics reported as balanced.
Pembrolizumab 400 mg q6w × 9 cycles (1 year), first dose before MDT. Median cycles delivered 6.6.
MDT was SABR in 73% vs 72% and surgery in 23% vs 28%. Dose, fractionation and target definition not reported in source.
Primary: relapse-free survival. Secondary: distant RFS, local relapse, OS, safety; only safety secondaries are reported in the abstract.
Any AE 80% vs 21%, G3 7% vs 3%. P-related AEs 59%, led by hypothyroidism 23%; no G4/5.
KEYNOTE-564 established adjuvant pembrolizumab after Nx and for M1NED within 1 year of Nx. PE-PE moves that into unresected oligomets ablated by SABR or surgery, including relapse up to 5 years out.
No local vs distant relapse split, so the site of benefit is unknown. RFS assessor blinding not stated in an open-label trial, and 2 of the 9 planned cycles went undelivered at the median.
The RFS gain is large but rests on 35 events, with a CI upper bound of 0.92. It does not settle whether IO at MDT beats IO deferred to relapse, which is the comparison that decides treatment-free intervals.
| Endpoint | P+MDT (n=56) | MDT alone (n=29) | Effect |
|---|---|---|---|
| Median RFS | 25.4 mo | 11.0 mo | HR 0.47 (95% CI 0.24-0.92), p=0.024 |
| RFS events | 19 | 16 | 35 total |
| Any AE | 80% | 21% | n/a |
| G3 AE | 7% | 3% | n/a |
CONSORT flow
Randomized phase II met its RFS primary, but N=85 with a 29-pt control arm, 17.5-mo median f/u, open-label, and only 2 deaths; abstract-only.
- Local vs distant relapse split: where does pembrolizumab add benefit?
- OS benefit vs deferring IO until relapse after MDT
- SABR dose/fractionation interaction with perioperative IO
📚 Sources · 📄 1 paper
Abstract
SARON NCT02417662
ForSynchronous oligometastatic AGA-negative NSCLC, 1-5 mets, non-progressing on 1L SACT
HR 0.99
95% CI 0.63-1.55, p=0.95; mOS 31.0 vs 28.0 mo, not met
TL;DRConsolidation RT added to 1L SACT: mOS 31.0 vs 28.0mo (HR 0.99, p=0.95) despite mPFS 13.9 vs 8.9mo (HR 0.64) in synchronous oligometastatic AGA-negative NSCLC.
Pattern of failure is the RT read: 12-mo local failure fell 39.5% to 13.0%, but new distant mets ran 36.2% vs 32.3%. Comprehensive RT controls what it treats without changing systemic seeding, so consolidation in AGA-negative oligometastatic NSCLC is a PFS and local-control decision, not a survival claim.
In synchronous oligometastatic AGA-negative NSCLC stable or responding on 1L SACT, this supports consolidation RT for local control and PFS when lesions threaten morbidity; it does not support counselling a survival gain, and it does not address EGFR/ALK-positive disease. The longer read
12-mo local failure fell 39.5% to 13.0% with radical RT to primary ± nodes plus SABR to all OM sites, while new distant mets were unchanged (36.2% vs 32.3%). Consolidation is justified on local control and PFS; dose and fractionation are not reported in source, so technique transfer is unverified.
The OS null (HR 0.99) arose on a mixed backbone: 40.0% chemo, 15.0% IO, 45.0% chemo-IO, with IO added to control mid-trial. Whether consolidation adds survival on uniform 1L chemo-IO remains untested, so referral for RT is a PFS decision, not a survival one.
10 details 2 trials watching
Multicentre randomised (1:1) phase II, N=140 across 22 UK centres, Oct 2016 to Jul 2023. Stratified by SACT, histology, N-stage, number of metastases, brain mets and site. Median follow-up 37.4 mo.
Synchronous oligometastatic AGA-negative NSCLC, 1-5 metastases in ≤3 organs, all sites amenable to SABR/SRS, randomised after initial SACT with CR, PR or SD. Median age 68, 58.6% adenocarcinoma, 52.9% N2/3, 62.9% a single OM site.
SACT was 40.0% chemo, 15.0% IO and 45.0% chemo-IO; the control arm changed to include IO in January 2020. Median SACT cycles was 4 in both arms, with maintenance permitted.
Radical RT to the lung primary ± locoregional nodes plus SABR to all OM sites. 62/70 (88.6%) received RT: 51 conventional and 11 SABR to the primary, 54 SABR to ≥1 OM site. Dose and fractionation not reported in source.
OS. Major secondary: PFS. Also reported: cumulative incidence of local failure and new distant metastasis, AEs, EORTC QLQ-C30/LC13.
G≥3 AE rate 28.6% in both arms; 6 pts had a G3 event possibly RT-related. QoL similar between arms.
The Gomez LCT phase II reported OS 41.2 vs 17.0 mo, but in 49 pts before routine IO. SABR-COMET supported the oligometastatic paradigm with few lung primaries. SARON is the larger NSCLC-specific randomised test and does not reproduce the OS benefit.
Systemic backbone shifted mid-accrual, so the RT effect on a uniform chemo-IO backbone is not isolated. Post-progression therapy, including salvage RT in the control arm, is not reported in source and could compress OS.
RT did what it was aimed at: local failure fell and PFS improved, while new distant metastasis was unchanged. The OS null points to systemic relapse as the limiting event, so lesion count alone selects poorly for the pts in whom ablation alters natural history.
| Endpoint | SACT+RT | SACT | Effect |
|---|---|---|---|
| mOS (primary) | 31.0 mo | 28.0 mo | HR 0.99 (95% CI 0.63-1.55), p=0.95 |
| mPFS | 13.9 mo | 8.9 mo | HR 0.64 (95% CI 0.43-0.95), p=0.03 |
| 12-mo cumulative incidence, local failure | 13.0% | 39.5% | p<0.01 |
| 12-mo cumulative incidence, new distant mets | 36.2% | 32.3% | p=0.28 |
| G≥3 AE rate | 28.6% | 28.6% | n/a |
CONSORT flow
Randomised, completed analysis with OS as stated primary and null result, diverging from prior small LCT trial OS signal. Phase II size leaves OS CI wide.
- Does consolidation RT add OS on a uniform chemo-IO backbone? active Nivolumab and Ipilimumab With or Without Local Consolidation Therapy in Treating Patients With Stage IV Non-Small Cell Lung Cancer Phase 3n=339 · primary completion 2027-03 · phase 3 nivo/ipi ± local consolidation, stage IV NSCLCrecruiting First-line Immunotherapy-based Standard of Care and Local Ablative Treatments for Oligometastatic Non-small Cell Lung Cancer Patients. Phase 3n=124 · primary completion 2030-02 · phase 3 1L IO ± chemo with vs without radical local tx
- Can ctDNA or systemic response select pts who gain OS from consolidation?
- How much did control-arm salvage RT compress the OS difference?
📚 Sources · 📄 2 papers
Abstract
Abstract
SARON
ForSynchronous 1-5 met driver-negative NSCLC, no PD after induction SACT
TL;DRmOS 31.0 vs 28.0 mo, HR 0.99 (0.63-1.55), adding consolidation RT to SACT in synchronous oligometastatic driver-negative NSCLC; PFS improved, magnitude not given.
The PFS gain from consolidation RT did not carry into OS (HR 0.99, 95% CI 0.63-1.55), and QoL and AEs did not differ. RT here was comprehensive: primary (+/- nodes) by conventional RT or SABR plus SABR/SRS to every met. That frames the consolidation decision for non-progressors after induction as disease control at no measured toxicity cost, not survival.
In de novo synchronous oligometastatic driver-negative NSCLC with CR/PR/SD after induction SACT, this supports consolidation RT for progression control but does not establish an OS gain; it does not extend to pts progressing on induction or to EGFR-mutated disease. The longer read
Comprehensive RT (primary +/- nodes by conventional RT or SABR, plus SABR/SRS to all mets) improved PFS without a QoL or AE penalty but left OS unchanged (HR 0.99). Consolidation for non-progressors after induction is a disease-control decision, not a survival one.
In pts who respond or stabilise on induction SACT, adding RT did not change OS (mOS 31.0 vs 28.0 mo). The systemic backbone and maintenance remain the survival lever, and per-arm subsequent therapy is not reported in source.
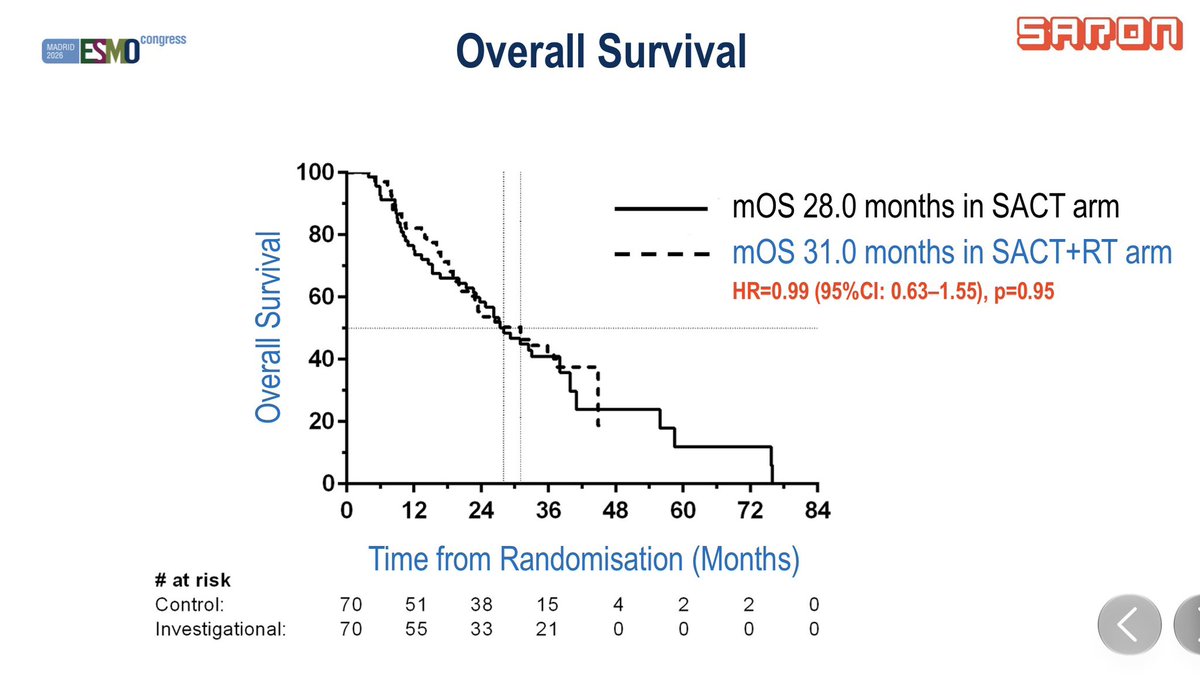
| Arm | mOS | HR (95% CI) | p |
|---|---|---|---|
| SACT (control) | 28.0 months | 0.99 (0.63-1.55) | 0.95 |
| SACT+RT | 31.0 months |
+1 more figure

11 details 2 trials watching
Randomised phase II, 1:1 by minimisation, stratified by histology, N-stage, met number, brain mets, SACT and site. N=200 registered, N=134 randomised; follow-up for 3 years or until death.
De novo synchronous oligometastatic NSCLC without driver mutation: 1-5 mets in up to 3 organs, PS 0-1, PET-CT and brain CT/MRI staged. Brain mets allowed only with at least one extracranial met. Randomised only with CR/PR/SD and PS 0-2 after 6-8 weeks induction SACT.
Conventional RT or SABR to the primary (+/- nodes) plus SABR/SRS to all metastases, delivered within a window of up to 4-6 further weeks of induction SACT. Dose and fractionation not reported in source.
PFS, OS, QoL and AEs reported. Which endpoint was primary is not stated in source.
PFS improved with RT (no effect size in source). OS HR 0.99 (95% CI 0.63-1.55), p=0.95; mOS 31.0 vs 28.0 mo.
No significant difference in AEs or QoL per presenter; no rates in source.
Gomez (Lancet Oncol 2016) and Iyengar (JAMA Oncol 2018) supported LCT after chemotherapy, while Elamin (ESMO 2025) and Iyengar (ASCO 2024) found no LCT benefit in oligo-persistent disease on chemo-IO. SARON's OS-null result sits with the latter.
The schema lists 134 randomised but the OS at-risk table shows 70 per arm, unresolved in source. Maintenance SACT was permitted, and its use by arm is not reported.
Comprehensive RT bought PFS without measured toxicity or QoL cost, but no OS benefit at this sample size. The CI is wide enough that a moderate OS effect in either direction is not excluded.
Randomised phase II, but source names no primary endpoint and gives no PFS magnitude; the only quantified result is a null OS with a wide CI.
- Does the PFS gain translate to OS with longer follow-up? recruiting Standard Maintenance Therapy (SMT) vs Local Consolidative Radiation Therapy and SMT in OM-NSCLC Phase 3n=190 · primary completion 2026-04 · phase 3 LCRT + maintenance vs maintenance, 1-5 mets
- Role of consolidation RT on a chemo-immunotherapy backbone not yet Local Consolidative Therapy Versus Maintenance Immunotherapy After First-Line Chemoimmunotherapy in Metastatic NSCLC Phase 2n=117 · primary completion 2029-12 · LCT vs maintenance IO after 1L chemo-IO PR
- Which oligometastatic subsets benefit (met number, brain mets)?
📚 Sources · 🐦 1 tweet
Presenting the UK’s SARON study Dr @fifimcdrmh to a full hall at #ESMO26
— Gerry Hanna (@gerryhanna) October 25, 2026
In patients with de novo oligometastatic mutation driver negative #NSCLC , consolidation radiotherapy to the primary and metastases improved PFS but no OS
No significant difference in QOL or AEs
Huge… pic.twitter.com/EmWoQXHalE
Low-Dose Involved Field RT in Indolent Lymphomas
ForRecurrent symptomatic indolent B-cell lymphoma (mostly FL G1-2), pretreated
TL;DR4 Gy involved-field RT in recurrent indolent lymphoma: ORR 92%, CR 61%, median time to local progression 25 mo, toxicity virtually absent.
The dose is the read: 2×2 Gy produced CR 61% with near-zero toxicity, and the 41 selected responders re-treated reached RR 98%, so the field can be re-irradiated. CR pts held local control for a median 42 mo, while PR pts progressed in-field at 10 mo, which frames 4 Gy as palliation that is durable mainly when it achieves CR.
In a pretreated pt with recurrent symptomatic FL grade 1-2, this supports 4 Gy involved-field RT as a low-toxicity palliative option, repeatable on response; it does not address transformed disease or curative-intent early-stage FL. The longer read
2×2 Gy produced CR 61% with near-zero toxicity, and re-treatment of selected responders gave RR 98%, so the field can be re-irradiated. In-field control was durable in CR pts (median TLP 42 mo) but not PR pts (10 mo), and the bulky and multi-site CR signals point to where 4 Gy may fall short.
14 details 2 trials watching
Phase II protocol, single cohort, N=109 assessable of 111 treated, 304 irradiated sites. Response assessed 4-6 wk post-RT then every 3 mo; median follow-up for pts in remission 7 mo.
Symptomatic recurrent B-cell indolent lymphoma; proven transformation and concurrent steroids or chemo excluded. Median age 62, median 2 prior regimens (range 0-11), bulky disease in 52% of pts with size data.
4 Gy as 2×2 Gy 48h apart (n=80) or 1×4 Gy (n=29), megavoltage photons or electrons. Target was the entire nodal area or the node with a 1.5 cm margin, involved sites only; 6 pts had total nodal irradiation.
in-field lymphoma control, response defined by local activity only, worst site counted. Secondary: TP (any progression) and TLP (in-field), Kaplan-Meier from first RT day.
ORR 92%, CR 61%, PR 31%. Median TP 14 mo, TLP 25 mo; CR pts TLP 42 mo. Re-treatment in 41 selected responders: RR 98%, CR 71%.
| Response group | Median TP | Median TLP |
|---|---|---|
| All (n=109) | 14 mo | 25 mo |
| CR (n=67) | 25 mo | 42 mo |
| PR (n=34) | 9 mo | 10 mo |
| Nonresponders | 2 mo | 2 mo |
Toxicity virtually absent: one transient alopecia, one transient hyperpigmentation. Antiemetics for upper abdominal fields; allopurinol for bulky disease, no gout or tumor lysis.
Concordant with Girinsky et al (135 sites, 48 pts) on RR, CR and inferior bulky-site results, but 2yr local PFS in PR pts 46% there vs 10% here. FORT later tested this low-dose approach against conventional-dose RT in a randomized design.
Comparison with pts' own prior regimens is historical and confounded by line of therapy, with power falling as numbers drop. Prognostic CR signals (≤2 sites P=.01, ≤5 cm P=.006) sit amid many tests; mixed target-volume definitions left to physician discretion.
A local, repeatable, near-toxicity-free option for systemic disease, with response rates matching first-line systemic therapy in this cohort. It does not settle whether 4 Gy matches conventional dose for durability, particularly in PR or bulky sites.
Single-cohort phase II, no randomized comparator vs conventional-dose RT or systemic therapy; within-patient historical comparison, 7-mo median follow-up in remitters.
- Does 4 Gy match conventional-dose RT for durable local control? n=375 · primary completion 2028-06 · phase 3 VLDRT vs standard-dose RT in FL/MZL
- Optimal role of low-dose RT alongside modern anti-CD20 therapy n=100 · primary completion 2027-09 · phase 3 RT + anti-CD20, low-dose 2x2 Gy context
- Is 4 Gy adequate for bulky or multi-site disease?
📚 Sources · 📄 1 paper
Abstract
Single-Fraction SBRT vs Multifraction RT for Nonspine Bone Metastases NCT02163226
ForPainful, predominantly nonspine bone mets, life expectancy >3 mo, no prior RT
TL;DR3-mo ITT pain response 38% vs 21% (P=.05) with 12-16 Gy single-fraction SBRT vs 30 Gy/10; 2-yr local PFS 100% vs 75.6%.
Dose, not single fraction per se, carries the pain signal: 3-mo ITT response was 62% (13 of 21) with 16 Gy vs 30% (18 of 60) with 12 Gy, and 12 Gy tracked 30 Gy/10 at 9 mo (13.3% vs 15.2%). Because 16 Gy went to smaller lesions, the dose choice remains hypothesis-level.
In a pt with a painful nonspine bone met, good performance status and longer expected survival, this supports single-fraction SBRT as a reasonable alternative to 30 Gy/10; it does not test SBRT against an 8 Gy single fraction or extend to spine lesions, cord compression or pathologic fracture. The longer read
Dose carries the pain signal: 3-mo ITT response was 62% (13 of 21) with 16 Gy vs 30% (18 of 60) with 12 Gy, and 12 Gy tracked 30 Gy/10 at 9 mo. Local failure was 0% with SBRT at 24 mo, but 16 Gy went to smaller lesions, so the dose pick is hypothesis-level.
14 details 2 trials watching
Phase 2, nonblinded, randomized noninferiority trial at one institution, 1:1, N=160 (81 SBRT, 79 MFRT). Stratified by tumor size, bone site and number of sites irradiated. Enrolled September 2014 to June 2018.
Pathologic cancer diagnosis, painful bone mets (score ≥2 of 10), age ≥18, life expectancy >3 mo; up to 3 fields allowed. Excluded prior RT to the site, untreated cord compression, pathologic fracture at the site, and recent radioisotope.
SBRT 12 or 16 Gy x1 by lesion size (4 cm cutoff) vs 30 Gy in 10 fx. PTV = GTV + 5 mm, no CTV; 2D/3D, IMRT or VMAT delivery. Prophylactic 7-day low-dose dexamethasone recommended for SBRT only.
Primary: pain response by international consensus criteria (pain score plus MED), noninferiority margin 10%. Secondary: MDASI QoL, CTCAE toxicity, local control, OS.
No toxicity differences between arms. G3 fatigue 9.9% vs 5.1% (P=.37), fracture 1.2% vs 0% (P=.99); MDASI scores improved in both arms without a difference.
Prior randomized trials found no pain difference between single and multifraction conventional courses, with more retreatment after 8 Gy. RTOG 9714 and the Dutch Bone Metastasis Study are the conventional-dose trials behind that equivalence. This trial escalates the single fraction but never tests it against 8 Gy.
Dexamethasone given asymmetrically to SBRT pts confounds early pain response. The 16 vs 12 Gy contrast is non-randomized and tracks lesion size. Five SBRT pts did not receive treatment due to insurance denial, and median OS of 6.7 mo leaves few pts at risk for late local failure.
The ITT data support noninferiority and a local-control advantage for SBRT; the superiority read depends on per-protocol denominators. The live question is 16 Gy vs 8 Gy in pts selected for longer survival, which needs a phase 3.
| Analysis · timepoint | SBRT | MFRT | P |
|---|---|---|---|
| ITT · 1 mo | 44% (n=36) | 30% (n=24) | .18 |
| ITT · 3 mo | 38% (n=31) | 21% (n=17) | .05 |
| Per-protocol · 2 wk | 34 of 55 (62%) | 19 of 52 (36%) | .01 |
| Per-protocol · 3 mo | 31 of 43 (72%) | 17 of 35 (49%) | .03 |
| Per-protocol · 9 mo | 17 of 22 (77%) | 12 of 26 (46%) | .04 |
| Timepoint | 16 Gy x1 | 12 Gy x1 | 30 Gy/10 | P |
|---|---|---|---|---|
| 3 mo | 62% (13 of 21) | 30% (18 of 60) | 21% (17 of 79) | .003 |
| 9 mo | 42.9% (9 of 21) | 13.3% (8 of 60) | 15.2% (12 of 79) | .005 |
| Endpoint | SBRT | MFRT | P |
|---|---|---|---|
| 1-yr local PFS | 100% | 90.5% | .01 (curve) |
| 2-yr local PFS | 100% | 75.6% | .01 (curve) |
| 24-mo cumulative local failure | 0% | 9.7% | .02 |
| 2-yr reirradiation | 0% | 5.3% | .10 |
CONSORT flow
Single-institution randomized phase 2 with one-sided alpha 0.20; superiority signals are per-protocol amid heavy attrition, comparator 30 Gy/10 rather than 8 Gy. Authors call for phase 3.
- Does 16 Gy SBRT beat 8 Gy single fraction for pain?
- Phase 3 confirmation of SBRT pain response in nonspine bone mets recruiting A Phase III Randomized Trial Comparing Stereotactic Body Radiation Therapy (SBRT) vs Conventional Palliative Radiation Therapy for Painful Bone Metastases Phase 3n=220 · primary completion 2027-06 · phase 3 SBRT dose levels vs conventional palliative RTrecruiting Stereotactic Body Radiotherapy vs Conventional Palliative Radiotherapy for Painful Non-Spine Bone Metastases Phase 3n=230 · primary completion 2027-07 · phase 3 SBRT vs conventional RT, non-spine pain relief
- Which pts live long enough to gain from SBRT local control?
📚 Sources · 📄 1 paper
Gomez LCT oligometastatic NSCLC (long-term results)
ForStage IV NSCLC, ≤3 mets, no progression after front-line systemic therapy
14.2 vs 4.4 mo
median PFS, 95% CI 7.4-23.1 vs 2.2-8.3, P = .022
TL;DRmOS 41.2 vs 17.0 mo (P=.017) and mPFS 14.2 vs 4.4 mo favoring LCT over maintenance/observation in oligometastatic NSCLC after front-line therapy.
The OS gap tracks survival after progression, 37.6 vs 9.4 mo: only 15 of 39 progressors (41%) got LCT at progression, and in the MT/O arm 7 were blocked by polymetastatic progression. That argues for consolidating every site while disease is still oligometastatic, not holding RT for progression. Dose and fractionation are not in source text.
In stage IV NSCLC with ≤3 metastases and no progression after front-line platinum doublet, EGFR TKI or crizotinib, this supports consolidating all sites over maintenance alone; it does not extend to IO-treated pts, >3 metastases, or disease progressing on first-line therapy. The longer read
The OS gap tracks survival after progression, 37.6 vs 9.4 mo, and 7 MT/O progressors lost LCT eligibility to polymetastatic progression. That argues for consolidating every site while still oligometastatic rather than reserving RT for progression; dose and fractionation are not in source text.
Maintenance or observation was the comparator, and adding LCT gave mOS 41.2 vs 17.0 mo on a pre-IO backbone of platinum doublet, EGFR TKI or crizotinib. Whether the gap persists with IO maintenance, absent from this trial, is the open regimen question.
10 details 5 trials watching
Randomized phase II, 1:1, 3 institutions (MD Anderson, London Health Sciences Center, University of Colorado); unmasked. Closed early by DSMB after 49 of 74 enrolled pts were randomized (94 planned). Median follow-up 38.8 mo (28.3-61.4).
Stage IV NSCLC, ≤3 metastases (primary not counted), ECOG ≤2, no progression after front-line therapy: ≥4 cycles platinum doublet, or ≥3 mo EGFR TKI or crizotinib. Randomization dynamically balanced on met number, response, CNS mets, N stage and EGFR/ALK status.
LCT was RT, surgery or both to all active disease sites, modality chosen by MDT; concurrent chemoRT allowed for primary and regional nodes. Dose and fractionation not reported in source text (Appendix Table A1).
Primary: PFS from randomization. Secondary: OS, toxicity, time to new lesions. Powered (90%) for PFS 4 to 7 mo, HR 0.57; P<.10 deemed significant.
PFS, OS and survival-after-progression gains in the arm table above. Late LCT at progression correlated with OS in a multivariable model, HR 0.44 (0.18-1.06), P=.064; initial LCT HR 0.30 (0.12-0.75).
| Endpoint | LCT (n=25) | MT/O (n=24) | P |
|---|---|---|---|
| Median PFS (1° EP) | 14.2 mo (7.4-23.1) | 4.4 mo (2.2-8.3) | .022 |
| Median OS | 41.2 mo (18.9-NR) | 17.0 mo (10.1-39.8) | .017 |
| Survival after progression | 37.6 mo | 9.4 mo | .034 |
| Time to new lesions | 14.2 mo (5.7-24.3) | 6.0 mo (4.4-8.3) | 0.11 |
| Deaths | 11 of 25 | 18 of 24 | n/a |
No additional grade ≥3 toxicity beyond events reported in the initial publication.
The authors state no prior randomized trial had shown an OS benefit from LCT in lung cancer. They align their proposed oligometastatic definition (0-3 metastases, unconstrained by molecular profile) with most pts enrolled on SABR-COMET and the UT Southwestern randomized phase II trial, and point to NRG-LU002 as the phase III test.
Unmasked with heterogeneous physician-chosen maintenance. Post-progression and late-LCT analyses are exploratory, post-randomization, and exclude 3 MT/O pts who crossed over before progression. EGFR/ALK cohort n=8, too small to read.
The OS gain is carried by survival after progression, consistent with a window in which all sites are still treatable. Whether the effect survives IO maintenance and a full-size trial is unsettled.
CONSORT flow
Randomised phase II closed early for PFS benefit at 49 of 94 planned pts; OS is secondary and tested at P<.10. Needs phase III confirmation (e.g. NRG-LU002).
- Does the OS benefit hold with IO-era maintenance? active Nivolumab and Ipilimumab With or Without Local Consolidation Therapy in Treating Patients With Stage IV Non-Small Cell Lung Cancer Phase 3n=339 · primary completion 2027-03 · phase III nivo/ipi ± LCT, stage IV NSCLCrecruiting First-line Immunotherapy-based Standard of Care and Local Ablative Treatments for Oligometastatic Non-small Cell Lung Cancer Patients. Phase 3n=124 · primary completion 2030-02 · phase III 1L IO-based SoC ± local ablative tx
- Does LCT add OS in EGFR/ALK-driven oligometastatic NSCLC? recruiting Local Consolidative Radiation Therapy Plus TKI Versus TKI Alone in Driver Mutated OM-NSCLC Phase 2n=106 · primary completion 2026-11 · randomized TKI ± LCRT, EGFR/ALK/ROS oligometrecruiting Osimertinib With or Without Primary Lung Tumor Resection for EGFR-Mutant Oligometastatic Non-Small Cell Lung Cancer Phase 3n=154 · primary completion 2031-08 · phase III osimertinib ± primary resection, EGFR
- Does a phase III trial confirm the OS benefit? recruiting Standard Maintenance Therapy (SMT) vs Local Consolidative Radiation Therapy and SMT in OM-NSCLC Phase 3n=190 · primary completion 2026-04 · phase III maintenance ± LCRT, 1-5 mets
📚 Sources · 📄 1 paper
Abstract
SOFT Preop
ForResectable, borderline or LA type A PDAC, ECOG 0-2, post >1 mo neoadj chemo
41% vs 38%
SBRT vs Chemo-RT, p = 0.754, ns; chemo-RT superiority hypothesis not met
TL;DRPath node positivity 41% SBRT vs 38% chemo-RT (p = 0.754) preop in PDAC; mOS 26.04 vs 42.96 mo (p= 0.639); QOL favored SBRT.
Local/regional recurrence split 6 SBRT vs 2 chemo-RT (8 events, 7.8%) at median follow-up 3.4 years, with elective nodes at 25 Gy/5 and primary at 33-40 Gy in 5, mostly on 1.5 T adaptive MR guidance. The preop fractionation choice moves toward SBRT on QOL only where that nodal volume and platform are reproduced.
In resectable, borderline, or LA type A PDAC already through >1 month of neoadjuvant chemo and planned for preop RT, this informs choosing 5-fraction SBRT over 28-fraction chemo-RT on QOL grounds; it does not address whether preop RT adds to chemo alone. The longer read
Local/regional recurrence split 6 SBRT vs 2 chemo-RT (8 events, 7.8%) at median follow-up 3.4 years, with elective nodes at 25 Gy/5 and primary at 33-40 Gy in 5, mostly on 1.5 T adaptive MR guidance. The fractionation choice moves toward SBRT on QOL only where that nodal volume and platform are reproduced.
83/98 (84.7%) reached resection, 41 SBRT and 42 chemo-RT, with no difference in surgical complications, so the 5-fraction course did not cost operability. Node positivity was 41% vs 38%; margin negativity and pathologic response are called equal but no figures appear in the abstract.
11 details 1 trial watching
Prospective, randomized phase II, 1:1 allocation after neoadjuvant chemo. 102 pts targeted and enrolled, anticipating a 15% drop out before surgery; 4 withdrew after enrollment. Median follow-up among all enrolled pts 3.4 [2.6, 5.1] years.
Resectable, borderline, or locally advanced (LA) type A PDAC, ECOG 0-2, > 1 month of neoadjuvant chemo. Median age 65 (34-82); 38%/42%/20% resectable, borderline, and LA type A. Prior chemo was FOLFIRINOX (79%), gemcitabine/nab-paclitaxel (12%), or other (9%), with 92% receiving more than 2 months.
Chemo-RT: 50.4 Gy/28 fractions with weekly gemcitabine or capecitabine. SBRT: 25 Gy/5 to elective nodes and 33-40 Gy in 5 to the primary, without concurrent chemo. Most SBRT pts were treated using 1.5 T adaptive MRI guidance.
Primary: pathologic node positivity, hypothesizing lower rates with chemo-RT. Secondary: PFS, OS, patient-reported QOL (PROMIS), physician-reported toxicity, surgical complications, translational endpoints.
Arm-level figures are in the table. 83/98 (84.7%) completed all intended therapy including surgical resection, equal in both arms.
| Endpoint | SBRT | Chemo-RT | p |
|---|---|---|---|
| Path node positivity | 41% | 38% | p = 0.754 |
| Median OS | 26.04 mo (95% CI 17.9 to 59.28) | 42.96 mo (95% CI 18.72 to 54.72) | p= 0.639 |
| Alive at 3 years | 42.6% | 57.5% | p = 0.198 |
| PFS | 14.28 mo (95% CI 9-29.64) | 21.6 mo (95% CI 10.56-38.04) | p = 0.96 |
| Local/regional recurrence (events) | 6 | 2 | not reported |
| Completed all therapy incl. resection | 41 | 42 | not reported |
No difference in surgical complications; no rates given. Physician-reported toxicity was a secondary endpoint but is not reported in the abstract. PROMIS physical function, global physical health, and fatigue were better preserved with SBRT (p = < 0.05).
Alliance A021501 tested preop SBRT or hypofractionated RT against chemotherapy alone, and PREOPANC established gemcitabine-based preop chemo-RT against upfront surgery. Neither compared one RT schedule with another. The authors describe this as the first randomized trial comparing SBRT with chemo-RT in the neoadjuvant setting for PDAC.
Abstract only: no per-arm allocation counts, no QOL magnitudes or timepoints, and no figures for pathologic response or margin negativity despite the conclusion citing them. QOL is patient-reported in an unblinded comparison. Concurrent agent varied in the chemo-RT arm and primary SBRT dose ranged 33-40 Gy.
The trial shows SBRT is deliverable preop with equal resection completion and better QOL, and it does not show nodal sterilization differs. It does not settle survival equivalence: median OS 26.04 vs 42.96 mo and LRR 6 vs 2 point the same direction in a sample too small to resolve them.
Randomised phase II, N=102, built to show chemo-RT superiority on nodal positivity and null. Not an equivalence design; survival and LRR lean numerically toward chemo-RT.
- Is preop SBRT non-inferior to chemo-RT for OS in PDAC?
- Does 25 Gy/5 elective nodal SBRT give adequate regional control?
- Does any preop RT add to neoadjuvant FOLFIRINOX alone? recruiting Preoperative mFOLFIRINOX (or Gem-Nab-P) +/- Isotoxic High-dose SBRT for Borderline Resectable Pancreatic Adenocarcinoma Phase 2n=256 · primary completion 2027-12 · preop mFOLFIRINOX +/- isotoxic high-dose SBRT in BRPC
📚 Sources · 📄 1 paper
Abstract
NRG-HN009 (p16-negative phase II toxicity)
Forp16-negative locoregionally advanced SCCHN, 70 Gy RT + concurrent cisplatin
T-score ratio 1.11
90% upper confidence bound 1.33, p=0.77 · phase III criteria not met
TL;DRT-score ratio (weekly/Q3) 1.11, p=0.77: weekly cisplatin not less toxic with 70 Gy in p16-negative locoregionally advanced SCCHN, no phase III.
6-mo LRF was 4.6% (Q3) vs 9.6% (weekly), absolute difference 5.0% (95% CI 1.0, 8.9), despite worse RT QA on Q3 (81% vs 94% per protocol or acceptable). RT quality does not explain the gap. With 70 Gy fixed, schedule choice rests on toxicity type, not total G3-4 burden.
In p16-negative locoregionally advanced SCCHN receiving 70 Gy with concurrent cisplatin, this questions choosing weekly 40 mg/m2 on tolerability grounds, since G3-4 event counts were not lower; it does not extend to the p16-positive cohort, reported separately. The longer read
6-mo LRF was 4.6% (Q3) vs 9.6% (weekly), absolute difference 5.0% (95% CI 1.0, 8.9), despite worse RT QA on Q3 (81% vs 94% per protocol or acceptable). RT quality does not explain the gap. With 70 Gy fixed, the concurrent schedule is the variable to weigh for locoregional control.
Weekly 40 mg/m2 traded toxicities instead of lowering them: G3-4 AKI 11% vs 3% and nausea 12% vs 4% on Q3, WBC decrease 28% vs 14% and hypomagnesemia 8% vs 2% on weekly. Chemotherapy delivery was per protocol or acceptable in 80% on Q3 vs 98% on weekly; cumulative dose not reported.
12 details 1 trial watching
Randomized phase II/III; this is the phase II acute toxicity report for the p16-negative cohort. 234 randomized (118 Q3, 116 Q1) between Oct 2021 and Sept 2025; 91% completed all follow-up up to 6 months. QA modality reviews were done on a random sample of cases.
p16-negative locoregionally advanced SCCHN. Median age 60; 76% male; 58% Zubrod 0; 87% former or current smokers, 70% >10 pack-years. 57% larynx, 28% oropharynx, 15% hypopharynx; 83% T1-3 and 74% node-positive.
Cisplatin 100 mg/m2 Q3 weeks (Q3) vs cisplatin 40 mg/m2 weekly (Q1), each with RT. Chemotherapy delivery scored per protocol or acceptable variation in 80% on Q3 vs 98% on Q1. Cumulative cisplatin dose delivered is not reported in source.
70 Gy in both arms; fractionation, technique and target volumes are not reported in source. RT reviews were completed for 91% of sampled pts, scored per protocol or acceptable variation in 81% on Q3 vs 94% on Q1.
acute toxicity by T-score, the number of all treatment-related grade 3-4 AEs during treatment or within six months. To proceed to phase III, the mean T-score ratio (Q1/Q3) had to be below 1 at 1-sided p<0.1, together with a 6-month locoregional failure difference criterion (printed as '= 8%' absolute in the portal text).
The cohort did not meet criteria for continuing to phase III; arm-level values are in the tables.
| Endpoint | Q1 Cis (weekly) | Q3 Cis | Effect |
|---|---|---|---|
| Mean T-score | 2.48 (95% CI 1.97, 2.99) | 2.23 (95% CI 1.81, 2.65) | Ratio 1.11 (90% upper bound 1.33), p=0.77 |
| 6-month locoregional failure | 9.6% | 4.6% | Absolute difference 5.0% (95% CI 1.0, 8.9) |
| AE term | Q3 Cis | Q1 Cis |
|---|---|---|
| Nausea | 12 | 4 |
| WBC decreased | 14 | 28 |
| Dehydration | 9 | 1 |
| Hypomagnesemia | 2 | 8 |
| Acute kidney injury | 11 | 3 |
Total G3-4 burden was similar, but the profile differed by schedule. Q3 carried more G3-4 nausea (12% vs 4%), dehydration (9% vs 1%) and acute kidney injury (11% vs 3%); weekly carried more WBC decrease (28% vs 14%) and hypomagnesemia (8% vs 2%). Late toxicity is not reported in source.
The Tata Memorial randomized trial (Noronha et al.) favored Q3 over a lower weekly dose for locoregional control in a mostly postoperative population, while JCOG1008 supported weekly dosing after surgery. This cohort tests the schedule question with 70 Gy RT in p16-negative disease and gives no toxicity support for weekly; the source draws no comparison to either trial.
The T-score weighs every G3-4 event equally, so marrow and renal events are interchangeable in the primary. QA was scored on a random sample, not all cases, and per-arm cumulative cisplatin dose is missing. The portal text has lost the inequality in the LRF criterion, so the abstract alone does not show whether that half of the rule passed.
The tolerability premise for weekly cisplatin did not hold here: toxicity was redistributed, not reduced. The LRF difference favors Q3 but rests on a 6-month read in a toxicity-driven phase II, so it is a direction, not an efficacy result. Pooled results for all 475 pts were deferred to the presentation.
CONSORT flow
Randomized, prespecified phase II go/no-go analysis; weekly failed its toxicity criterion, leaving Q3 as the reference schedule. Abstract only; 6-month LRF is immature and not an efficacy test.
- Does the 6-month LRF gap persist in longer-term locoregional control and survival?
- Do pooled p16+ and p16- results (475 pts) show the same toxicity pattern?
- Late toxicity and hearing outcomes by cisplatin schedule n=100 · primary completion 2028-09 · randomized weekly LD vs HD cisplatin CRT, p16-stratified
📚 Sources · 📄 1 paper
Abstract
TORCH-iTNT NCT06281405
ForpMMR LARC, T3-4/N+ M0, 96.6% with at least one high-risk feature
61.5% vs 37.1%
48/78 with SCRT vs 26/70 without; no p-value or CI reported
TL;DRCR (pCR + cCR) 61.5% with SCRT 25Gy/5Fx → CAPOX + toripalimab vs 37.1% without RT in pMMR LARC; no p-value reported.
The RT read sits in cCR, not pCR: 25 pts after SCRT 25Gy/5Fx vs 7 without RT reached cCR and went to W&W, so the short course is what opened the organ-preservation route. The no-RT arm still carried adjuvant chemoradiotherapy for positive circumferential margins, at a rate the source does not report.
In pMMR LARC (T3-4/N+ M0) with high-risk features where organ preservation is the aim, this supports retaining SCRT ahead of CAPOX plus PD-1 inhibitor; it does not extend to dMMR disease, and it does not show that omitting RT preserves function. The longer read
The RT read sits in cCR, not pCR: 25 pts after SCRT 25Gy/5Fx vs 7 without RT reached cCR and went to W&W, so the short course is what opened the organ-preservation route. The no-RT arm still carried adjuvant chemoradiotherapy for positive circumferential margins, at an unreported rate.
CAPOX plus toripalimab without RT gave a 37.1% (26/70) CR rate in pMMR LARC, but with no chemotherapy-alone arm the PD-1 inhibitor's contribution is unmeasured. G3-4 thrombocytopenia was similar across arms (12.9% vs 14.1%), so adding SCRT did not visibly cost hematologic tolerance of six cycles.
Omitting RT sent more pts to resection: 58 of 70 in the no-RT arm had surgery vs 52 of 78 after SCRT, with 7 vs 25 entering W&W. pCR among resected was 32.8% vs 44.2%. Margin status, sphincter preservation and anorectal function are not yet reported.
11 details 1 trial watching
Multicenter randomized phase II, 192 pMMR LARC pts enrolled. Initial results as of January 31, 2026 cover the 148 who completed treatment (70 in Group A, 78 in Group B). Allocation ratio, stratification and follow-up duration are not stated in source.
pMMR LARC, T3-4/N+ M0. Baseline characteristics described as balanced. 96.6% (143/148) had at least one high-risk feature: low tumor location, cT4, cN2, MRF+ or EMVI+.
Group A: 6 cycles of CAPOX plus toripalimab. Group B: SCRT followed by the same 6 cycles. cCR pts were offered W&W, non-cCR pts were recommended for surgery.
SCRT 25Gy/5Fx before immunochemotherapy in Group B. Group A received no neoadjuvant RT, with adjuvant chemoradiotherapy reserved for positive circumferential margins. Target volumes, technique and the interval from SCRT to response assessment are not reported in source.
Primary: complete response rate, defined as pCR plus cCR. Secondary: organ preservation rate, anorectal function, adverse events and survival outcomes.
Thrombocytopenia was the most common grade 3-4 AE, 12.9% in Group A and 14.1% in Group B. No other AE data, and no RT-attributable or surgical toxicity, are reported in source.
TORCH, the same group's predecessor, tested induction vs consolidation sequencing of SCRT with CAPOX and toripalimab; this trial asks instead whether SCRT can be dropped. UNION set SCRT followed by immunochemotherapy against long-course chemoradiotherapy. PROSPECT asked the RT-omission question with chemotherapy alone in a lower-risk population than the one enrolled here.
cCR criteria and the assessment timepoint are not stated, and cCR calls cannot be blinded to arm. The pCR denominator in Group B excludes the 25 cCR pts who went to W&W, so resected-only pCR is not a like-for-like comparison. No chemotherapy-alone arm, so toripalimab's contribution is unmeasured.
The gap in CR is carried mostly by clinical responses, which is the outcome that matters for W&W and also the softer of the two components. The rationale for the no-RT arm was functional sparing, yet 58 of 70 Group A pts went to surgery vs 52 of 78 in Group B, and anorectal function is not yet reported. Regrowth after W&W will decide whether the cCR advantage holds.
Initial results in 148 completers of 192 enrolled; no p-value or CI; CR is an early response endpoint, and organ preservation, function and survival readouts are pending.
- Local regrowth rate after W&W in each arm not yet the Efficacy of MR-guided Online Adaptive Radiotherapy for Locally Advanced Rectal Cancer Phase NAn=49 · primary completion 2026-12 · SCRT on MR-linac; W&W local recurrence rate endpoint
- Anorectal function with vs without SCRT
- Does toripalimab add to CAPOX alone in pMMR LARC without RT?
📚 Sources · 📄 1 paper
Abstract
Ultralow-dose 4 Gy RT for myeloma bone metastases
ForMultiple myeloma, uncomplicated painful bone lesion; 79% prior chemo
TL;DRPain response 59% at 4 wks (per protocol; ITT 40/70, 57%) after 4Gy to painful MM bone lesions; 24% needed a second RT course.
The ITT read runs opposite to the abstract's framing: CR+PR was 40/70 (57%) at 4 wks, 33/70 (47%) at 8 wks and 37/70 (53%) at 6 mo, with 25/70 (36%) not completing the 6 mo assessment. The decision in play is 4Gy first with reRT held in reserve; 24% needed a second course.
In MM with an uncomplicated painful bone lesion, this supports 4Gy as a response-adapted first step with reirradiation in reserve; it does not extend to complicated lesions or to pts who need fast relief, given a median 36 days to pain relief. The longer read
The ITT read runs opposite to the abstract's framing: CR+PR was 40/70 (57%) at 4 wks, 33/70 (47%) at 8 wks and 37/70 (53%) at 6 mo, with 25/70 (36%) not completing the 6 mo assessment. The decision in play is 4Gy first with reRT held in reserve; 24% needed a second course.
12 details
Prospective, multi-institutional, single-arm phase II. 63 evaluable pts with 70 lesions from 7 institutions, treated 4/2019-9/2025. Median follow-up after RT 186 days.
Multiple myeloma with an uncomplicated painful bone lesion. Median age 66, 49% female, 89% ECOG 0-1, 79% prior chemo (median 1 line), 40% prior RT to a different area. Median baseline BPI 4.8.
4Gy total, delivered as 2Gy x 2 or 4Gy x 1 (29% received 4Gy x 1). Reirradiation with a clinician-choice regimen could be considered at 4 weeks after initial treatment for inadequately controlled pain (the inequality symbol is garbled in the source). Target volume and technique not stated in source.
Primary: proportion with self-reported pain response at 4 weeks. Response was scored on average BPI and oral morphine equivalent dosing per the International Consensus on Palliative RT, assessed at 4 weeks, 8 weeks and 6 months.
Response rates by timepoint are in the table. Median BPI and OMED decreases were 2.25 and 5mg at 4 weeks and 2.75 and 6.2mg at 8 weeks. Median time to pain relief was 36 days, median duration 148 days, with no difference by fractionation.
| Timepoint | ITT CR+PR | Per protocol CR+PR | Did not complete |
|---|---|---|---|
| 4 wks | 40/70 (57%) | 40/68 (59%) | 2/70 (2%) |
| 8 wks | 33/70 (47%) | 33/52 (63%) | 18/70 (26%) |
| 6 mo | 37/70 (53%) | 37/45 (82%) | 25/70 (36%) |
No grade 3+ treatment-related toxicity. Lower-grade events and hematologic toxicity are not reported in the source, although marrow sparing was the stated rationale.
The source states there is no consensus on the most effective palliative dose in MM. The ultralow-dose concept comes from indolent lymphoma, where FoRT tested it against a conventional dose. With no comparator arm here, the 59% at 4 weeks cannot be ranked against conventional palliative fractionation.
Missing assessments grow from 2/70 at 4 weeks to 25/70 at 6 months, and reasons are not given, so the late per-protocol rates are vulnerable to informative dropout. Handling of reirradiated lesions in the 6 month response is not stated. Pain response is self-reported in an unblinded single-arm design.
Best read as a strategy: 4Gy first, escalate on failure. A 63% response at 4 weeks after reirradiation suggests the low first dose did not obviously compromise salvage, at the cost of time (median 95 days to relief after reRT). It does not settle whether 4Gy matches conventional dosing up front, or whether it spares marrow.
Single-arm phase II, 63 pts, no comparator against conventional palliative fractionation; late responses rest on a per-protocol denominator with 36% non-completion at 6 mo.
- 4Gy vs conventional palliative fractionation in MM bone lesions: randomised comparison needed
- Does 4Gy reduce hematologic toxicity vs higher-dose palliative RT?
- Which lesions fail 4Gy and need reirradiation?
📚 Sources · 📄 1 paper
Abstract
RTOG 3506 (STEEL)
ForPost-RP BCR with ≥1 high-risk feature, receiving SRT + 24mo ADT
HR 0.62
80% CI 0.42-0.91, one-sided p=0.052
TL;DRPFS HR 0.62 (80% CI 0.42-0.91, one-sided p=0.052) adding enzalutamide to SRT + 24mo ADT in high-risk post-RP BCR; BF at 2y 11% vs 19%.
Both arms received SRT + 24 months GnRHa, so the trial isolates ARSI intensification, not the RT contribution; SRT dose and field are not reported in source. BF at 2y dropped 19% to 11%, but Gr 3-4 lymphopenia rose 15% vs 5%, worth weighing if pelvic nodal fields are in the plan.
In post-RP BCR with Gleason 8-10, SVI, pN1, persistent PSA or PSA ≥0.7 already planned for SRT + 24 months ADT, this supports discussing enzalutamide as investigational intensification; it does not extend to lower-risk BCR or shorter ADT courses.
RT was fixed across arms, so this informs what to pair with SRT, not dose or field; technique is not reported in source. BF at 2y 11% vs 19% suggests the SRT + 24mo ADT backbone still leaves room for intensification in high-risk BCR.
Enzalutamide 160 mg on top of 24 months GnRHa cut PFS hazard (HR 0.62, 80% CI 0.42-0.91) in a screening design. Gr 3-4 lymphopenia 15% vs 5% and hypertension 8% vs 5% are the toxicity trade to weigh pending phase III.

| Arm | PFS HR (80% CI) | p |
|---|---|---|
| SRT+ENH ADT | 0.62 (0.42, 0.91) | one-sided p=0.052 |
| SRT+STD ADT | Referent | n/a |
+2 more figures
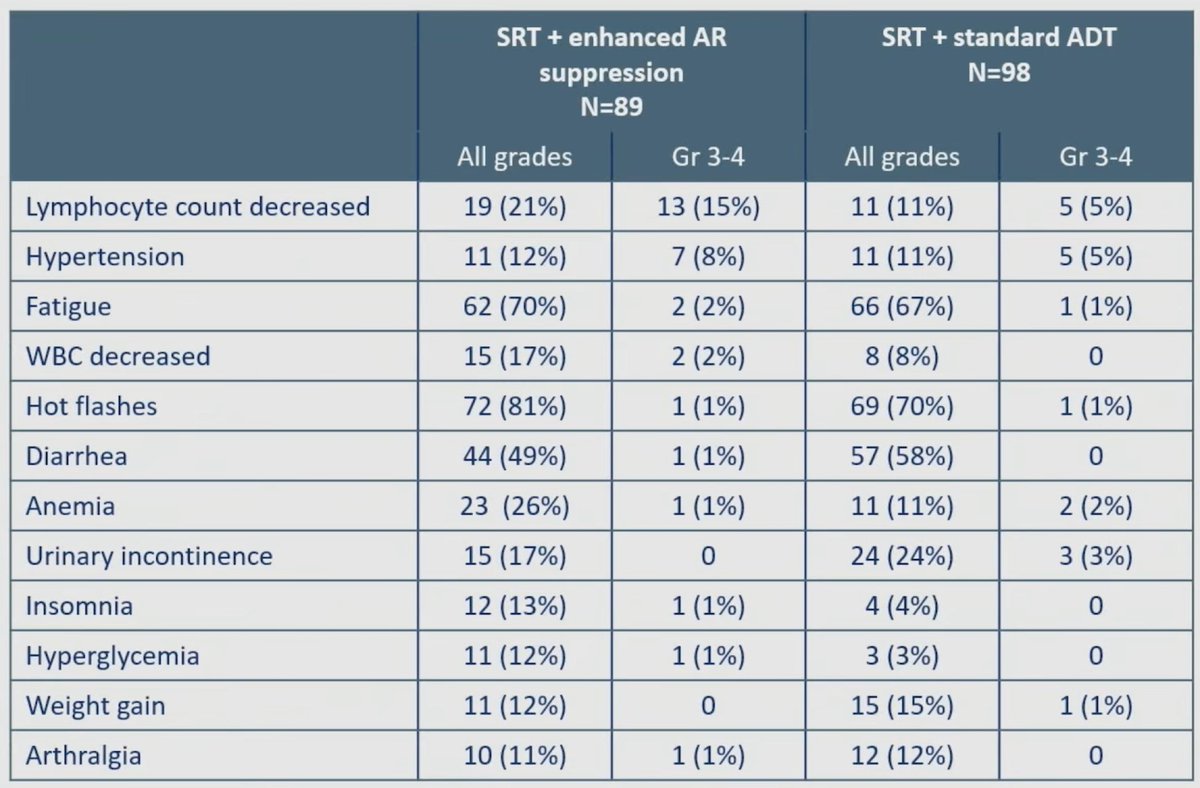
| AE (all grades) | SRT + enhanced AR suppression (N=89) | SRT + standard ADT (N=98) |
|---|---|---|
| Lymphocyte count decreased | 19 (21%) | 11 (11%) |
| Hot flashes | 72 (81%) | 69 (70%) |
| WBC decreased | 15 (17%) | 8 (8%) |
| Anemia | 23 (26%) | 11 (11%) |
| Diarrhea | 44 (49%) | 57 (58%) |
| Urinary incontinence | 15 (17%) | 24 (24%) |
| Hyperglycemia | 11 (12%) | 3 (3%) |
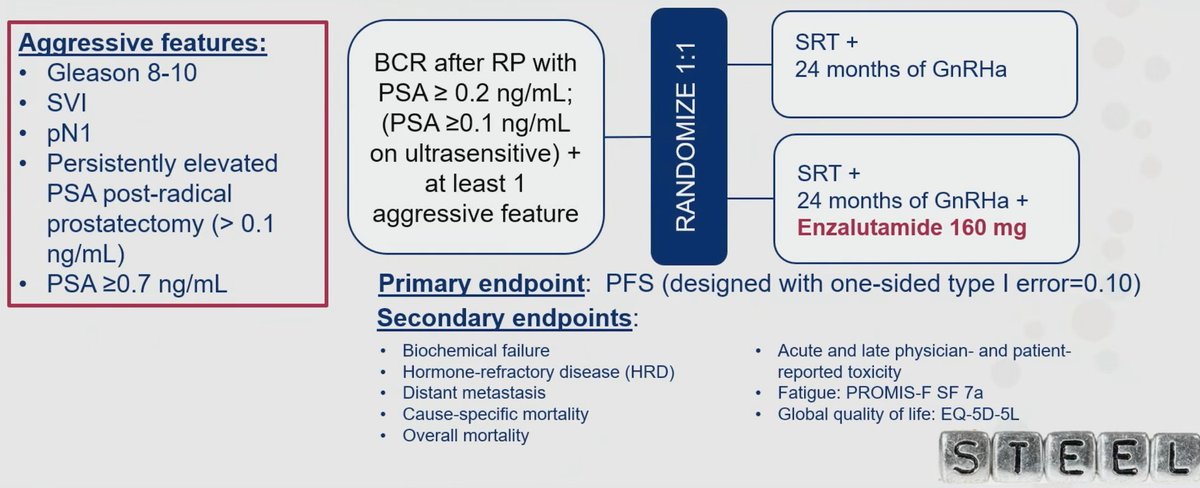
8 details
Randomized phase II, 1:1, n=188, final results. Median follow-up 33.1 mos. Designed with a one-sided type I error of 0.10.
BCR after RP with PSA ≥0.2 ng/mL (or ≥0.1 ng/mL ultrasensitive) plus ≥1 aggressive feature: Gleason 8-10, SVI, pN1, persistently elevated post-RP PSA >0.1 ng/mL, or PSA ≥0.7 ng/mL.
Control: 24 months GnRHa. Experimental: 24 months GnRHa + enzalutamide 160 mg.
Salvage RT in both arms. Dose, fractionation and target volume (prostate bed vs pelvic nodes) are not reported in source.
Primary: PFS. Secondary: biochemical failure, hormone-refractory disease, distant metastasis, cause-specific and overall mortality, physician- and patient-reported toxicity, fatigue (PROMIS-F SF 7a), global QoL (EQ-5D-5L).
PFS HR 0.62 (80% CI 0.42-0.91), one-sided p=0.052. BF at 2 yrs 11% vs 19%.
More Gr 3-4 lymphopenia with enza, 13 (15%) vs 5 (5%), and Gr 3-4 hypertension 7 (8%) vs 5 (5%). All-grade hot flashes 81% vs 70%.
RTOG 9601, GETUG-AFU 16 and SPPORT established adding ADT to SRT; STEEL asks the next question, whether an ARSI on top of long-course ADT adds further. EMBARK tested enzalutamide in high-risk BCR without RT, a different setting.
SRT technique not reported, so RT transferability can't be judged. PFS definition and blinding not stated in source. The 24-month ADT control is itself intensified relative to many current practices.
The signal clears the trial's own screening threshold, but no OS or metastasis data in source, so the cost in lymphopenia and hypertension is set against a surrogate benefit only. The question is now phase III-ready, not practice-ready.
Randomized phase II screening design: one-sided α 0.10, 80% CI, surrogate PFS endpoint, 33mo median f/u. Needs phase III confirmation before ARSI intensification with SRT.
- Does PFS gain translate to MFS or OS?
- Phase III confirmation of ARSI intensification with salvage RT
- Role of pelvic nodal RT alongside enhanced AR suppression
📚 Sources · 🐦 1 tweet
Final Results from RTOG 3506 (STEEL): Randomized Ph II -- 24 mos of Enza + ADT vs ADT in HR Pts with BCR Undergoing Salvage RT @EdwinPosadasMD @urotoday #ASTRO26
— Zach Klaassen (@zklaassen_md) September 29, 2026
📌n=188, mFU 33.1 mos
📌Enza + ADT vs ADT, PFS: HR 0.62, 80%CI 0.41-0.91; p = 0.052
📌BF @ 2 yrs: 11% vs 19% pic.twitter.com/fkHw8hzOri
LAVA-CRLM NCT03654131
For1-3 oligometastatic CRLM ≤4 cm (treated ≤3 cm), Child-Pugh A, curative intent
HR 0.87
95% CI 0.43-1.74, p=0.70; 1-yr 83.0% vs 77.7%, not met
TL;DR1-yr freedom from local progression 83.0% SBRT vs 77.7% MWA (HR 0.87, p=0.70); treatment-related G2+ toxicity 3% vs 25% in oligometastatic CRLM.
The dose and platform set the transfer bar: 45 Gy/3 fx at the 67% isodose, BED10 >173 Gy to GTV, 88% on MR-linac with daily adaptation, and no G3+ toxicity vs 4 (8%) after MWA. SBRT's case rests on that toxicity gap for small lesions, not on a local control win.
In pts with 1-3 CRLM ≤3 cm judged suitable for both ablation and SBRT, this supports SBRT as a non-invasive alternative when ablation access or procedural risk is the concern; it does not extend to 3-4 cm lesions or to settings without ablative-dose delivery. The longer read
Ablative dosing (45 Gy/3 fx, BED10 >173 Gy to GTV) on MR-linac with daily adaptation produced no G3+ toxicity and a 1-yr FFLP of 83.0%. The transfer question is platform: only 5 pts were treated on a conventional linac, so non-MR centres lack direct support.
For HPB teams, MWA carried 4 (8%) G3+ events including a fatal hepatic necrosis with perforation, vs none with SBRT, at no detectable local control cost for lesions ≤3 cm. Resection remains standard; this informs the non-resection choice, where SBRT can spare anaesthesia and open or laparoscopic access.
10 details
Investigator-initiated randomised phase II, 1:1, two Danish centres, no stratification. N=100 randomised Jan 2019 to Dec 2024; mITT 92. Open-label, with masked 1° endpoint imaging review.
1-3 CRLM, each ≤4.0 cm, Child-Pugh A, liver volume ≥700 mL, no prior liver RT. MDT-deemed suitable for both MWA and SBRT; limited extrahepatic disease allowed if curative strategy feasible. Median lesion 1.2 cm; 78% had a single metastasis.
45 Gy/3 fx preferred, 50 Gy/5 fx when OAR constraints required, prescribed to the 67% isodose; PTV 10 mm craniocaudal, 5 mm radial. BED10 >173 Gy to GTV in all. 88% on MR-linac with daily online adaptation.
Primary: patient-level freedom from local progression of treated lesions (new lesions not events). Secondary: OS, treatment-related G3+ toxicity, late G2+ toxicity; EORTC QLQ-C30.
Acute G2+ 1 (3%) SBRT vs 13 (25%) MWA; G3+ only after MWA, 4 (8%) including one death from hepatic necrosis with capsular perforation. Liver pain G1 in 3 (7.5%) SBRT vs 25 (48%) MWA. QoL did not differ.
Authors cite MWA local control exceeding 90% and 1-yr SBRT LC ranging 50% to 95% in prior, largely retrospective series. Dose here clears Kang's BED10 >117 Gy threshold for ~90% 1-yr LC, so a dose deficit does not explain SBRT's result.
KRAS-mutant disease was 45% vs 24% in the MWA vs SBRT arms, with no molecular stratification; Hong reported KRAS-mutant 1-yr LC 43% vs 72%, a large enough modifier to move arm estimates. Single institutional network; post-protocol systemic therapy uncontrolled.
The trial gives the first randomised head-to-head data, not an equivalence claim; a null HR with CI 0.43-1.74 leaves room for either modality to be meaningfully better. What it settles more firmly is that SBRT avoids the invasive-procedure harms MWA carries.
| Endpoint | SBRT | MWA | Effect |
|---|---|---|---|
| 1-yr FFLP, mITT | 83.0% (72.3-95.4) | 77.7% (66.5-90.9) | HR 0.87 (0.43-1.74), p=0.70 |
| 1-yr FFLP, per-protocol | 86.0% (75.3-98.2) | 77.7% (66.5-90.9) | HR 0.78 (0.37-1.63), p=0.50 |
| 3-yr OS, mITT | 71.5% (58.3-87.7) | 63.3% (49.3-81.2) | HR 0.91 (0.48-1.70), p=0.80 |
| Toxicity | SBRT | MWA | Test |
|---|---|---|---|
| G2+ acute (≤1 mo) | 1 (3%) | 13 (25%) | n/a |
| G3+ acute (≤1 mo) | 0 (0%) | 4 (8%), incl 1 death | Fisher p=0.13 |
| 1-yr cumulative G2+ | 7.5% (1.9-18.4) | 20.7% (10.6-33.1) | Fine-Gray HR 0.51 (0.21-1.24) |
| 3-yr cumulative G2+ | 24.6% (9.8-42.9) | 32.7% (18.5-47.6) | Gray's p=0.13 |
CONSORT flow
Randomised but small phase II powered for HR 0.38, not equivalence; null 1° EP with wide CI cannot establish SBRT matches MWA. Toxicity underpowered.
- Does SBRT match MWA for 3-4 cm colorectal liver metastases?
- Does KRAS/TP53 status modify SBRT vs MWA local control?
- Would a powered non-inferiority trial confirm local control parity?
📚 Sources · 📄 1 paper
Testosterone Treatment in Prostate Cancer Survivors (Bhasin RCT) NCT03716739
ForHypogonadal men post-RP, pT2 Gleason 3+3/3+4, undetectable PSA ≥2 yr
TL;DRSexual activity +0.91 daily events vs placebo (95% CI 0.56-1.26, P<.001), zero biochemical recurrences, 12wk TRT in hypogonadal men post-RP for Gleason 3+3/3+4.
Men treated with RT or ADT were excluded, so the zero-BCR signal does not transfer to post-RT survivors, the hypogonadal population a radiation oncologist actually follows. Post-RT pts retain prostate tissue, and this trial offers no data on TRT against that background.
In hypogonadal men with undetectable PSA ≥2 years after RP for pT2 Gleason 3+3 or 3+4 disease, this supports short-term TRT as an evidence-backed option for sexual symptoms; it does not extend to post-RT, post-ADT, or higher-grade survivors. The longer read
For the urologist following hypogonadal men after RP for pT2 Gleason 3+3/3+4 disease, this provides the first randomized efficacy data for TRT, with an effect above the stated MCID. It does not settle oncologic safety: 0 vs 0 BCR over 12 wk plus 3 mo in a near-zero-risk cohort cannot rule out harm.
10 details 1 trial watching
Randomized, placebo-controlled, double-blind, parallel-group phase 2 (SPIRIT), 2 academic centers, 1:1, N=136. Enrollment May 2019 to last visit May 2025; target revised from 142 to 134 with DSMB concurrence.
Men ≥40 post-RP for organ-confined pT2N0M0, Gleason 3+3 or 3+4, preop PSA <10, undetectable PSA ≥2 yr. Hypogonadal (T <275 ng/dL and/or free T ≤70 pg/mL) plus low libido, ED, or fatigue. Mean age 68.6; 38% Gleason 6, 62% Gleason 7.
Testosterone cypionate 100 mg IM weekly × 12 wk vs placebo. Total T rose 349 ng/dL (95% CI 283-415) more than placebo; adherence 95% vs 94%.
Primary efficacy: change in sexual activity (PDQ question 4). Primary safety: biochemical recurrence (≥2 consecutive PSA ≥0.2 ng/mL). Secondary: desire, erectile function, affect, body composition, VO2 peak, stair-climb power.
No biochemical recurrence in either arm. Erythrocytosis in 3 TRT pts; SAEs 1 vs 3; no MACE or VTE. One TRT pt had detectable PSA 0.1 to <0.2 ng/mL during treatment.
Described by the authors as the first randomized placebo-controlled trial of TRT in prostate cancer survivors; prior support for TRT after RP rested on observational series. Many guidelines still list prostate cancer history as a TRT contraindication.
Baseline recurrence risk in this cohort is so low that 0 vs 0 BCR carries little information about harm. Erectile function did not move despite EPIC-26 gains, and no P value adjustment was made across secondaries.
The efficacy case for TRT in this population is now randomized and exceeds the MCID. The safety case remains a short-horizon absence of events, which justifies a larger long-term trial rather than settling the contraindication.
| Endpoint | Treatment effect (95% CI) | P |
|---|---|---|
| Sexual activity (PDQ-4), 1° EP | 0.91 (0.56 to 1.26) | <.001 |
| Sexual desire (DISF-SD) | 2.96 (1.46 to 4.45) | <.001 |
| EPIC-26 sexual domain | 5.35 (1.63 to 9.07) | .005 |
| Erectile function (IIEF) | 0.93 (−0.43 to 2.29) | .18 |
| Energy | 1.43 (−0.53 to 3.40) | .15 |
| PANAS positive affect | 0.60 (−0.85 to 2.04) | .42 |
| PANAS negative affect | −1.39 (−2.53 to −0.25) | .02 |
| Event | Placebo | Testosterone |
|---|---|---|
| Biochemical recurrence | 0 | 0 |
| ≥1 AE, pts (events) | 47 (138) | 49 (160) |
| SAEs, pts (events) | 1 (1) | 3 (3) |
| Erythrocytosis (Hb >18 g/dL) | 0 | 3 (3) |
| MACE | 0 | 0 |
| VTE | 0 | 0 |
| Bone fractures | 3 (3) | 0 |
CONSORT flow
Efficacy primary met in a clean double-blind RCT, but the question that gates practice (oncologic safety) is untestable at N=136 and 12 wk; authors frame it as proof-of-concept.
- Long-term oncologic safety of TRT after RP recruiting Impact of Peri-operative tEstosterone Levels on oNcological and Functional Outcomes in RadiCal prostatEctomy Phase 3n=140 · primary completion 2027-12 · phase 3 TRT gel vs placebo post-RP, oncologic outcomes
- TRT safety in post-RT or higher-grade survivors
- Durability of benefit beyond 12 weeks
📚 Sources · 📄 1 paper
Abstract
SIB-CRT vs Standard CRT for LARC (NCT02195141) NCT02195141
ForStage II/III rectal adenocarcinoma, neoadjuvant chemoRT candidates
15.2% vs 18.4%
P=0.695, primary endpoint not met
TL;DR9yr LC 87.1% vs 70.1% (HR 0.40, P=0.038) and OS 74.3% vs 48.9% (HR 0.43) favoring SIB dose escalation.
The boost was 56 Gy to PGTV and 60 Gy to involved lateral nodes on a 50 Gy/25 fx pelvic base, a deliverable prescription with acute G3 toxicity 14.5% vs 19.6%. LC 87.1% vs 70.1% is the mechanistically coherent signal; the OS and MFS separation on 106 pts is not, and gates any move to boost outside a trial.
In stage II/III LARC where perioperative chemotherapy is not planned or not tolerated, this supports testing an integrated boost to gross disease and involved lateral nodes; it gives no read on pts receiving modern TNT, where the subgroup showed no added benefit. The longer read
The prescription is deliverable and specified: 56 Gy to PGTV, 60 Gy to involved lateral nodes, on a 50 Gy/25 fx pelvic base, with acute G3 toxicity 14.5% vs 19.6% and no late toxicity reported. LC 87.1% vs 70.1% is the endpoint a boost can own; treat the OS and MFS separation as hypothesis-generating for a boost trial, not license to escalate off-protocol.
The benefit was confined to pts who did not receive perioperative chemotherapy (9yr DFS 70.8%, HR 0.343, P=.014), with no additional benefit in those who did, and chemo receipt was not randomized. Read as a signal about RT dose in chemotherapy-ineligible pts rather than any argument against systemic intensification.
9 details 5 trials watching
Prospective randomized phase 2, 1:1, N=106 (55 SIB-CRT, 51 CRT), accrued August 2013 to February 2015. Median follow-up 116.6 months, which is the study's real asset.
Stage II/III rectal adenocarcinoma. Radical surgery planned 6 to 8 weeks after chemoradiotherapy. Perioperative chemotherapy was not randomized, and its receipt defines the subgroup that carries the result.
Both arms received 50 Gy/25 fx to the pelvis. The experimental arm added a simultaneous integrated boost of 56 Gy to PGTV and 60 Gy to lateral metastatic nodes where present, so the escalation targets gross primary and involved lateral nodes rather than the elective volume.
Primary: pCR rate. Secondary: DFS, OS, MFS, LC, CSS and toxicity. Every result the conclusion rests on is secondary.
Acute grade 3 toxicity 14.5% (SIB-CRT) vs 19.6% (CRT), primarily radiation dermatitis. Late toxicity is not reported in the source, which matters most for a boost delivered near bowel and for pts followed nearly a decade.
Neoadjuvant dose escalation in LARC has repeatedly raised pCR without translating to survival; this trial reports the mirror image, a null pCR (15.2% vs 18.4%) with survival separation. The result also sits against the TNT era, where systemic intensification rather than RT dose is the current lever, and the chemo-receiving subgroup here showed no additional benefit.
The survival claim is a secondary-endpoint result from 51 vs 55 pts, so a handful of events moves each HR, and no confidence intervals are reported in the source. The driving subgroup is defined by non-randomized chemotherapy receipt, and the higher rate of curative treatment in the SIB arm (89.1% vs 78.4%) is itself a plausible route to the OS difference independent of dose.
A pelvic boost has a defensible mechanism for LC 87.1% vs 70.1% and essentially none for MFS 70.8% vs 47.2%. The authors attribute the distant benefit to intensified control of micrometastases; the simpler reading is that a small trial with a large curative-treatment imbalance produced correlated secondary endpoints.
| Endpoint | SIB-CRT | CRT | Effect |
|---|---|---|---|
| DFS | 70.8% | 47.4% | HR 0.46, P=0.013 |
| OS | 74.3% | 48.9% | HR 0.43, P=0.008 |
| MFS | 70.8% | 47.2% | HR 0.48, P=0.017 |
| LC | 87.1% | 70.1% | HR 0.40, P=0.038 |
| CSS | 77.4% | 57.2% | P=0.027 |
| pCR | 15.2% | 18.4% | P=0.695 |
CONSORT flow
Randomized phase 2, N=106, primary endpoint (pCR) missed; survival gains are secondary endpoints with wide implied precision and a non-randomized chemo subgroup driving them.
- Does SIB add anything on a total neoadjuvant therapy backbone n=37 · primary completion 2026-05 · SIB-SCRT plus CAPOX and PD-1 in high-risk LARCn=156 · primary completion 2026-12 · randomises GTV SIB 58.75 vs 50 Gy/25f for CRrecruiting THeragnostic Utilities for Neoplastic DisEases of the Rectum by MRI Guided Radiotherapy Phase NAn=179 · primary completion 2027-01 · RT dose escalation gated by early regression index
- Late GI and GU toxicity of the boost beyond 9 years active Safety of a Boost (CXB or EBRT) in Combination With Neoadjuvant Chemoradiotherapy for Early Rectal Adenocarcinoma Phase 3n=148 · primary completion 2023-06 · safety endpoint for CXB vs EBRT boost after nCRTrecruiting Standard Dose Versus High Dose of Radiotherapy in Rectal Preservation With Chemo-radiotherapy in Rectal Cancer Patients Phase 3n=162 · primary completion 2026-12 · 62 Gy vs 50.4 Gy phase 3, dose-escalation toxicity
- Whether the curative-treatment rate imbalance explains the OS gap
📚 Sources · 📄 1 paper
Abstract
Proactive immune cell sparing SBRT (NCT04273893) NCT04273893
PREPRINTnot peer-reviewed
ForEarly-stage NSCLC, inoperable or declining surgery, SBRT without systemic therapy
13.4% (5.3%)
95% CI 2.8 to 24.0; p = 0.01
TL;DRImmune-sparing lung SBRT planning cut ALC loss: overall improvement 13.4% (95% CI 2.8-24.0), G3 lymphopenia 0% vs 15.4%; survival trend unpowered.
The dosimetric lever is low-dose spill, not the target: V5 to thoracic spine fell 87% and LN stations 58% with lung V5 down only 8%, all within RTOG 0813/0915 criteria. Benefit concentrated in central tumors (29.5% ALC gain) and was absent for peripheral PTV <20cc, so arc and beam-angle choices for central SBRT are where this plan change applies.
In a central early-stage NSCLC going to 5-fx SBRT without systemic therapy, this supports treating heart, great vessels, thoracic spine and LN stations as low-dose avoidance structures; it does not change planning for small peripheral PTVs under 20cc or establish a survival gain. The longer read
The lever is low-dose spill, not target coverage: thoracic spine V5 fell 87% and LN-station V5 58% with lung V5 down only 8%, inside RTOG 0813/0915 criteria. Gains concentrated in central tumors (29.5% ALC improvement) and vanished for peripheral PTV <20cc, so beam and arc choices for central SBRT are where this applies.
16 details
Randomized phase II, 1:1, stratified by tumor location, permuted blocks, not masked. Enrolled Feb 2020 to Apr 2023; 55 randomized, 51 analyzed (25 vs 26). Survival and subgroup analyses were unplanned and exploratory.
Early-stage NSCLC (AJCC v8), ECOG 0-2, unable or unwilling to undergo surgery; recurrent NSCLC eligible. Excluded RT within 2 yr and systemic therapy within 1 yr prior or 6 mo after. Median age 74 both arms.
45-60 Gy in 5 fx (majority 60 Gy/5), IMRT or VMAT, 4DCT ITV plus 5mm radial / 8mm sup-inf PTV margin. Optimized plans met standard RTOG 0813/0915 criteria while minimizing dose to heart, great vessels, thoracic spine and lymph-node-stations, contoured to a 40 cGy/fx low-dose envelope.
Primary: in vivo lymphocyte depletion at end of treatment, 4 wk and 6 mo; safety/toxicity (co-primary). Algorithm performance reported separately. OS and EFS descriptive only.
Central tumors drove the effect (29.5% overall ALC improvement, p=0.004); peripheral PTV <20cc showed no difference. G3 lymphopenia 0% vs 15.4% (p=0.04).
| Timepoint | Optimized | Standard | Between-group diff |
|---|---|---|---|
| End of SBRT | -16% | -31% | 15.1% (3.7-26.5), p=0.01 |
| 4 weeks | -22% | -34% | 12.3% (0.2-24.5), p=0.05 |
| 6 months | -16% | -26% | 10.4% (-4.7-25.5), p=0.17 |
| Population · endpoint | Optimized | Standard | p |
|---|---|---|---|
| All pts · OS | 82.1% | 65.1% | 0.23 |
| All pts · EFS | 62.3% | 56.7% | 0.27 |
| Tx-naive · OS | 93.4% | 69.4% | 0.14 |
| Tx-naive · EFS | 75.0% | 59.8% | 0.10 |
G3 AEs 2 (lung infection) optimized vs 4 standard (dyspnea, hypoxia, lung infection); all recovered. No G2+ pneumonitis or G4+ events in either arm.
Both arms sat inside RTOG 0813/0915 planning criteria, so the comparison isolates immune-OAR avoidance on top of current SBRT constraints. Prior lymphopenia-outcome links in thoracic RT are largely associative; this is a randomized test that planning alone moves ALC.
Arm imbalance in central (36.0% vs 23.1%) and treatment-naive (64.0% vs 88.5%) pts biases the survival comparison. Tx-naive OS reported as 93.4% and 94.1% in different sections. LN V5 OS split is a non-randomized dosimetric stratification.
Establishes feasibility and an ALC effect, not a clinical one. Whether sparing lymphocytes during SBRT translates to EFS/OS, or to better IO response when combined, needs the multi-institutional powered trial the authors call for.
Preprint, small randomized phase II with unmasked lymphocyte surrogate primary; survival analyses unplanned and unpowered. Arm imbalance in central and treatment-naive pts.
- Does lymphocyte-sparing SBRT improve EFS or OS in a powered trial?
- Does immune-sparing planning enhance SBRT plus immunotherapy outcomes?
- Optimal dose limits for thoracic spine and lymph-node-stations
📚 Sources · 📄 1 paper
Abstract
Consolidative TRT + Atezolizumab Maintenance in ES-SCLC NCT04462276
ForES-SCLC with ≥SD after carbo-etoposide-atezolizumab induction, unselected
6.7 vs 13.4 mo
HR 1.55 (95% CI 0.90-2.69), P = .34; primary end point not met
TL;DRPrimary EP missed: mOS 6.7 vs 13.4mo (HR 1.55, P=.34) with consolidative 30Gy/10fx; trial halted for fatal SAEs.
The failure is toxicity, not tumor control: PFS was identical (2.4 vs 2.6 mo) while fatal AEs hit 19.4% vs 3.0%, and TRT carried an AE HR of 2.47 (1.15-5.32). Dose was modest (30 Gy/10 fx, postinduction volumes, below OAR thresholds), so de-escalating the plan is not the obvious fix; baseline DLCO SB and radiation-induced lymphopenia are the selection levers.
In unselected ES-SCLC responding to chemoimmunotherapy, this argues against offering consolidative thoracic RT during atezolizumab maintenance off-trial, particularly with low baseline DLCO; it says nothing about limited-stage disease or thoracic RT given without concurrent IO maintenance. The longer read
The dose was already conservative (30 Gy/10 fx, postinduction volumes, below OAR thresholds) and no dosimetric parameter tracked with serious events, so de-escalating the plan is not an obvious mitigation. Concurrent vs sequential timing did not change AE risk either. Selection (baseline DLCO SB 45.3 vs 56.7 in fatal-AE pts) and lymphocyte-sparing planning are the live levers.
Arm B's mOS of 13.4 mo and 56.6% 1-yr OS beat the IMpower133 atezolizumab benchmark, so maintenance alone was performing normally and the detriment is attributable to the added modality. TRT carried an AE HR of 2.47 (1.15-5.32) while longer atezolizumab exposure did not, which supports continuing maintenance unmodified rather than adding thoracic RT off-trial.
12 details 5 trials watching
Multicenter open-label phase 2 randomized trial (TREASURE, AIO-TRK-0320) at 20 sites in Germany and Austria, accrual September 2020 to August 2022, follow-up to September 2024, database lock April 2025, post hoc OS update April 2026. Planned 104 randomized for 80% power on a 20% absolute 12-month OS improvement; halted at 68 on SMC recommendation.
ES-SCLC with at least stable disease after induction carboplatin-etoposide-atezolizumab. 34 per arm, mean age 63.3 vs 65.6 y, 63.2% male, ECOG 0-1, thoracic PR in 82.4% overall. Randomization stratified by brain metastases, induction response, and prophylactic cranial irradiation.
30 Gy in 10 fractions to the postinduction thoracic primary and involved lymph node volume. Doses and volumes sat within or below typical clinical ranges and below established organ-at-risk thresholds, and concurrent versus sequential delivery relative to atezolizumab made no difference to AE occurrence.
Primary: overall survival from randomization, by stratified log-rank and multivariable Cox in the ITT population. Secondary: PFS and frequency plus severity of AEs and SAEs. Sensitivity analyses in per-protocol and an adjusted ITT excluding fatal AEs.
SAEs 61.3% vs 18.2% (P < .001) and fatal AEs 19.4% vs 3.0% (P = .04), dominated by infection and respiratory events. Grade 3 or greater trAE rate in arm A (26%) exceeded published benchmarks for atezolizumab monotherapy and for consolidative TRT without immunotherapy, which is the argument for an interaction between the two modalities rather than either alone.
Arm B tracked or beat the IMpower133 atezolizumab benchmark (13.4 mo and 56.6% 1-yr vs 12.3 mo and 51.7%), so the control arm was not underperforming; arm A fell well below it. Prior prospective single-arm series of TRT added to chemoimmunotherapy reported no toxicity increase, while randomized PACIFIC-2 and CheckMate-73L in NSCLC both showed more fatal infections in the concurrent thoracic RT plus IO arms.
Early termination at 68 of 104 makes every efficacy estimate exploratory, and the OS confidence interval (0.90-2.69) crosses 1. Causal attribution of the deaths was contested: investigators called 4 of the arm A fatalities unrelated, the SMC reclassified 3 of those as possibly or probably related. Risk-factor analyses (DLCO SB, GTV, dosimetry) are small-N and post hoc.
The PFS/OS dissociation is the load-bearing observation. Identical PFS argues the RT did nothing systemically, so the OS gap most plausibly reflects treatment-related deaths rather than faster progression, a reading the adjusted-ITT sensitivity analysis complicates by remaining consistent after excluding fatal AEs.
| Endpoint | Arm A (+TRT) | Arm B | P |
|---|---|---|---|
| Any toxic effects | 30 (96.8%) | 25 (75.8%) | .02 |
| SAEs | 19 (61.3%) | 6 (18.2%) | <.001 |
| trAEs | 71.0% | 30.3% | .001 |
| trSAEs | 29.0% | 6.1% | .01 |
| Fatal AEs | 6 (19.4%) | 1 (3.0%) | .04 |
CONSORT flow
Randomized, prespecified OS primary, halted early for fatal SAEs; result contests the single-arm safety data that encouraged consolidative TRT in the IO era.
- Can DLCO or lymphocyte kinetics select pts who tolerate consolidative TRT active Thymus Dosimetric and Morphologic Predictors of Radiation-Induced Lymphopenia in Stage III NSCLCn=450 · primary completion 2027-12 · thymus dose + morphology as RT lymphopenia predictors
- Does lymphocyte-sparing planning mitigate the infection signal n=55 · primary completion 2023-05 · SBRT planning optimized to cut lymphocyte depletionn=212 · primary completion 2026-11 · randomises lymphocyte-sparing vs conventional thoracic RT
- Is the late 2-year OS crossover real or small-numbers noise recruiting Phase II Trial of Consolidative Thoracic Radiotherapy for ES-SCLC After Standard Care of Chemo-immunotherapy Phase NAn=104 · primary completion 2025-09 · consolidative TRT after chemo-IO, PD-L1 maintenancerecruiting Association of Thoraco-mediastinal Radiotherapy With Maintenance Immunotherapy Treatment With Atezolizumab Phase 2n=37 · primary completion 2026-12 · consolidative TRT + atezolizumab maintenance in ES-SCLC
📚 Sources · 📄 1 paper
Abstract
10-yr SBRT Survival/Toxicity (Meier et al.)
ForLocalised low- or intermediate-risk prostate, no ADT, prostate volume up to 100 cc
TL;DR10-yr RFS 90% overall (94% LR, 86% IR) with 40 Gy/5 fx; grade 3 late toxicity 1.4-1.5%, no grade 4-5.
Two-thirds of relapses fell between 5 and 10 yr, so the reassurance PACE-B gives at 5 yr is provisional. The unfavorable IR subgroup sits at 77% (60-93) vs 92% for favorable IR (p=0.002), which is where the ADT-with-SBRT question actually lives, not in the pooled 86% IR number.
In unfavorable intermediate-risk prostate considered for 40 Gy/5 fx monotherapy, the 77% 10-yr RFS (vs 92% favorable IR) is the number that informs an ADT discussion; the favorable IR and low-risk data do not carry that concern. The longer read
Two-thirds of relapses fell between 5 and 10 yr, so PACE-B's 5-yr reassurance is provisional. Within IR, unfavorable pts sat at 77% (60-93) vs 92% favorable (p=0.002) with 40 Gy/5 fx and no ADT, which is where the ADT-addition question lives, not in the pooled 86%.
11 details 4 trials watching
Investigator-initiated phase 2 nonrandomized trial across 21 centers (community, regional, academic), enrolling Jan 2008 to Apr 2010. 310 evaluable pts, median age 68, median follow-up 9 yr. Kaplan-Meier estimation with log-rank comparison of LR vs IR.
172 low-risk (T1b-T2a, Gleason 6, PSA under 10) and 138 intermediate-risk (T1b-T2b, Gleason 7 or Gleason 6 with PSA 10-20), all confirmed by central pathologic review. IR pts subclassified favorable vs unfavorable by MSK criteria. Prostate volume up to 100 cc allowed; prior TURP and baseline AUA score were not exclusions.
40 Gy in 5 fractions (8 Gy x 5, equivalent to ~100 Gy at 2 Gy/fx assuming a/b = 2) on a noncoplanar robotic platform. Fiducial tracking with translational and rotational intrafractional motion correction was mandatory. Androgen suppression was not allowed, so the outcomes are RT-attributable.
Relapse defined as biochemical failure (nadir + 2), clinical failure, or administration of any salvage, antiandrogen, or systemic therapy. Late toxicity was physician-reported, CTCAE v3, events beyond 3 mo. Day 0 was the last day of treatment.
10-yr OS 84% (76-91). Freedom from local failure 96% (93-99) overall. The separation that matters is within IR: favorable 92% vs unfavorable 77%, p = 0.002, whereas LR vs IR overall was not significant (p = 0.19).
| Group | 10-yr RFS (95% CI) | p |
|---|---|---|
| Whole group | 92% (87-96) | n/a |
| Low risk | 94% (89-99) | 0.19 (LR vs IR) |
| Intermediate risk | 86% (77-94) | 0.19 (LR vs IR) |
| MSK favorable IR | 92% (90-100) | 0.002 (fav vs unfav) |
| MSK unfavorable IR | 77% (60-93) | 0.002 (fav vs unfav) |
Four pts had five grade 3 events, all GU, and no grade 4-5 events occurred. Cumulative 10-yr grade 3 rates were 1.4% LR and 1.5% IR, far below the 10% rate the trial deemed acceptable. Grade 2+ GU 14% exceeds grade 2+ GI 2.1% by roughly sevenfold; no new late grade 3+ events after year 5.
IR relapse-free survival (86%) sits above the 74-78% 10-yr RFS of dose-escalated EBRT in RTOG 0126, and the authors note an updated HYPO-RT-PC now shows superior 10-yr RFS in the 6.1 Gy x 7 arm. Toxicity matched Fuller's CyberKnife trial but was lower than the PACE-B SBRT arm and PATRIOT, both of which treated substantial fractions on a conventional linac.
The toxicity advantage over PACE-B and PATRIOT is confounded by platform, and the sponsor makes that platform, so the comparison cannot separate tracking from delivery-era and case-mix differences. Toxicity is physician-reported CTCAE only, with no patient-reported instrument, which understates GU bother relative to the EPIC-based comparators. Comparator EBRT series (RTOG 0126) predate modern IGRT.
The durability question, not the toxicity question, is what 10 yr answers here: two-thirds of relapses occurred between 5 and 10 yr, in this trial and in Fuller's. That timing means a 5-yr non-inferiority readout is structurally optimistic for both arms, and it reframes what PACE-B's 5-yr result can and cannot settle.
Single-arm nonrandomized phase 2, no concurrent comparator; sponsor-funded with device-specific delivery. Extends existing 5-yr SBRT data rather than testing a new question.
- Whether ADT improves outcomes for unfavorable intermediate-risk pts receiving SBRT n=310 · primary completion 2025-12 · phase 3 prostate SRT +/- short-term ADT, bDFSn=222 · primary completion 2027-12 · SBRT without ADT in UIR, Decipher-gatedn=392 · primary completion 2030-04 · SBRT + 6-mo ADT vs SBRT alone, NCCN UIR cohort
- Whether intrafractional tracking, not platform, drives the toxicity difference recruiting Is Adaptive SBRT for Prostate vs Image-guided Radiotherapy a True Evolution (ASPIRE) Phase 3n=320 · primary completion 2030-02 · adaptive vs image-guided SBRT, urinary endpoint
- 10-yr PACE-B relapse rates vs conventional fractionation
📚 Sources · 📄 1 paper
ARTO NCT03449719
ForOligometastatic CRPC, ≤3 sites, no prior systemic therapy for CRPC
TL;DRAdding SBRT to all met sites improved OS: median NR vs 50 mo, HR 0.55 (0.33-0.92), p=0.021 in omCRPC.
The prescription is the transferable part: 1-5 fractions at BED ≥100 Gy to ALL sites, not an index lesion, so this is ablative comprehensive MDT rather than debulking. That, plus a control arm on a modern ARSI backbone, is what separates ARTO from the hormone-sensitive MDT trials and moves the question from omission to comprehensive ablation in CRPC.
In mCRPC with three or fewer sites and no prior CRPC-directed systemic therapy, this supports discussing comprehensive ablative SBRT alongside starting abiraterone; it does not extend to polymetastatic disease or to pts already progressing through an ARSI. The longer read
The transferable parameter is the prescription: 1-5 fractions at BED ≥100 Gy to ALL sites, not an index lesion. If a lesion cannot reach that dose, the pt has not had the tested intervention. This moves comprehensive ablative MDT from PSA-directed to survival-directed intent in CRPC.
The abiraterone plus ADT backbone was identical in both arms, so the OS difference is not a systemic-therapy effect and does not change drug choice or sequencing. What changes is the referral: a pt starting abiraterone for CRPC with ≤3 sites is now a radiotherapy conversation, not systemic therapy alone.
Also covered Jun 12
9 details 5 trials watching
Multicentre phase 2 randomised open-label trial, 16 academic and community centres in Italy, 1:1 by random permuted blocks, stratified by centre, ECOG PS and number of metastases. Enrolment Jan 2, 2019 to Sept 7, 2022; median follow-up 53 months (IQR 43-60). ITT analysis.
Age ≥18 with prostate adenocarcinoma and metastatic castrate-resistant disease, no more than three metastatic sites, and no previous systemic therapy for the mCRPC state. N=157 (control 82, experimental 75). No race or ethnicity data collected.
Both arms received ADT plus oral abiraterone acetate 1000 mg daily. The experimental arm added SBRT; the systemic backbone was identical, so the contrast isolates the radiotherapy.
SBRT delivered to all sites of metastatic disease in one to five fractions at a biologically effective dose ≥100 Gy. Comprehensive ablative intent, not treatment of an index lesion.
Primary: 6-month biochemical response (PSA decline ≥50% from baseline), reported previously. After the primary was met the power calculation was updated post-hoc for overall survival, finalised before unmasking; this report is an unplanned long-term OS analysis.
Most common grade 3-4 events were infectious complications (five control, zero experimental) and cardiovascular disorders (three each). One treatment-related death, in the control group, from myocardial failure. No excess grade 3-4 toxicity attributable to SBRT in the reported events.
STOMP and ORIOLE established MDT in hormone-sensitive oligometastatic disease without a systemic backbone, and SABR-COMET tested SABR across mixed histologies. ARTO is the randomised test in castrate-resistant disease with an ARSI given to both arms, which is the setting those trials leave open.
Open-label with no sham, and the OS power calculation was revised after the primary read, so the alpha spent on this comparison is not the trial's original design. The experimental median is not reached, meaning the reported HR rests on a control-arm curve that is itself only partly mature at 53 months.
A survival signal from comprehensive ablation on top of a modern ARSI backbone is the strongest randomised argument yet that MDT in CRPC is doing more than delaying PSA progression. What it does not settle is whether the benefit tracks the ablative dose, the completeness of coverage, or simply the favourable biology of pts whose disease stayed oligometastatic into castration resistance.
See the OS figures above; per-arm event counts beyond the medians and HR are not reported in source.
CONSORT flow
Randomised phase 2, but the OS analysis is unplanned with post-hoc power revision and the primary endpoint was 6-month PSA response. N=157.
- Does the OS benefit hold in a prespecified phase 3? active Prostate-cancer Treatment Using Stereotactic Radiotherapy for Oligometastases Ablation in Hormone-sensitive Patients Phase 3n=550 · primary completion 2026-06 · randomised phase 3, SBRT to all mets in mHSPCrecruiting Veterans Affairs Seamless Phase II/III Randomized Trial of STAndard Systemic theRapy With or Without PET-directed Local Therapy for Oligometastatic pRosTate Cancer Phase 2/3n=464 · primary completion 2026-09 · phase 2/3 SST +/- PET-directed local therapyrecruiting Metastasis-directed Therapy in Oligoprogressive Castration-refractory Prostate Cancer Phase 3n=246 · primary completion 2029-01 · phase 3 MDT in oligoprogressive CRPC, n=246
- Is benefit dose-dependent or driven by completeness of ablation? recruiting HIghly MetAstatic Life Prolonging Therapy-Resistant Prostate Cancer: Role of Stereotactic Radiotherapy for Bone and Lymph Node Metastases (HIMARS) Phase NAn=18 · primary completion 2028-05 · volume-escalated SBRT, defines max tolerated volume
- Does MDT benefit persist with newer ARSIs or PSMA radioligand therapy? n=107 · primary completion 2030-10 · 225Ac vs 177Lu-PSMA-617 with MDT SBRT
📚 Sources · 📄 1 paper
Abstract
DOREMY NCT02106312
ForLocalized translocation-confirmed myxoid liposarcoma, trunk or extremity, resectable
TL;DR5yr LRFS 97.4% after 36Gy/18fx preop RT in myxoid liposarcoma, wound complications 21%, median f/u 66.4mo.
The number that moves the dose decision is 97.4% 5yr LRFS at 36 Gy, matched to a 21% wound complication rate, with only 3% late G3. Dose is 2 Gy daily to 36 Gy preop, standard fractionation, so it transfers directly. This is a de-escalation read confined to translocation-confirmed MLS.
In localized translocation-confirmed myxoid liposarcoma of trunk or extremity going to resection, this supports 36 Gy preop as a discussed option in place of 50 Gy; it does not extend to other soft tissue sarcoma histologies, which were not enrolled. The longer read
36 Gy in 2 Gy daily fractions preop yielded 97.4% 5yr LRFS (95% CI 93.9-100%) at median 66.4 mo, with late G3 in only 3%. Standard fractionation, no special technique required, so the de-escalation from 50 Gy transfers directly in translocation-confirmed MLS.
The surgical read is the wound complication rate: 21% overall, 16% needing intervention, after preop RT at the reduced dose. Whether that beats 50 Gy is untested here (no comparator arm), but it is the number to weigh against reconstruction planning in trunk and extremity resections.
10 details 1 trial watching
Prospective, single-group, phase 2 nonrandomized trial across 9 tertiary sarcoma centers in Europe and the US. Enrollment ran November 2010 to May 2020; data analyzed January to December 2025. Median follow-up 66.4 months (IQR 48.8-87.5).
Adults with biopsy-proven and translocation-confirmed localized myxoid liposarcoma of the trunk or extremity. N=90, mean age 47 (SD 13.1), 50 (56%) male.
Preoperative RT to a reduced dose of 36 Gy in once-daily 2-Gy fractions, followed by resection. Delivered per protocol in all patients. Three pts (3%) did not proceed to surgery because of intercurrent metastatic disease.
Long-term local recurrence-free survival, progression-free survival, disease-specific survival, overall survival, and late toxic effects. No single stated primary endpoint for this long-term analysis.
Wound complications in 18 pts (21%), with 14 (16%) requiring intervention. Late toxic effects were grade 2 in 13 pts (15%) and grade 3 in 3 pts (3%).
The authors argue the long-term data support adopting 36 Gy as an option through shared decision-making, explicitly on the grounds that a phase 3 trial is impractical in a rare cancer. That is an argument about feasibility, not about evidence level, and the reader should price it as such.
Fourteen-year accrual window spans changing surgical and imaging practice, so the wound complication rate reflects a long era rather than current technique. Late toxicity is reported only as pooled grade counts, without organ or site attribution, which limits comparison against 50 Gy series.
| Endpoint | 5yr rate | 95% CI |
|---|---|---|
| Local recurrence-free survival | 97.4% | 93.9-100% |
| Progression-free survival | 81.0% | 72.6-89.4% |
| Disease-specific survival | 89.5% | 82.6-96.4% |
| Overall survival | 88.5% | 81.2-95.8% |
Single-arm phase 2, no randomised 50 Gy comparator; authors concede phase 3 impractical in a rare histology. Long f/u strengthens but does not replace randomisation.
- Wound complication rate vs 50 Gy in a randomised comparison n=300 · primary completion 2031-01 · prospective MLS registry, 36Gy vs 50Gy preop arms
- Whether dose reduction extends to other translocation-driven sarcoma subtypes
- Local control beyond 10 years
📚 Sources · 📄 1 paper
Abstract
REVELUTION
ForNon-metastatic intermediate/high-risk prostate cancer receiving definitive RT + ADT
68.9 mm³ adjusted mean difference
Leuprolide vs relugolix; crude 56 vs 25 mm³. CI/p not reported in source
TL;DRAdjusted 12-mo total plaque volume rose 68.9 mm³ more with leuprolide vs relugolix in men getting prostate RT.
Reported via UroToday →
Every man here got prostate ± pelvic nodal RT, so this is an RT-clinic decision, not a med-onc one: for the 6-month ADT course you prescribe alongside definitive RT, the agonist added 68.9 mm³ of adjusted total plaque volume at 12 months, driven by non-calcified plaque. A radiation-alone control cohort was enrolled in parallel, though its comparison was not reported in source.
For the intermediate/high-risk man starting definitive prostate RT with 6+ months of concurrent ADT, particularly with elevated ASCVD 10-year risk, this supports weighing agent choice on cardiovascular grounds; it says nothing about ADT duration or about men on ADT without RT. The longer read
The entire cohort received prostate ± pelvic nodal RT, so this is your ADT prescription, not someone else's: the agonist added 68.9 mm³ of adjusted total plaque volume at 12 months, driven by non-calcified plaque. It moves agent selection for the 6-month course accompanying definitive RT, particularly in men with elevated baseline ASCVD risk.
This supplies the missing mechanism under HERO's MACE difference: comparable testosterone suppression, divergent coronary plaque trajectory, with the signal in non-calcified rather than calcified plaque. It argues the agonist-antagonist cardiovascular gap is pharmacologic rather than an artifact, though the population here is non-metastatic and radiotherapy-treated.
Also covered Sep 30
11 details 4 trials watching
Single-institution, parallel-cohort, open-label randomized trial across four Emory-affiliated centers, enrolling June 2020 to 2024. ADT-eligible pts randomized 1:1 relugolix vs leuprolide, stratified by ASCVD 10-year risk score; a parallel prospective RT-alone cohort was enrolled as control.
94 men with non-metastatic prostate cancer, intermediate and high risk, all treated with pelvic radiotherapy to the prostate with or without pelvic nodes. Lower-risk men eligible for definitive RT alone without planned ADT formed the parallel arm.
Relugolix 360 mg day 1, then 120 mg daily; leuprolide in 3-month depots. ADT given for at least six months, longer by cancer risk tier.
All pts received pelvic radiotherapy to the prostate with or without the pelvic lymph nodes. Dose, fractionation and technique are not reported in source.
Primary: change in total plaque volume. Secondary: changes in plaque subtypes (non-calcified, calcified, low-attenuation). Serial CCTA at baseline (within 7 days of treatment start) and 12 months, blinded to arm, quantified by the automated HeartFlow tool; 12-month mean difference by ANCOVA adjusted for age, statin use and baseline plaque volume.
The adjusted total-plaque-volume difference of 68.9 mm³ favouring relugolix was driven mainly by non-calcified plaque; calcified and low-attenuation plaque showed no significant difference with low absolute change. Per-arm CIs and p-values are not reported in source.
| Measure | Leuprolide | Relugolix |
|---|---|---|
| Total plaque volume, crude difference | 56 mm³ | 25 mm³ |
HERO (2020) showed a lower MACE rate with relugolix vs leuprolide and drove the FDA approval, but offered no mechanism, since both agents suppress testosterone comparably and share the hypogonadal metabolic profile. REVELUTION supplies the candidate mechanism, accelerated coronary atherosclerosis under GnRH agonism, consistent with the 2010s observational signal that agonists carry higher cardiovascular risk than orchiectomy.
The imaging endpoint is validated as a predictor of MACE, not a substitute for it, and 12 months is short for plaque trajectories. The parallel RT-alone cohort was not randomized against either ADT arm, so the no-hormone comparison is observational and cannot isolate radiotherapy's own contribution to plaque change.
If the agonist-antagonist difference is real and mechanistic, the decision it moves is which ADT agent accompanies definitive RT in a man with baseline cardiovascular risk, not whether to give ADT at all. It does not establish that changing agent prevents events; that inference still rests on HERO.
Small single-institution randomized trial with an imaging surrogate (plaque volume), not clinical MACE. Supplies a mechanism for HERO rather than independent outcome evidence.
- Does the plaque difference translate to fewer clinical cardiovascular events recruiting Effects of Relugolix vs Leuprolide on Cardiac Function in Patients With Prostate Cancer Phase 2n=70 · primary completion 2027-12 · relugolix vs leuprolide, cardiac MRI + performancerecruiting REVELUTION-2: Relugolix+Abiraterone Acetate (AA) Versus Leuprolide+AA Cardiac Trial Phase 3n=72 · primary completion 2029-07 · relugolix vs leuprolide + AA, cardiac CTA, pelvic RT
- Plaque trajectory beyond 12 months and after ADT completion n=100 · primary completion 2026-12 · randomised CCTA vs usual care, ADT >12mo planned
- Does pelvic radiotherapy itself contribute to coronary plaque change n=200 · primary completion 2029-11 · ADT cardiotox cohort enrolls with and without RT
📚 Sources · 📄 1 paper
Abstract
ARTO NCT03449719
ForOligometastatic CRPC, ≤3 nonvisceral lesions, starting first-line abiraterone
92% v 68.3%
OR 5.34 (95% CI, 2.05 to 13.88; P = .001)
TL;DRAdding SBRT to abiraterone in oligometastatic CRPC: biochemical response 92% vs 68.3%, OR 5.34; PFS HR 0.35.
Surfaced from a review's discussed trials
The systemic backbone is fixed (AAP both arms), so the entire effect is RT-attributable: PFS HR 0.35 for ablating ≤3 nonvisceral lesions. That isolates the metastasis-directed question in castration-resistant disease, where prior randomized MDT data sit in the hormone-sensitive setting. Dose and fractionation are not in the source text, which limits direct transfer.
In castration-resistant pts with three or fewer nonvisceral metastases starting first-line abiraterone, this supports considering metastasis-directed SBRT concurrently; it does not extend to visceral, higher-volume, or hormone-sensitive metastatic disease. The longer read
The randomized contrast is SBRT alone, since AAP is fixed in both arms: PFS HR 0.35 (95% CI 0.21-0.57) for ablating ≤3 nonvisceral lesions. This moves the offer-MDT-at-castration-resistance decision, though dose, fractionation and target volume are absent from the source text, so technique transfer cannot be judged.
Systemic management is unchanged: both arms received first-line abiraterone and prednisone, so nothing here alters drug choice or sequencing. The read is whether to involve radiation oncology at the start of AAP in low-volume CRPC, with progression deferred (HR 0.35) but no survival endpoint reported.
Also covered Jul 7
8 details 5 trials watching
Multicenter randomized phase 2, 1:1 allocation, N=157 enrolled January 2019 to September 2022. Median follow-up not reported in source.
Oligometastatic castrate-resistant prostate cancer, defined as three or fewer nonvisceral metastatic lesions. Visceral disease excluded by definition.
Both arms received abiraterone acetate and prednisone (AAP). The experimental arm added concomitant SBRT, so AAP is a fixed backbone and the randomized contrast is radiotherapy alone.
SBRT to all sites of disease, delivered concomitantly with AAP. Dose, fractionation and target-volume detail are not reported in the source text, which gates how directly the result transfers to a given SBRT practice.
Primary: biochemical response, PSA decrease ≥50% from baseline at 6 months. Secondary: complete biochemical response (PSA <0.2 ng/mL at 6 months) and progression-free survival. No survival endpoint reported.
No toxicity reported in source, so the added burden of ablating up to three lesions is unquantified. PSA endpoints are mechanically sensitive to removing PSA-producing deposits, and the 6-month timepoint precedes any durability read.
STOMP and ORIOLE established the randomized signal for metastasis-directed therapy in hormone-sensitive oligometastatic disease. ARTO's addition is that the signal persists on an ARSI backbone in castration-resistant disease, a setting those trials did not test.
The PFS HR 0.35 is the more meaningful of the two results, since it is less mechanically coupled to ablating PSA-producing lesions than the primary endpoint. What remains unsettled is whether deferring progression on an ARSI translates into anything durable, which a phase 2 sized for a 6-month PSA readout cannot answer.
Randomized phase 2 with a 6-month PSA surrogate primary endpoint; no OS, no reported toxicity, and phase 3 confirmation in CRPC is absent.
- Does the PFS benefit translate to overall survival n=102 · primary completion 2027-04 · randomised SBRT in oligomet CRPC on ARSi backbonerecruiting Metastasis-directed Therapy in Oligoprogressive Castration-refractory Prostate Cancer Phase 3n=246 · primary completion 2029-01 · phase 3 MDT in castration-refractory, up to 5 lesions
- SBRT-attributable toxicity when ablating up to three sites recruiting SBRT Versus Hypofractionated Radiotherapy for Biochemically Recurrent or Oligometastatic Prostate Adenocarcinoma Phase 3n=118 · primary completion 2030-01 · phase 3 powered on SBRT toxicity vs hypofx RTrecruiting Fractionated Stereotactic Radiotherapy Plus Second-generation Antiandrogen for Oligometastatic Castration-resistant Prostate Cancer Patients. Phase 2n=51 · primary completion 2030-05 · SBRT + abiraterone/enza in mCRPC, safety endpoint
- Whether benefit holds beyond three lesions recruiting HIghly MetAstatic Life Prolonging Therapy-Resistant Prostate Cancer: Role of Stereotactic Radiotherapy for Bone and Lymph Node Metastases (HIMARS) Phase NAn=18 · primary completion 2028-05 · volume-escalated SRT in high-volume mets, MTV endpoint
📚 Sources · 📄 1 paper
Abstract
ORIOLE NCT02680587
ForHormone-sensitive oligorecurrent prostate ca, 1-3 mets on conventional imaging, ADT-free
19% vs 61%
7/36 vs 11/18, P=.005
TL;DR6-mo composite progression 19% vs 61% with SABR (P=.005); mPFS not reached vs 5.8 mo, HR 0.30.
Surfaced from a review's discussed trials
The actionable RT parameter is target selection, not dose: 16 of 36 SABR pts had PSMA-avid lesions left untreated because planning was blinded to PET, and those men progressed at 38% vs 5% by 6mo (distant MFS 6.0 vs 29.0mo, HR 0.19). That argues total consolidation of PET-avid disease, so PSMA-PET-based planning is the decision this moves.
In hormone-sensitive oligorecurrent prostate cancer with 1-3 conventionally imaged mets and no recent ADT, this supports deferring ADT with SABR to all PET-avid sites; it does not speak to de novo synchronous oligometastatic or castration-resistant disease. The longer read
Target selection, not dose, is the transferable parameter: planning was blinded to PSMA-PET, so 16/36 SABR pts had avid lesions untreated, and they progressed 38% vs 5% at 6mo with distant MFS 6.0 vs 29.0mo (HR 0.19). That argues for PET-based planning and total consolidation of avid disease. Dose and fractionation are not reported in source text.
The comparator here is observation with ADT deferral, not a systemic regimen, so the read is about sequencing: SABR pushed median PFS from 5.8 months to not reached in men deliberately kept off ADT. Whether that delay costs anything downstream is untested at 18.8 months median follow-up.
11 details 5 trials watching
Phase 2, 2-arm randomized trial across 3 US radiation facilities affiliated with one university hospital. 80 men screened, 54 randomized 2:1 to SABR or observation, accrual May 2016 to March 2018, data cutoff May 20 2019. Median follow-up 18.8 months (range 5.8-35.0).
Recurrent hormone-sensitive prostate cancer with 1 to 3 metastases detected on conventional imaging (CT, MRI, or bone scan), asymptomatic, arisen within the prior 6 months, no larger than 5.0 cm. Prior definitive treatment of the primary required; salvage prostate-bed or pelvic RT allowed. No ADT within 6 months of enrollment or 3 or more years total. Median age 68 in both arms; Gleason grade ran higher in the observation arm (mean 8 vs 7).
SABR to metastatic sites, with treatment planning blinded to PSMA-PET, so PET-avid lesions outside the conventional-imaging map were left untreated in 16 of 36 SABR pts. Dose and fractionation are not reported in the source text. Local control 98.9% at 6 months.
Primary: progression at 6 months, a composite of PSA rise, radiographic progression on conventional imaging, symptomatic progression, ADT initiation for any reason, or death. Secondary: SABR toxicity, 6-month local control, PFS, Brief Pain Inventory QoL, and concordance between conventional imaging and PSMA-PET.
No grade 3 or higher adverse events in either arm. No differences in Brief Pain Inventory scores between arms or within either arm over time.
Sits alongside STOMP, the other randomized trial of metastasis-directed therapy versus surveillance in oligorecurrent hormone-sensitive disease, and reaches the same directional conclusion from an independent population. What ORIOLE adds is the PSMA-PET consolidation question, which STOMP's choline-PET-selected design could not isolate.
The composite primary is driven partly by ADT initiation for any reason, a clinician decision made without blinding in an open trial, so the treating team's knowledge of arm allocation can move the endpoint directly. The PET-untreated-lesion comparison is a within-arm post-randomization subgroup (19 vs 16 men), not a randomized contrast, and the men whose conventional imaging missed more disease plausibly had more disease to begin with.
The trial makes two distinct claims and they carry different weight. That SABR beats observation on a 6-month composite in a 54-man phase 2 is a signal, not a standard; that leaving PSMA-avid disease untreated tracks with earlier and more distant failure is the finding that changed how the field plans these treatments, even though it rests on an observational contrast inside one arm.
CONSORT flow
Phase 2, N=54, 6-month composite primary including ADT initiation, median f/u 18.8mo. Hypothesis-generating for MDT; no OS or definitive endpoint.
- Does deferring ADT via SABR change overall survival n=162 · primary completion 2031-04 · randomises RDT alone vs RDT + ADT, PFS primary
- Optimal SABR dose and fractionation for prostate oligometastases recruiting OligoCare TwiCs (Trials Within Cohorts) Trial Comparing Acute Toxicity in Single-fraction vs Multiple-fraction SBRT for Metastasis-directed Treatment (SPRINT) Phase NAn=302 · primary completion 2029-02 · single- vs multi-fraction SBRT, acute toxicity primary
- Does PSMA-PET-guided total consolidation improve outcomes prospectively recruiting Treatment With Darolutamide +/- Radiation Therapy for Patients With a Castration Resistant Cancer and Metastases Detected by Functional Imaging Phase 3n=336 · primary completion 2029-10 · phase 3 darolutamide +/- SBRT to functional-imaging metsn=1000 · primary completion 2030-12 · prospective registry, PSMA PET-guided directed RTrecruiting Metastasis Directed Stereotactic Body Radiotherapy for Oligo Metastatic Hormone Sensitive Prostate Cancer Phase NAn=118 · primary completion 2031-12 · randomised MD-SBRT vs SOC, PSMA-PET-defined 1-3 mets
📚 Sources · 📄 1 paper
Abstract
RADIOSA NCT03940235
ForMetachronous oligorecurrent hormone-sensitive prostate cancer, ≤3 lesions
TL;DRcPFS 32.2 vs 15.1 mo, HR 0.43, adding 6 months of ADT to ablative SBRT in metachronous oligorecurrence.
Surfaced from a review's discussed trials
The RT is nearly free here: one G3 event (left ureter stenosis) and no late toxicity across 105 pts treated to a stated BED >100 Gy, so the entire cost of this decision is 6 months of castration. SBRT alone still gave 15.1-mo cPFS, the benchmark for deferring systemic therapy in a selected pt.
In a man with metachronous oligorecurrence, three or fewer nodal or bone lesions after radical local treatment, this supports adding a short ADT course to ablative SBRT over SBRT alone; it does not extend to synchronous, higher-volume, or castration-resistant disease. The longer read
The RT side of the decision is nearly free: one G3 event (left ureter stenosis) and no late toxicity at a stated BED >100 Gy. The 15.1-mo SBRT-alone cPFS is the benchmark that ablative prescription buys, so a softer nodal dose is not this control arm.
The systemic question is duration, not agent: 6 months of LHRH started within a week of SBRT, 22 G1 events, all resolved. cPFS 32.2 vs 15.1 mo (HR 0.43) with no OS or castration-resistance readout leaves open whether this modifies disease or defers detection.
8 details 5 trials watching
Single-centre randomised open-label phase 2 at the European Institute of Oncology, Milan. 105 pts assigned 1:1 between Aug 1, 2019 and April 30, 2023; median follow-up 31 months (IQR 16-36). Modified intention-to-treat analysis, 3 pts lost to follow-up.
Metachronous oligorecurrent hormone-sensitive disease: biochemical progression after radical local treatment with ≤3 lesions (pelvic nodal, extra-regional nodal, or bone) on next-generation imaging, ECOG 0-1. Median age 70 (IQR 65-75). Stratified by doubling time (≤3 vs >3 mo), node vs bone, and PET vs MRI.
30 Gy in 3 fractions every other day to all oligometastatic sites, or equivalent regimens by site. Stated EQD2 98.6 Gy (α/β 1.5 Gy) and BED >100 Gy, an ablative prescription rather than a symptomatic one, which is the dose the control-arm result belongs to.
6 months of ADT with an LHRH analogue in the combination arm, begun within 1 week before SBRT; no ADT in the control arm. The RT backbone is fixed across arms, so the randomised variable is the short systemic course alone.
Primary: clinical progression-free survival, assessed in 51 pts per group. No overall survival, ADT-free survival, or castration-resistance readout is reported in source.
Radiation contributed one G1 GI event; the only G3 was a left ureter stenosis in the combination arm, with no late toxicity in either group. The 22 G1 events were ADT-attributed and had resolved by last follow-up, so the harm ledger sits with the systemic course, not the RT.
STOMP and ORIOLE established MDT against observation in metachronous oligorecurrence, partly on the strength of keeping men off systemic therapy. EXTEND tested the mirror-image addition, MDT layered onto hormone therapy. This is the first randomised trial in this setting to report improved cPFS for the combination.
Progression was assessed unmasked, and PSA suppression from the randomised ADT gates the restaging that defines the event. Median follow-up sits below the combination arm's median cPFS of 32.2 mo, so the tail after testosterone recovery is thin. No biomarker separates the pts who would do well on SBRT alone.
Local and systemic therapy read as additive here rather than redundant, but the trade is priced in cPFS only. Whether 6 months is the right duration, and for whom SBRT alone suffices, is exactly what the investigators leave to future biomarker work.
CONSORT flow
Randomised, prespecified primary cPFS hit (HR 0.43). Single-centre, N=105, surrogate composite endpoint, so it supports adding short ADT to MDT rather than establishing it.
- Optimal ADT duration alongside metastasis-directed SBRT active Testing the Addition of the Drug Relugolix to the Usual Radiation Therapy for Advanced-Stage Prostate Cancer, The NRG Promethean Study Phase 2n=194 · primary completion 2029-02 · SBRT +/- relugolix vs placebo in oligomet CSPCn=162 · primary completion 2031-04 · randomises RDT +/- ADT in radiorecurrent oligomet CSPC
- Biomarkers identifying pts who do well with SBRT alone active Immune Response Evaluation in Oligorecurrent and Oligoprogressive Prostate Cancer Patients Treated With SBRT Phase NAn=40 · primary completion 2026-07 · immune profiling of SBRT + ADT in oligorecurrence
- Whether cPFS benefit translates to OS or delayed castration resistance active Prostate-cancer Treatment Using Stereotactic Radiotherapy for Oligometastases Ablation in Hormone-sensitive Patients Phase 3n=550 · primary completion 2026-06 · phase 3, n=550, SBRT + SOC in oligomet HSPCrecruiting Metastasis Directed Stereotactic Body Radiotherapy for Oligo Metastatic Hormone Sensitive Prostate Cancer Phase NAn=118 · primary completion 2031-12 · phase 3 MD-SBRT vs standard tx, failure-free survival
📚 Sources · 📄 1 paper
Abstract
NRG Oncology RTOG 0539 NCT00895622
ForWHO grade 1-3 meningioma, newly diagnosed or recurrent, any resection extent
TL;DR10-yr PFS 85.2% observed low-risk, 72.2% intermediate-risk at 54 Gy, 42.5% high-risk at 60 Gy.
The transferable RT read is the target: 54 Gy/30 fx for intermediate-risk and 60 Gy/30 fx for high-risk, with grade 3+ RT-attributed toxicity 9.6% and 15.1%. Recurrent grade 1 salvaged with RT reached only 67.0% 10-yr OS, worse than upfront grade 2 post-GTR at 91.0%, which argues against deferring RT in a grade 1 you expect to recur.
In newly diagnosed WHO grade 2 meningioma after GTR, this supports upfront 54 Gy while NRG BN003 and ROAM read out; it does not speak to observation in that group, since no untreated grade 2 arm was enrolled. The longer read
The transferable parameters are 54 Gy/30 fx intermediate-risk and 60 Gy/30 fx high-risk, with grade 3+ RT-attributed toxicity of 9.6% and 15.1%. Recurrent grade 1 salvaged with RT reached only 67.0% 10-yr OS vs 91.0% for upfront grade 2 post-GTR, which argues against deferring RT in a grade 1 likely to recur.
Extent of resection carried more weight than histology: STR vs GTR gave PFS HR 2.58 (1.09-6.11) and OS HR 3.38 (1.28-8.91) on multivariable analysis. Even in observed low-risk grade 1 disease, 10-yr PFS was 88.0% after GTR vs 72.7% after STR, so a Simpson-grade decision at the first operation still shows at 10 years.
10 details 4 trials watching
Multi-arm prospective phase 2 trial (NCT00895622) of risk-adapted management, not randomised: each risk group followed its own assigned strategy. 244 consented, 165 eligible and treated per protocol. Original endpoint was 3-yr PFS, previously reported; this is the mature analysis with data cutoff 8/15/2023 and median follow-up 12.1, 12.0 and 11.1 years across the three cohorts.
Adults ≥18 with Zubrod 0-1 and histologically confirmed unifocal WHO grade 1-3 meningioma, newly diagnosed or recurrent, any resection extent, with centrally confirmed pathology. Median age 56, 62 in the high-risk group; 65.5% female overall. Recurrent disease made up 30.8% of the intermediate and 47.2% of the high-risk cohorts.
Group 1 (grade 1 post-GTR/STR) was observed only. Group 2 (recurrent grade 1, or newly diagnosed grade 2 post-GTR) received 54 Gy in 30 fractions. Group 3 (newly diagnosed grade 2 post-STR, newly diagnosed grade 3, or recurrent grade 2/3) received 60 Gy in 30 fractions.
The gradient tracks risk assignment cleanly at 10 years, and the two Cox covariates that survive adjustment are recurrent disease and subtotal resection, both for PFS and OS. See the cohort and covariate tables above.
| Cohort | Management | 10-yr PFS | 10-yr OS | 10-yr cum. incidence progression |
|---|---|---|---|---|
| Low (grp 1, n=60) | Observation | 85.2% (75.7-94.8) | 94.1% (87.6-100) | 8.9% (3.2-18.2) |
| Intermediate (grp 2, n=52) | RT 54 Gy | 72.2% (59.2-85.1) | 84.7% (74.2-95.2) | 21.2% (10.8-33.9) |
| High (grp 3, n=53) | RT 60 Gy | 42.5% (28.7-56.3) | 51.1% (37.0-65.2) | 39.3% (25.8-52.5) |
| Covariate | PFS HR (95% CI), p | OS HR (95% CI), p |
|---|---|---|
| Recurrent vs initial | 2.5 (1.01-6.18), p=0.047 | 2.86 (1.06-7.70), p=0.038 |
| STR vs GTR | 2.58 (1.09-6.11), p=0.031 | 3.38 (1.28-8.91), p=0.014 |
Grade 3+ AEs attributed to radiotherapy occurred in 5 pts (9.6%) of the intermediate-risk and 8 pts (15.1%) of the high-risk cohorts. Newly reported late events in the intermediate group were auditory and neurologic grade 3 plus one grade 4 hemorrhage. Zubrod, MMSE and neurologic function score were stable over time.
This is the mature counterpart to the trial's own 3-yr landmark reports and now sits as the benchmark alongside the ongoing de-escalation questions in NRG BN003 (NCT03180268) and ROAM/EORTC 1308, both of which test whether grade 2 post-GTR needs RT at all. Until those read out, the 10-yr PFS 72.2% and OS 84.7% here are the reference numbers for treating that group.
Pathology was graded under the WHO criteria of the enrolment era, so some group 1 tumors would likely be reclassified today, which is the trial's own proposed explanation for the poor recurrent grade 1 outcomes. Subgroup estimates rest on very small denominators, with intervals such as 15.0% (0-42.0%) for recurrent grade 2 PFS that cannot support a practice decision on their own.
The trial settles the low-risk question (observe after GTR, 10-yr PFS 88.0%) and confirms that high-risk disease is not controlled by 60 Gy, with 10-yr PFS 42.5%. What it cannot settle is whether the intermediate-risk result reflects RT or favorable biology, since no group 2 patient went untreated.
Non-randomised risk-adapted phase 2 with mature 10+ yr follow-up; supports existing consensus (observe post-GTR grade 1, RT otherwise) rather than testing it against a control.
- Does grade 2 meningioma post-GTR need adjuvant RT at all recruiting Observation or Radiation Therapy in Treating Patients With Newly Diagnosed Grade II Meningioma That Has Been Completely Removed by Surgery Phase 3n=163 · primary completion 2027-06 · randomised RT vs observation, GTR grade II
- Whether molecular classification reassigns recurrent grade 1 tumors n=210 · primary completion 2026-03 · methylation + histone PTM signature for recurrence
- How to improve first-line treatment for high-risk meningioma recruiting Vismodegib, FAK Inhibitor GSK2256098, Capivasertib, and Abemaciclib in Treating Patients With Progressive Meningiomas Phase 2n=124 · primary completion 2027-01 · mutation-matched targeted arms, progressive tumorsactive A Trial of Increased Dose Intensity Modulated Proton Therapy (IMPT) for High-Grade Meningiomas Phase NAn=21 · primary completion 2027-08 · dose-escalated IMPT, STR grade II / grade III
📚 Sources · 📄 1 paper
Abstract
RAPCHEM (BOOG 2010-03) NCT01872975
ForcT1-2 (<5cm) cN1 breast cancer, post-neoadjuvant chemo and surgery
2.9% (24/838)
Low 2.4%, intermediate 3.2%, high 2.8%
TL;DR10yr locoregional recurrence 2.9% (24/838) with response-adapted RT after neoadjuvant chemo; 2.4% in the RT-omission-eligible low-risk group.
Reported via The ASCO Post →
The allocation rule, not the recurrence rate, is the transferable part: ypN0 after mastectomy received no RT at all and still ran 2.4% at 10yr, and ypN1 pts had regional nodes omitted entirely. Dose, fractionation and target-volume detail are not reported in source, which limits direct transfer.
In cT1-2 cN1 pts who convert to ypN0 after neoadjuvant chemotherapy, this supports the safety of a de-escalated RT volume over 10 years; it does not extend to cN2-3 disease, and the randomised comparison remains open. The longer read
The transferable content is the allocation rule: ypN0 after mastectomy got no RT and ran 2.4% at 10yr, ypN1 had regional nodes omitted at 3.2%. Dose, fractionation and target volumes are not reported in source, so the volume decision transfers but the technique does not.
The de-escalation is entirely downstream of chemotherapy response: nodal clearance after neoadjuvant treatment is what unlocks the smaller RT volume, which raises the stakes on regimen choice and on documenting response. It does not change drug selection or sequencing itself.
8 details 3 trials watching
Prospective multicentre cohort, N=848 across 17 Dutch centres, accrued 2011-2015, presented at EBCC15 with 10-year follow-up; 838 completed follow-up. Not randomised: every patient received the RT volume their risk group assigned.
Breast tumour under 5 cm with 1 to 3 involved lymph nodes at presentation, treated with neoadjuvant chemotherapy then surgery (BCS or mastectomy). Most underwent axillary lymph node dissection.
Volume was set by post-chemotherapy nodal status. ypN0: breast RT after BCS, none after mastectomy. ypN1: breast or chest wall only, regional nodes omitted. ypN2+: breast or chest wall plus regional nodal irradiation. Dose and fractionation are not reported in source.
24 of 838 (2.9%) had a locoregional recurrence without distant spread at 10 years. Per-group counts appear in the detail table; the rates do not separate across strata.
The randomised test of this exact question is NSABP B-51/RTOG 1304 (NCT01872975), which the investigators expect in about 3 years; until then no trial has randomised ypN0 pts to nodal RT versus omission. Prior nodal-RT evidence (MA.20, EORTC 22922) was built in upfront-surgery populations, so it cannot arbitrate a post-chemotherapy response-adapted rule.
The 2.9% rate is uninterpretable without a comparator: a low event count in a de-escalated cohort is equally consistent with the omitted RT having been unnecessary and with the cohort being low-risk to begin with. ALND staging also means the ypN0 label carries more information than a modern sentinel-node ypN0 does.
The finding that recurrence is flat at 2.4% / 3.2% / 2.8% across escalating risk is the intended signal: the added RT in the higher strata may be doing the work that keeps them level with the low-risk group. It does not settle whether the low-risk group needed any RT, only that the allocation rule did not produce a visible failure.
Single-arm prospective cohort with no randomised comparator; allocation used ALND-era nodal staging. Confirmatory randomised answer (NSABP B-51) still pending.
- Does response-adapted RT omission hold under sentinel-node-only staging?
- Late toxicity avoided by omitting regional nodal irradiation n=827 · primary completion 2029-12 · randomised WBI alone vs WB+RNI in pN1 post-BCSnot yet A Study of Postoperative Regional Nodal Radiotherapy in Intermediate-risk Breast Cancer Phase 3n=3142 · primary completion 2032-12 · phase 3 RNI vs no RNI, toxicity evaluated
- Distant recurrence and survival in the de-escalated groups not yet A Study of Postoperative Regional Nodal Radiotherapy in Intermediate-risk Breast Cancer Phase 3n=3142 · primary completion 2032-12 · tumor-free survival non-inferiority without RNI
📚 Sources · 📄 1 paper
Abstract
RAD-IO
ForMIBC cT2-T3 (13% N+), bladder-preservation intent, 75% prior neoadjuvant chemo
TL;DR12-mo DFS 40/50 (80%, 95% CI 0.67-0.89) with durvalumab added to 5FU/MMC chemoRT, clearing the pre-set GO bar (≥75%).
The RT is unchanged from standard UK practice (55Gy/20fr bladder, 46Gy/20fr nodes when N+), so nothing here alters target volume or dose. What is new is that durvalumab was delivered neoadjuvant, synchronous AND adjuvant around that backbone, and only 61% completed it, which is the number gating any future randomised trial design.
In cT2-T3 MIBC pts choosing bladder preservation with 5FU/MMC chemoRT, this supports enrolling on a checkpoint-inhibitor chemoRT trial rather than adding durvalumab off protocol; it does not extend to cisplatin-ineligible pts having RT alone or to those with extensive nodal disease. The longer read
The RT is unchanged: 55Gy/20fr bladder, 46Gy/20fr to nodes in the N+ expansion, standard UK practice, so no target-volume or dose decision moves. The trial's value for an RT reader is that a 12-month adjuvant IO tail can be run around that backbone at all, though only 61% completed it.
Durvalumab was given in all three positions (neoadjuvant, synchronous, adjuvant 12 months) on a 5FU/MMC backbone, and 39% discontinued early. That delivery figure, not the 80% DFS, is what constrains which durvalumab schedule is worth randomising in bladder preservation.

+3 more figures


| Treatment status | N = 54 | % |
|---|---|---|
| Completed planned treatment | 33 | 61 |
| Discontinued early | 21 | 39 |

| Baseline | Number | % |
|---|---|---|
| Age, median (IQR) | 69 | 62-76 |
| Female | 10 | 18 |
| Male | 45 | 82 |
| Prior neoadjuvant chemo, yes | 41 | 75 |
| cT2 | 44 | 80 |
| cT3 | 11 | 20 |
| N+ | 7 | 13 |
10 details
Single-arm multi-stage feasibility and safety trial of durvalumab added to 5-fluorouracil/mitomycin C chemoradiotherapy in muscle-invasive bladder cancer. N=55 enrolled, 54 treated. A stage 1 expansion opened to node-positive pts, the first 6 with N+ disease.
Median age 69 (IQR 62-76), 45 (82%) male. cT2 in 44 (80%), cT3 in 11 (20%), N+ in 7 (13%) (N1 4, N2 3). 41 (75%) had prior neoadjuvant chemotherapy, so this is largely a post-NAC bladder-preservation population.
Durvalumab before, during and for 12 months after chemoRT, with 5-fluorouracil and mitomycin C as the radiosensitising backbone. 33/54 (61%) completed planned treatment; 21/54 (39%) discontinued early.
55Gy in 20 fractions to bladder; node-positive pts received 46Gy in 20 fractions to nodes alongside the bladder dose. This is the standard UK hypofractionated schedule, not an escalated or de-escalated variant.
Primary: disease-free survival rate at 12 months post chemoRT, read against a prespecified GO/NO-GO framework (GO ≥75%, contextual 60-75%, NO-GO <60%).
40/50 (80%) disease free at 12 months, 95% CI 0.67 to 0.89, clearing the GO threshold. 2 pts pending and 3 not evaluable. Investigators report very high bladder preservation and survival versus their previous trial data; those comparator figures are not given in the source.
The benchmark is the team's own BC2001 trial (James, JCO 2016), whose chemotherapy randomisation gave DFS HR 0.78 (0.60-1.02), stratified logrank p=0.07 on the slide shown. Comparison is to that historic control experience, not to a contemporaneous arm.
A 12-month DFS read is short for a preservation strategy where salvage cystectomy and late nodal relapse both fall outside the window. The evaluable denominator dropped from 55 to 50, and with 2 still pending the point estimate can move relative to a 75% threshold it clears by 5 points.
This clears a feasibility gate, not an efficacy one: the design question it answers is whether a randomised trial of durvalumab plus chemoRT is worth running, and the answer is yes. The 39% early discontinuation is the finding that should shape that trial, since a 12-month adjuvant tail that four in ten pts do not finish may not be the schedule worth randomising.
Single-arm feasibility/safety trial, N=55, 12-mo endpoint benchmarked against historic in-house CRT data. No randomised comparator; hard maturity gate applies.
- Which durvalumab component (neoadjuvant, synchronous, adjuvant) drives benefit
- Whether 80% 12-mo DFS survives a randomised comparator
- Drivers of the 39% early discontinuation
📚 Sources · 🐦 3 tweets
RAD-IO at #ASCO26: durvalumab added to chemoradiation in muscle-invasive bladder cancer cleared its efficacy bar in a bladder-preservation approach. Single-arm, benchmarked against prior CRT data.
— Katy Beckermann (@katy_beckermann) May 30, 2026
Durvalumab given before, during, and 12 months after chemoRT (55Gy/20Fr +… pic.twitter.com/UXxwoZzaMC
#ASCO26 🔬 Abstract 4504 | RAD-IO
— Dra. María Natalia Gandur Quiroga (@nataliagandur) May 30, 2026
Durvalumab + chemoradiotherapy in muscle-invasive bladder cancer
Presented by Nicholas D. James, PhD, MBBS, FRCP@OncoAlert@ASCO
Bladder preservation in MIBC remains one of the most important curative-intent questions in GU oncology.
The key… pic.twitter.com/W6JqzTVsJ3
RAD-IO: chemoradiation (5FU+MMC) + Durva in MIBC. #ASCO26 pic.twitter.com/yTyhkdjCox
— Álvaro Pinto (@dralvaropinto) May 30, 2026
A-DREAM
FormHSPC, PSA <0.2 after 18-24mo ADT + ≥12mo ARPI
41.0% (32/78)
80% CI 33.1-48.9%, one-sided p 0.0249
TL;DR41% treatment-free with eugonadal T at 18mo after stopping ADT+ARPI in responding mHSPC (80% CI 33.1-48.9%, one-sided p 0.0249).
The RT-relevant detail is baseline burden: 51.3% had prostate RT and 29.5% had RT to metastatic sites, so the cohort that tolerated interruption was heavily locally treated, and 4 pts (5.1%) took RT as their non-protocol next step off ADT. Metastasis-directed RT is not tested here, but this is the population where a de-intensification question meets it.
In mHSPC with PSA under 0.2 after 18-24 months of ADT plus at least 12 months of ARPI, this supports discussing a protocolized interruption with PSA and testosterone monitoring; it does not extend to pts with persistent PSA or to unselected metastatic disease. The longer read
The cohort was RT-heavy before interruption: 51.3% had prostate radiation and 29.5% had radiation to metastatic sites, and 4 (5.1%) took radiation as their non-protocol next step off ADT. Metastasis-directed RT to extend time off systemic therapy is the randomizable question this describes but does not test.
The composite splits usefully: 57.7% stayed treatment-free for 18 months but only 66.7% recovered testosterone (median 9.0 months), so gonadal recovery, not disease control, is the rate limiter in a median-age-70 cohort. Counsel the two risks separately before interrupting.

+3 more figures


| Characteristic | Value |
|---|---|
| Median age | 70 (49-90) |
| High volume (CHAARTED) | 27 (35.1%) |
| Low volume (CHAARTED) | 50 (64.9%) |
| Prostate RT as local therapy | 40 (51.3%) |
| RT to metastatic sites | 23 (29.5%) |
11 details 5 trials watching
Alliance single-arm phase 2, N=75 planned, 78 eligible enrolled 07/2022-03/2024. Median follow-up 26.9 months. Monitoring PSA and testosterone q3mo, scans at least q6mo (q3mo with rising PSA), QOL q6mo.
mHSPC on ADT + ARPI with PSA <0.2 stable or falling after 18-24 months of ADT and at least 12 months of ARPI. Median age 70 (49-90), 84.6% White, 64.9% low volume by CHAARTED, 35.1% high volume. Median PSA prior to starting ADT+ARPI 18.99 ng/mL.
Not an intervention, but the cohort was RT-heavy at baseline: 40 (51.3%) had radiation as local therapy, 31 (39.7%) had no local therapy, 7 (9.0%) prostatectomy +/- RT. 23 (29.5%) had radiation to metastatic sites. Dose and fractionation not reported in source.
Primary: treatment-free with eugonadal testosterone (T ≥150 ng/dL) at 18 months. Secondary: time to eugonadal T, duration off treatment, QOL. Exploratory: rPFS, TTNT, OS (CSS/NCSS), cost. Re-initiation triggered by PSA ≥5 ng/mL, PCWG3 radiographic change, or prostate-cancer-related symptoms.
Primary endpoint met: 32/78 (41.0%), 80% CI 33.1-48.9%, one-sided p 0.0249. Testosterone recovered in 52 (66.7%) by 18 months with median time to eugonadal T 9.0 months (95% CI 8.4-12.4); 45 (57.7%) stayed treatment-free for 18 months. rPFS 15/78 events, median NE; OS 4/78 events, median NE.
The 18-month primary readout is short for a de-intensification question whose real risk is late: 4 of 29 pts who resumed per protocol later progressed and discontinued the original ARPI, so re-treatment did not uniformly restore control. Deaths (4) included non-prostate causes (myelodysplastic syndrome, influenza, myocardial infarction), and with no continuous-treatment arm the OS curve carries no comparative information.
Intermittent ADT has been tested before in metastatic disease (SWOG 9346 could not exclude an OS decrement with intermittent therapy in mHSPC), but A-DREAM asks the question in the modern ARPI-intensified era with a molecularly deeper response gate, which is why the cohort's off-treatment rate looks better than the older intermittent literature suggests. That comparison is a rationale, not a result: A-DREAM has no randomised arm.
The number that matters clinically is not 41% but its two components: testosterone recovery is the rate limiter (66.7% recovered, median 9.0 months), while disease control off treatment was more common (57.7% treatment-free at 18 months). A trial that de-intensifies successfully on disease grounds can still miss its endpoint on gonadal recovery in an older cohort, and that distinction determines who to counsel.
Single-arm phase 2, no continuous-treatment control, 18mo primary readout in a deeply selected responder cohort. Interruption safety needs a randomised comparator.
- Does interruption cost overall survival vs continuous ADT+ARPI active A Study of an Intermittent ADT Approach With Apalutamide Monotherapy in Participants With mCSPC Phase 3n=420 · primary completion 2026-10 · phase 3 intermittent vs continuous, rPFS non-inferiorityrecruiting Optimal PSA Triggered Individual Management of Androgen Sensitive Prostate Cancer Phase 2n=160 · primary completion 2030-10 · randomised intermittent relugolix+ARPI after PSA response
- Which responders recover testosterone and which do not active Comeback From Long coursE Androgen Deprivation Therapy (ADT) With RElugolix and Darolutamide (CLEARED) Phase 2n=33 · primary completion 2028-11 · 1° EP is T recovery rate after 2y relugolix+darolutamidenot yet Clinical Trial to Observe the Effects of Tamoxifen on Testosterone Recovery in Medically Castrated Prostate Cancer Patients Phase 2n=96 · primary completion 2030-10 · tamoxifen vs no tamoxifen for T recovery post-ADT
- Can metastasis-directed RT extend time off systemic therapy n=254 · primary completion 2031-08 · PSMA-guided SBRT added after 6mo darolutamide+ADT
📚 Sources · 🐦 1 tweet
Can treatment be safely stopped in selected patients with mHSPC?
— MJosé Juan (@mjuanfi81) May 30, 2026
Phase II A-DREAM trial, 41% of responders remained treatment-free with testosterone recovery 18m after stopping ADT/ARPI. At a median FU of 21 months, 35% of patients required treatment re-initiation.@OncoAlert pic.twitter.com/iW2VDBWWhN
ARACOG (AFT-47)
ForAdvanced prostate cancer (mHSPC, nmCRPC, mCRPC) starting an ARSI
daro -15.8 vs enza -36.1
median % change in MCCD at 24 wks, P=0.009
TL;DREnzalutamide MCCD decline -36.1 vs -15.8 for darolutamide at 24wks (P=0.009) in randomized phase 2, N=111.
The comparison is between each pt's own worst-hit domain, and those differed by arm (PALFAM for daro, SWM for enza), so the read is how far the worst domain falls, not which one. Crossover before 24wks was scored at crossover inside the randomized arm, which attenuates rather than widens the gap. Moves ARSI selection when cognitive burden matters, not efficacy.
In a man starting an ARSI for mHSPC or nmCRPC where cognitive burden is a live concern, this supports darolutamide over enzalutamide on measured cognition; it does not speak to disease control, which was never compared head-to-head. The longer read
For ARSI selection where the two drugs are treated as equivalent on disease control, this puts a measured number on the cognitive difference (median MCCD -15.8 vs -36.1, P=0.009) instead of an AE-table impression. It moves drug choice, not sequencing or line of therapy.

| Metric | Darolutamide (N=48) | Enzalutamide (N=47) |
|---|---|---|
| Maximally changed module | PALFAM | SWM |
| Domain | Visual memory / executive function | Working memory / executive function |
| Median change, baseline to 24 wks | -15.8 | -36.1 |
| Between-arm P | P=0.009 | P=0.009 |
+2 more figures


8 details
Randomized open-label phase 2 from the Alliance for Clinical Trials in Oncology, N=111, stratified by age (<65, 65-80, >80). Enrolled 8/17/2021 to 3/11/2025, with CANTAB modules, PROMs and timed-up-and-go collected at 12 and 24 weeks.
Men with mCRPC, nmCRPC or mHSPC. Randomization was stratified by age across three bands (<65, 65-80, >80), so the design anticipated an older population. Baseline cognitive eligibility criteria not reported in source.
Darolutamide was provided by the study; enzalutamide was given through standard of care, so the two arms differed in drug supply as well as drug. Doses and concurrent ADT not reported in source.
Primary: % change from baseline to 24 weeks in the Maximally Changed Cognitive Domain (MCCD), drawn from 5 remotely delivered CANTAB modules (SWM, PALFAM, OTS, SSP, RVP) covering executive function, visual memory, attention and working memory. Blood for polygenic hazard score and AR testing, PROMs and timed-up-and-go were collected alongside.
Median MCCD change -15.8 with darolutamide (PALFAM) vs -36.1 with enzalutamide (SWM), P=0.009, across 48 and 47 pts in the primary analysis. No oncologic endpoint was reported in source.
The two drugs have never been compared head-to-head for efficacy, and cognition in ARAMIS and ARASENS (darolutamide) and PROSPER and ARCHES (enzalutamide) was captured as clinician-graded adverse events against placebo, not measured with a battery. Mild executive dysfunction is exactly the harm an AE table structurally misses.
Pts crossing over before 24 weeks carried their crossover score into the randomized arm, which should attenuate the gap rather than widen it. CANTAB is a research battery, not a clinical diagnostic, and no link to function, falls or discontinuation is reported in source. 24 weeks says little about years of therapy.
This shifts an argument that has run on mechanism and on AE tables onto measured performance. Where the two drugs are treated as interchangeable for disease control, cognition becomes a defensible tiebreaker. What it does not settle is whether an MCCD gap of this size is felt by the pt.
Randomized, prespecified primary endpoint met against a named comparator; open-label design and the composite MCCD construct temper it. Consistent with darolutamide's known limited CNS penetration.
- Whether the MCCD difference translates to function, falls, or discontinuation
- Durability of cognitive divergence beyond 24 weeks
- Whether apalutamide differs from enzalutamide on the same testing
📚 Sources · 🐦 2 tweets
#ASCO26 GU Oncology Spotlight 🚨
— Dra. María Natalia Gandur Quiroga (@nataliagandur) May 30, 2026
🔬 Abstract 5005 | ARACOG / AFT-47
Cognitive effects of darolutamide vs enzalutamide
Presented by Alicia K. Morgans, MD, MPH, FASCO@CaPsurvivorship @OncoAlert@ASCO
In prostate cancer, we often discuss AR pathway inhibitors through the lens… pic.twitter.com/vpZr1w6kc6
ARACOG (AFT-47) met its primary endpoint: enzalutamide caused significantly greater cognitive decline than darolutamide at 24 weeks in advanced prostate cancer.
— Katy Beckermann (@katy_beckermann) May 30, 2026
Randomized open-label phase 2, 111 pts (mHSPC, mCRPC, nmCRPC), DAR vs ENZ.
Cognition was measured with CANTAB, a… pic.twitter.com/kj4vfGRVyp
CHRYSALIS-2
ForTreatment-naive advanced NSCLC with atypical (uncommon) EGFR mutation
TL;DRMedian OS 41.0 mo (95% CI 27.7-NE) with 1L amivantamab + lazertinib in atypical EGFR-mutant NSCLC, single-arm n=49.
In treatment-naive advanced NSCLC with an atypical EGFR mutation, this supports amivantamab plus lazertinib as a prospectively benchmarked option where none is established; it does not extend to classical exon 19del/L858R disease or exon 20 insertions. The longer read

+1 more figure
8 details 3 trials watching
Single-arm expansion cohort of the CHRYSALIS-2 program, n=49, 1L atypical EGFR-mutated advanced NSCLC. Median follow-up 31.3 mo. No randomised comparator arm.
Treatment-naive advanced NSCLC harbouring an atypical (uncommon) EGFR mutation. Baseline strata shown on the swimmer plot include age ≥65y, Asian ancestry and CNS involvement; per-stratum counts are not reported in source.
IV amivantamab (EGFR/MET bispecific) plus lazertinib (third-generation EGFR TKI). No chemotherapy backbone. Median duration of treatment 13.3 months (range <0.1-53.2), with 39% of 1L participants still on treatment beyond 2 years.
Median OS 41.0 mo (95% CI 27.7-NE), described by the presenters as roughly 3.5 years. The upper CI bound is not estimable, so the point estimate is anchored on the lower bound of 27.7 mo.
Reported only as consistent with prior reports, no new safety signals with longer follow-up. No grade 3+ rates, infusion-reaction rates or dermatologic AE rates appear in the source.
The atypical EGFR label pools biologically distinct alterations (G719X, S768I, L861Q and compound variants) whose single-agent TKI sensitivity differs; n=49 cannot resolve per-variant benefit, and the curator's read of no variant-outcome association is an absence of signal in a small cohort, not evidence of uniformity. No comparator, so the 41.0 mo median cannot be positioned against afatinib or osimertinib series in the same population.
Atypical EGFR is the part of the EGFR-mutant space where no regimen is settled, so a 41.0 mo median in 49 pts is meaningful as a benchmark even without randomisation. The practical question this leaves open is whether the bispecific's added toxicity and IV schedule are justified over an oral TKI alone, which this design cannot answer.
Single-arm n=49 expansion cohort, no randomised comparator against afatinib or osimertinib in atypical EGFR. Maturity gate: single-arm never reaches confirmatory.
- Doublet vs single-agent osimertinib or afatinib in atypical EGFR n=480 · primary completion 2029-02 · phase 3 firmonertinib vs osimertinib/afatinib, PACC 1L
- Which atypical EGFR variants drive the durable-response tail
- Whether subcutaneous amivantamab preserves efficacy with less infusion burden n=418 · primary completion 2024-01 · phase 3 SC vs IV ami + lazertinib, randomisedrecruiting A Study of Amivantamab in Participants With Advanced or Metastatic Solid Tumors Including Epidermal Growth Factor Receptor (EGFR)-Mutated Non-Small Cell Lung Cancer Phase 2n=520 · primary completion 2027-08 · SC co-formulation activity + safety cohorts
📚 Sources · 🐦 1 tweet
Amivantamab + lazertinib achieved a median OS of 41.0 months in treatment-naïve atypical EGFR-mutant NSCLC, with no clear association between EGFR variant subtype and outcome. A compelling option. Meanwhile, amivantamab continues evaluation across multiple tumor types. #ASCO26 pic.twitter.com/aWn3Ja60Ji
— Chul Kim (@chulkimMD) May 29, 2026
ESAONA
For1L EGFR-mutant NSCLC with brain metastases
95.5% vs 79.6%
p = 0.0004
TL;DRiORR 95.5% vs 79.6% (p=0.0004) and intracranial PFS HR 0.46 favoring asandeutertinib in 1L EGFR-mutant NSCLC with brain mets.
The RT-relevant number is intracranial PFS: median not reached vs 17.5 mo, HR 0.46. If a first-line TKI holds CNS disease that long, the deferral-of-brain-RT window widens, but the source reports no prior-RT stratification, no CNS-RT use by arm, and no lesion size or symptom criteria, so this cannot yet gate an SRS-versus-defer decision.
In treatment-naive EGFR-mutant NSCLC with asymptomatic brain metastases, this supports the case for TKI-first CNS control as a hypothesis, not a change in practice; it says nothing about symptomatic or large lesions where local therapy is already indicated.
Intracranial PFS median not reached vs 17.5 mo, HR 0.46, is the number that touches the SRS-timing decision in asymptomatic brain mets. The source gives no prior-RT stratification and no salvage-RT rates by arm, so the deferral question stays open rather than answered.
The intracranial effect (HR 0.46) is roughly double the systemic one (HR 0.64), so the case for asandeutertinib rests on CNS penetration rather than broad potency. Serious TRAEs run 10.8% vs 7.1%, a real but modest trade against a phase II endpoint with no OS.

| Endpoint | Asandeutertinib (n=111) | Osimertinib (n=113) | Effect |
|---|---|---|---|
| Intracranial ORR (BICR) | 95.5% (89.8-98.5) | 79.6% (71.0-86.6) | p = 0.0004 |
| Intracranial PFS (BICR) | Median not reached | 17.5 mo (15.18-NA) | HR 0.46, p = 0.0020 |
| Overall PFS (BICR) | Median not reached | 17.2 mo (15.18-19.55) | HR 0.64, p = 0.0473 |
| Any TRAE | 99.1% | 95.6% | n/a |
| Serious TRAE | 10.8% | 7.1% | n/a |
7 details 4 trials watching
Randomised phase II, N=224, asandeutertinib (n=111) vs osimertinib (n=113). Endpoints read by BICR. Follow-up duration, stratification factors and alpha allocation are not reported in the source slide.
First-line EGFR-mutated NSCLC with brain metastases. The source does not state lesion number, size, symptom status, or whether prior CNS radiotherapy was permitted, which is the eligibility gate an RT reader needs.
Intracranial ORR by BICR is the headline, with intracranial PFS and overall PFS reported alongside. No overall survival data in source.
Any TRAE 99.1% vs 95.6%; serious TRAE 10.8% vs 7.1%. The excess serious-event rate is small in absolute terms but sits on a phase II denominator, and no organ-level breakdown is given in source.
The intracranial separation (HR 0.46) is larger than the systemic one (HR 0.64), which points at CNS penetration rather than a general potency gain as the mechanism. For radiation oncology the question is whether that CNS margin is durable enough to defer SRS in asymptomatic pts; a phase II with unreached medians and no OS cannot answer it.
CONSORT flow
Phase II, conference-slide source only; no OS, borderline overall-PFS p, and no reported CNS-RT or prior-RT stratification. Needs phase III before displacing osimertinib.
- Does intracranial PFS benefit translate to overall survival
- Salvage brain RT and SRS rates by arm recruiting Observation or Upfront Cranial RT in Oncogene Mutated NSCLC With Asymptomatic BM: A Phase III RCT Phase 3n=190 · primary completion 2025-12 · randomises upfront SRS/WBRT vs TKI alone, asx BMrecruiting A Study of Stereotactic Radiosurgery (SRS) and Standard Treatment in People With Lung Cancer That Has Spread to the Brain Phase 2n=56 · primary completion 2027-12 · SRS after 3mo osimertinib vs osimertinib alonerecruiting Early or Delayed Intervention of Brain Radiotherapy Combined With Almonertinib in EGFR Mutated NSCLC With Brain Metastases Phase 3n=232 · primary completion 2028-12 · early vs delayed SRS timing on 3G TKI, phase 3
- Activity in symptomatic or leptomeningeal CNS disease recruiting A Clinical Trial of Furmonertinib Combined With Anlotinib as First-line Treatment for Advanced NSCLC With EGFR-sensitive Mutations and Brain Metastasis Phase 2n=146 · primary completion 2027-09 · 1L 3G TKI + anlotinib, brain/LM mets at dx
📚 Sources · 🐦 1 tweet
#ASCO26 🧠🌍
— Dr Rishabh Jain (@DrRishabhOnco) May 30, 2026
Could a next-generation EGFR TKI outperform osimertinib in patients with brain metastases?
The phase II ESAONA trial suggests the answer may be yes.
🧪 LBA2007 | ESAONA
1L EGFR-mutated NSCLC with brain metastases
👥 n=224
⚔️ Asandeutertinib vs Osimertinib
Key… https://t.co/mEOKGNKgf7 pic.twitter.com/pUQuH6i2cV
SPIN Score (Celiac Plexus Radiosurgery) NCT03323489
ForPancreatic cancer with retroperitoneal pain considered for celiac plexus SRS
TL;DRPost-hoc predictors of pain response after celiac SRS: response 32% / 53% / 89% by 0 / 1 / 2 SPIN points.
The actionable RT read is timing, not technique: neurotoxic chemo exposure carried OR 5.1 (p=0.009) against response, so the referral decision moves earlier in the disease course, before oxaliplatin or taxane neuropathy. Celiac SRS is NCCN-listed and single-fraction, so the gate is who you irradiate and when, not dose.
In pancreatic cancer pts with retroperitoneal pain scoring above 6 and no prior neurotoxic chemo, this supports considering celiac SRS earlier rather than after systemic lines; it does not tell you what to do for the chemo-exposed, low-pain pt, where response was 32%. The longer read
The gate on celiac SRS is patient selection and timing, not plan quality: neurotoxic chemo exposure carried OR 5.1 (p=0.009) against pain response, and 2-point pts responded 89% vs 32% at 0 points. Argues for taking the referral early rather than as last-line salvage.
The variable that mattered is one med onc controls: prior neurotoxic chemotherapy predicted failure of celiac SRS (OR 5.1, p=0.009). For a pt with severe retroperitoneal pain, this argues for a celiac SRS referral alongside, not after, an oxaliplatin or taxane backbone.

| SPIN score | n | Pain response |
|---|---|---|
| 0 | 31 | 32% |
| 1 | 40 | 53% |
| 2 | 19 | 89% |
10 details
Post-hoc analysis of the pivotal single-arm phase 2 celiac plexus radiosurgery trial (NCT03323489), n=90 evaluable. Candidate baseline predictors screened by univariate then multivariate logistic regression, with only multivariate-significant variables carried into the score. Internal validation by bootstrap resampling, 500 iterations, for an optimism-corrected AUC.
Pain response per parent protocol: a ≥2-point reduction in average pain on the Brief Pain Inventory-Short Form, baseline to three weeks. Parent-trial response was 53% (95% CI 42-64%).
Only neurotoxic chemotherapy exposure (OR 5.1, p=0.009) and baseline pain intensity (OR 1.8, p=0.003) survived multivariate analysis; age and therapy line dropped out to collinearity. The resulting 2-point score separated response into 32% / 53% / 89%, with AUC 0.716 apparent, 0.714 optimism-corrected.
| Predictor | Univariate | Multivariate |
|---|---|---|
| Neurotoxic chemo exposure | OR 5.33 (2.13-13.4), p<0.001 | OR 5.1, p=0.009 |
| Baseline pain intensity | OR 1.73, p=0.003 | OR 1.8, p=0.003 |
| Age | OR 1.06, p=0.014 | lost significance |
| Therapy line | OR 0.65, p=0.04 | lost significance |
The score was derived and internally validated in the same 90 pts, so the bootstrap corrects optimism from resampling but not from the variable-selection step that preceded it. The 2-point stratum is n=19, and the dichotomy at pain >6 was picked from the same data that shows steeper response above 7 and 8.
The neurotoxic-chemo term is the interesting one because it is a timing variable a clinician controls, not a fixed patient trait: it implies referral for celiac SRS competes with the systemic sequence rather than following it. Whether that reflects true nerve injury blunting an ablative pain response, or confounding by later-line disease biology, the post-hoc design cannot separate.
Post-hoc derivation on the parent trial's own 90 pts; internal bootstrap only, no external cohort. Design dominates the read regardless of effect size.
- External validation of the SPIN score in an independent cohort
- Is neurotoxic chemo effect causal or a proxy for later-line disease
- Durability of pain response beyond the 3-week endpoint
📚 Sources · 🐦 1 tweet
Celiac SRS = convenient, effective tx for intractable pain, but who benefits most?
— Dr. Nina Niu Sanford (@NiuSanford) May 30, 2026
Post-hoc Ph2 analysis identified 2 response predictors (SPIN score): severe baseline pain & no prior neurotoxic chemo.
Supports earlier use before potential chemo neuropathy. #ASCO26 @OncoAlert pic.twitter.com/3qFYU6N1iD
PEACE V-STORM NCT03569241
ForPelvic nodal oligorecurrence (≤5 PET+ nodes) after radical local prostate tx
4yr 76% vs 63%, HR 0.62
80% CI 0.44-0.86, p=0.063 (α 0.20)
TL;DR4yr MFS 76% vs 63% (HR 0.62, 80% CI 0.44-0.86) favoring whole-pelvis ENRT over MDT for pelvic nodal oligorecurrence, both with 6mo ADT.
The RT signal is regional: 4yr locoregional RFS 85% vs 62% (HR 0.45), consistent with MDT failing mostly in the pelvis. The benefit sat in PSMA-staged pts (HR 0.48) and PSA <1 (HR 0.27), so it moves the choice from nodal SBRT to whole-pelvis 45/25 with 65 Gy SIB. Prostate bed inclusion, not the pelvic field, drove added GI toxicity.
In a man with up to five PET-detected pelvic nodal recurrences below the aortic bifurcation after radical local treatment, this supports whole-pelvis ENRT with nodal SIB over nodal SBRT alone, both with 6 mo ADT; it does not extend to para-aortic, bone, or visceral disease. The longer read
The RT signal is regional: 4yr locoregional RFS 85% vs 62% (HR 0.45), consistent with MDT failing mostly in the pelvis. The benefit sat in PSMA-staged pts (HR 0.48) and PSA <1 (HR 0.27), so it moves the choice from nodal SBRT to whole-pelvis 45/25 with 65 Gy SIB. Prostate bed inclusion, not the pelvic field, drove added GI toxicity.
11 details 2 trials watching
Phase 2, open-label, randomised (1:1) trial at 21 hospitals in Australia, Belgium, Italy, Norway, Spain, Switzerland. Minimisation stratified by PET tracer (choline vs PSMA) and MDT type (sLND vs SBRT/SIB). Median follow-up 50 mo (IQR 42-58).
Biochemical relapse after RP, postoperative RT or definitive RT, with ≤5 PET-detected pelvic nodes up to the aortic bifurcation. Excluded: bone/visceral mets, nodes above the bifurcation, testosterone <50 ng/dL. Median PSA 1.00 vs 0.85 ng/mL; 81% and 83% PSMA-staged.
ENRT: 45 Gy/25 fx whole pelvis + 65 Gy SIB to PET+ nodes, IMRT/VMAT mandatory. MDT: SBRT 30 Gy/3 fx every other day, 3 mm PTV margin, or extended sLND. Prostate bed RT ≥66 Gy/33 fx suggested for high-risk RP features in both arms, with benchmark-case QA.
6 mo LHRH agonist or antagonist in both arms, started no later than the first fraction. ADT was not to be restarted without clinical progression.
Primary: MFS (any M1 on PET or death). Secondary: bRFS, locoregional RFS, ADT-free survival, late G2+ GU/GI toxicity. OS, PCSS and time to castration resistance had too few events to report.
4yr cumulative G2+ GU 28% vs 31% (p=0.73) and GI 7% vs 9% (p=0.93), MDT vs ENRT. One ENRT pt had a recto-urethral fistula needing surgery. No treatment-related deaths.
First randomised comparison of MDT vs ENRT for nodal oligorecurrence. The single-arm GETUG-P07-OLIGOPELVIS reported 3yr bRFS 45% with ENRT, in a higher-PSA, choline-staged cohort. POINTER-PC (phase 3) and GETUG-P12-OLIGOPELVIS 2 are the confirmatory tests.
Prostate bed RT was unevenly used (25% vs 41%) and linked to both local control and GI toxicity, which muddies attribution to the pelvic field. No central PET review, and the PSA and nodal-level subgroups are post hoc.
The MFS gain is mostly prevention of further nodal (M1a) spread, consistent with PSMA PET under-staging microscopic pelvic disease. It does not settle whether the benefit holds at higher PSA or with choline staging, or whether it reaches survival.
| Endpoint | ENRT | MDT | HR (80% CI), p |
|---|---|---|---|
| MFS (1°) | 76% (69-81) | 63% (56-69) | 0.62 (0.44-0.86), p=0.063 |
| bRFS | 57% (50-64) | 41% (34-47) | 0.62 (0.48-0.80), p=0.014 |
| Locoregional RFS | 85% (80-90) | 62% (55-69) | 0.45 (0.31-0.65), p=0.0047 |
| ADT-free survival | 77% (70-82) | 60% (53-67) | 0.60 (0.43-0.83), p=0.049 |
| Subgroup | HR (80% CI) | Interaction p |
|---|---|---|
| PSMA PET | 0.48 (0.32-0.72) | 0.12 |
| Choline PET | 1.21 (0.64-2.28) | 0.12 |
| PSA <1 | 0.27 (0.14-0.52) | 0.029 |
| PSA ≥1 | 1.00 (0.67-1.50) | 0.029 |
| No common iliac node | 0.49 (0.33-0.74) | 0.20 |
| Common iliac node | 1.04 (0.55-1.95) | 0.20 |
| Endpoint | MDT | ENRT | p |
|---|---|---|---|
| 4yr cumulative G2+ GU | 27/97 (28%) | 29/93 (31%) | 0.73 |
| 4yr cumulative G2+ GI | 7/97 (7%) | 8/93 (9%) | 0.93 |
| G3 urinary incontinence | 6 (6%) | 9 (10%) | n/a |
| G3 diarrhoea | 1 (1%) | 2 (2%) | n/a |
CONSORT flow
Randomised phase 2 hit its MFS primary at 50 mo median f/u, but was powered at α 0.20 with 80% CIs; authors call for phase 3 confirmation (POINTER-PC).
- Will phase 3 (POINTER-PC) confirm ENRT over MDT? not yet Best Salvage Treatment for High-risk Relapsing Prostate Cancer (PEACE-9 - ESCALATE-RT) Phase 3n=140 · primary completion 2030-07 · phase 3 MDT ± WPRT in oligorecurrence, ADT + enza
- Is ENRT benefit confined to PSMA-staged, PSA <1 pts?
- Role of prostate bed RT when PSMA PET is locally negative recruiting Comparing "Salvage" Radiotherapy and Individualized PSMA PET/CT Targeted Treatment in With Relapsing Prostate Cancer Phase 3n=450 · primary completion 2027-10 · phase 3 standard SRT vs PSMA-individualized therapy
📚 Sources · 📄 1 paper
INRT-AIR & DARTBOARD pooled analysis
ForHNSCC oropharynx/larynx/hypopharynx, stage I-IVB, excluding T1-2N0 larynx
TL;DR5yr solitary elective nodal recurrence 0% with ENI omission in HNSCC; 5yr OS 87%, PFS 74%, n=117.
The number that matters is 0% solitary elective nodal recurrence at 5 yrs: elective volumes are where the parotid, constrictor and pharyngeal dose lives, and this is the first pooled long-term read that omitting them does not trade nodal control. MDADI 84.9 at 12 mo with no significant decline is the swallowing correlate. No dose or CTV detail in source, so the contouring approach cannot be replicated from this abstract.
In stage I-IVB oropharynx, larynx or hypopharynx SCC being planned for definitive chemoRT, this supports enrolling on an INRT protocol rather than adopting nodal omission off-trial; it does not extend to T1-2N0 larynx, which was excluded. The longer read
This is the elective-volume decision, the one de-escalation lever definitive chemoRT has never randomised. 0% solitary elective nodal recurrence at 5 yrs with MDADI 84.9 at 12 mo says the trade is not nodal control, but the nodal selection ran through an AI model on staging PET/CT, so the transferable piece may be the selection step, not the omission.

+1 more figure

11 details 2 trials watching
Patient-level pooled analysis of 2 prospective trials, INRT-AIR and DARTBOARD, both testing involved nodal radiotherapy. N=117, median follow-up 3.4 years. No randomised comparator arm receiving standard elective nodal irradiation.
HNSCC of oropharynx, larynx, and hypopharynx, stage I-IVB, explicitly excluding T1-2N0 larynx. Completed PET/CT and neck CT were required for eligibility, which is also the imaging substrate the nodal-selection step depends on.
Definitive chemoradiotherapy with omission of elective nodal irradiation (ENI), treating involved nodes only (INRT). Suspicious node identification was assisted by an artificial-intelligence model reading the staging PET/CT and neck CT. Dose, fractionation and margin expansions are not reported in the source.
5-yr solitary elective nodal recurrence 0%. 3-yr cumulative incidence: local 9.5%, regional 4.3%, distant 11%. 5-yr OS 87%, PFS 74%. Mean composite MDADI 84.9 at 12 months with no significant decline after treatment.
Pooling two protocols with different designs into one patient-level cohort assumes their INRT definitions were interchangeable, which the source does not establish. Median follow-up of 3.4 years supports a 5-year estimate on a shrinking risk set, and HPV status, which drives OS in an oropharynx-weighted cohort, is not reported.
The zero solitary elective nodal failures make the mechanistic case that undissected, PET-negative elective levels rarely harbour disease that only ENI would sterilise. What the pooled cohort cannot settle is whether the result survives outside two experienced centres using an AI-assisted nodal-selection step, which is precisely the component a general department would have to reproduce.
Pooled single-arm prospective cohorts, n=117, no randomised comparator against standard elective nodal RT. Presenters state randomised evidence needed before non-trial use.
- Randomised INRT vs elective nodal irradiation in definitive chemoRT recruiting Dose De-escalation and Sentinel LN Mapping Driven Radiotherapy of Contralateral Neck in Ipsilateral Node Positive HNSCC Phase NAn=147 · primary completion 2027-01 · sentinel node mapping tailors contralateral neck volumerecruiting Invert-Prospective Phase II Randomized Trial of Involved Nodal Versus Elective Neck RadioTherapy Phase 2n=80 · primary completion 2028-07 · randomised INRT vs ENI, solitary elective recurrence
- Does AI-assisted nodal selection outperform physician contouring
- Whether INRT toxicity benefit is measurable against standard elective volumes
📚 Sources · 🐦 1 tweet
Day FOUR of #ESTRO26 Coverage by OncoAlert 🚨
— OncoAlert (@OncoAlert) May 18, 2026
Omission of elective nodal irradiation in HNSCC: long-term results and patient-level pooled analysis from 2 prospective trials (INRT-AIR & DARTBOARD)
Presenter Sympascho Young 🇺🇸
A patient-level pooled analysis of 117 patients… pic.twitter.com/KaaT70nSNH
EXTEND
ForOligometastatic solid tumors, 1-5 metastases, on standard systemic therapy
HR 0.54
95% CI 0.41-0.72, p<0.001
TL;DRPFS HR 0.54 (0.41-0.72), p<0.001 for MDT added to SOC across 6 oligometastatic baskets; RT delivered 98% of MDT.
The prostate-excluded HR 0.60 (0.40-0.89) is the number that matters for an RT reader: the benefit survives removal of the two prostate baskets, where MDT is already routine. RT delivered 98% of MDT (370/379), so this is a radiotherapy result, though dose and fractionation are not reported in source.
In a patient with 1-5 metastases from pancreas or a non-breast, non-kidney histology already on standard systemic therapy, this supports discussing MDT as an addition rather than a deferral; it does not resolve the breast or kidney question, where the baskets were inconclusive. The longer read
RT delivered 98% of MDT (370/379 metastases), so the all-basket HR 0.54 and the prostate-excluded HR 0.60 (0.40-0.89) are radiotherapy effect sizes. The prostate-excluded analysis is the one that moves practice beyond the population where MDT is already routine, though dose, fractionation and target volume are not reported in source.
MDT was added on top of standard systemic therapy rather than substituted for it, so nothing here supports deferring or de-escalating systemic treatment. The ctDNA findings (detectable at enrollment with shorter PFS, clearance at 3 months with better survival) are the medonc-relevant signal, pointing toward a molecular rather than lesion-count definition of who to refer.
13 details 5 trials watching
Multicenter randomized phase II basket trial, 6 histology baskets with basket-specific stratification and powering. Accrual 2018 to 2023, median follow-up 53 months.
Patients with 1-5 metastases on standard-of-care systemic therapy, allocated to breast, pancreas, kidney, two prostate baskets, or an "Other" basket. 521 screened, 350 randomized, 334 analyzed per protocol (MDT+SOC n=166; SOC n=168).
Radiotherapy delivered 98% of MDT (370/379 metastases), so this is effectively a radiotherapy trial. Dose, fractionation, technique and target-volume definition are not reported in source.
Primary: PFS, pre-specified in the per-protocol set at three levels (within each basket, across all baskets, and across all baskets excluding the prostate baskets). Exploratory: ctDNA and immune profiling.
All-basket PFS HR 0.54 (95% CI 0.41-0.72), p<0.001; excluding prostate, HR 0.60 (95% CI 0.40-0.89). Superiority in pancreas, prostate and "Other"; breast and kidney inconclusive. No per-basket effect sizes reported in source.
SABR-COMET randomized 99 patients across mixed histologies; STOMP and ORIOLE were prostate-only and smaller. EXTEND's contribution is scale plus histology resolution: it keeps a benefit when the prostate baskets are removed, which the prostate-only trials could not address.
The primary analysis is per-protocol rather than ITT, and an unblinded PFS endpoint in a trial that ablates the very lesions being measured favors the intervention arm. The "Other" basket is a mixed-histology pool, so its superiority signal is the hardest of the three to carry into a single phase III.
The prostate-excluded HR 0.60 is the trial's most load-bearing number, since it shows the pooled result is not simply the prostate literature reasserting itself. The ctDNA correlations (detectable at enrollment with worse PFS and survival; clearance at 3 months with better survival) point at a biological rather than anatomic definition of oligometastasis, which is the more interesting question EXTEND raises without settling.
CONSORT flow
Randomized phase II, per-protocol primary, histology-specific signals explicitly framed as hypothesis-generating for phase III. Consistent with SABR-COMET / STOMP / ORIOLE direction.
- Does MDT-driven PFS benefit translate to overall survival n=340 · primary completion 2026-11 · OLIGAMI: randomised MDT after 12wk systemic, breastactive Stereotactic Ablative Radiotherapy for Comprehensive Treatment of Oligometastatic (1-3 Metastases) Cancer Phase NAn=330 · primary completion 2030-11 · SABR-COMET-style RCT with OS as primary, 1-3 mets
- Can ctDNA select oligometastatic patients for MDT n=60 · primary completion 2027-12 · SABR cohort tracking ctDNA dynamics as biomarker
- Confirmatory phase III in pancreas oligometastatic disease recruiting Stereotactic Body Radiotherapy in Patients With Rare Oligometastatic Cancers (OligoRARE) Phase NAn=200 · primary completion 2028-08 · phase III SBRT+SOC, OS endpoint, pancreas among sitesactive SENECA: First Line metaStatic pancrEatic caNcer Primary and Distant (if Oligometastatic) lEsion direCted rAdiotherapy Phase 3n=108 · primary completion 2030-01 · randomised phase 3 SBRT vs chemo alone, 1L met pancreas
📚 Sources · 📄 1 paper
Abstract
FASTRACK II NCT02613819
ForPrimary RCC ≤10cm, T1b-dominant, medically inoperable or declined surgery
100% at 36, 60, 84 mo
ITT population, RECIST-assessed, median f/u 62 mo
TL;DR100% freedom from local progression at 36, 60, and 84mo after single-fraction 26Gy or 42Gy/3fx SABR in inoperable primary RCC.
The transferable detail is the size-adapted prescription: 26Gy in one fraction under 4cm, 42Gy/3fx above it, with median tumour 46mm and 65% T1b or higher. That is a larger-tumour cohort than most ablation series, and zero local failures out to 84mo supports offering SABR when a 77-year-old is turned down for nephrectomy.
In a medically inoperable or surgery-declining patient with a primary RCC up to 10cm, including T1b and larger where thermal ablation is a poor fit, this supports SABR as a durable local option; it does not speak to the operable patient, where nephrectomy remains untested against it. The longer read
The transferable detail is the size-adapted prescription: 26Gy single fraction under 4cm, 42Gy/3fx above it, in a cohort with median tumour 46mm and 65% at least T1b. Zero local failures to 84mo supports offering SABR when the patient is turned down for nephrectomy; bowel toxicity (two colonic obstructions) sets the technical ceiling.
This is the non-surgical arm of the small-renal-mass conversation getting real prospective follow-up, at a median tumour of 46mm where thermal ablation performs worst. It changes what you can tell a high-risk or surgery-declining patient at referral; it does not test SABR against partial nephrectomy in an operable patient, which remains unstudied.
10 details
Non-randomised phase 2, eight hospitals in Australia and the Netherlands, run by TROG and ANZUP. Enrolment July 28 2016 to Feb 27 2020; 71 enrolled, one withdrew consent before treatment. This report is the pre-planned final follow-up at a median of 62 months (IQR 60-72).
Histologically confirmed primary RCC, medically inoperable, high risk, or declined surgery, ECOG ≤2, tumours ≤10 cm, N0-N1. Median age 77 years (70-82), 49 (70%) male. Median tumour size 46 mm (37-55), with 39 (56%) T1b, six (9%) T2a and one (1%) T3a.
Size-adapted prescription: 26 Gy in a single fraction for tumours ≤4 cm, 42 Gy in three fractions 48 h apart for tumours >4 cm. Histological confirmation was required before treatment, so this is a biopsy-proven cohort rather than a radiographic-diagnosis one.
Primary: freedom from local progression by RECIST, assessed in the intention-to-treat population, as was safety.
100% local control at 36, 60 and 84 months, with no local recurrences and no cancer-related deaths reported in the cohort.
Seven (10%) patients had at least one treatment-related grade 3 event within 9 months: pain in four (6%), nausea and vomiting in three (4%), colonic obstruction in two (3%), diarrhoea in one (1%). No grade 4 events and no treatment-related deaths; no new long-term safety signals emerged with extended follow-up.
A 100% point estimate in 70 pts carries a wide confidence bound that the headline hides, and RECIST is an imperfect local-control instrument after ablative RT, where a treated mass commonly persists without viable tumour. Renal function trajectory, the endpoint that actually competes with nephrectomy, is not reported in this source.
Prior SABR evidence in primary RCC was retrospective and pooled, so a prospective multicentre dataset at 84 months is the new contribution rather than the effect size itself. Comparison to partial nephrectomy and thermal ablation remains indirect: no randomised trial has run, and this cohort was selected against surgery by definition.
The finding that transfers is durability at a tumour size where thermal ablation performs worst, with a median of 46 mm and 65% at least T1b. What it does not settle is whether SABR is a choice rather than a fallback, which needs a randomised or matched comparison in operable pts, with renal function as a co-primary.
Single-arm phase 2, N=70, inoperable or surgery-declining pts only. No randomised comparator vs partial nephrectomy or thermal ablation. Maturity gate holds despite 62mo f/u.
- SABR vs partial nephrectomy in operable pts
- Renal function trajectory after SABR vs nephrectomy
- SABR vs thermal ablation in T1b tumours
📚 Sources · 📄 1 paper
Abstract
OLIGOMA NCT04495309
ForMetastatic breast cancer, ≤5 lesions, any treatment line; mostly ER+/HER2- first-line
35.8 vs 20.4 mo
HR 0.48 (95%-CI 0.25-0.91), p=0.021
TL;DRmPFS 35.8 vs 20.4mo, HR 0.48 (0.25-0.91) p=0.021 with ablative RT to all lesions in oligometastatic breast.
The RT question here is whether ALL lesions must be treated: eligibility required ablative RT to every metastasis, and pts needing palliative RT to all sites were excluded, so this is comprehensive ablation, not selective consolidation. With 2/3 bone lesions and >80% carrying 1-3 mets, the transferable case is the low-burden bone-dominant pt. No dose or fractionation reported in source.
In ER+/HER2- metastatic breast with 1-3 mostly bone lesions starting first-line systemic therapy, this supports discussing ablative RT to all sites; it does not extend to pts with >5 lesions or those needing palliative RT to every site. The longer read
The transferable detail is the eligibility rule, not the HR: RT went to ALL metastatic lesions, and pts needing palliative RT to every site were excluded. With >80% carrying 1-3 mets and 2/3 bone, this is comprehensive ablation of low-burden disease. Dose and fractionation not reported in source.
The systemic regimen was fixed by tumor board BEFORE randomisation, so the PFS separation is attributable to RT rather than to differential drug management. Nearly three-quarters were on first-line endocrine or chemotherapy, so the question this moves is whether to pause and refer for ablation at diagnosis of oligometastatic disease, not which regimen to pick.

+3 more figures

| Arm | QLQ-C30 summary, mean (95%-CI) | Between-group change (ANCOVA) |
|---|---|---|
| Experimental | 72.2 (67.2-77.2) | -2.1 (-9.2-5.1) |
| Control | 74.3 (69.3-79.3) | n/a |


9 details 5 trials watching
Randomised trial (ARO-2021-09), systemic therapy alone vs systemic therapy plus local ablative radiotherapy to all metastatic lesions. Stratified by type of systemic therapy and treatment line. Systemic regimen was set by multidisciplinary tumor board before randomisation, so the only variable is RT.
Metastatic breast cancer, any treatment line, maximum 5 lesions. Median age 58 (experimental) vs 59 (control); ER positive 76.7% vs 81.8%, HER2 positive 7.5% vs 15.0%. Nearly three-quarters were on first-line endocrine or chemotherapy. >80% had 1-3 metastases and 2/3 of lesions were bone.
Local ablative RT was delivered to all metastatic lesions, not a selected subset. Palliative RT to symptomatic metastases was permitted, but pts requiring palliative RT to all metastases were not eligible. Dose, fractionation and technique not reported in source.
Co-primary: PFS and quality of life (EORTC QLQ-C30) at 12 weeks post-randomisation. Secondary: overall survival, toxicity, compliance, QLQ-C30 and QLQ-BR23, and patient satisfaction with cancer care (EORTC PATSAT C33).
Both co-primary endpoints read out in the trial's favour: PFS separated, and the 12-week QoL difference stayed inside the prespecified non-inferiority margin of -10 points with baseline adjustment. OS not reported in source.
Beyond the accrual shortfall, the QoL co-primary rested on n=64 of 87 randomised, and 12 weeks is too early to capture late RT toxicity in a population with a 35.8-month median PFS. Toxicity and compliance were secondary and are not reported in source.
This is the first RCT to show a PFS benefit from MDT in oligometastatic breast cancer specifically, a histology under-represented in the earlier mixed-tumour MDT randomised experience. Eight trials in the same question (TAORMINA, STEREO-SEIN, LARA, CLEAR, COSMO, ARCHER, ISTMET, OLIGAMI) are still recruiting, so the field will not settle on 87 pts.
The result establishes direction, not magnitude: an HR of 0.48 from an early-terminated trial is the estimate most likely to regress. What it does settle is the tolerability question, since short-term QoL was not degraded by treating every lesion. Which pts benefit most, by lesion count, site and systemic line, remains open.
CONSORT flow
Recruitment stopped at <20% of initial target; 87 pts, PFS CI 0.25-0.91. Positive and randomised, but underpowered against eight ongoing confirmatory trials.
- Which oligometastatic breast subgroups benefit most from MDT n=340 · primary completion 2026-11 · phase 3 MDT with subtype-specific systemic therapynot yet Adding Surgery and Radiation to the Usual Treatment for HER2-Positive Breast Cancer That Had Already Spread at Diagnosis Phase 3n=562 · primary completion 2032-05 · HER2+ de novo, 1-5 mets, SBRT added to SOC
- Does the PFS benefit translate to overall survival n=150 · primary completion 2025-08 · randomised SABR vs SOC in de novo oligomet BCn=345 · primary completion 2025-12 · TAORMINA: randomised SABR + systemic, 1-5 mets
- Optimal dose and fractionation for bone-dominant ablation recruiting OligoCare TwiCs (Trials Within Cohorts) Trial Comparing Acute Toxicity in Single-fraction vs Multiple-fraction SBRT for Metastasis-directed Treatment (SPRINT) Phase NAn=302 · primary completion 2029-02 · SPRINT: single- vs multi-fraction SBRT randomised
📚 Sources · 🐦 3 tweets
📌 Metastases-directed treatment in Patients with Oligometastatic Breast Cancer: Results from the OLIGOMA-trial (ARO-2021-09, NCT04495309) @DavidKrugMD 👏🏻 #ESTRO26 @ESTRO_RT @OncoAlert #OncoAlertAF pic.twitter.com/YDMef0fXRm
— Elisabetta Bonzano MD, PhD (@to_be_elizabeth) May 17, 2026
❗️ The OLIGOMA trial results just dropped at #ESTRO26 and they are massive. A 15-month improvement in median PFS for OMD breast cancer (HR = 0.48). This adds to the growing mountain of evidence that MDT (Metastasis-Directed Therapy) works. Lets’s go 🧵 1/n pic.twitter.com/5uiEVSYtdH
— NonsparseOncologist (@5_utr) May 17, 2026
Here are some details!
— Jeff Ryckman (@jryckman3) May 17, 2026
On OLIGOMA, nearly 3/4 were first line endocrine or chemotherapy. #ESTRO26 #OncTwitter@CJTsaiMDPhD pic.twitter.com/r3kJzNNsyK